Why The Skeleton Matters More Than You Think
Most people think of the skeletal system as just the frame that holds everything up. It does that, sure. But it's doing a lot more behind the scenes than you'd expect if you actually paid attention. I spent a few years working in anatomical illustration and biomechanics consulting, and one thing became clear fast: the skeleton is not a static structure. It's dynamic, constantly adapting to load, stress, and even hormonal signals. Miss that fact and you misunderstand practically everything about it.
What Are The Functions Of The Skeleton
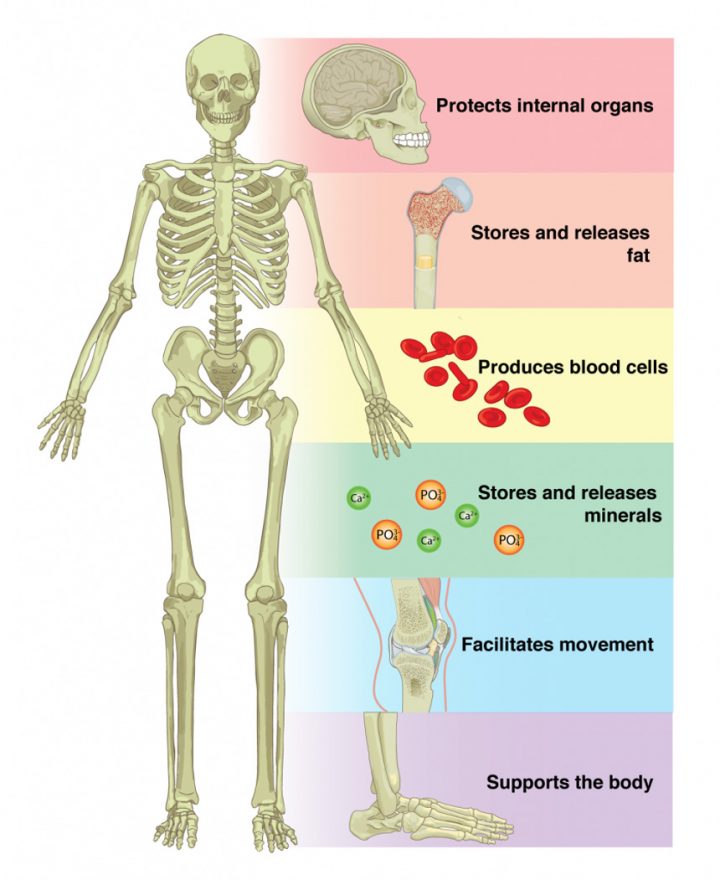
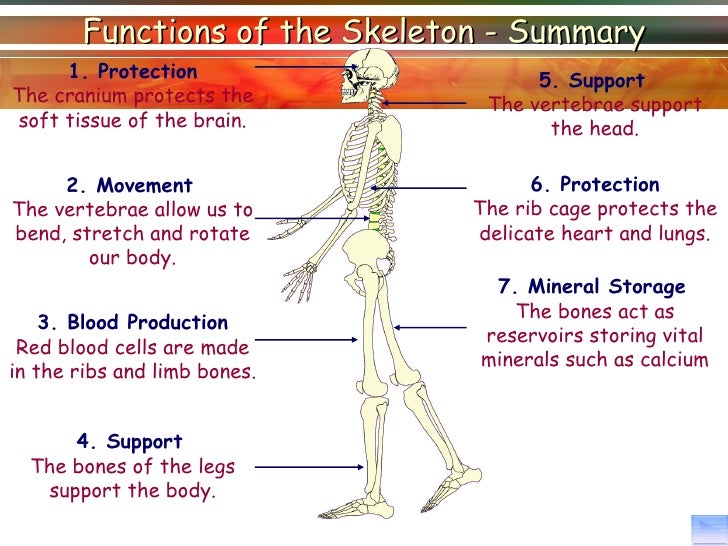
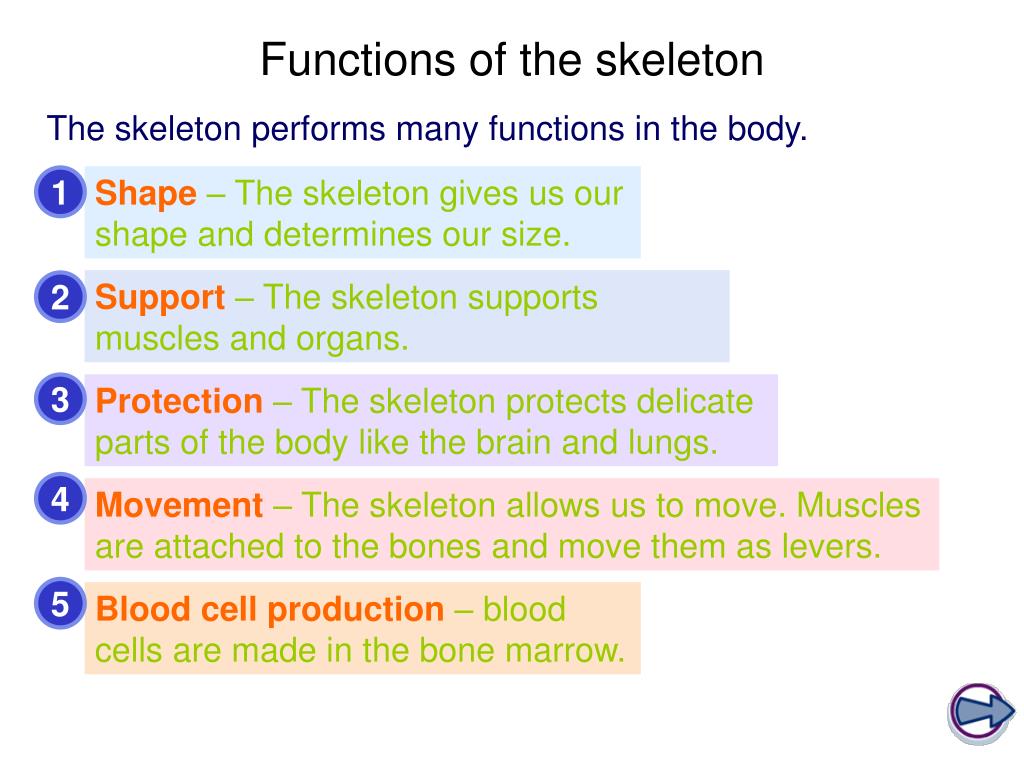
Let me just list them out plainly instead of dancing around the question. Support. The skeleton gives the body its shape and provides attachment points for soft tissues. Without it, you're a puddle. That's the most obvious function and honestly the one most people stop at. Protection. The skull protects the brain. The rib cage shields the heart and lungs. The vertebrae encase the spinal cord. These are hard-bone encasements built over millions of years of evolutionary pressure. Not elegant, but effective.
Movement. Bones act as levers. Muscles pull on them. Joints serve as fulcrums. The whole thing is a mechanical system. The lever arm of the femur, for instance, is what lets you generate enough torque to jump or sprint. Without leverage, muscle attachment would be useless. Mineral storage. About 99 percent of your body's calcium is stored in bone. Phosphate matters too. When blood levels drop, osteoclasts break down bone matrix to release minerals into circulation. This is a continuous negotiation between structural integrity and metabolic need. Blood cell production. Red marrow generates red blood cells, white blood cells, and platelets. In adults, this happens mainly in the flat bones and the proximal ends of long bones. Vertebrae, ribs, sternum, pelvis, and the femoral head are the big ones. Skull bones too, though that declines with age.
Get the Full Details

Endocrine function. Bone tissue secretes hormones. Osteocalcin, produced by osteoblasts, influences glucose metabolism and testosterone production. This is still a relatively new area of research, but it's well-established enough now that you can't ignore it. Bone is an endocrine organ.
The Mechanics Of It All
Here's where things get interesting, and where most introductory material drops the ball. Bone is living tissue. It's constantly being remodeled through a process called bone turnover. Osteoclasts resorb old or damaged bone. Osteoblasts lay down new matrix. This cycle takes about three to four months for a complete remodeled packet in cortical bone, and it never stops. I once worked on a project tracking fracture healing timelines across different age groups. The data was straightforward enough, but the real insight came from understanding that older patients weren't just healing slower — their remodeling baseline was already compromised. Chronic low-grade inflammation, reduced osteoblast activity, and diminished hormonal signals all converge to make bone turnover less efficient with age. It's not just "bones get brittle." It's a systems problem.
Another thing people routinely miss: trabecular bone and cortical bone respond to mechanical load completely differently. Trabecular bone, the spongy stuff inside vertebrae and at joint ends, is incredibly sensitive to loading patterns. It reorganizes along stress lines within weeks. Cortical bone, the dense outer shell, takes months to show measurable changes in density. If you're studying bone adaptation, you need to treat these as two separate systems with different response times. I ran into a specific edge case once where a patient had normal DEXA scan readings but was still experiencing stress fractures in the tibia. The issue was that DEXA measures areal bone mineral density and doesn't capture trabecular microarchitecture. Two-point DXA gave a false sense of security. We ended up relying on HR-pQCT (high-resolution peripheral quantitative CT) to visualize the actual trabecular structure, which revealed significant degradation that the standard scan completely missed. This is a known limitation in clinical practice but it's easy to overlook if you're only looking at BMD numbers.
Common Misunderstandings
Number one: bones are dead structures. They're not. They're highly vascularized and innervated. A fractured bone is painful because there are nerve endings in the periosteum — the connective tissue membrane covering the bone. Damage that membrane and you lose sensation, which is actually a clinical problem because it reduces the body's natural protective feedback. Number two: more bone mass always equals stronger bones. Not necessarily. Bone quality matters as much as quantity. Microarchitecture, mineralization density, collagen cross-linking, and even the degree of microdamage accumulation all factor into actual mechanical strength. A bone with high BMD but poor trabecular connectivity can be weaker than a lighter bone with good structure. Number three: the skeleton is fixed after adulthood. It's not. Peak bone mass is reached around age thirty, but remodeling continues throughout life. The rate just shifts. After midlife, resorption tends to outpace formation, particularly in women after menopause due to the drop in estrogen. Men experience a slower, more gradual decline driven largely by decreasing testosterone.
There's also the issue of bone loss in zero gravity. Astronauts lose roughly one to two percent of bone mineral density per month in space. That's roughly ten to twenty times the rate of postmenopausal bone loss on Earth. Countermeasure protocols exist — resistance exercise, pharmaceutical interventions like bisphosphonates — but they're not perfect. This is a practical limit of what we can currently do to maintain skeletal integrity in extreme environments.
Practical Takeaways
If you're studying this for a class, focus on the five core functions and understand the remodeling cycle. Those are the foundations. Everything else builds on them. If you're dealing with this from a clinical or fitness perspective, pay attention to loading. Weight-bearing exercise stimulates osteoblast activity. The mechanical strain on bone triggers signaling pathways — Wnt/-catenin is the big one — that promote bone formation. Resistance training is more effective than low-impact cardio for bone density. This isn't theory. It's been replicated dozens of times. The caveat is that exercise-induced bone gain plateaus quickly. You don't keep building bone forever by lifting heavier. The dose-response curve flattens out, and excessive loading without adequate recovery actually increases fracture risk through accumulated microdamage. There's a sweet spot, and it varies by individual. General guidelines suggest three to five sessions per week of progressive resistance training with adequate protein and vitamin D intake, but that's a starting point, not a prescription.

I've seen people push too hard on the assumption that more stimulus equals more bone. It doesn't. Bone adapts to novelty and progressive overload, but it also needs rest. Sleep, nutrition, and hormonal balance matter just as much as the mechanical signal. Neglect any of those and the skeletal response is blunted regardless of how hard you train.