Why People Get This Wrong
You open any biology textbook and you see a diagram of a skeleton with a numbered list next to it. Support. Protection. Movement. That's the baseline answer. But if you're studying for an anatomy exam, working in physical therapy, or just trying to understand what's actually happening in a living body, the list format hides a lot of the complexity. The skeletal system isn't a static scaffolding. It's metabolically active tissue that's constantly breaking down and rebuilding itself. When I was helping a student prepare for her boards, she'd memorized the six functions perfectly and still couldn't explain why a patient with prolonged immobility loses bone density at roughly 1-2% per week. She knew the list but not the mechanism. The real picture only clicks when you connect each function to the cellular machinery underneath. Osteocytes sense mechanical strain. Osteoblasts lay down matrix. Osteoclasts resorb it. Hormones shift the balance between those two processes. Without that foundation, you're just repeating terms without understanding what they mean in practice.
What Are The Skeletal System Functions
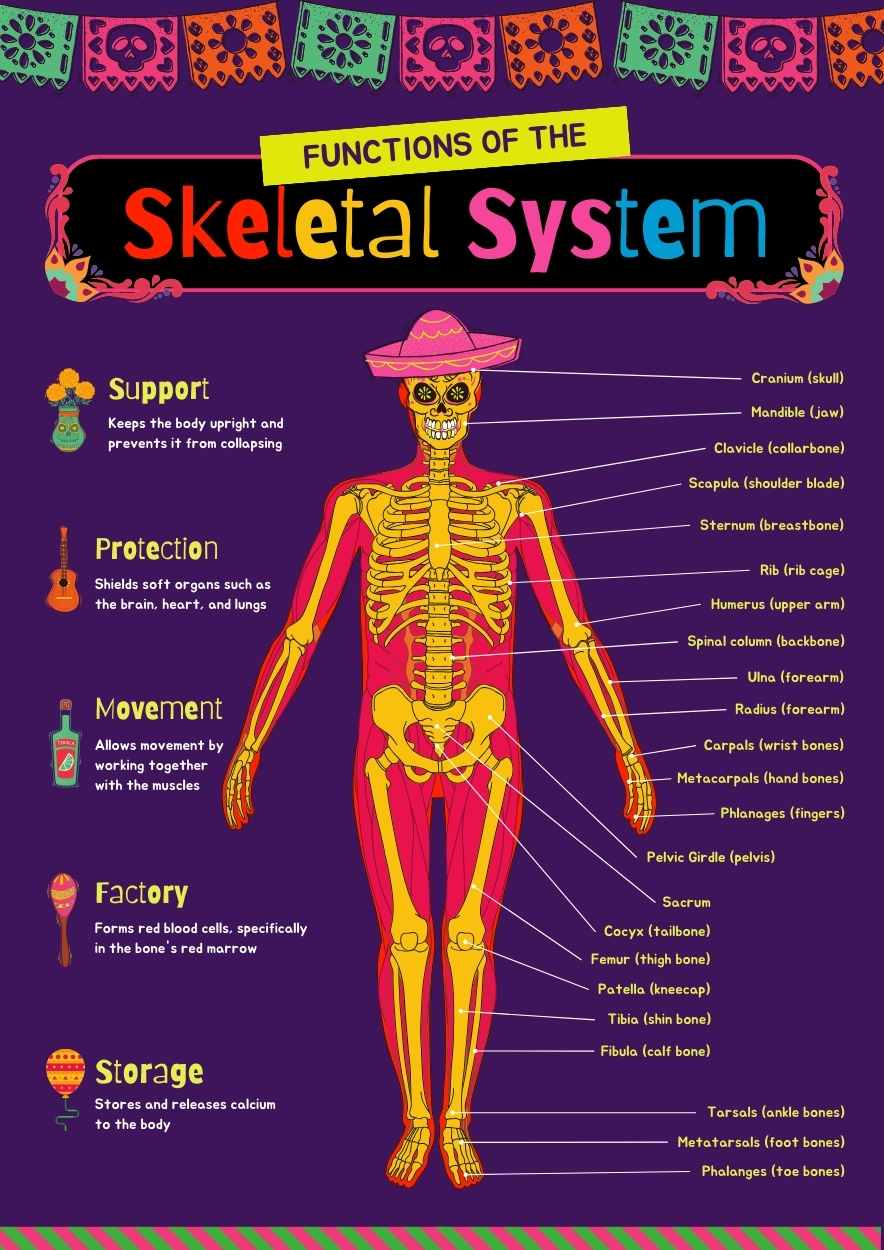
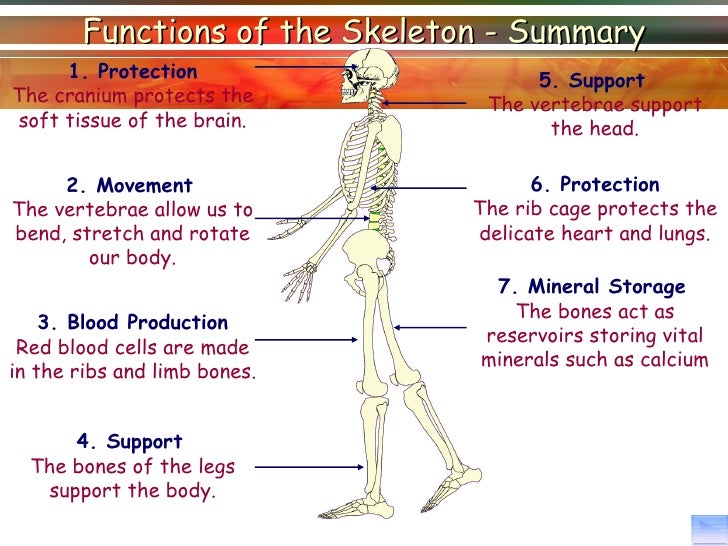
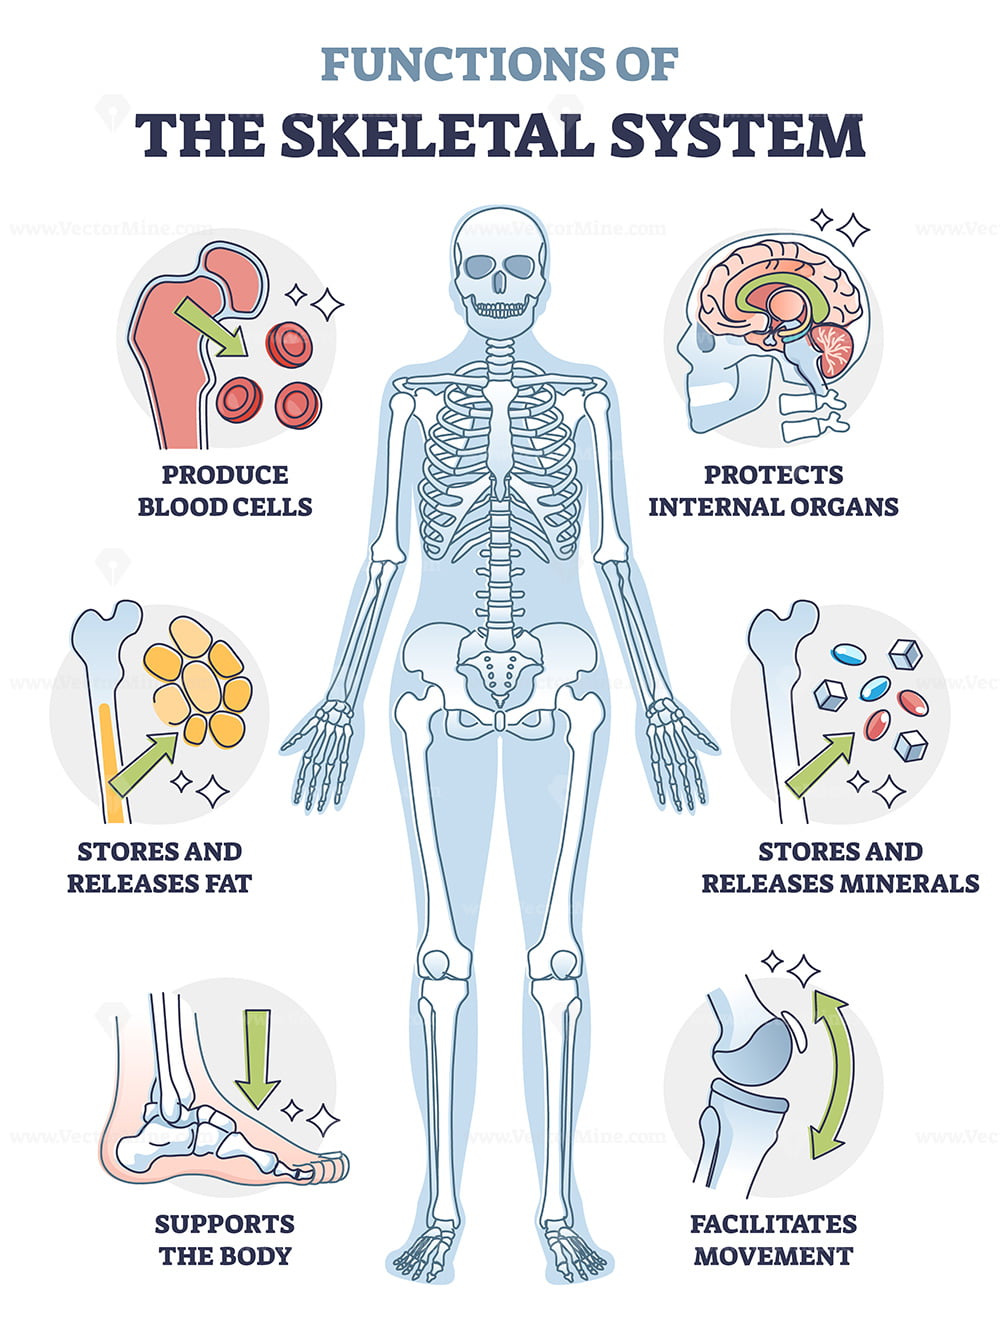
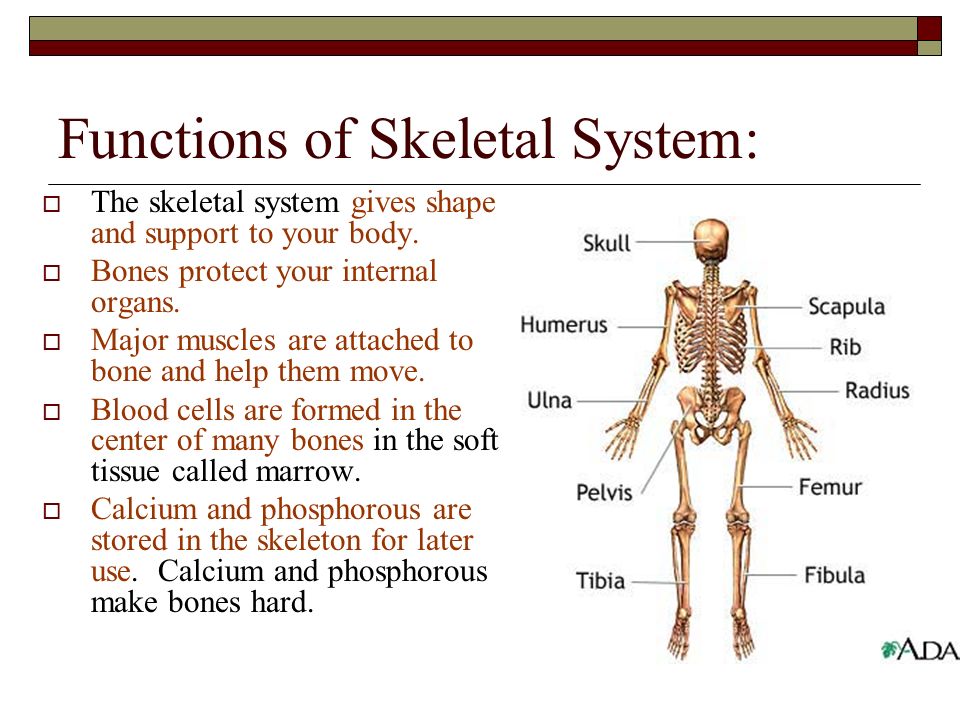
Mechanical support is the most obvious function. Your skeleton gives the body shape and provides attachment points for muscles, ligaments, and tendons. Without it, you'd be a soft shapeless mass. The axial skeleton protects internal organs while the appendicular skeleton handles locomotion. But here's something most introductory courses don't emphasize enough: the skull doesn't just protect the brain. The vertebral column also shields the spinal cord, and the rib cage guards the heart and lungs. Each bone serves multiple purposes simultaneously. Mineral storage is where things get interesting. About 99% of the body's calcium and 85% of its phosphorus are stored in bone tissue. When blood calcium drops, parathyroid hormone signals osteoclasts to resorb bone and release calcium into circulation. This isn't a passive process. It's a tightly regulated feedback loop that can shift mineral balance in minutes. I remember reading a case study where a patient with hyperparathyroidism had serum calcium levels so high they were causing kidney stones, cognitive changes, and cardiac arrhythmias. The bones weren't just storing minerals anymore. They were actively hemorrhaging them into the bloodstream. Hematopoiesis refers to blood cell production, which happens in the red marrow of certain bones. In adults, this is primarily the pelvis, sternum, vertebrae, ribs, and skull. The femur and humerus contribute too, but less so in later years as yellow marrow replaces red marrow. A common pitfall is assuming that any bone can produce blood cells. It can't. Marrow space occupancy matters, and conditions like myelofibrosis or certain cancers crowd out hematopoietic tissue, leading to anemia and immune suppression.
Endocrine function is the part most people skip. Bone tissue secretes osteocalcin, a hormone that influences glucose metabolism and fat deposition. It also plays a role in male fertility. Researchers found that male mice lacking osteocalcin had reduced sperm production. In humans, lower osteocalcin levels correlate with type 2 diabetes risk. This isn't textbook-level detail you'll find in every resource, but it's well established now. Bone is an endocrine organ. It communicates with other tissues through signaling molecules, not just structural support. I spent time troubleshooting a lab scenario once where students were asked to predict blood calcium levels after a parathyroidectomy. Almost everyone guessed incorrectly because they didn't account for the fact that without PTH, calcium resorption from bone stops almost entirely, and vitamin D activation drops, reducing intestinal calcium absorption. The result is hypocalcemia, sometimes severe enough to cause tetany within hours. Understanding the interplay between these systems is what separates someone who memorizes from someone who actually knows the material. Acid-base balance is another function people rarely mention. Bone acts as a buffer. When blood pH drops, hydroxyapatite crystals in bone release alkaline salts that neutralize excess hydrogen ions. It's a slow process compared to chemical buffers in the blood, but over hours or days it matters. Chronic metabolic acidosis from conditions like untreated renal failure can actually leach bone mineral over time, contributing to osteoporosis even without other risk factors.
Get the Full Details
How These Functions Interact in Real Bodies
The skeletal system doesn't operate in isolated boxes. Every function feeds into the others. Weight-bearing exercise stimulates osteoblast activity, which improves mineral density, which in turn supports better movement mechanics. Blood cell production requires adequate iron and B vitamins, which come from diet and are absorbed with help from stomach acid and intrinsic factor. Mineral storage depends on vitamin D, which the skin synthesizes from sunlight and the kidneys activate. Break any link in that chain and the whole system shows it. Osteoporosis is the clearest example of systemic failure. It's not simply "weak bones." It's an imbalance where resorption outpaces formation across the entire skeleton. Postmenopausal women are at higher risk because estrogen loss accelerates osteoclast activity. Men experience a slower decline in testosterone, so the rate of bone loss is typically more gradual. But the mechanism is the same. Microarchitectural deterioration reduces mechanical strength, and minor falls that would never fracture a healthy skeleton can cause hip or vertebral compression fractures in someone with significant osteoporosis. Another thing worth noting: the spine is both a protective structure and a weight-bearing column, which creates a unique vulnerability. Vertebral bodies are made of cancellous bone, which has a high surface area and remodels quickly. That's good for metabolism but makes these segments prone to collapse under compressive loads when bone quality declines. The nerves running through the spinal canal add urgency to any fracture in that region.
Practical Limitations You Should Know About
For all its sophistication, the skeletal system has real bottlenecks. Bone remodeling is energy-intensive. During calorie restriction or malnutrition, the body prioritizes vital organ function over bone maintenance. That's why eating disorders like anorexia nervosa are so destructive to skeletal health. Low body weight reduces mechanical loading on bones, and hormonal disruption from starvation impairs osteoblast function. The combination is brutal. Age is another hard constraint. Peak bone mass is reached around age 30. After that, you're slowly losing ground unless you intervene with exercise, nutrition, or medication. No amount of calcium supplementation reverses the natural decline. Exercise and resistance training provide the mechanical stimulus that tells your body to maintain bone. Without that signal, extra calcium just circulates in your blood until your kidneys filter it out. Bone density scans (DEXA) measure what they measure, but they don't capture everything. Two people can have the same T-score and very different fracture risks because bone quality involves microarchitecture, mineralization patterns, and collagen integrity, not just mineral content. Research into bone quality assessment is ongoing, but routine clinical practice still relies heavily on DEXA. If your scan shows osteopenia, don't panic. It's a warning sign, not a sentence. But don't ignore it either. The window where lifestyle changes matter most is between normal bone density and established osteoporosis.