Understanding the Progression of Lewy Body Dementia
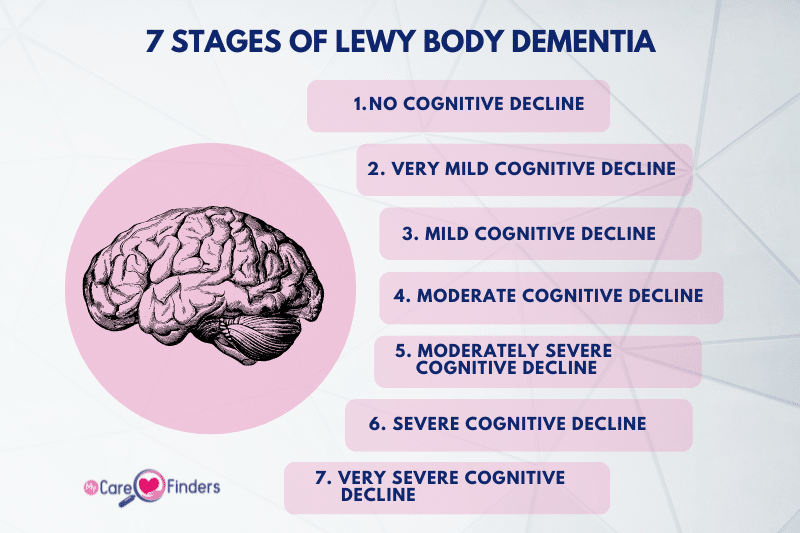
Most people get handed a diagnosis and immediately start looking for stages online. What they find is a mix of staging systems that don't align well with each other. The reality is messier than any chart. I've spent years working with families navigating this disease, and the staging frameworks available are useful as rough guides but fail at predicting anything close to individual trajectories. People in the same stage can look radically different depending on what subtype of LBD they have, what comorbidities they carry, and how well their autonomic nervous system is coping. There isn't one universally accepted staging system for LBD. That's the first thing to understand. The most commonly referenced framework comes from the Clinical Diagnostic Criteria for DLB, which categorizes patients into mild, moderate, and severe dementia based on functional ability and cognitive testing. Then there's the Lubel-Staging Scale used primarily in research settings, and the Global Deterioration Scale adapted for use with LBD populations. None of them map perfectly onto what actually happens day to day. Mild stage typically involves noticeable cognitive fluctuations and early parkinsonian features. Motor symptoms might not yet be prominent enough for a full Parkinson's diagnosis. People can often still drive, manage finances with effort, and maintain some independence in activities of daily living. But the fluctuations are there. A patient might perform within normal range on a morning MMSE and then require help with basic tasks the same afternoon because their attention has shifted inward.
Moderate stage is where the real complexity shows up. Cognitive decline becomes consistent rather than fluctuating, which is actually worse in some ways because caregivers lose the good days. Motor symptoms are clearly established now. Gait becomes festinating or unstable. Swallowing issues start appearing in some patients. REM sleep behavior disorder often intensifies, sometimes leading to injuries. Hallucinations tend to become more persistent and visually detailed. Medication management becomes a daily negotiation between neurologists, caregivers, and pharmacy limitations. Severe stage involves near-total dependence. Speech may be reduced to single words or lost entirely. Patients are usually non-ambulatory. Aspiration risk is high. This is where pneumonia and other infections become the primary threats to survival. Average survival from diagnosis is around five to seven years, though some patients live considerably longer. Younger onset cases can progress differently, sometimes slower in motor terms but faster in certain cognitive domains. I encountered a case last year where the staging completely broke down. A patient in what should have been moderate-stage LBD based on cognitive testing was managing a small vegetable garden, reading, and living alone with minimal assistance. But his dysautonomia was devastating. Blood pressure drops were so severe he couldn't stand for more than ten minutes without collapsing. The cognitive scales said one thing. His actual daily functioning said something entirely different. I had to rewrite care plans three times in two months because the standard staging tools weren't capturing what was actually happening. The workaround was combining the MoCA for cognition, the UPDRS for motor, and the DISAS for autonomic dysfunction into a single tracking document. It took extra work every visit but it actually predicted what came next.
Here's something most patient education materials don't mention clearly enough. The visual-spatial and perceptual deficits in LBD often worsen before memory does. This is the opposite of Alzheimer's, and it means standard cognitive screening tools miss early LBD consistently. A patient can pass a clock drawing test while being completely unable to navigate a familiar grocery store. The mini-mental state exam has a documented sensitivity of about 58% for LBD compared to 91% for Alzheimer's. That gap matters when you're trying to stage someone accurately. Another counter-intuitive point is that medication sensitivity isn't just a side effect concern. It's a diagnostic and staging marker. Up to half of LBD patients show severe neuroleptic sensitivity, and this tends to appear earlier and more intensely than in Parkinson's disease dementia. I've seen patients who were labeled treatment-resistant depression because antipsychotics triggered catastrophic reactions. The reaction itself becomes part of the staging picture. If a patient responds to a low-dose quetiapine challenge with significant improvement in hallucinations without severe sedation or motor worsening, they're likely earlier stage. If the same dose causes acute dystonia or near-syncope, the disease burden is higher than the cognitive scores suggest. The stages I've described are linear. LBD doesn't progress linearly. Patients have stepwise declines followed by plateaus that last months. A fall causing a hip fracture can drop someone two stages overnight due to deconditioning and delirium. Infections do the same thing. A urinary tract infection that would send an Alzheimer's patient mildly confused for three days can leave an LBD patient at their lowest functional level for two weeks. These acute on chronic events are where the staged model fails most visibly.
Get the Full Details

If you're tracking progression for yourself or a loved one, don't rely on any single tool. Use the MoCA, track motor symptoms with the UPDRS Part III if you can get a copy of the rating sheet, and keep a daily log of fluctuations, hallucinations, and sleep disturbances. The log is more valuable than any clinical assessment done once every six months. Neurologists see patients at their best during appointments. The fluctuations happen elsewhere. Having written records of those patterns is the difference between accurate staging and guessing.