Understanding Behavioral Disorders: What Actually Happens
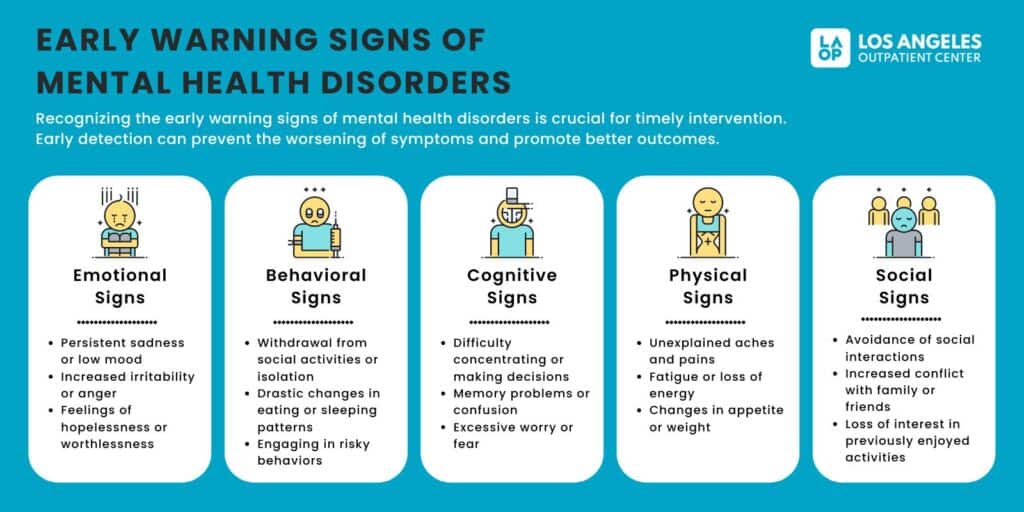
Behavioral disorders are a broad category, and most people lump everything together. That's the first problem. What Are The Symptoms Of Behavioral Disorders isn't a single checklist you can apply to anyone. It's a spectrum of conditions where behavior deviates from expected norms for age, development, and culture. The DSM-5 organizes them, but even that system is messy in practice. The most common behavioral disorders fall into a few buckets. Conduct Disorder involves repeated violation of others' rights or societal norms—aggression, destruction of property, deceitfulness, serious rule breaking. Oppositional Defiant Disorder is shorter in scope but more frequent: chronic anger, argumentative behavior toward authority figures, deliberate annoyance of others, and blame-shifting. ADHD, while technically neurodevelopmental, shows up as behavioral symptoms everywhere. Impulsivity, inattention, hyperactivity—they disrupt functioning in school, work, and relationships. Then there are the less discussed ones. Intermittent Explosive Disorder involves recurrent impulsive aggressive outbursts that are grossly disproportionate to the situation. Reactive Attachment Disorder stems from severe early neglect and shows up as emotionally withdrawn behavior with minimal social responsiveness. Disinhibited Social Engagement Disorder is the flip side—overly familiar behavior with strangers, lack of appropriate boundaries.
How These Manifest in Real Settings
I worked with a kid who came in labeled ODD. Classic presentation on paper. Defiant, argumentative, couldn't sit still, blew up at teachers. But when we actually sat down and looked at the history, he'd been moved through six foster homes by age nine. What looked like oppositional behavior was actually trauma response. The aggression wasn't defiance—it was hypervigilance disguised as hostility. Treating it as pure ODD would have been a mistake. We ended up with attachment-focused therapy and medication for the underlying anxiety, and the "oppositional" behaviors dropped significantly within three months. The point is that symptom overlap is massive. Aggression appears in Conduct Disorder, ODD, PTSD, bipolar disorder, and ADHD. Blaming everyone on willpower ignores how much neurobiology is involved. A child with ADHD isn't choosing to be disruptive. The prefrontal cortex literally struggles to regulate impulses. That's not an excuse—it's a mechanism. Understanding the mechanism changes how you approach treatment.
Red Flags That Warrant Professional Evaluation
School refusal isn't always behavioral. Sometimes it's the visible symptom of an underlying disorder. When a child's behavior changes dramatically—whether escalation or withdrawal—after a certain age threshold, that's worth investigating. Age matters enormously. Some behaviors are normal at three and pathological at thirteen. Tantrums in a toddler are developmentally expected. Same behavior in a ten-year-old? Different conversation entirely. Here's what most people miss. Duration and impairment. A behavior has to be persistent—typically six months or more—and it has to cause significant impairment in at least two settings. Home and school. Work and home. If someone is struggling only in one environment, you need to look at that environment before you label the person. I've seen kids misdiagnosed because the school was under-resourced and the teacher was overwhelmed. The kid wasn't the problem. The setting was.
Get the Full Details

Common Pitfalls in Assessment
Cultural bias is huge and underacknowledged. Behaviors that are normative in one cultural context get pathologized in another. Direct eye contact might be respectful in some families and defiant in others. Physical expressiveness varies wildly across cultures. A clinician who doesn't understand that will overdiagnose. I once reviewed a case where a Southeast Asian child was flagged for Conduct Disorder because he didn't make eye contact with adults and spoke softly. In his culture, that's proper respect. The diagnosis was wrong, and the family was terrified. Another pitfall is conflating mood disorders with behavioral ones. Bipolar depression in children can look exactly like oppositional behavior. Irritability is the primary symptom, not euphoria. Kids with bipolar don't always present with the classic manic episodes adults show. They present as constantly angry, impossible to reason with, and unable to regulate emotion. Without a thorough mood assessment, you end up treating the wrong thing.
Treatment Approaches That Actually Work
For Conduct Disorder and ODD, Parent Management Training is the gold standard. Not because parents are doing anything wrong, but because changing the response pattern at home breaks the cycle. The child learns that certain behaviors no longer produce the expected reaction. It's operant conditioning applied systematically. Studies show meaningful improvement in about 60-70% of cases when parents are consistent. Medication plays a role but it's rarely standalone. Stimulants for ADHD-related behavioral symptoms. Atypical antipsychotics like risperidone for severe aggression in Conduct Disorder, though the side effect profile is significant. SSRIs when anxiety or depression is comorbid. The key is matching the intervention to the primary diagnosis, not layering medications on a misdiagnosis. For trauma-related behavioral disorders, talk therapy alone often fails. EMDR and trauma-focused CBT have better outcomes because they address the root cause rather than just managing symptoms. I worked with a teenager who'd been in foster care since age four. His conduct issues were severe—arson, animal cruelty, threats against peers. Standard behavioral contracts did nothing. Once we addressed the attachment trauma, the behaviors decreased substantially. You can't behavior-modify your way out of trauma.
What Doesn't Work
Scare tactics. Tough love programs. Boot camps. Those approaches assume the behavior is willful defiance and the cure is more punishment. That's backwards for almost every behavioral disorder. Punishment without addressing the underlying cause tends to escalate symptoms, especially in trauma-affected kids. The research is clear on this, but some programs keep getting funded because they sound tough. Another failure mode is relying solely on school-based interventions. A teacher can't provide the dosage of therapy a kid needs. Individual or family therapy, consistent parenting strategies at home, and sometimes medication management are all necessary pieces. Schools can accommodate and support, but they shouldn't be expected to treat. The hardest truth is that outcomes vary enormously. Some kids improve dramatically with the right intervention. Others don't, and the reasons are complex—co-occurring conditions, family instability, lack of access to quality care, sheer severity of the disorder. There's no universal fix, and pretending otherwise does real harm.