Understanding Muscle Types From the Ground Up
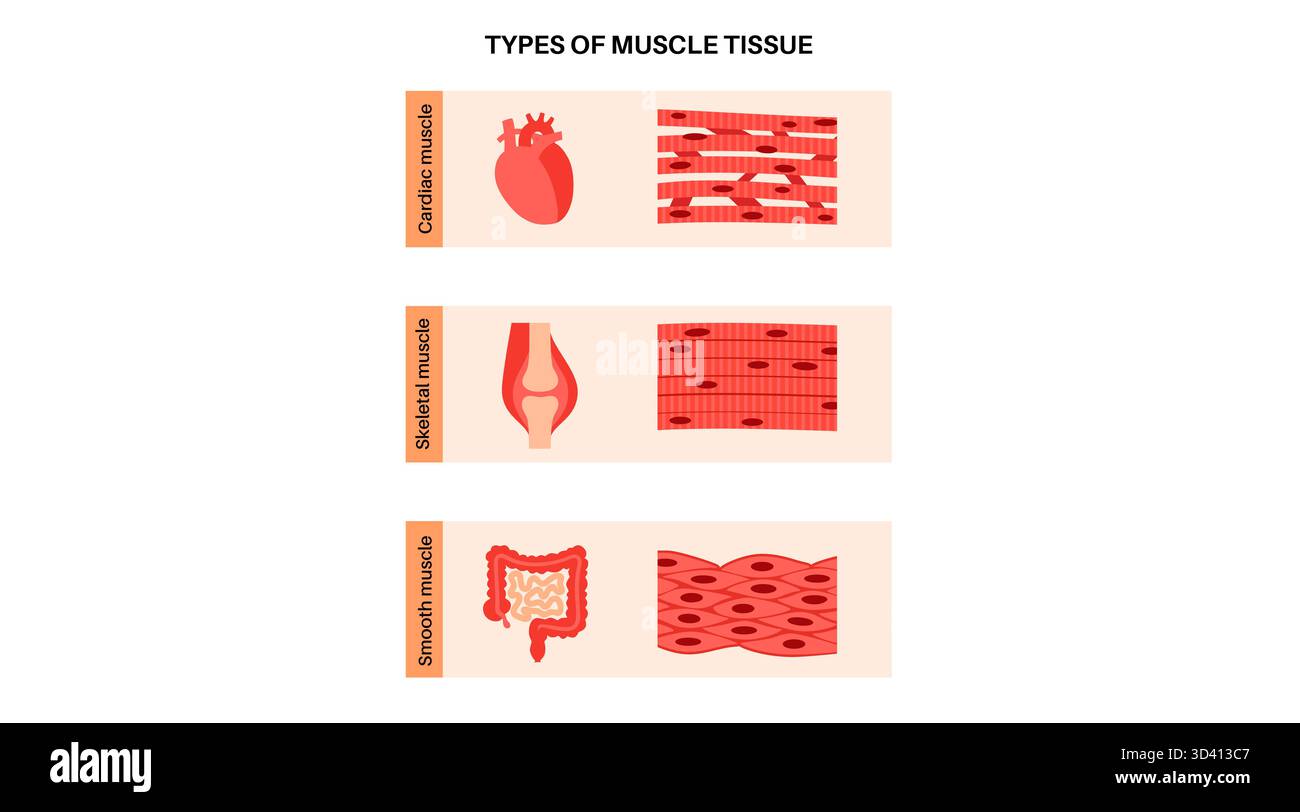
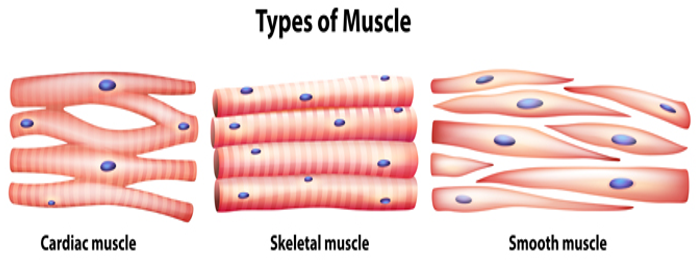
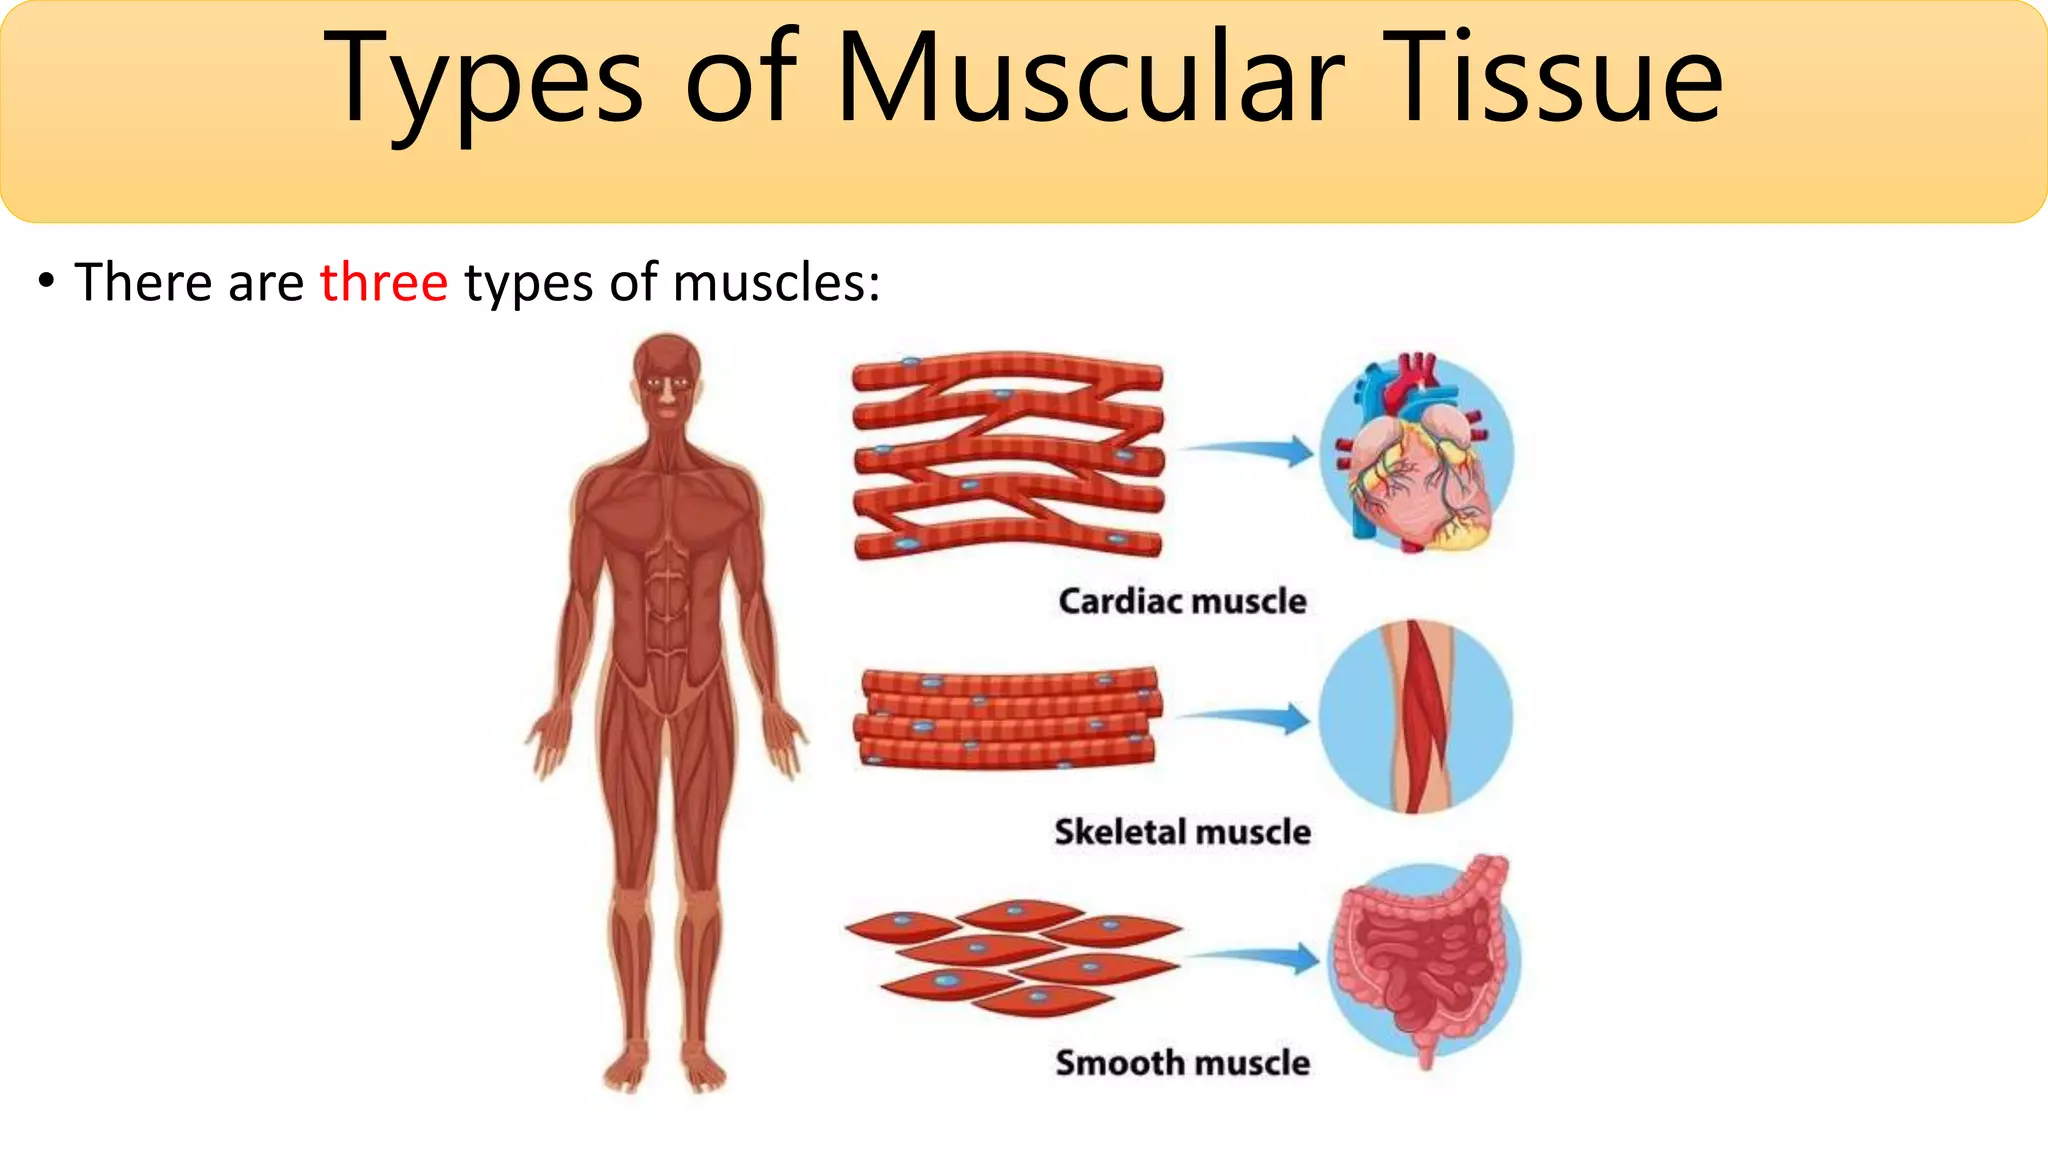
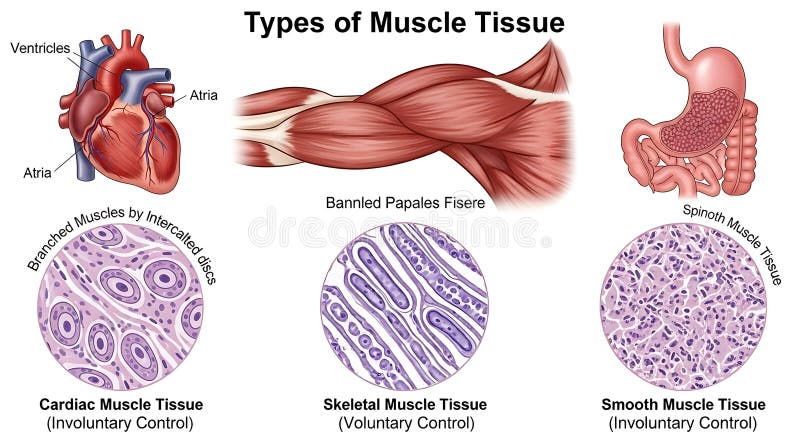
Most people learning about the human body encounter the three types of muscle at some point. They are skeletal muscle, smooth muscle, and cardiac muscle. These classifications aren't arbitrary — they're based on structure, control mechanism, and location. I learned this the hard way during an early career phase when I was coaching athletes through a rehabilitation program and noticed something most beginners miss: people assume "muscle" means one thing. It doesn't. Training the wrong type of muscle tissue with the wrong protocol can actually delay recovery by weeks. Skeletal muscle makes up the bulk of what you see when you look at your own arms or legs. It's striated — meaning under a microscope it shows alternating light and dark bands — and it's voluntary, which means you consciously control it. A single skeletal muscle fiber is multinucleated, formed from the fusion of myoblasts during development. Each fiber runs the length of the muscle, and the whole unit is wrapped in connective tissue called epimysium. When you lift a weight, action potentials travel down motor neurons to the neuromuscular junction, acetylcholine is released, and the sarcomeres inside those fibers shorten. That's the basic mechanism. Nothing mystical about it. Smooth muscle lives in the walls of hollow organs — blood vessels, the digestive tract, the bladder, the uterus. It's also striated-less, non-voluntary, and its cells are spindle-shaped with a single nucleus. Unlike skeletal muscle, smooth muscle doesn't rely on the same fast-twitch or slow-twitch fiber classification. Instead, it uses latch-bridge mechanisms that allow it to maintain contraction for long periods with very little ATP expenditure. I remember working with a client who had chronic gastrointestinal dysmotility, and understanding smooth muscle pharmacology — how agents like calcium channel blockers or anticholinergics affect contraction — was the difference between sending them to the wrong specialist and actually solving the problem. Gastroenterologists understand this tissue type better than anyone.
Cardiac muscle is its own category entirely. It's striated like skeletal muscle but involuntary like smooth muscle, and it has unique features like intercalated discs with gap junctions that allow electrical coupling between cells. The heart doesn't just contract — it maintains a self-generated rhythm through the sinoatrial node. There's a common misconception that cardiac muscle can regenerate significantly after a heart attack. It can't. Cardiomyocyte turnover is roughly 1% per year at age 20 and drops to near zero by middle age. Most of what repairs the infarcted area is fibrotic scar tissue, not new muscle. That's clinically important because it explains why heart failure after a large MI is often progressive rather than stable.
Why The Distinction Actually Matters In Practice
I've seen too many trainers and even some healthcare providers treat all muscle as interchangeable. They're not. If you're designing a conditioning program, the fiber type composition of skeletal muscle matters enormously. Type I (slow oxidative) fibers are fatigue-resistant, rich in mitochondria and myoglobin, and suited for endurance. Type IIx (fast glycolytic) fibers generate high power but fatigue quickly. Type IIa sits somewhere in between. Your training stimulus determines which fibers you recruit and adapt. Heavy resistance training shifts fiber characteristics toward more Type IIa. Ultra-endurance work increases mitochondrial density in Type I fibers. Here's a practical example from my experience. A client came in with plantar fasciitis that wasn't resolving despite standard stretching and ice protocols. The issue was that her tibialis posterior — a skeletal muscle responsible for arch support — had developed significant eccentric weakness from years of poor running mechanics. Treating the fascia directly was like putting a bandage on a structural problem. We shifted to heavy slow resistance work for the lower leg musculature, specifically focusing on the tibialis posterior and peroneals, and the plantar fasciitis resolved in about six weeks where nothing else had touched it. The fascial pain was a symptom, not the cause. Another area where the distinction breaks down in public understanding is smooth muscle dysfunction. People don't realize that something like hypertension is fundamentally a smooth muscle problem — the vascular smooth muscle in arterial walls becomes hyperreactive or structurally remodeled, increasing peripheral resistance. Taking a calcium channel blocker directly targets L-type calcium channels in smooth muscle cells, reducing their ability to contract. That's a completely different mechanism than what happens when you take a beta-blocker, which affects cardiac muscle primarily. Understanding which tissue type is involved in a pathology changes which drugs you'd reach for first.
Get the Full Details
A Few Things Textbooks Don't Emphasize Enough
One thing that trips people up is the concept of muscle plasticity. Skeletal muscle can shift fiber type properties, but there's a hard ceiling. You can't convert someone into a pure sprinter or a pure marathoner through training alone because their baseline Type II fiber percentage is largely genetically determined. Elite sprinters typically have 75-80% Type II fibers in their quadriceps. Elite distance runners sit closer to 70-75% Type I. Training works within those constraints, not beyond them. Cardiac muscle has its own plasticity, but it's asymmetrical. The heart hypertrophies in response to volume overload (eccentric hypertrophy, like in swimmer's heart) and pressure overload (concentric hypertrophy, like in hypertension). Both are adaptive initially, but concentric hypertrophy from chronic uncontrolled high blood pressure is pathologic and leads to diastolic dysfunction. The wall thickens, the chamber size stays the same or shrinks, and filling becomes impaired. This is a distinction that cardiologists spend considerable time teaching residents about, and it's something primary care providers sometimes overlook until the patient presents with heart failure symptoms. Smooth muscle has a property called tonicity that's rarely discussed outside of physiology courses. Some smooth muscle, like the myogenic tone in arterioles, maintains a baseline level of contraction without any neural or hormonal input. This is crucial for maintaining blood pressure and regional blood flow distribution. When that tonic contraction goes awry — as in vasospastic angina or Raynaud's phenomenon — the result is sudden, dramatic reduction in blood flow. Nitroglycerin works by donating nitric oxide to vascular smooth muscle, causing relaxation and vasodilation. It's a direct pharmacological intervention on smooth muscle physiology, not some generic "blood vessel opener."
Where This Knowledge Falls Short
The biggest limitation in how these three muscle types are taught is that it creates artificial boundaries. In reality, there's overlap. Some smooth muscle-like properties exist in specialized skeletal muscle contexts, and the autonomic nervous system blurs the line between voluntary and involuntary control in ways that textbooks rarely capture. Aerobic training, for instance, improves cardiovascular function by affecting all three tissue types simultaneously — cardiac output increases, vascular smooth muscle responsiveness improves, and skeletal muscle oxidative capacity rises. Isolating one type in your thinking gives you an incomplete picture of physiological adaptation. Another blind spot is the role of connective tissue. Muscle doesn't exist in isolation. Tendons, fascia, and the endomysium-perimysium-epimysium continuum all transmit force. When a muscle fiber contracts, that force has to travel through multiple layers of connective tissue before it moves a bone. Damage or stiffness in any of those layers — which happens frequently in repetitive strain injuries — changes how the muscle functions regardless of its fiber type composition. I've seen physiotherapists miss this entirely and chase the "muscle" when the problem was fascial restriction. Finally, the aging process affects all three types differently. Skeletal muscle mass declines roughly 1-2% per decade after age 30, accelerating after 60. Smooth muscle in blood vessels becomes stiffer due to collagen deposition and reduced nitric oxide bioavailability, contributing to age-related hypertension. Cardiac muscle undergoes concentric remodeling with reduced compliance. These aren't separate problems — they're interconnected changes that compound each other. An older adult with sarcopenia, arterial stiffness, and diastolic dysfunction is dealing with the cumulative effect of all three muscle types aging in parallel.