The Small Intestine Breakdown
Most people know the small intestine is one long tube, but it's actually divided into three distinct regions, each with its own job. You might see them memorized for an exam, but the reality on the table or in clinical work is more nuanced than the textbook versions suggest.What Are Three Sections Of The Small Intestine
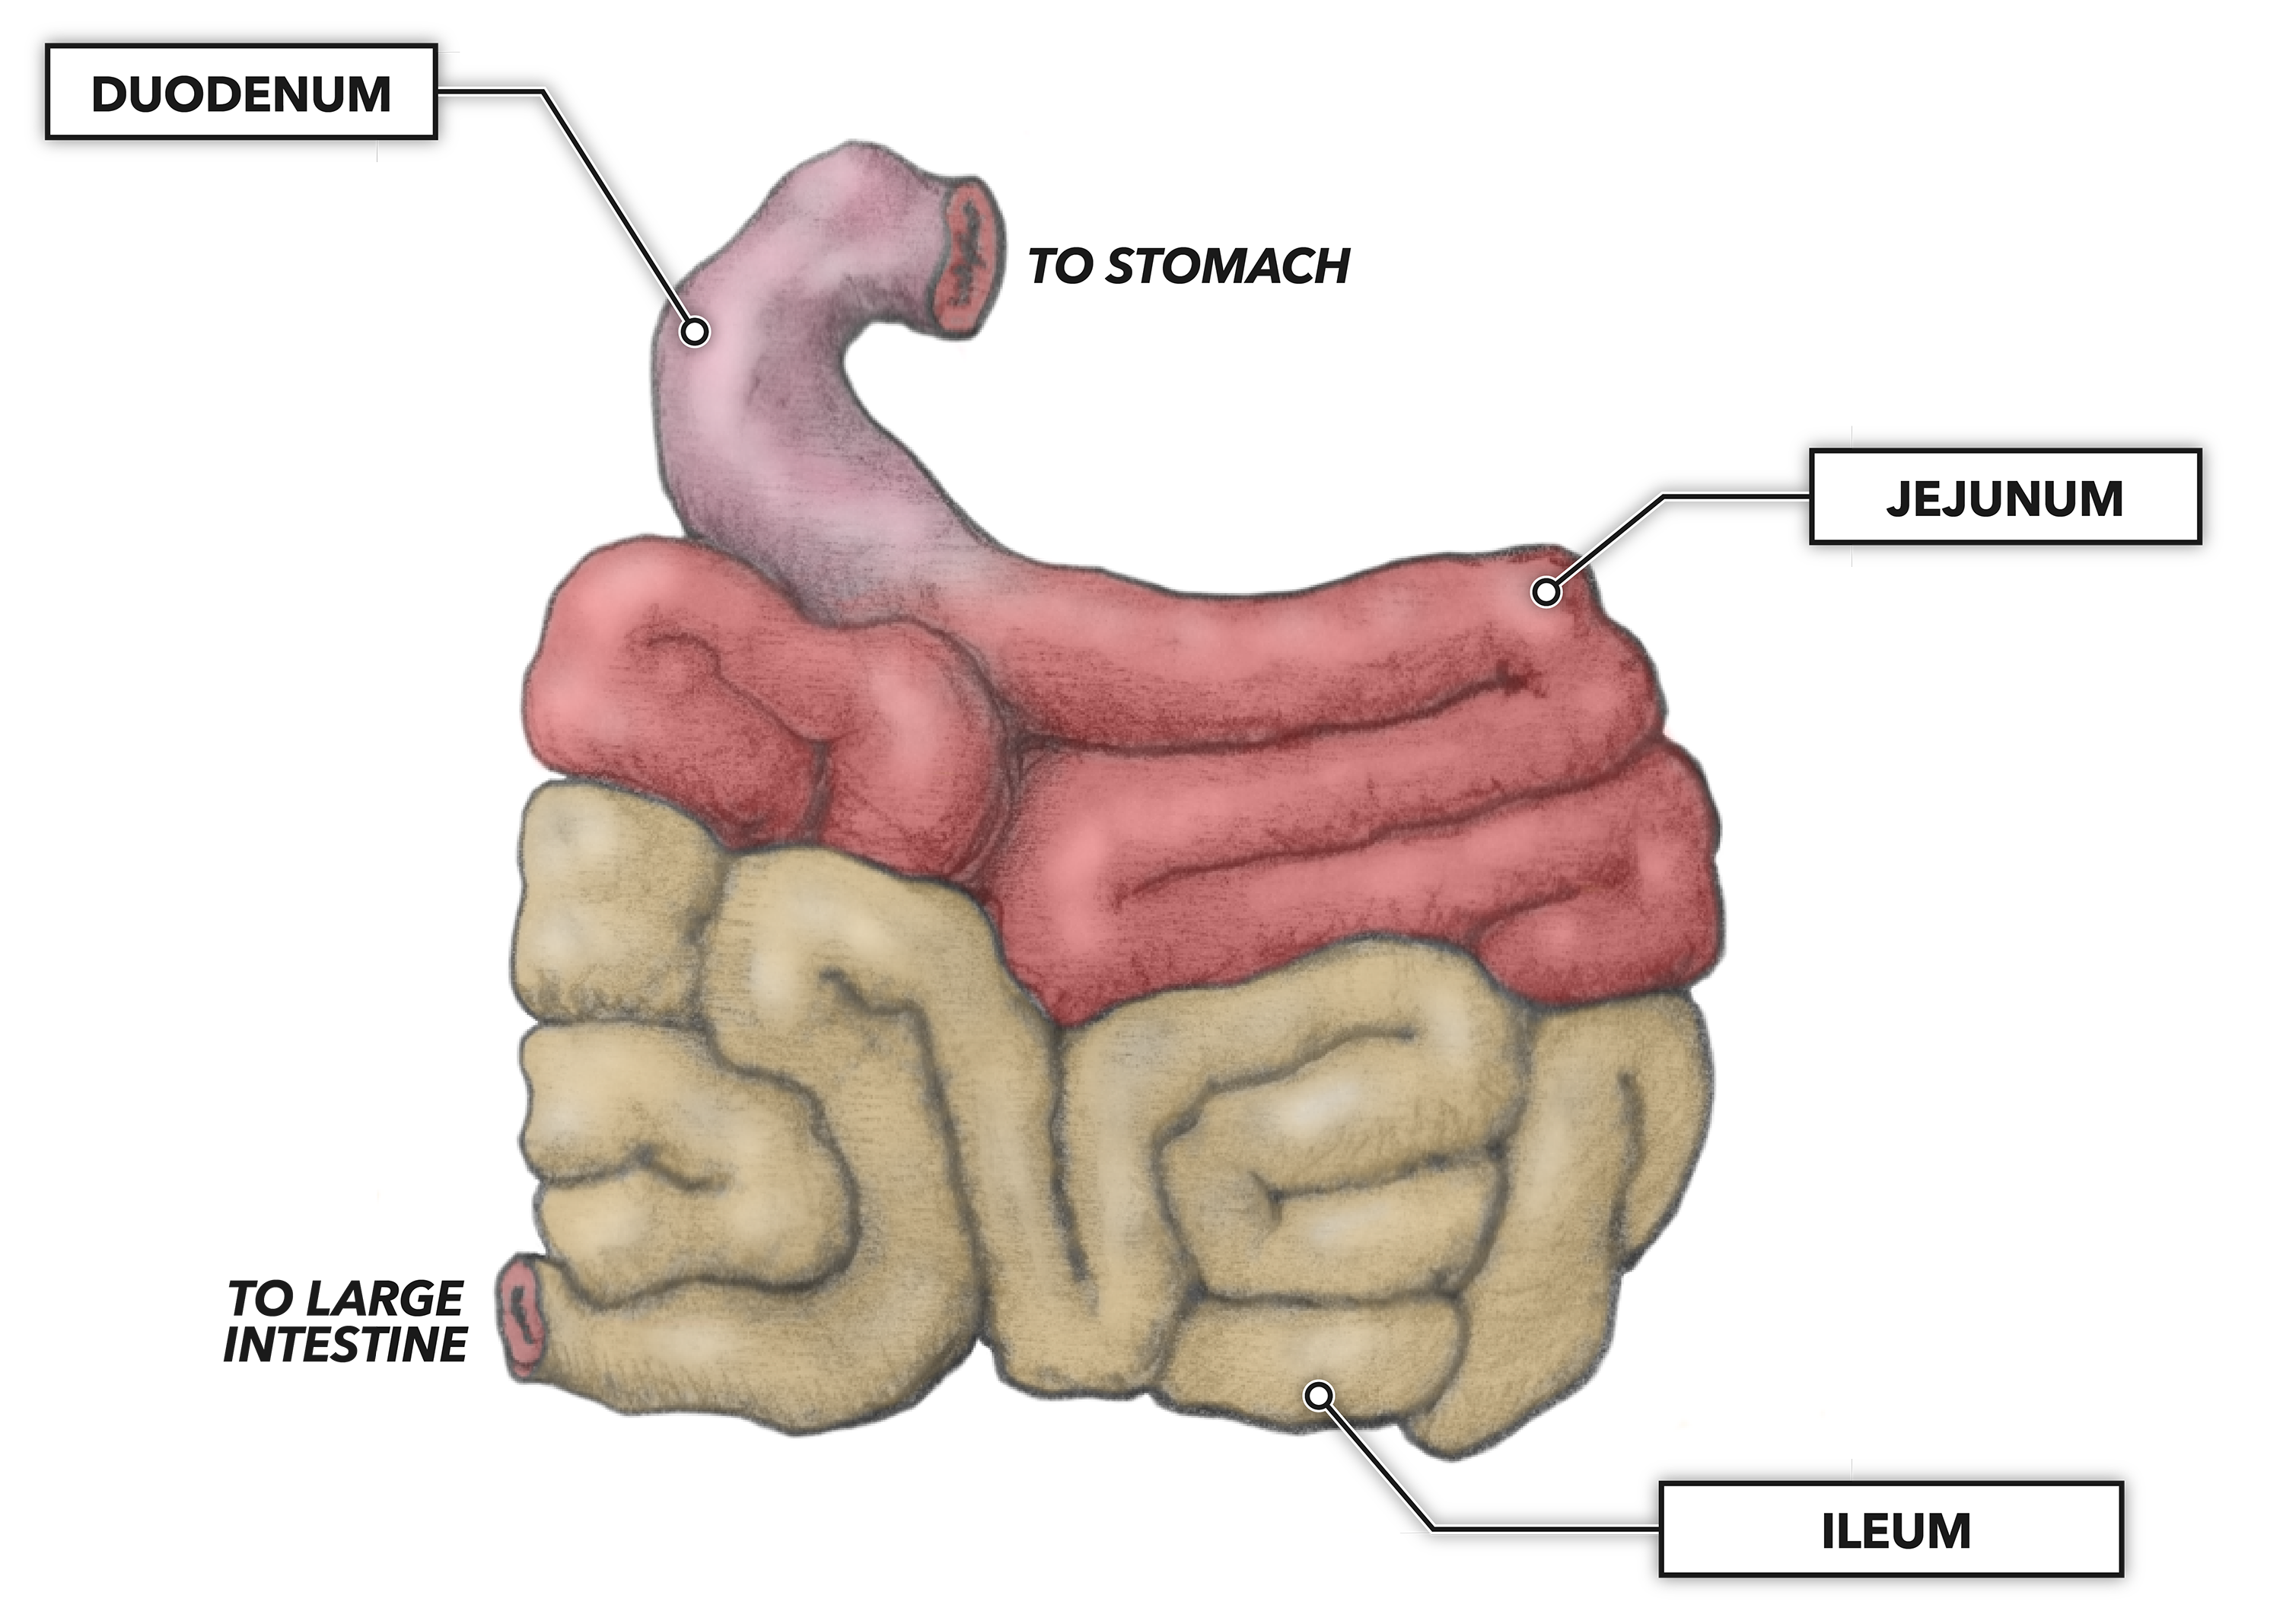
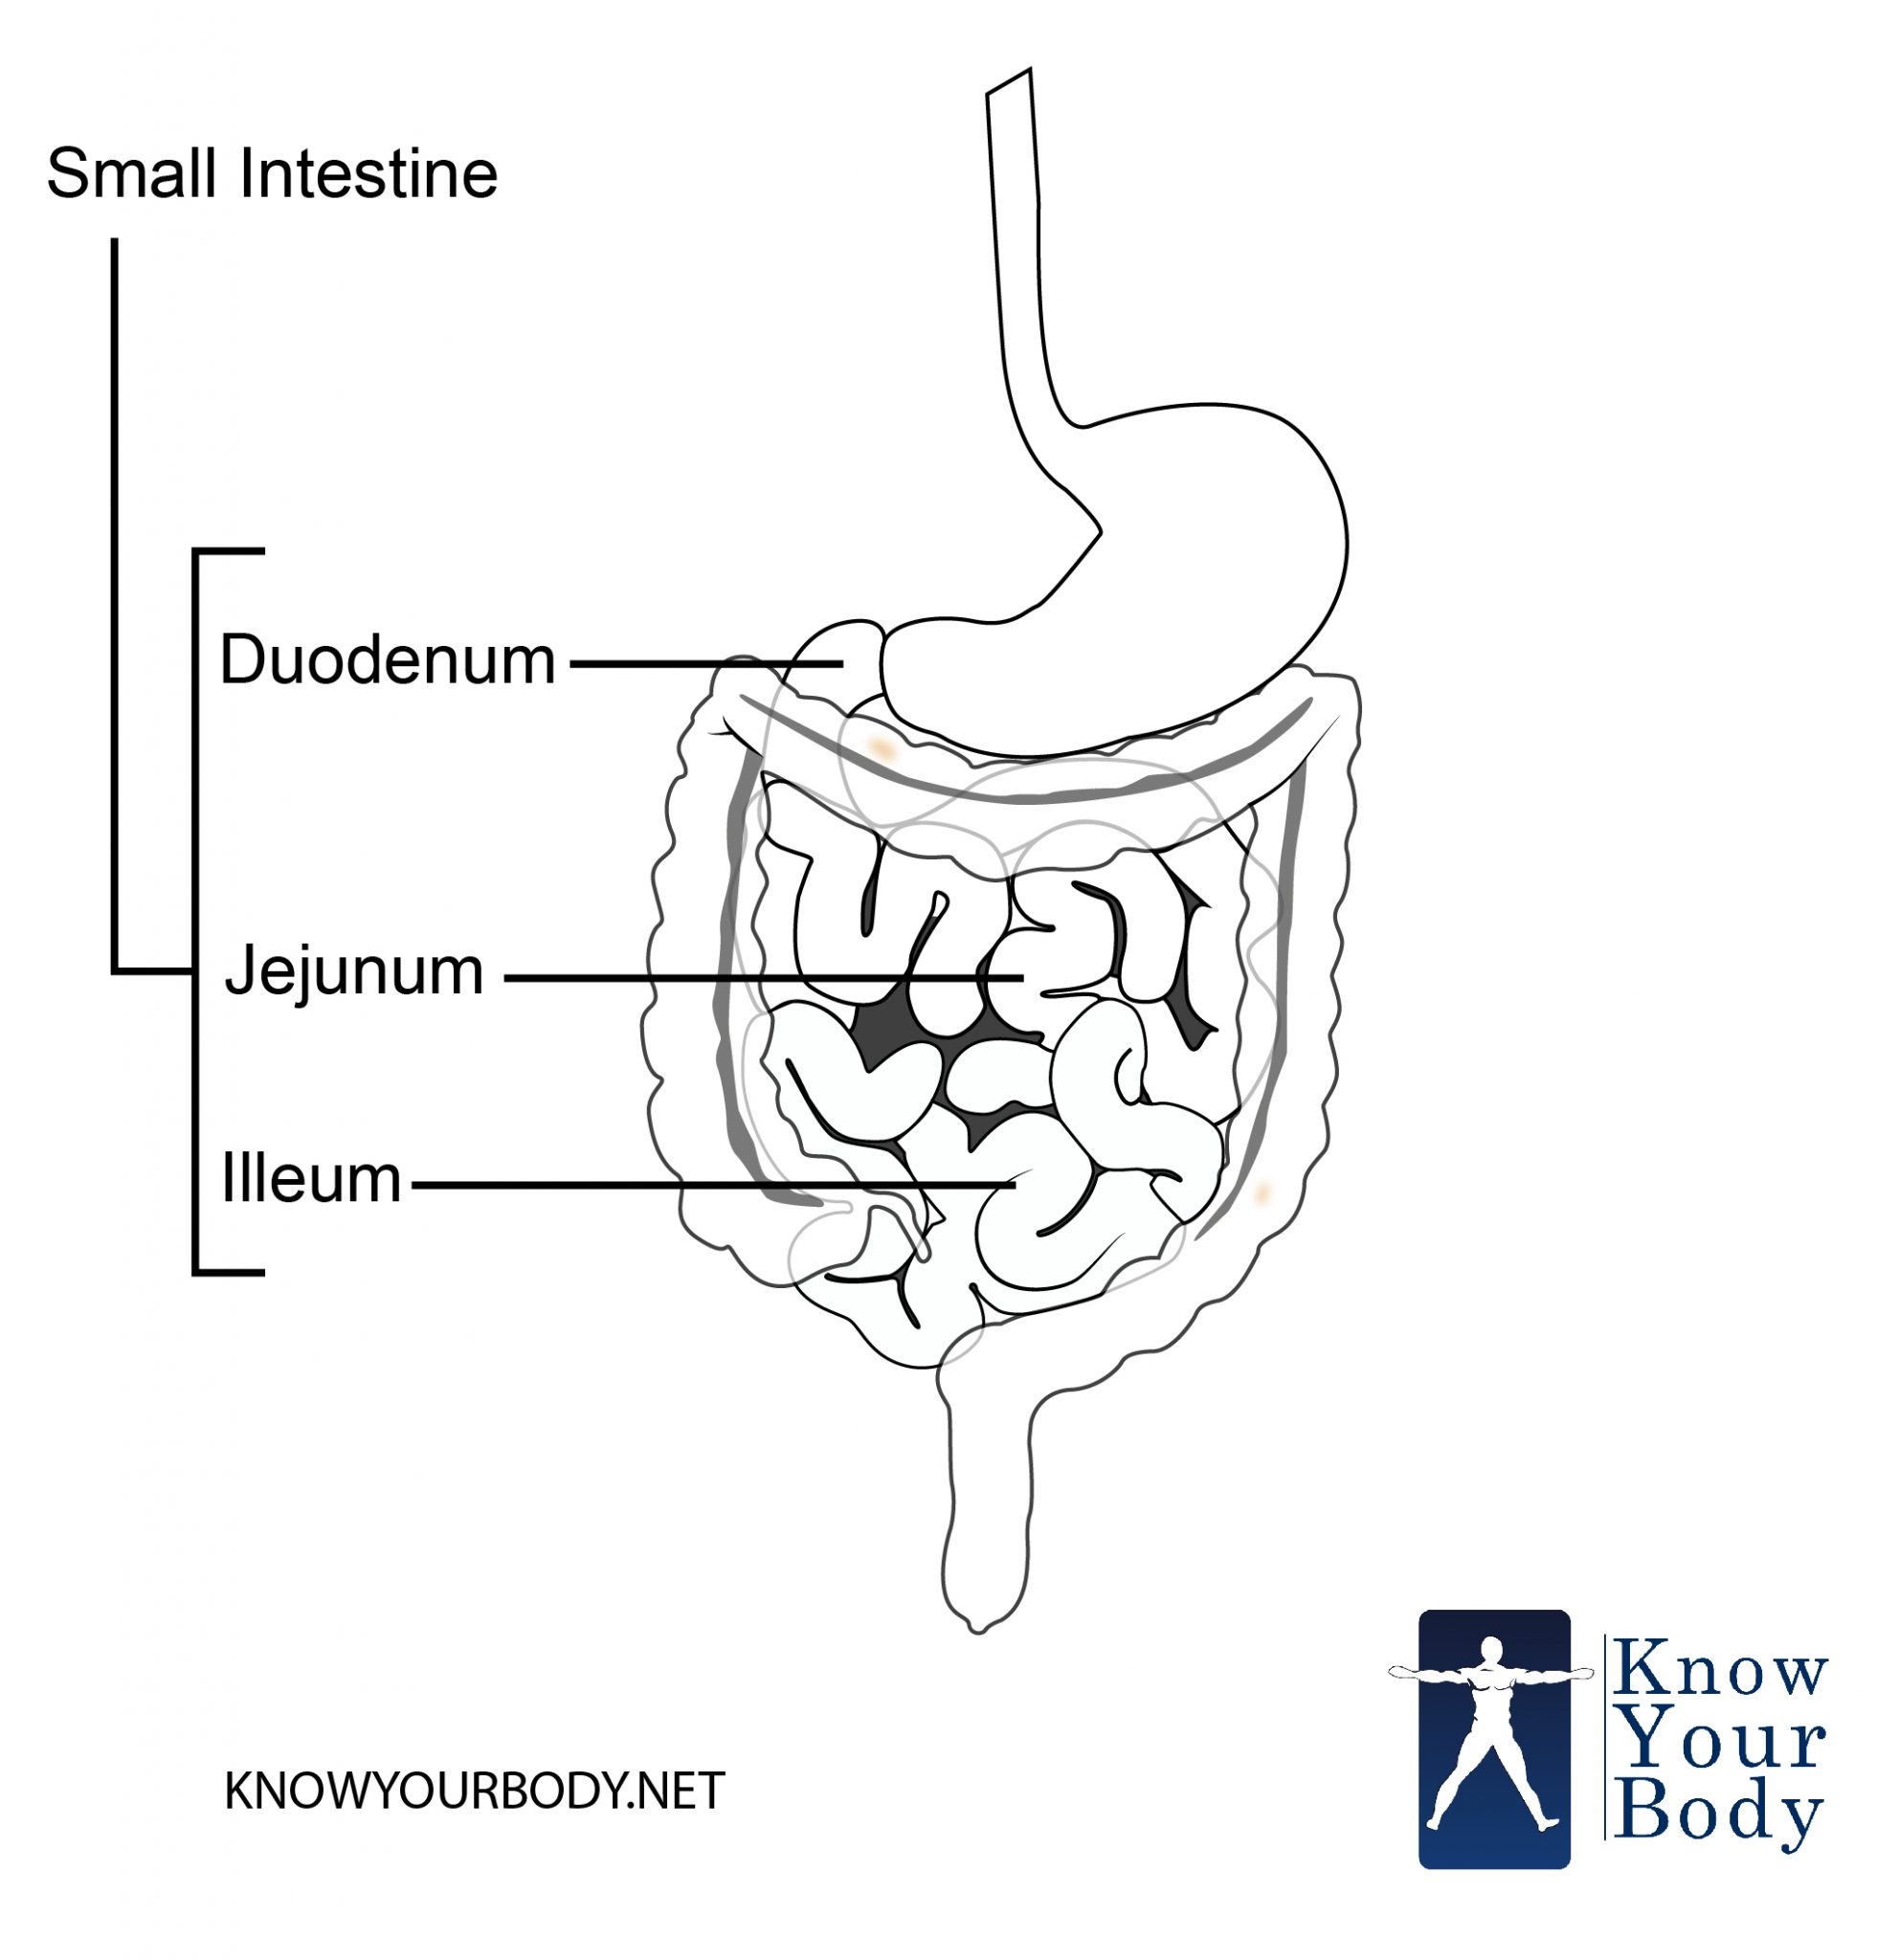
The three sections, in order from where food enters, are the duodenum, the jejunum, and the ileum. The duodenum is the shortest segment at roughly 25 to 30 centimeters. It hooks around the head of the pancreas and receives bile and pancreatic enzymes right here. The jejunum makes up the middle portion, about 2.5 meters long, and is where the bulk of nutrient absorption happens. The ileum is the final stretch, around 3.5 meters, and it specifically handles bile acid reabsorption and any remaining vitamins like B12. I remember running into an issue during a surgery rotation where the jejunum and ileum looked nearly identical to my eyes. The difference isn't obvious unless you know what to look for. The jejunum has thicker walls and more prominent circular folds called plicae circulares. The ileum is thinner-walled with fewer folds and you can often see the fatty appendages known as epiploic appendages along its surface. If you're studying dissection, focus on the mesenteric fat distribution and the visibility of those plicae. That's what separates them in practice. One thing textbooks don't always drive home is that the duodenum is technically retroperitoneal for most of its length. That matters clinically. When you're dealing with a posterior duodenal ulcer, it can erode into the gastroduodenal artery and cause serious bleeding. The fixed retroperitoneal position means inflammation or a perforation here doesn't present the same way as a free perforation in the mobile parts of the intestine. You get back pain, not the classic rigid abdomen you'd expect. I saw this misdiagnosed once because the team was focused on the wrong quadrant. The patient's complaint pattern didn't fit a typical acute abdomen, which was the first clue something deeper was going on.
The transition between the jejunum and ileum isn't a hard line either. There's no visible anatomical landmark that says "here ends the jejunum, here begins the ileum." Some surgeons estimate it at about the midpoint of the small bowel length from the ligament of Treitz to the ileocecal valve, but that's rough. In practice, you assess based on the features I mentioned earlier—wall thickness, fold density, and mesenteric characteristics. It took me several months of case exposure before I could reliably distinguish them without checking back to references. Beyond the basics, there's a practical detail about blood supply that's worth knowing. The duodenum gets its blood from both the celiac trunk and the superior mesenteric artery, which creates a potential watershed area. The pancreaticoduodenal arcades connect these two systems. If you're dealing with vascular compromise or surgical planning around this region, that dual supply is relevant. The jejunum and ileum are supplied entirely by the superior mesenteric artery through its jejunal and ileal branches, which is more straightforward but means occlusion here affects a larger segment. Understanding these three sections isn't just academic. The duodenum handles the chemical breakdown phase, the jejunum is the primary absorption zone for most macronutrients, and the ileum wraps things up with bile salt recycling and immune functions through the Peyer's patches concentrated there. If you're working in gastroenterology or surgery, knowing which section is affected by a condition changes your differential and your approach. Crohn's disease, for example, favors the terminal ileum, while celiac disease primarily damages the duodenal and jejunal mucosa.