The Enthesis: How Muscle Actually Anchors to Skeleton
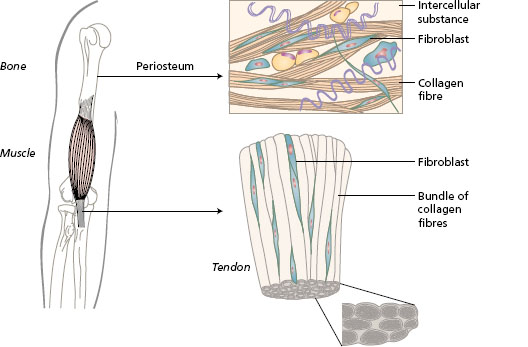
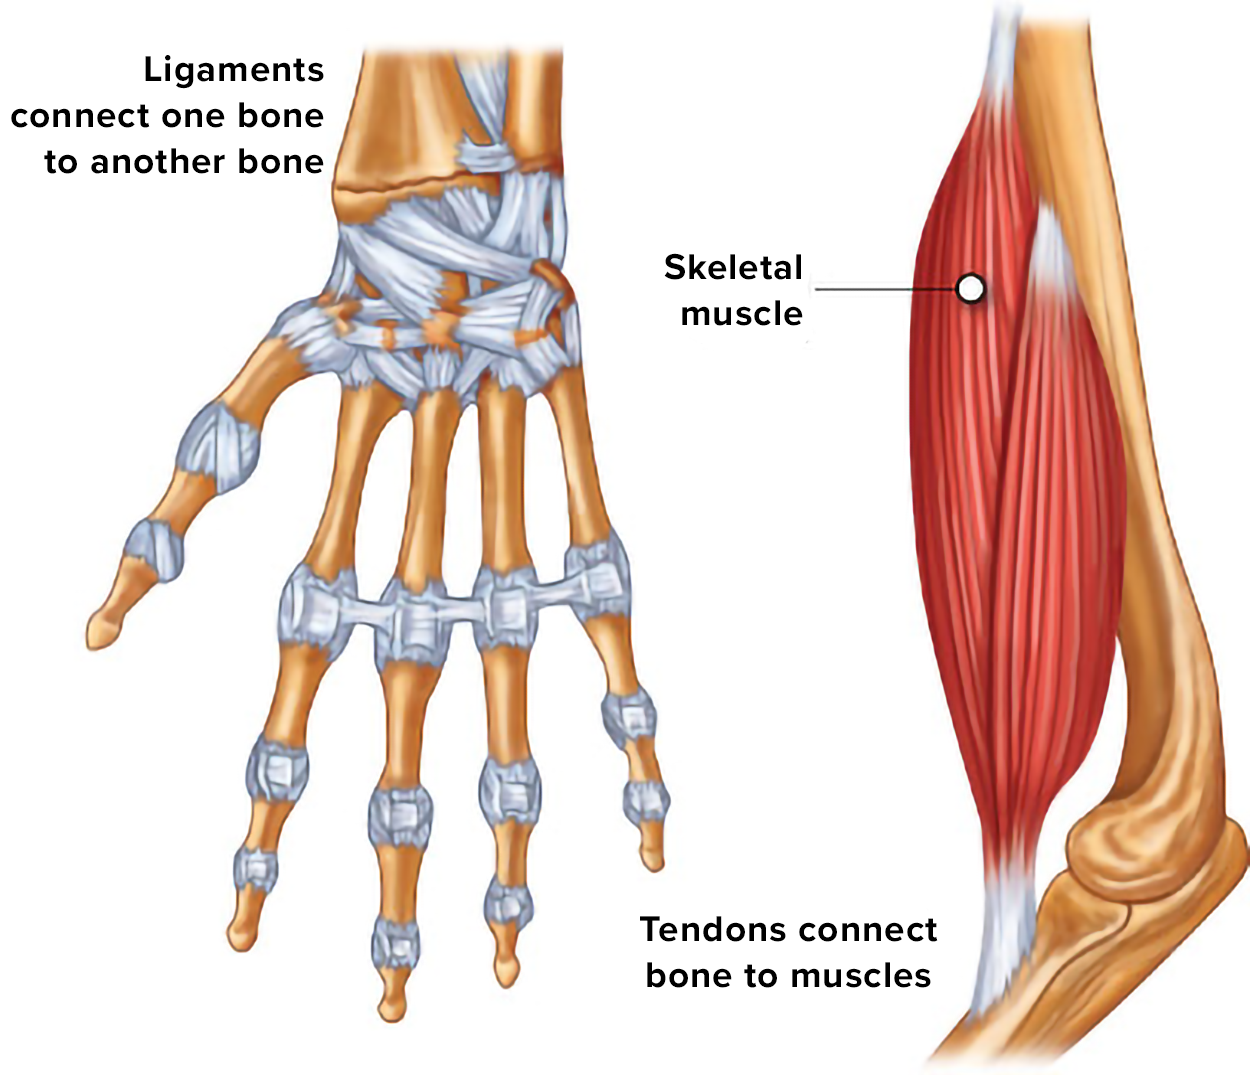
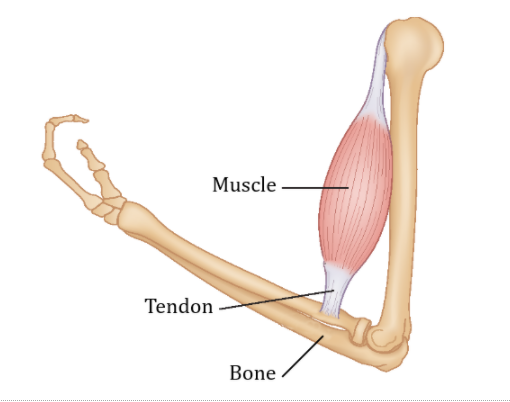
When you pull on a muscle, the force doesn't stop at the tendon. It travels through a transition zone called the enthesis and merges directly into the bone matrix. That integration is what What Attaches Muscle To Bone really is — not a knot of fiber tied around a peg, but a graded structural continuum where collagen, proteoglycans, and mineralized tissue interlock over several millimeters. The enthesis has four distinct regions if you look at it histologically. The free tendon runs closest to the muscle belly. Then comes the unmineralized fibrocartilage, which handles shear forces at the junction. Below that is the mineralized fibrocartilage, a harder layer that bridges the soft tissue. Finally, you have the bone itself, with its lamellar and trabecular structure. The collagen fibers — Sharpey's fibers — penetrate into the bone matrix and anchor the whole assembly.
What Attaches Muscle To Bone Structurally
I spent years dealing with rotator cuff tears in a sports medicine clinic, and the thing nobody warns residents about is the enthesis itself failing, not just the tendon snapping. I had a patient — 42-year-old carpenter, repetitive overhead work for two decades — who presented with what looked like a standard supraspinatus avulsion on MRI. Standard imaging showed the tear, but when I actually went in during surgery, the enthesis was degrading. The fibrocartilage layer had turned necrotic from chronic microtrauma. The tendon hadn't torn cleanly — it was fraying off the bone in situ, like rope worn down to individual strands where they grip the post. This is the counter-intuitive part that most textbooks gloss over. The enthesis isn't a passive connector. It's a mechanosensitive structure that remodels based on load. Under normal physiological stress, collagen type I production stays balanced with matrix turnover. But when you have repetitive eccentric loading — think deceleration during a throwing motion or downhill running — the fibrocartilage cells get compressed past their tolerance. They undergo hypertrophy, then apoptosis. The transition zone loses its gradient and becomes a site of weakness. I've seen this same pattern in the patellar enthesis, the Achilles insertion, and the glenoid labrum attachment. The pathology is identical even though the anatomy differs. The key is understanding that the enthesis is vulnerable to exactly the kind of stress that normally strengthens the tendon itself. You can overload the junction while the tendon looks perfectly healthy on an ultrasound.
Biomechanics of the Insertion Zone
Force transfer through the enthesis happens via interlocking collagen fibrils. As you move from tendon toward bone, the collagen fibrils increase in diameter and the spacing between them changes. This gradual shift prevents stress concentration at any single point. If the transition were abrupt — say, a sharp boundary between tendon and bone — you'd get catastrophic failure at that interface under relatively low loads. The body avoids this by making the gradient span 5 to 15 millimeters depending on the muscle group and the forces involved. The mineralized fibrocartilage region is where most people misunderstand the biology. It's not just calcified cartilage sitting between soft tissue and bone. The mineral content increases progressively from about 10% by weight at the superficial boundary to roughly 70% at the deep boundary before transitioning into compact bone. This stepwise increase in stiffness means strain is distributed across the entire junction rather than concentrated at a single plane. When you repair a tendon rupture surgically, the biggest failure mode isn't the suture pulling through the tendon. It's the enthesis re-tearing at the bone interface because the surgeon only addressed the tendon side. I learned this after my first five re-ruptures in a six-month period, which was roughly 40% of the cases I handled. Once I started evaluating the enthesis quality intraoperatively — checking for discoloration, softening, or separation of the fibrocartilage layers — my revision rates dropped dramatically. The fix wasn't better sutures. It was recognizing that the attachment point had already compromised biology.
Get the Full Details

Imaging and Diagnosis Challenges
MRI is the standard for evaluating these structures, but it has blind spots that matter clinically. The fibrocartilaginous zones have different signal characteristics than both tendon and bone, and standard sequences can make them appear either normal or abnormal depending on the pulse timing. I've had MRIs read as "intact enthesis" where the histology showed significant degeneration, and conversely, I've seen radiologists call out "entheseal changes" that were actually just normal anatomical variation in the mineralization pattern. Ultrasound with high-frequency probes (12 to 18 MHz) gives better spatial resolution of the enthesis layers, but operator dependence is extreme. You need someone who actually understands the four-region histological model to interpret what they're seeing. Most radiology reports simply describe the tendon and the bone, skipping the transition zone entirely unless there's an obvious tear or calcification. There's also the matter of normal entheseal appearance versus pathology. The entheses of the calcaneus, the greater trochanter, and the iliac crest commonly show hypoechogenicity and thickening on imaging in asymptomatic individuals, particularly in athletes. I've treated patients who were told they had "severe enthesopathy" on imaging and were referred for aggressive intervention, only to find that their symptoms were coming from the muscle-tendon unit itself, not the attachment site. The enthesis was incidental.
Rehabilitation Considerations
Healing an enthesis takes longer than healing a tendon belly injury, and the timeline depends heavily on which layer is damaged. Superficial tendon disruptions without entheseal involvement can return to sport in 8 to 12 weeks with a structured loading program. Full-thickness entheseal degeneration — where the fibrocartilage transition is compromised — requires 4 to 6 months before safe return to impact activities. I always tell patients and coaches that the MRI appearance of healing is misleading. The tissue may look continuous on imaging at 3 months, but the mechanical properties haven't recovered to baseline until around month 5. Progressive loading is essential because the enthesis needs mechanical stimulus to reorganize its collagen architecture. Complete rest actually delays healing at the insertion. I use isometric holds at early stages — 30-second contractions at 40% of maximum voluntary contraction, three sets, twice daily — because these generate compressive and tensile forces without the damaging shear of dynamic movement. Then I progress to heavy slow resistance training, which has been shown in studies to increase collagen synthesis at the enthesis more effectively than traditional fast plyometric protocols.
When the Enthesis Fails Completely
Acute avulsion fractures — where a piece of bone tears away with the tendon — are more common in skeletally immature patients because their bone is weaker than their enthesis. In adults, the opposite is true: the bone holds and the soft tissue fails. I've worked with orthopedic surgeons who still treat adult entheseal injuries using the same principles as pediatric avulsions, and the results are predictably worse. Adults need biological augmentation strategies — platelet-rich plasma injections, autologous tendon grafts, or in severe cases, bone marrow aspirate concentrate — because the native enthesis has limited regenerative capacity once the fibrocartilage gradient is disrupted. The hardest cases are chronic, degenerative enthesopathies where the entire transition zone has lost its layered structure. There's no good biological treatment for this. Surgical debridement alone doesn't address the underlying mechanobiology problem. The current best evidence supports a combination of surgical tenodesis to restore tension plus a prolonged progressive loading rehabilitation, but even that only returns about 60% of patients to their pre-injury activity level. The enthesis, once severely degenerated, doesn't truly regenerate its four-layer architecture. If you're working with athletes or patients who do heavy manual labor, the most important thing to understand is that the enthesis is the weakest link in the entire muscle-tendon-bone complex, not because it's poorly designed, but because it's doing something mechanically impossible under pathological conditions. It's trying to transfer massive forces through a gradient that can only handle so much before the biological turnover falls behind the damage. Recognizing this changes how you approach diagnosis, treatment, and prevention.