Respiratory Therapy With A Bachelor's Degree: Where It Actually Takes You
The degree itself won't magically unlock every door, but it does matter more than most entry-level people realize. Most RTs finish an associate program and that's perfectly fine for bedside work. But when you start looking past the first five years of your career, the bachelor's becomes a real differentiator. I've hired people, promoted people, and watched people leave the field within three years. The ones who stayed and moved up usually had that extra credential or they figured out a lateral move pretty quickly. It opens a wider range of clinical and non-clinical options, but the honest answer is that most of the doors it opens are about moving away from the bedside rather than deeper into it. You can still work full-time as a bedside respiratory therapist. That's absolutely something you can do. But the bachelor's path was designed partly because the industry knew that sticking to ICU and step-down forever has a ceiling. Here's what the realistic options look like.
Bedside Clinical Work
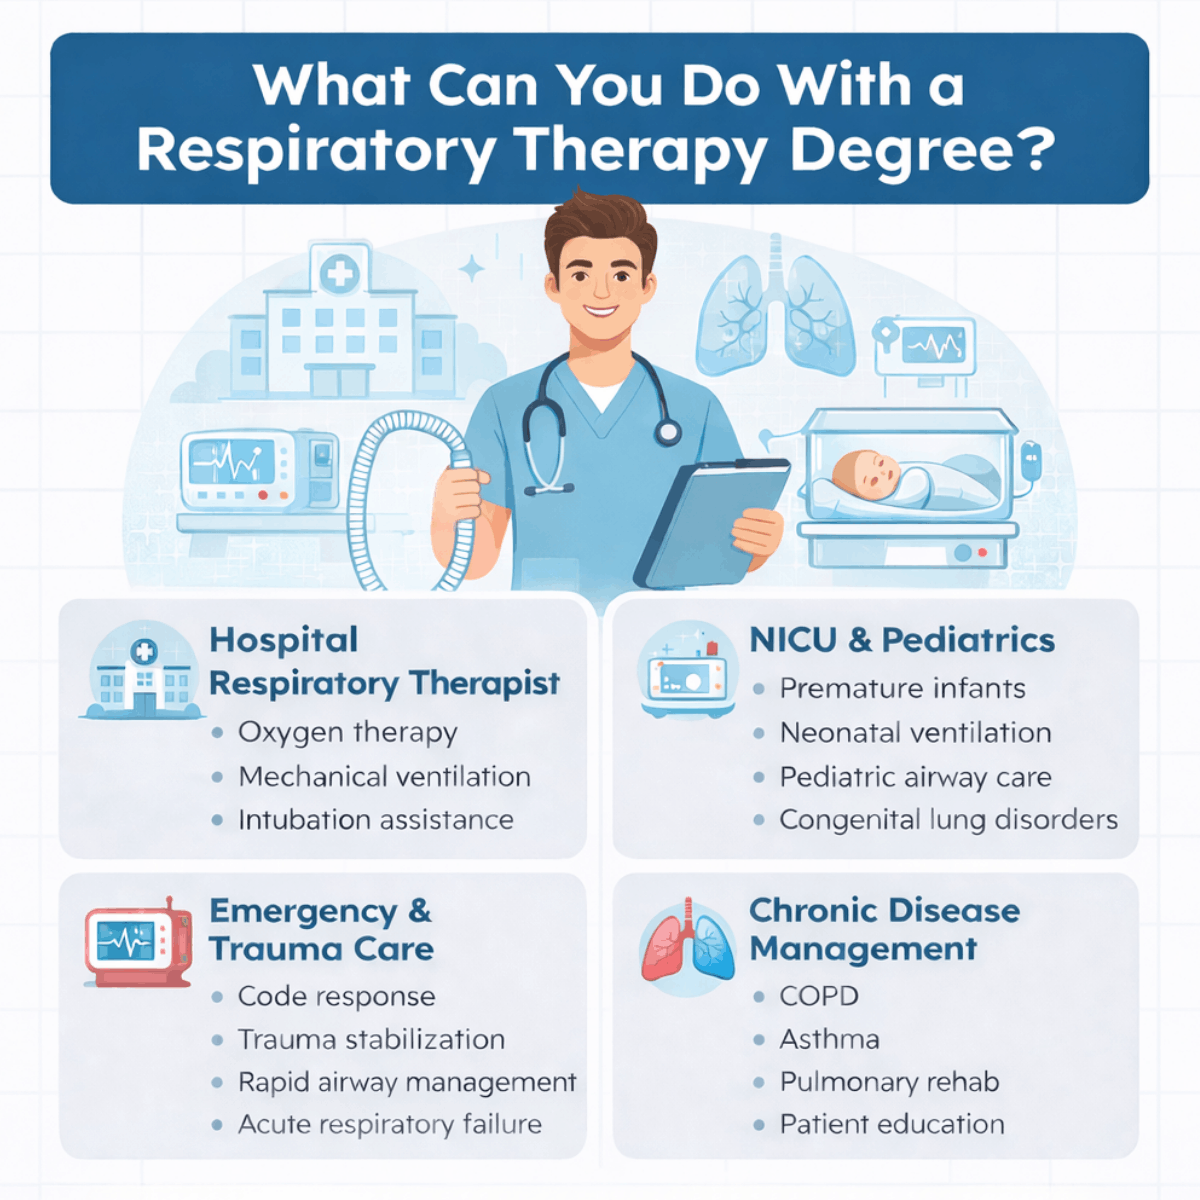
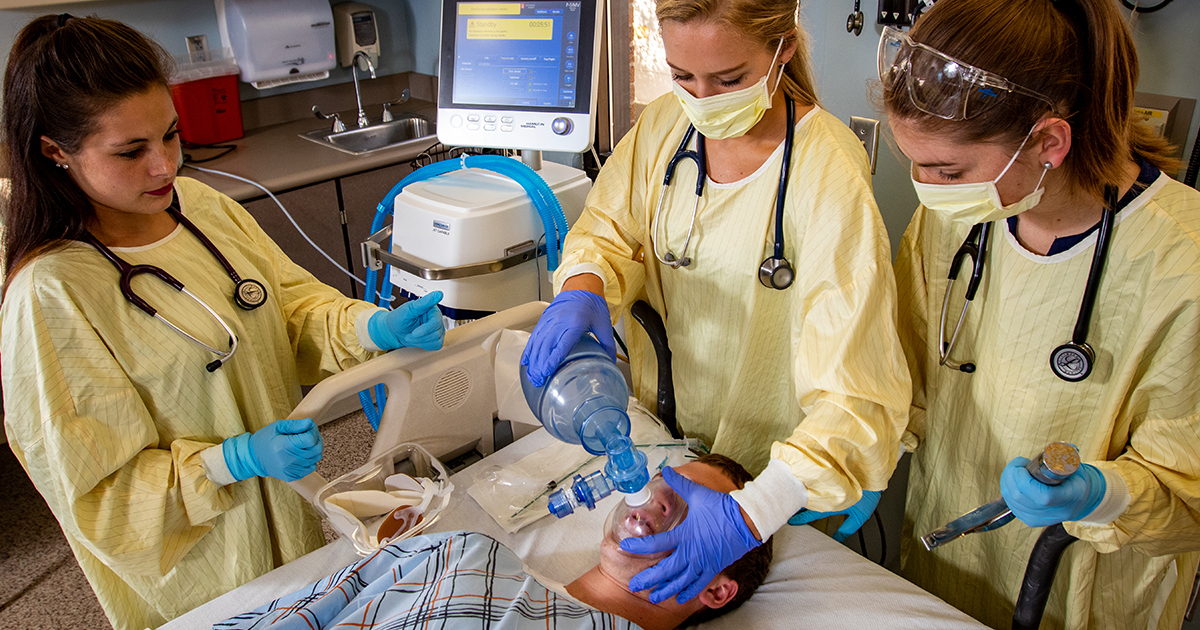
You'll manage mechanical ventilation for adult and pediatric patients. You'll handle airway management, bronchodilator therapy, arterial blood gas interpretation, and chest physiotherapy. You'll respond to code blues and rapid responses. That's the core of the job and it doesn't change just because you have a bachelor's. What changes is where hospitals will put you. Some larger health systems require or strongly prefer a bachelor's for ICU assignment, especially in magnet hospitals or academic medical centers. Others use it as a screening tool for charge nurse or educator positions. I've seen it both ways. One hospital I worked at wouldn't even let an associate-prepared RT into the neuro ICU regardless of experience. Another didn't care at all and promoted purely on merit. The work is physically demanding. You're lifting patients, positioning them, managing tangled ventilator circuits at 2 AM, and dealing with family members who are scared and angry. The pay is decent but not exceptional. In most markets you're looking at somewhere between sixty and one hundred thousand dollars annually depending on location, shift differential, and whether you pick up extra hours. Night shift pays more. Weekend rotation is mandatory in most places.
Specialized Clinical Roles
With a bachelor's plus experience, you can move into pulmonary function testing, sleep studies, neonatal transport, or hyperbaric medicine. These are real paths. They're not glamorous but they're stable and they keep you out of the worst parts of the acute care grind. Pulmonary function lab work is mostly scheduled testing. You run spirometry, body plethysmography, diffusion capacity, and bronchoprovocation. It's methodical and repetitive in a way that some people find calming. The pay is usually lower than ICU work. You're not doing codes. You're mostly interacting with outpatients who have chronic lung disease. Sleep medicine is another option. You run polysomnography studies, set up CPAP and BiPAP, and diagnose sleep apnea. It's detail-oriented work. The hours are better than ICU. You'll deal with claustrophobic patients and messy equipment setups but the pace is different. Some people prefer it. Some hate the administrative burden of documentation.
Get the Full Details

Neonatal and pediatric transport is more intense than standard bedside work. You're managing ventilators for premature infants and critically ill children, often in moving ambulances or aircraft. The patient population is smaller but the acuity is extremely high. It requires additional certification and you generally need significant respiratory therapy experience first. Pay tends to be higher to compensate for the stress and on-call demands.
Durable Medical Equipment And Home Care
This is a route a lot of people overlook. DME companies manage oxygen therapy, ventilators, and inhaler devices for patients who need them at home. You're doing assessments, fitting equipment, troubleshooting issues, and making house calls or remote checks. The work is autonomous and the schedule is usually regular business hours. The downsides are real though. The pay is typically lower than hospital work. You're dealing with insurance authorizations and prior renewals constantly. Some days you'll spend more time on the phone with a prior auth representative than you will with a patient. The clinical satisfaction is different too. You're not saving lives in real time. You're maintaining stability for chronic patients. I worked with a guy who left the ICU for DME after twelve years. He said it was the best decision he made for his mental health. He still saw patients but the stress level was completely different. His income dropped by about twenty percent. He didn't care.
Clinical Applications And Industry Roles
Companies like ResMed, Philips, and Hamilton Medical hire respiratory therapists as clinical applications specialists. You're traveling to hospitals, training staff on new ventilators and monitoring equipment, and serving as a bridge between the manufacturer and the clinicians. It's a legitimate career path and it pays well, often better than bedside work. The catch is that you're constantly traveling. Some weeks you're in three different states. Your luggage knows your schedule better than your family does. You need to be comfortable presenting to groups of strangers and handling difficult questions from clinicians who think your company's equipment is inferior to whatever they're already using. I spent six months working closely with a clinical applications team at a major hospital system when they were rolling out a new ventilator platform. The respiratory therapists on staff were genuinely frustrated. The interface wasn't intuitive, the alarm fatigue was worse than their current machines, and several senior RTs refused to touch it. My role was educational but the reality was that I was spending most of my time listening to complaints and reporting them back to the company. It's valuable experience but it's not always fulfilling.

Management And Leadership
If you want to move into supervision or management, the bachelor's degree matters. Most healthcare organizations have formal education requirements for charge nurse, department manager, and director positions. You can sometimes get exceptions with enough experience but the trend is toward requiring the degree. Respiratory therapy management involves scheduling, budgeting, performance reviews, policy development, and dealing with hospital administration. It's a completely different skill set from clinical work. Some RTs excel at it. Some hate it and wish they were back on the floor. I know people who managed departments for twenty years and loved every minute. I know others who lasted eighteen months before transferring back to bedside. The pay increases significantly. Department managers in large health systems can make well over a hundred thousand dollars. But the responsibility and politics come with it. You're making decisions that affect people's jobs. You're the middle manager between frontline staff and upper administration. It's not an easy place to be.
Education And Academia
Teaching in respiratory therapy programs is another option. Community colleges and technical schools need instructors. Some universities hire clinical faculty. The schedule is more predictable. Summers off are real in many programs. The pay is generally lower than clinical work but the lifestyle trade-off appeals to a lot of people. Most teaching positions prefer or require a master's degree now. A bachelor's alone might get you an adjunct or part-time position but the full-time roles are increasingly graduate-level. If education interests you, plan for that additional degree sooner rather than later.
A Practical Example From Real Experience
Let me share something specific. A few years ago I was consulted about a situation where a respiratory therapy department was struggling with ventilator-associated pneumonia rates. The hospital had a new batch of ventilators from a manufacturer that the staff wasn't familiar with. The old protocols didn't map cleanly onto the new equipment. VAP rates went up eighteen percent over six months. It wasn't catastrophic but it was measurable and concerning. The problem wasn't the ventilators. It was that the education program assumed familiarity with the previous brand. The new machine had different alarm configurations, different circuit setups, and a different approach to suctioning. Senior staff who'd been doing things one way for fifteen years were resistant to changing their process. New graduates had never learned the old way so they weren't entrenched but they were also making mistakes from ignorance rather than defiance. We created a targeted skills checklist that mapped old procedures to new equipment workflows. We ran hands-on sessions on the actual machines instead of classroom lectures. We paired experienced RTs with newer ones specifically to bridge the knowledge gap. The VAP rates came back down to baseline within four months. The key insight was that equipment transitions aren't just technical problems. They're cultural ones. The people doing the work need to understand why the change matters, not just how to operate the new device.
Counter-Intuitive Things About This Field
One thing most people don't understand is how much documentation matters. You can be the best ventilator manager in the hospital but if your charting is sloppy or incomplete, you're a liability. Insurance audits, legal discovery, and quality reviews all depend on your documentation. I've seen competent RTs lose jobs over documentation failures that had nothing to do with clinical skill. Another thing is the certification treadmill. You need BLS and ACLS. You need NPS and NPS-Pediatric. Some states require additional credentials. If you work in critical care transport you need CCRN or equivalent. These expire on different schedules and renewal costs add up. Budget for it. Keep track of expiration dates. Missing a renewal can suspend your ability to work. Here's something nobody tells you: the most valuable skill in respiratory therapy isn't knowing how to adjust ventilator settings. It's knowing when not to touch the ventilator. I've seen RTs and even some physicians make things worse by aggressively changing settings based on a single ABG or a momentary alarm. Sometimes the right intervention is to stabilize the patient, give them time, and reassess. Bad decisions based on incomplete information cause real harm.
The Limitations And Honest Downsides
The field is contracting in some ways. Fewer colleges are offering respiratory therapy bachelor's programs. The Bureau of Labor Statistics projects modest growth at best. Automation and streamlined protocols are reducing the number of RTs needed per patient in some settings. Hospital consolidation means fewer employer options in many regions. Physical wear and tear is real. Knee problems, back issues, and shoulder injuries are common after a decade or more of patient handling. The shift work disrupts sleep patterns and social life. Exposure to infectious diseases is an ongoing risk even with PPE. The career ceiling is genuine. Without a bachelor's or additional credentials, you'll likely spend your entire career at the same bedside level with incremental pay increases. The degree won't guarantee promotion but the absence of one will almost certainly limit your options. It's a gatekeeper credential more than a skill builder.
If you're considering this field, talk to working respiratory therapists in your area. Ask about their daily routines, their stress levels, their career trajectories. The reality on the ground is different from the brochure. Job descriptions list what the work could be. The actual day-to-day is usually messier and more mundane than that.