The Structural Reality of the Human Skeleton
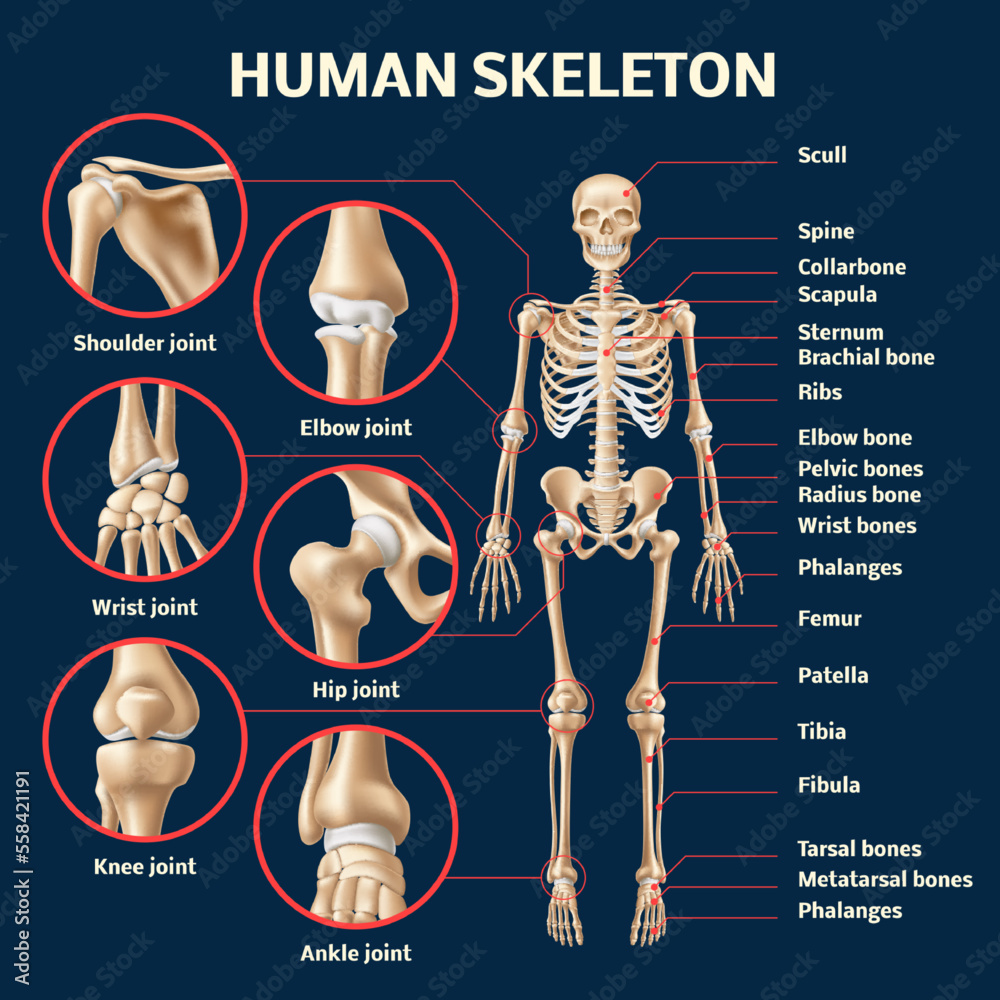
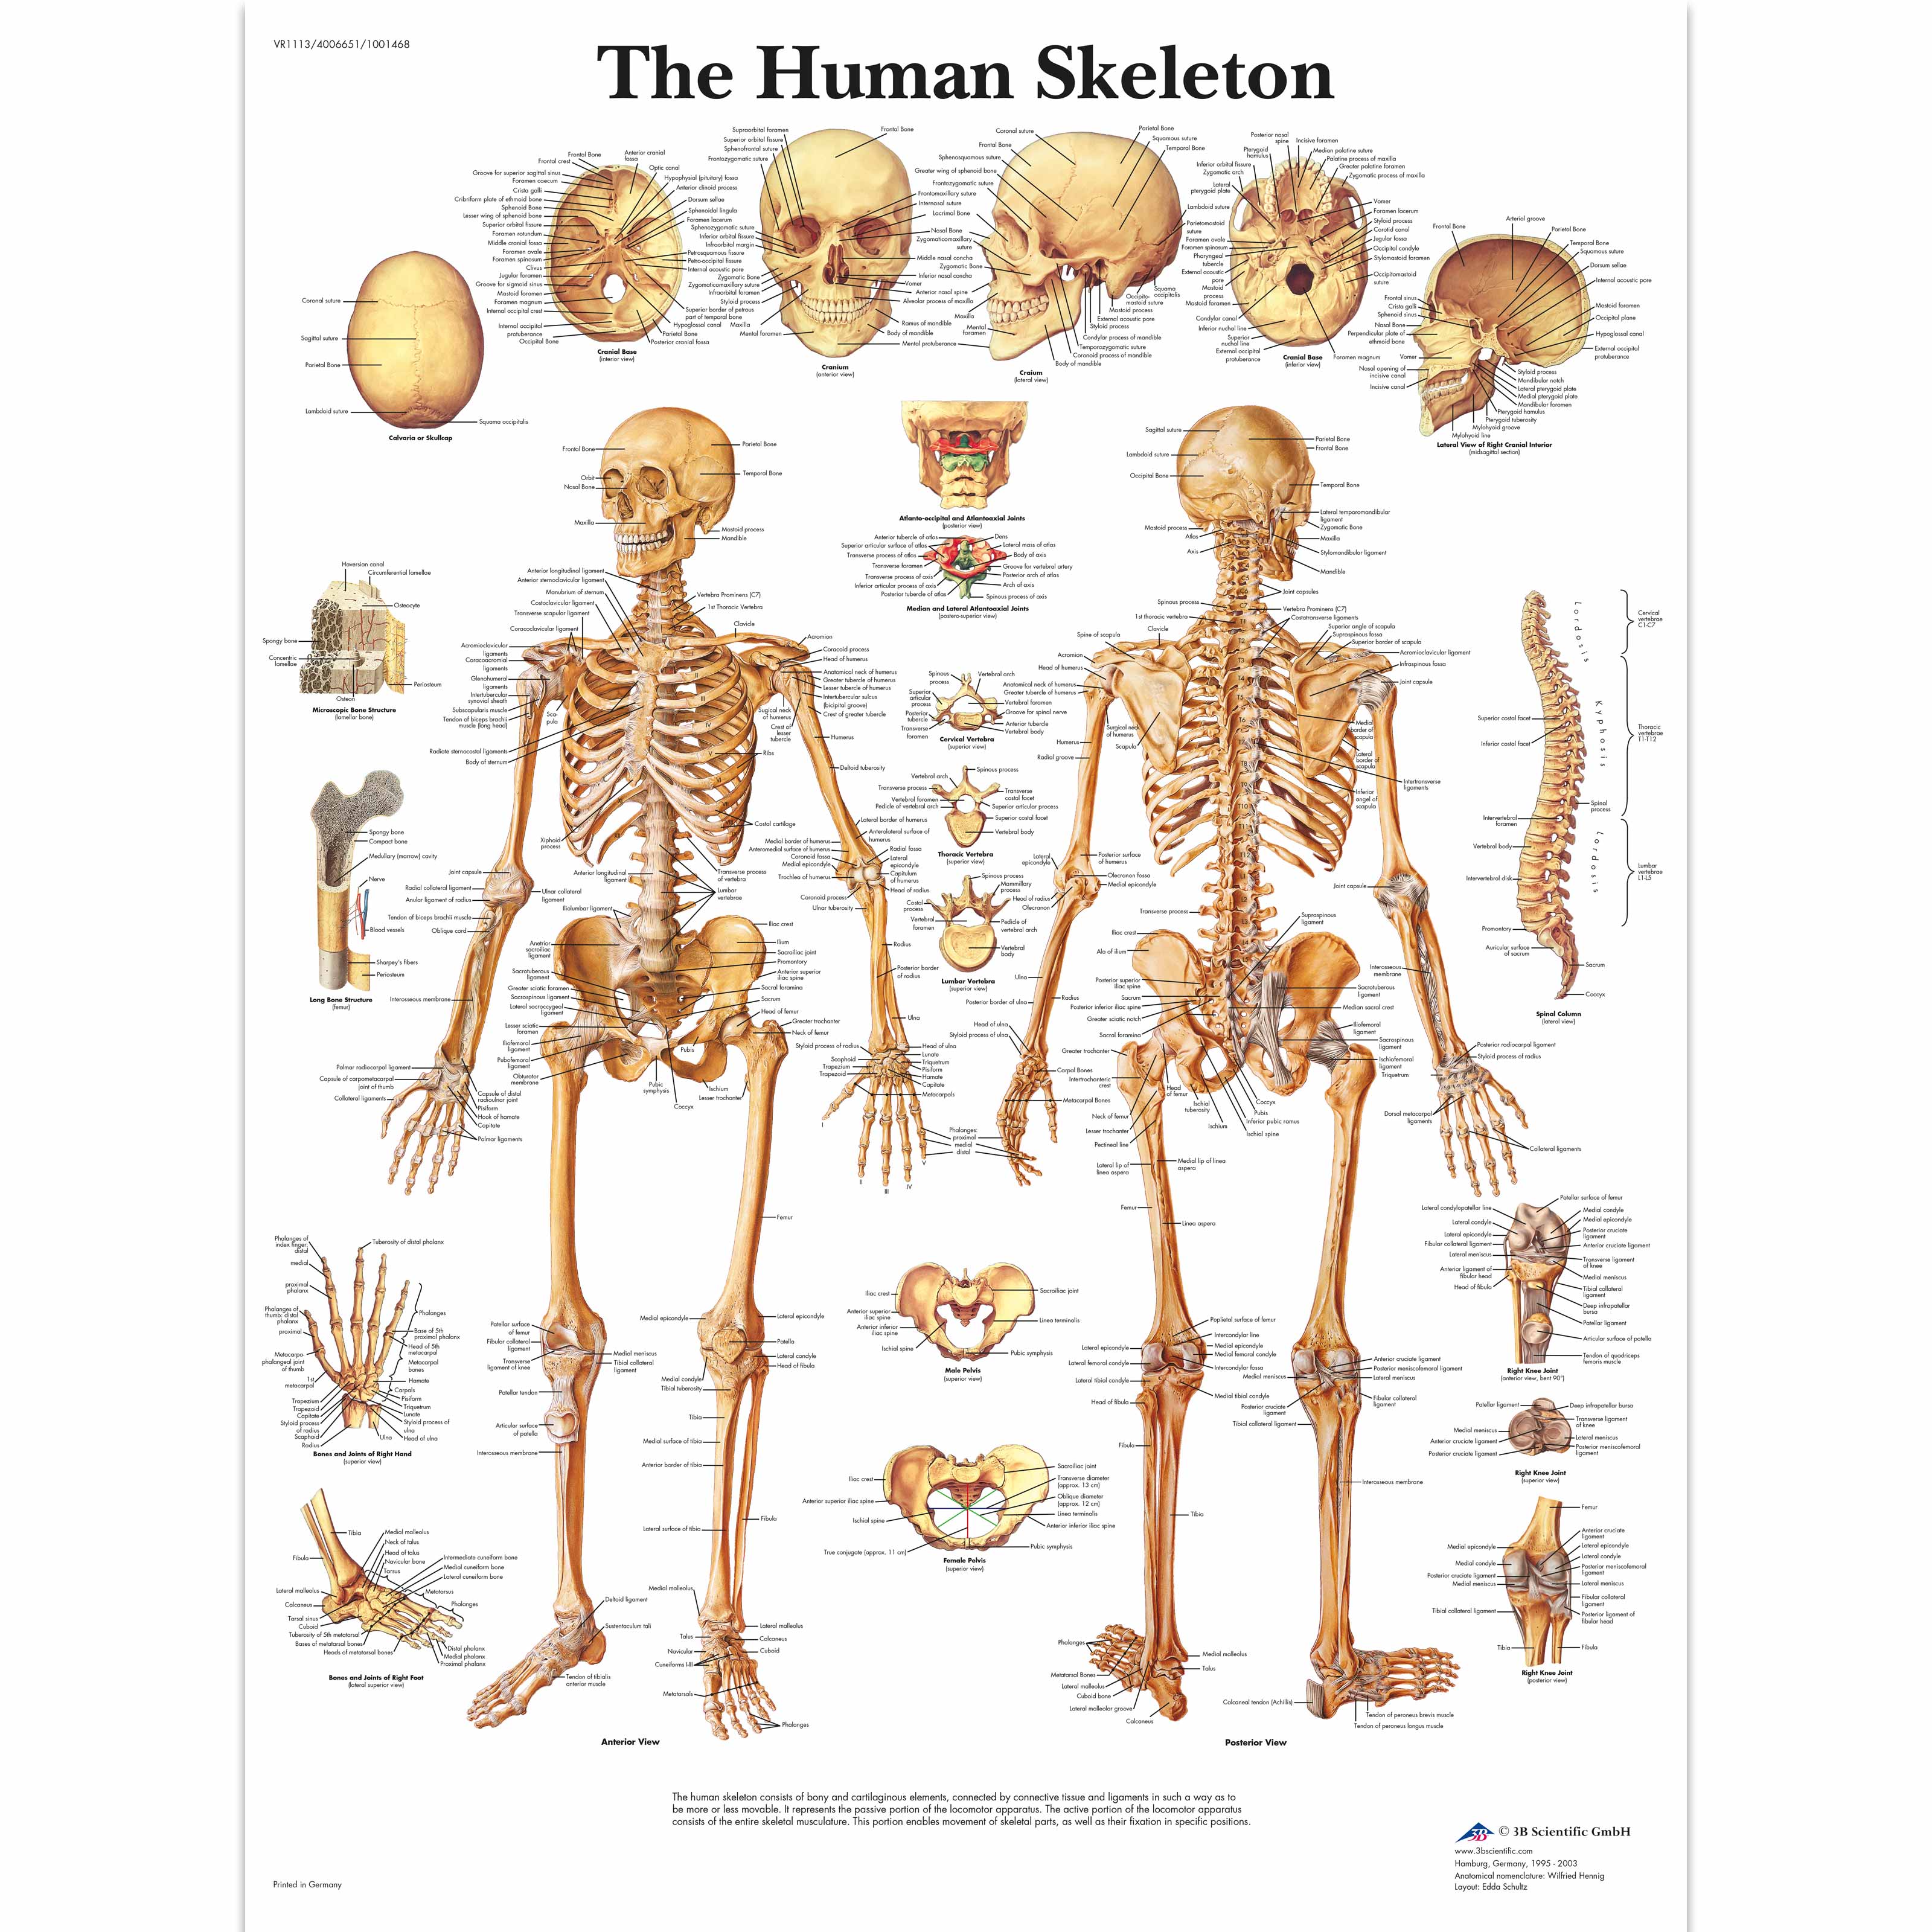
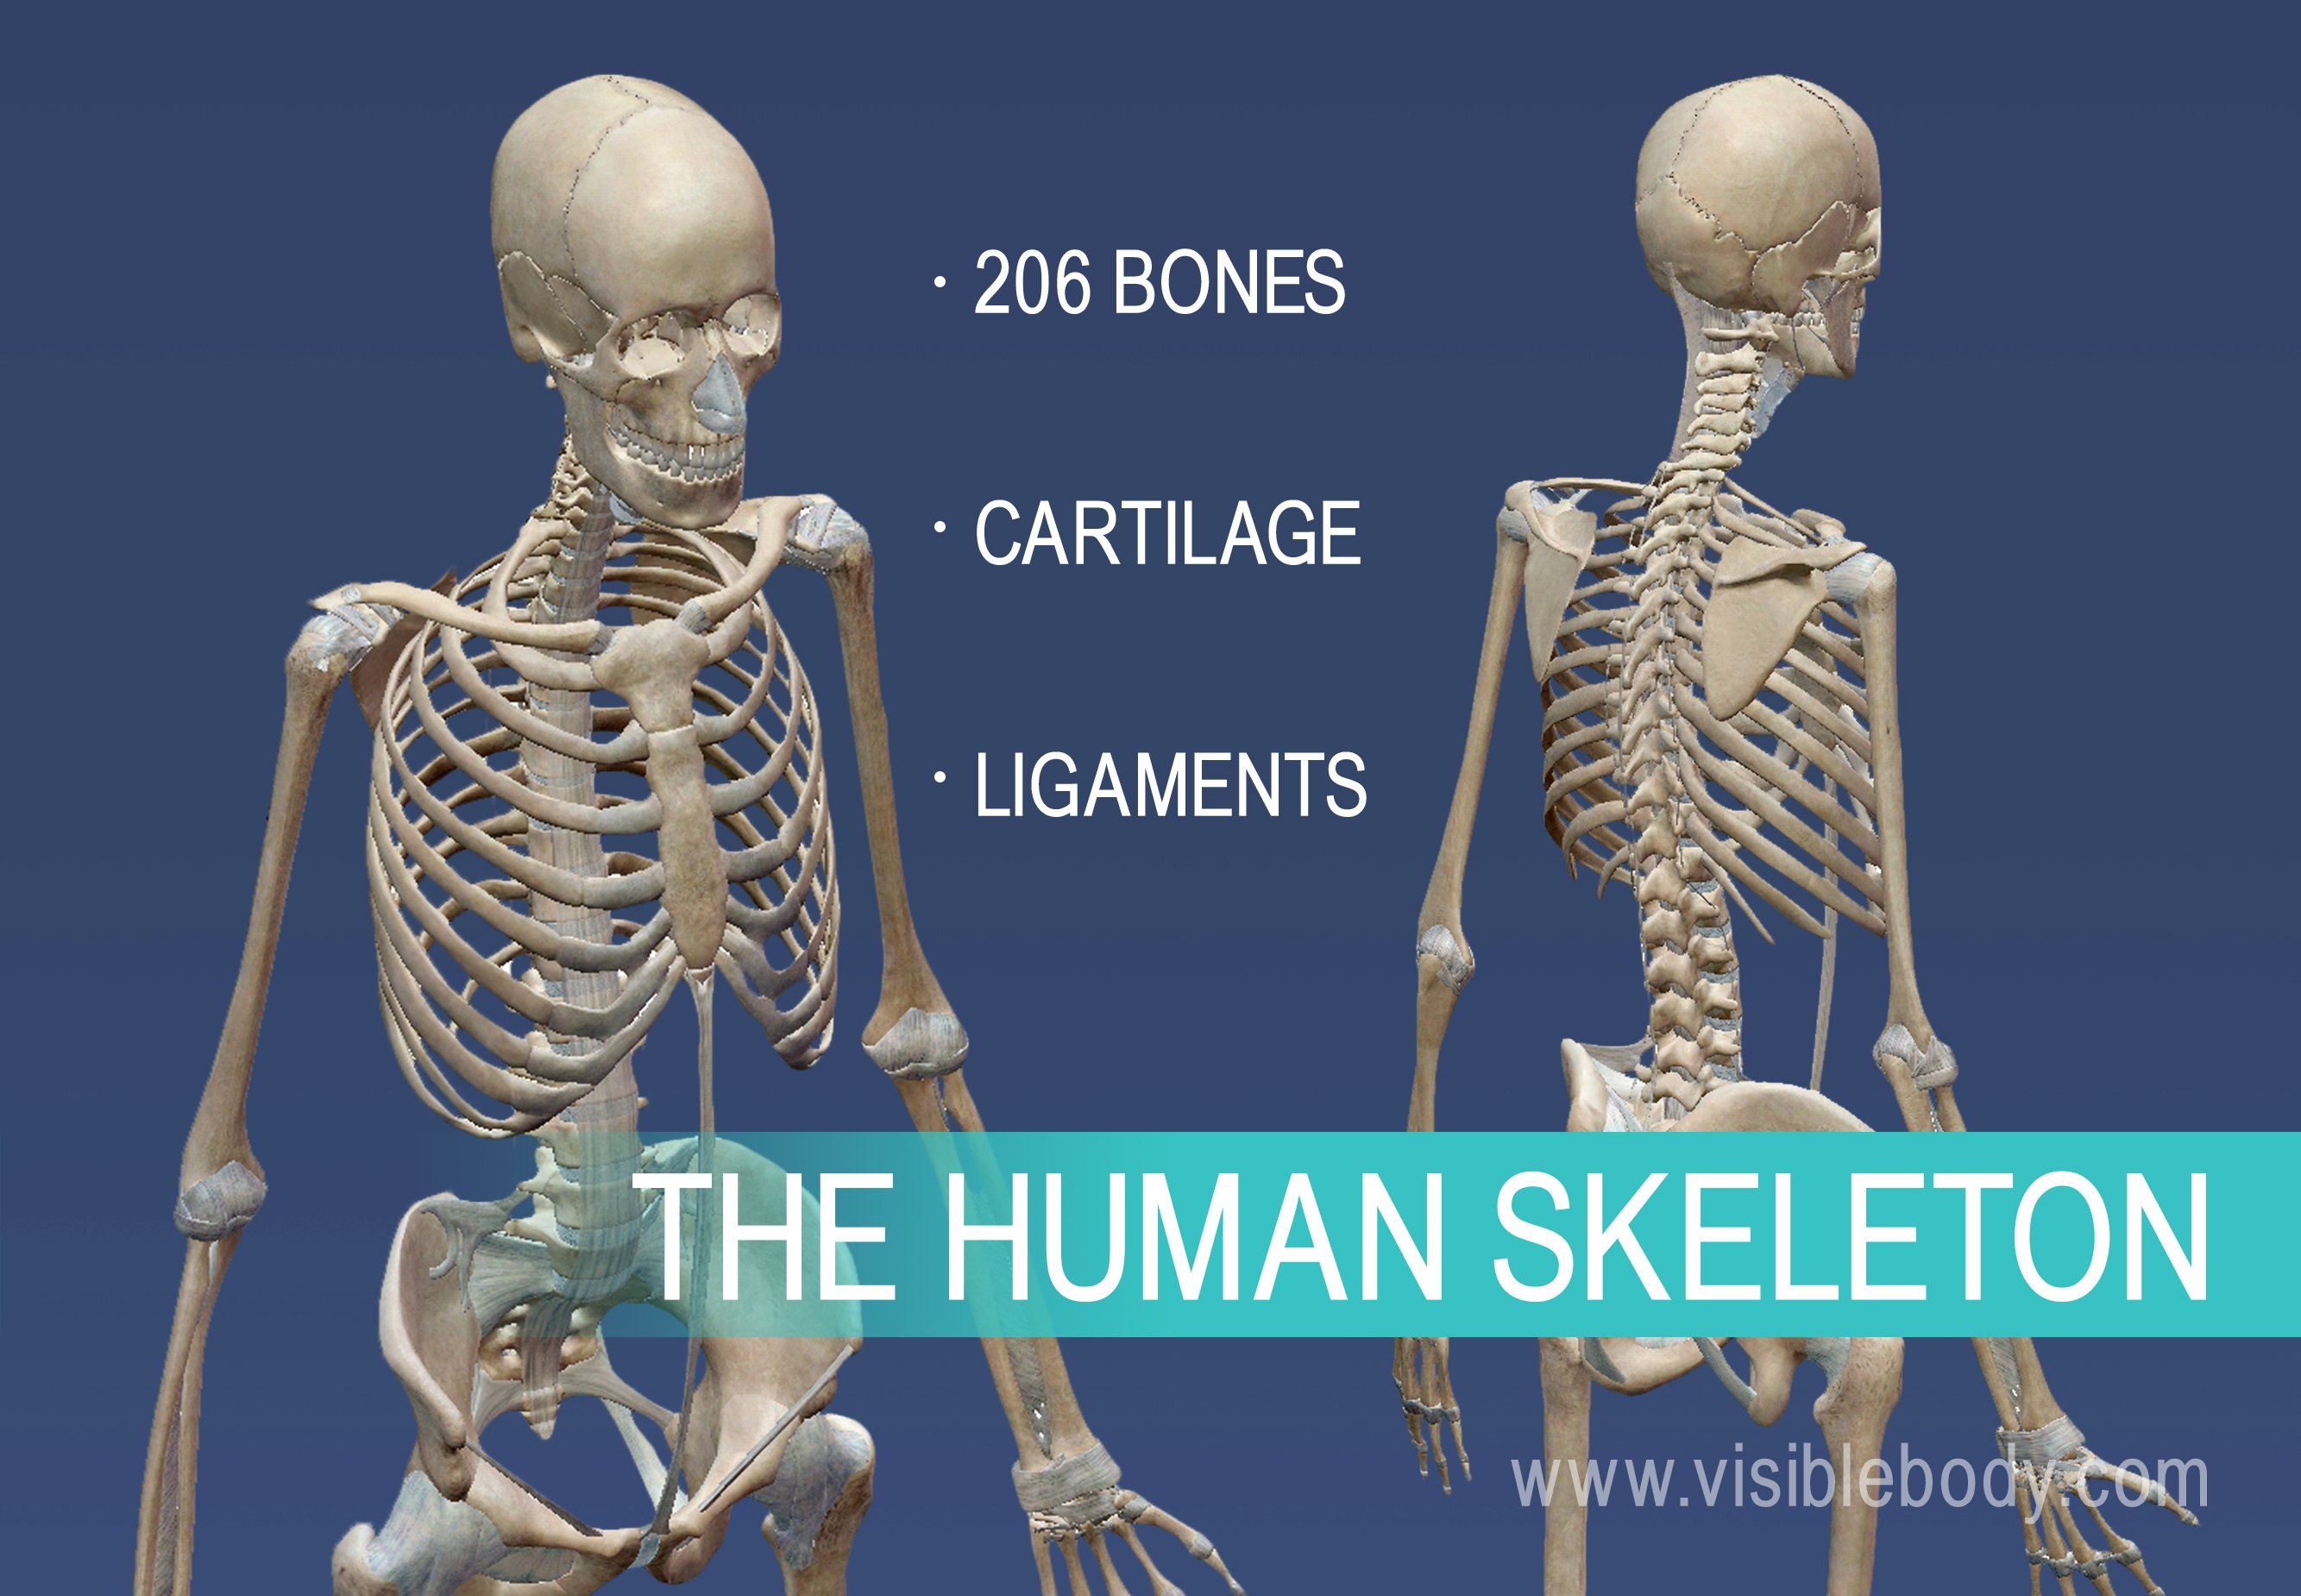
The skeleton does three basic things: it holds you upright, it protects your internal organs, and it gives your muscles attachment points so movement is even remotely possible. That is the short version. The actual picture is messier because bones are living tissue, not inert props, and they are constantly being remodeled based on the loads you put through them. What Does The Human Skeleton Do goes well beyond simple structural support when you look at how the system actually behaves under stress. Bones act as levers, yes, but they also manage compressive forces in ways most people do not account for. The femur handles roughly three times your body weight during normal walking and up to eight times during a jump. If bone structure were purely about raw strength, it would be massively overbuilt and impractically heavy. Instead, trabecular bone inside the epiphyses of long bones arranges itself along lines of stress. This internal architecture means you get strength where it is needed without the metabolic cost of solid cortical bone everywhere. A counter-intuitive point: bone does not get stronger by being rigid all the time. Bones adapt to dynamic loading. Static compression alone does not stimulate the same remodeling response as varied, multidirectional stress. This is why astronauts lose significant bone density in microgravity and why prolonged bed rest causes rapid demineralization. The body assumes bone is unnecessary and reabsorbs it. Calcium stored in the hydroxyapatite matrix gets released into the bloodstream when mechanical signals drop below a threshold.
I ran into a practical issue a few years back while working through a biomechanics simulation project. I was modeling force distribution through the lumbar spine during different lifting postures and kept getting unrealistic stress concentrations at L4-L5 no matter how I adjusted the material properties. The problem turned out to be that I was treating the intervertebral discs as simple spacers rather than pressure-distributing elements with viscoelastic behavior. Once I switched the disc material model to include creep and stress-relaxation parameters, the force transmission through the vertebral bodies dropped into a physiologically realistic range within about ten minutes of tweaking the solver settings. It was one of those cases where a simplified model gave convincing but wrong answers because the underlying physics were incomplete.
The Protection Function Is Not Just About Rigid Walls
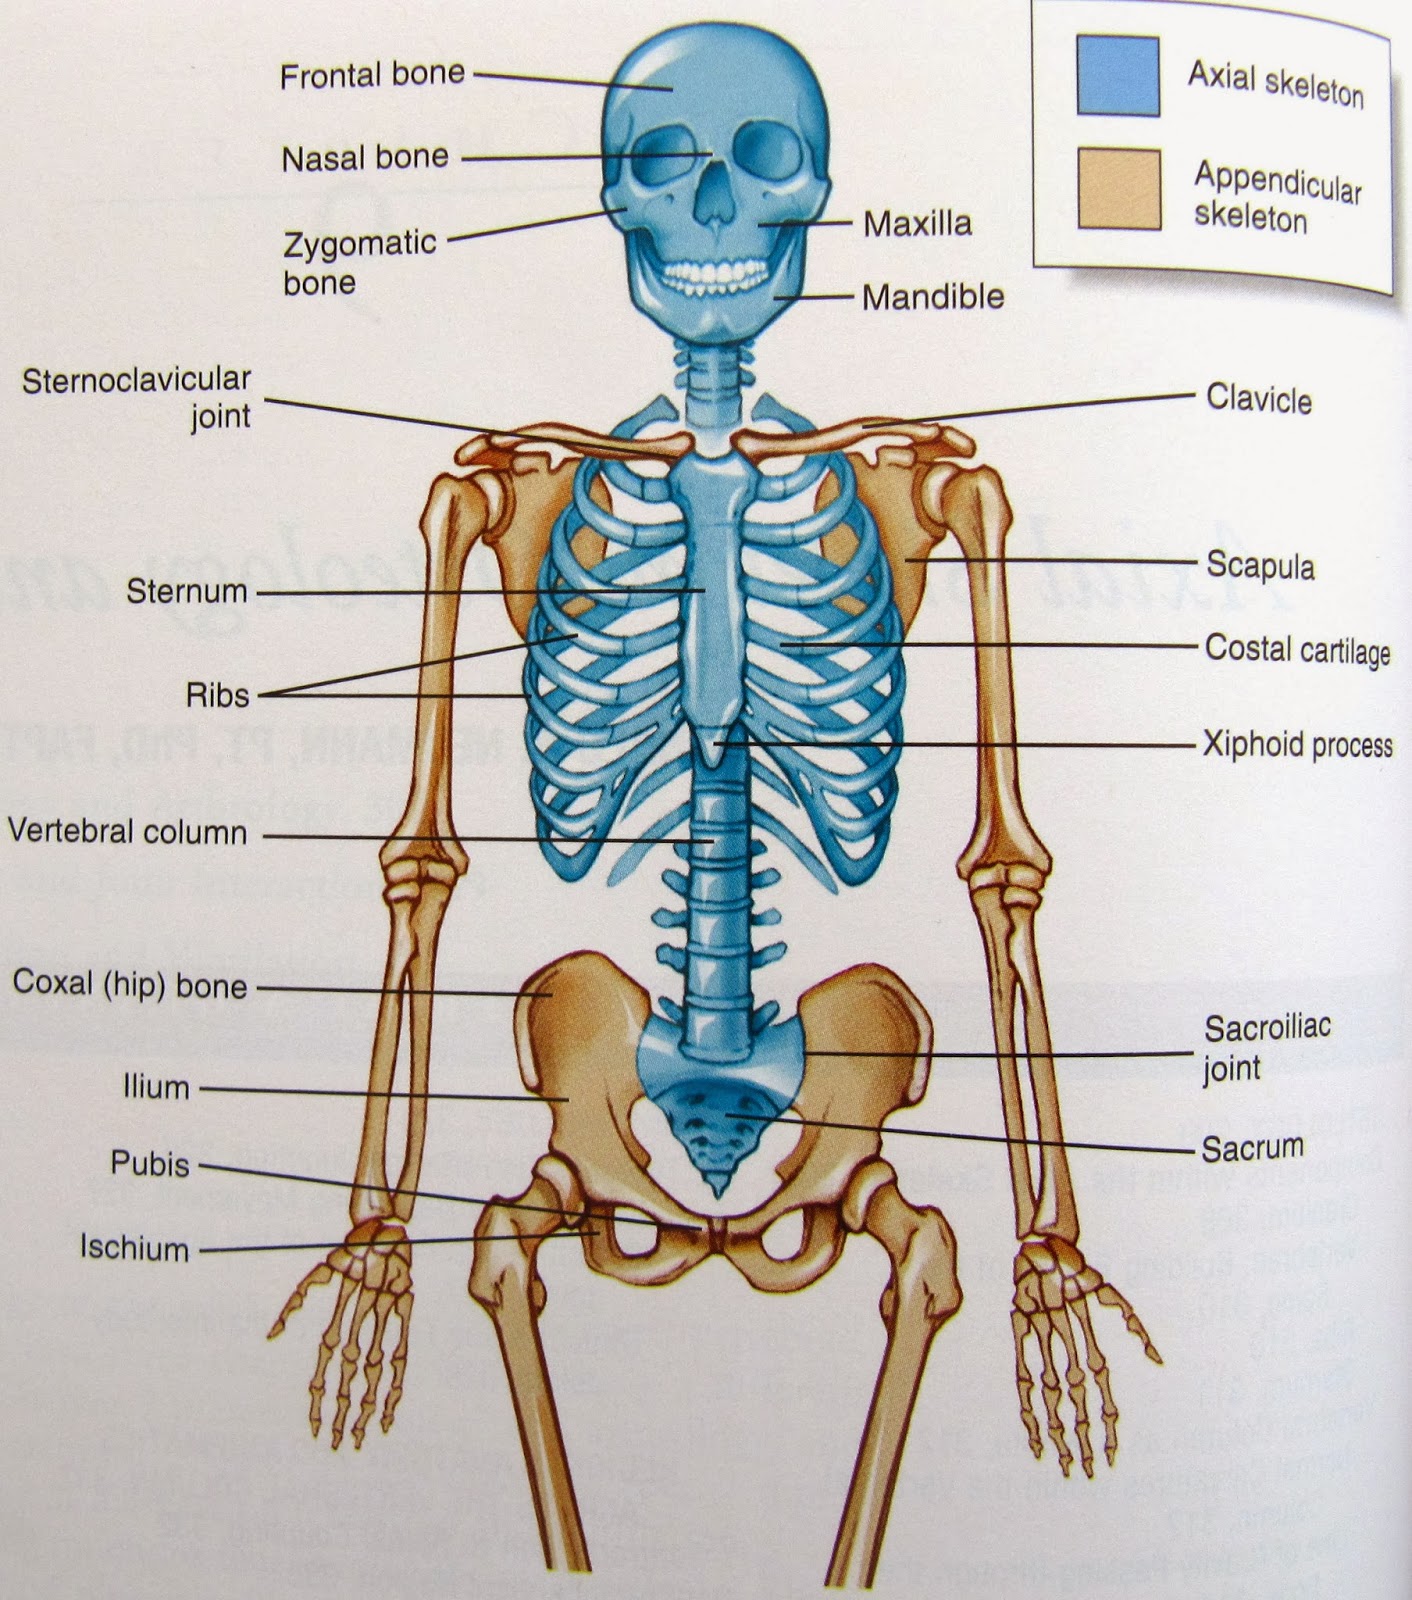
The skull protects the brain. The rib cage protects the heart and lungs. The vertebrae protect the spinal cord. That is obvious. What is less obvious is how much the skeletal system participates in gas exchange and oxygen transport indirectly. The sternum and proximal femur are major sites of hematopoiesis in adults. Bone marrow produces red blood cells, white blood cells, and platelets. When someone has bone marrow suppression from chemotherapy or certain infections, the skeleton stops doing one of its most vital jobs without any structural damage being visible on an X-ray. Another thing beginners miss: the skeleton is not a single connected unit. The axial and appendicular portions work independently in some contexts and together in others. Consider the pelvic girdle. The iliac bones anchor the gluteal muscles, the sacrum transfers load from the spine to the legs, and the pubic symphysis allows micro-movement during walking. If you treat the pelvis as a single rigid ring in any kind of structural analysis, your results will be off. The sacroiliac joints alone permit roughly two to three millimeters of movement and several degrees of rotation. That small amount matters for shock absorption and gait mechanics.
Get the Full Details

Mineral Homeostasis Is a Constant Trade-off
Bones store approximately 99 percent of the body's calcium and 85 percent of its phosphorus. This is not a vault. It is a reservoir that gets drawn from and replenished continuously through the action of osteoblasts and osteoclasts. Parathyroid hormone, calcitonin, and vitamin D regulate this process. When blood calcium drops, osteoclasts resorb bone matrix and release calcium into circulation. When calcium is abundant and mechanical loading is high, osteoblasts lay down new matrix. The net balance determines whether you gain or lose bone density over time. The downsides of this system are well documented. Osteoporosis affects roughly one in three women and one in five men over fifty in developed countries. It is silent until a fracture occurs. The common pitfall is assuming that calcium supplementation alone prevents bone loss. Resistance training and impact loading provide the mechanical stimulus that tells osteoblasts to build bone. Supplementation without loading is like buying building materials and never calling the construction crew. There is also the issue of bone turnover rate. In younger individuals, formation outpaces resorption. After peak bone mass is reached around age thirty, the balance tips gradually. Certain medications like bisphosphonates slow resorption and can be effective, but they also reduce bone remodeling to the point where microdamage accumulates. Atypical femoral fractures have been reported in long-term bisphosphonate users. The skeleton stops repairing itself as efficiently because the remodeling cycle is suppressed. Drug holidays are sometimes recommended after three to five years of therapy, though the evidence for when to restart or stop is still being refined.
Accessing Skeletal Data and Models
If you are looking for skeletal data for research, education, or visualization purposes, there are several publicly accessible resources. The Visible Human Project provides high-resolution CT and MRI datasets that include complete skeletal reconstructions. These are available from the National Library of Medicine and can be used for creating accurate 3D models or measuring bone dimensions. For downloadable 3D printable files, platforms like Sketchfab and Thingiverse host numerous skeletal models created from medical imaging data, ranging from full adult skeletons to individual bones with varying levels of anatomical detail. Open-source medical imaging toolkits such as 3D Slicer and MITK allow users to segment skeletal structures from DICOM files and export them as 3D meshes. The pipeline typically involves importing patient CT or MRI data, applying thresholding to isolate bone based on Hounsfield units, performing surface reconstruction, and exporting the result as an STL or OBJ file. The whole segmentation and export process usually takes between twenty to forty-five minutes depending on image resolution and the complexity of the region being processed.
Structural Limitations That Matter
The skeletal system has real limits. Bone strength decreases with age, and the rate of loss accelerates after menopause in women due to estrogen decline. Men experience a slower decline, but it is still significant. Trauma capacity is finite: a typical femoral shaft fracture requires a direct impact force exceeding three thousand newtons, which is roughly equivalent to the impact from a low-speed car collision or a fall from more than six meters onto a hard surface. One scenario where the skeleton completely fails as a protective structure is in severe osteomalacia. When vitamin D deficiency is profound enough to cause defective mineralization, bones become soft and deformed. The rib cage can collapse inward, the pelvis can narrow, and spinal curvature becomes severe. No amount of structural engineering in the bone matrix can compensate when the basic mineralization process is broken. In these cases, the treatment is not mechanical reinforcement. It is correcting the underlying metabolic defect with vitamin D and calcium supplementation, and sometimes addressing malabsorption issues in the gut. Another limitation worth noting is that skeletal imaging alone cannot tell you about soft tissue function. An X-ray shows bone alignment and density. It does not show ligament integrity, cartilage health, or muscle condition. A patient can have perfectly aligned vertebrae on a lateral spine X-ray and still have debilitating disc herniation or spinal stenosis that is invisible without MRI. Relying solely on skeletal imaging for diagnosing back pain is a common error that delays appropriate treatment and wastes time and resources.
Practical Takeaways
If you want to maintain skeletal health, mechanical loading is the most underutilized intervention. Weight-bearing exercise, resistance training, and impact activities like jumping produce signals that osteocytes detect and translate into bone formation. Nutrition matters, but it is secondary to mechanical stimulus for maintaining density in healthy adults. The skeleton responds to what it is asked to do, not what you feed it. When working with skeletal data or models, pay attention to the source of your images. Segmentation parameters dramatically affect the accuracy of your results. A Hounsfield unit threshold that is too low includes soft tissue and overestimates bone volume. A threshold that is too high excludes trabecular bone and underestimates structural integrity. Running a sensitivity analysis on your threshold values and comparing the output against known anatomical measurements takes about fifteen minutes and prevents subtle but significant errors downstream. The skeleton is not a framework. It is a dynamic organ system that trades materials, adapts to load, produces blood cells, and stores minerals. It fails silently until it fails catastrophically. Understanding how it actually works under real conditions, not just how it looks in an anatomy textbook, makes a practical difference in both clinical and research contexts.