Autonomic Function and Clinical Monitoring
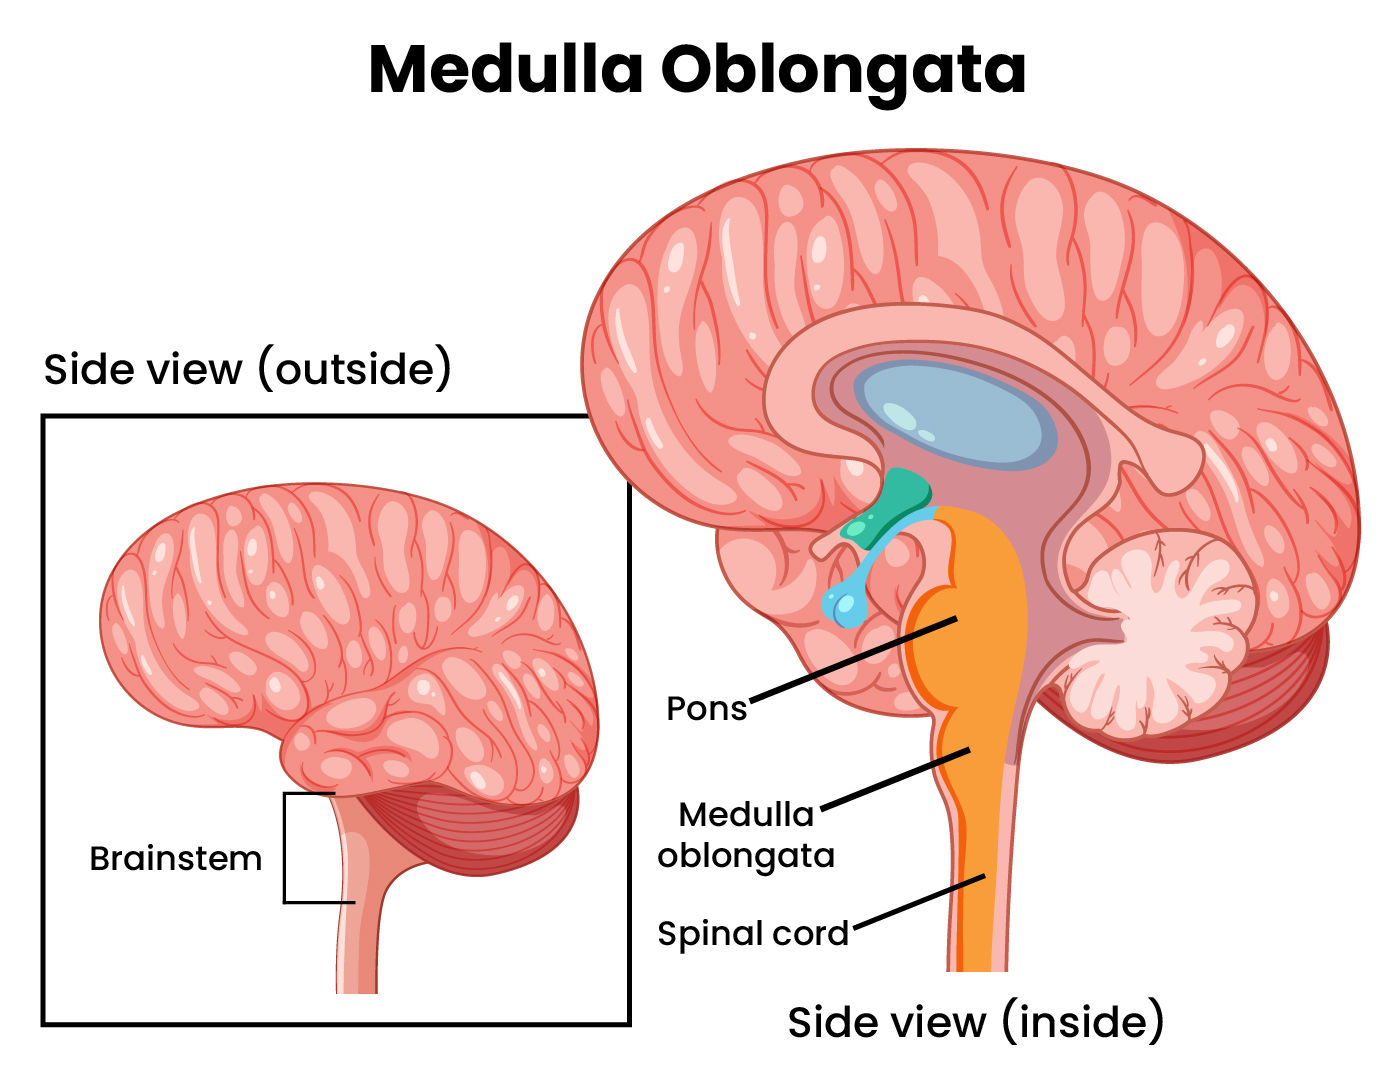
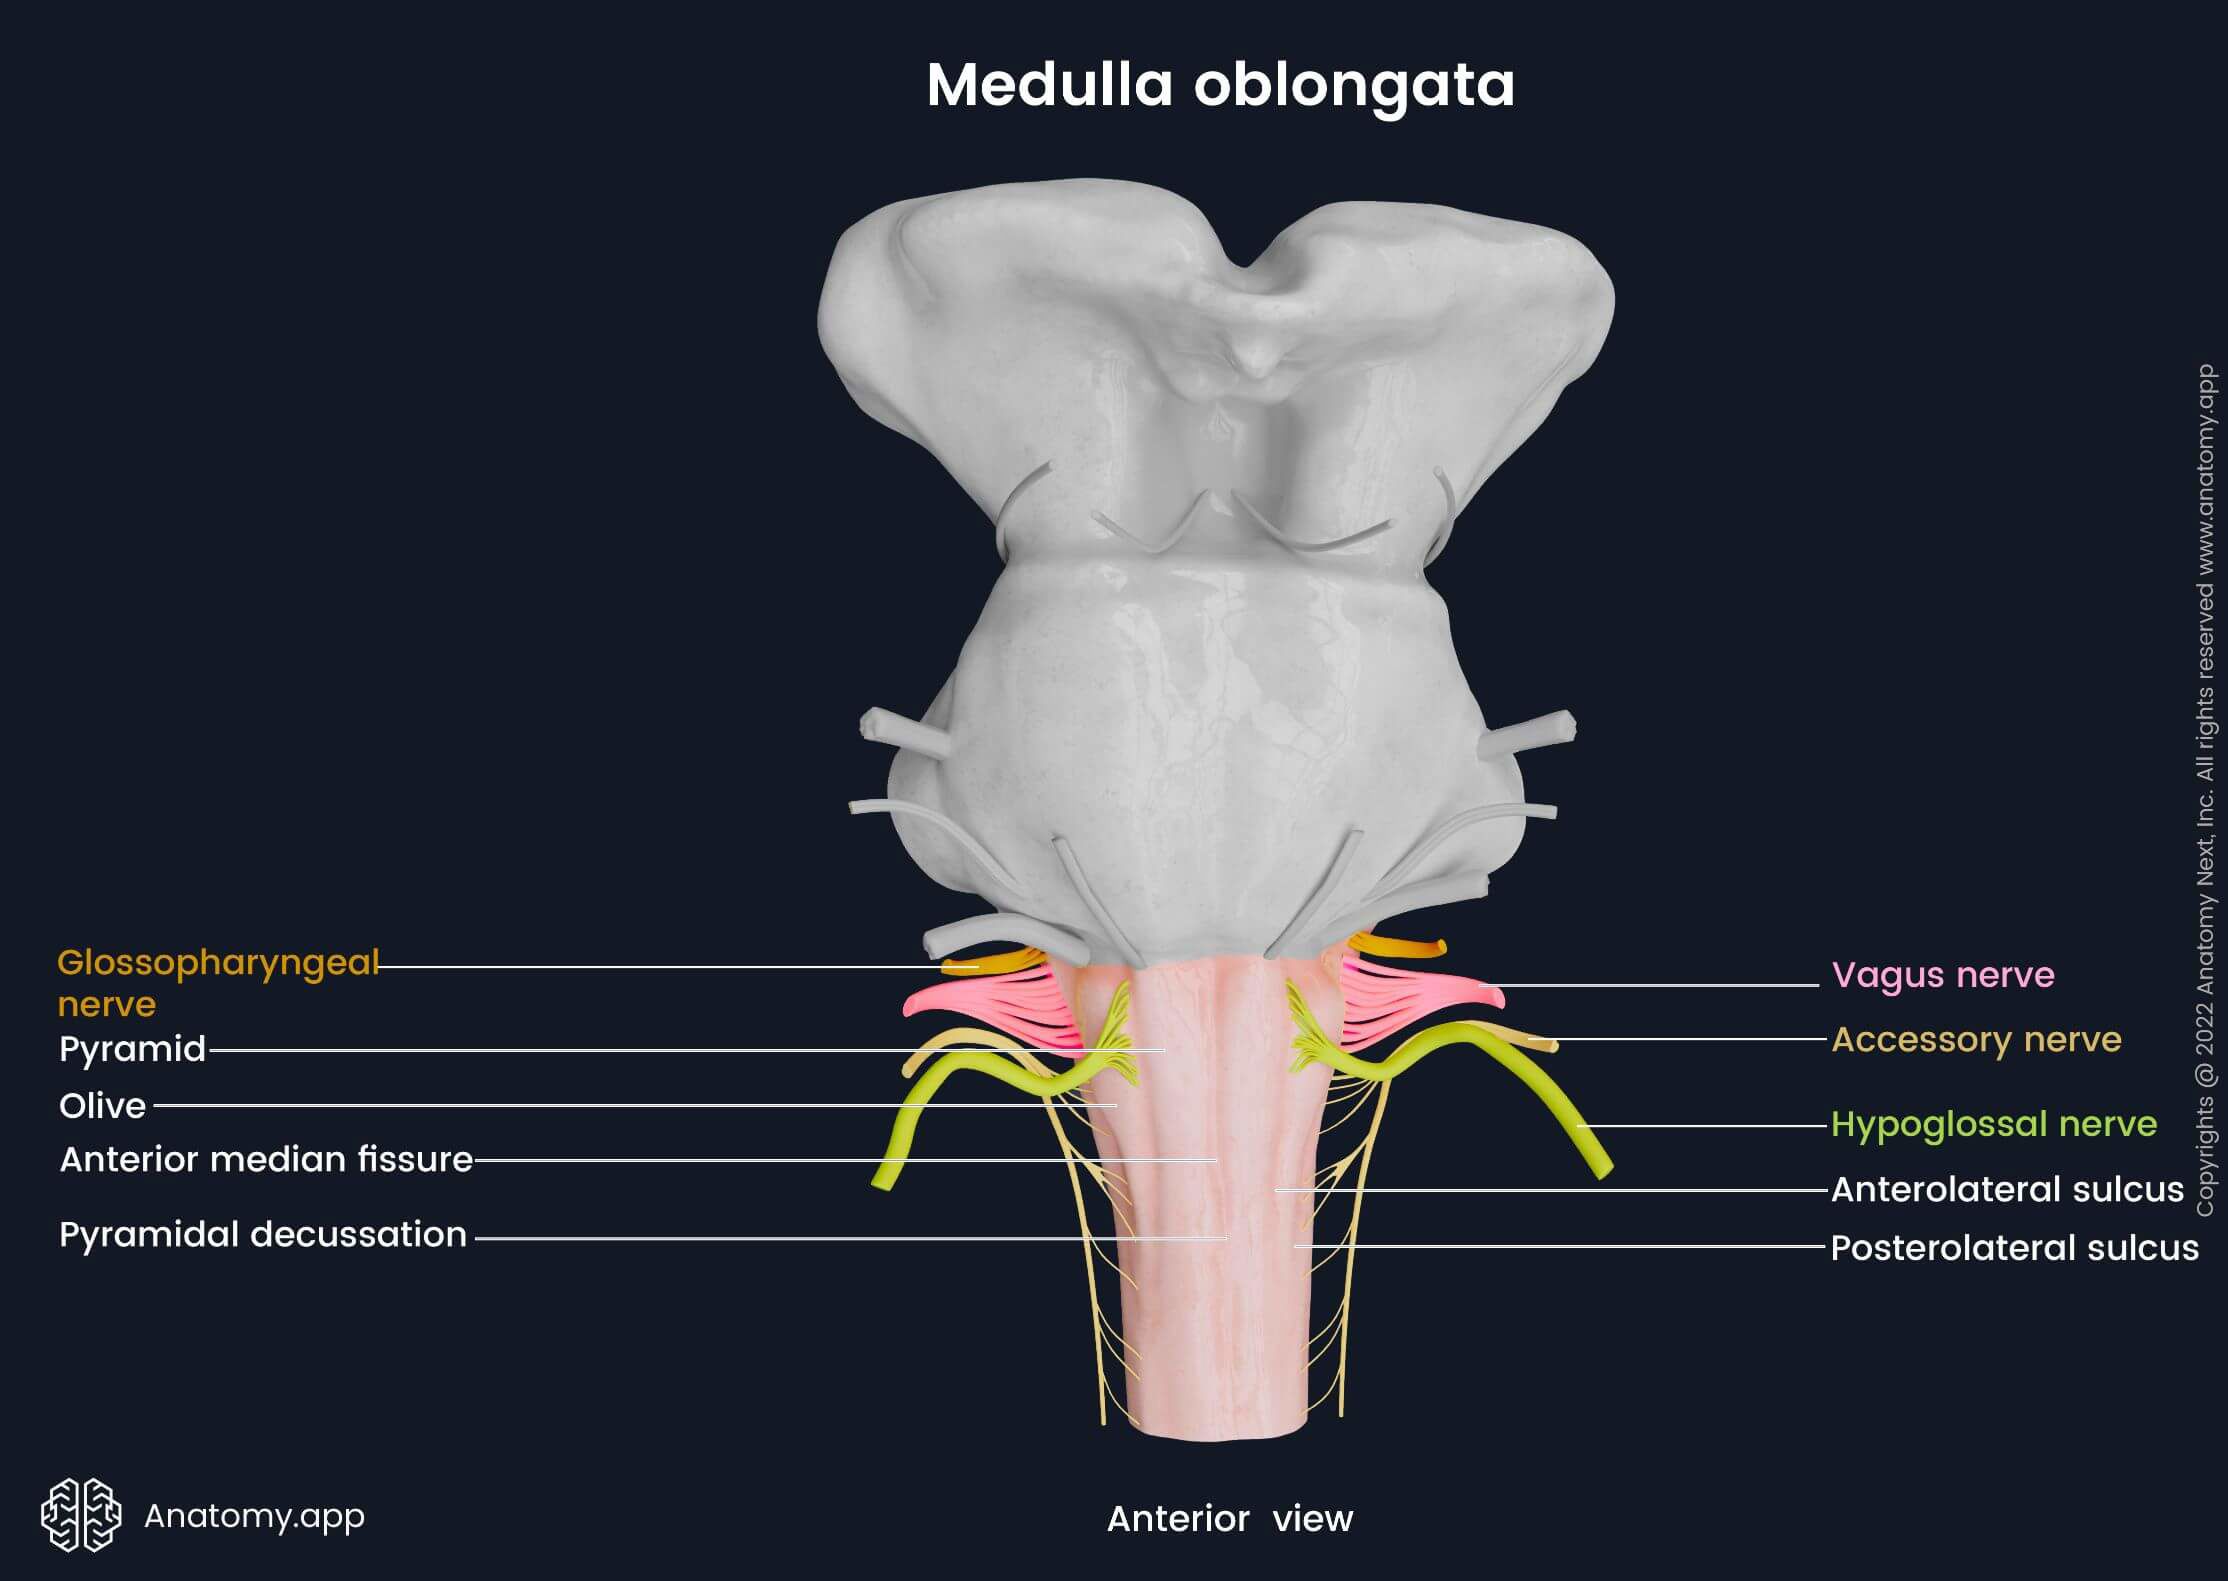
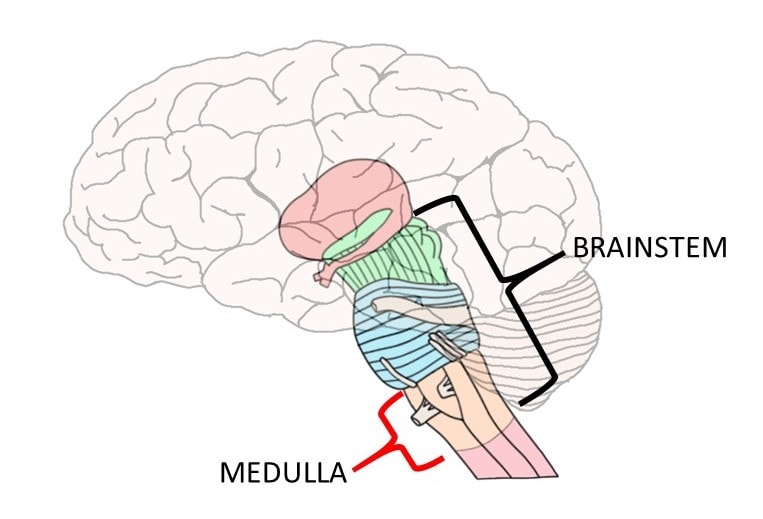
I spent about three years working in a neurocritical care unit before moving into research, and the thing that trips up most people is how much the medulla actually handles without anyone telling it to. You do not notice your breathing until something goes wrong, and that is kind of the whole point of what does the medulla oblongata do, really. It sits at the junction between the brain and spinal cord and runs a bunch of jobs you would not want to do manually. The structure itself is roughly the bottom two inches of the brainstem, right above the spinal cord, and it contains several nuclei that control cardiac rhythm, respiratory drive, vasomotor tone, and reflexes like swallowing and vomiting. The ventral surface is where the pyramids cross, which is why a stroke on one side produces weakness on the other side of the body. The dorsal side has the nucleus solitarius, which takes in taste and visceral sensory information from the glossopharyngeal and vagus nerves. Most textbooks list these as bullet points, but the way it actually works in a living person is more like a set of overlapping feedback loops. The pre-Bötzinger complex generates the basic respiratory rhythm, and then the retrotrapezoid nucleus adjusts that rhythm based on carbon dioxide levels in the blood. If the CO2 goes up even a little, the drive to breathe increases. It is not a simple on-off switch. It is a continuous adjustment that happens whether you are awake or asleep.
I remember one case where a patient with a small posterior fossa lesion started desaturating only when they lay flat. The medulla was partially compressing the respiratory centers, and the effect changed with head position. We ended up managing their sleep with BiPAP and elevating the head of the bed because the normal supine position pushed enough pressure on the brainstem to blunt the drive to breathe. That is the kind of thing you do not learn from a diagram.
Reflex Arcs and Visceral Control
Beyond the rhythmic patterns, the medulla coordinates a lot of protective reflexes. The vomiting center, technically called the area postrema when we are being precise, sits right at the edge of the fourth ventricle and acts as a chemoreceptor trigger zone. It can detect toxins in the blood and cerebrospinal fluid and initiate vomiting through connections to the nucleus tractus solitarius and the dorsal motor nucleus of the vagus nerve. Swallowing works similarly, with the nucleus ambiguus providing the motor output to the pharyngeal and laryngeal muscles. The coordination is tight enough that a disruption here produces dysphagia, which is why medullary lesions often present with difficulty swallowing, hoarseness, and sometimes aspiration. These are not theoretical risks. They are the actual clinical presentations you see in practice. The cardiovascular control comes from the rostroventrolateral medulla, which sends descending fibers to the spinal cord to regulate sympathetic outflow. When blood pressure drops, this area ramps up the signal to constrict blood vessels and increase heart rate. It is basically the body's baroreflex arc, running continuously. If it fails, you get labile blood pressure that can swing dangerously with minimal triggers like bladder distension or pain.
Get the Full Details

I once watched a patient with a medullary infarct develop hypertensive crises every time we repositioned them. The baroreflex was intact but dysregulated, so the normal stimulus of movement triggered an exaggerated sympathetic response. We had to titrate medications carefully and accept that the first few days of mobilization would be rough. The physiology here does not follow a neat protocol.
Clinical Relevance and Limitations
The medulla is vulnerable to compression, ischemia, and inflammation because of its location and the density of critical nuclei packed into a small space. A herniating supratentorial mass can push the brainstem downward and compress the medulla against the tentorium or clivus, leading to rapid respiratory arrest. This is one reason why we monitor neurological status closely in patients with increased intracranial pressure. Lateral medullary syndrome, caused by occlusion of the posterior inferior cerebellar artery or vertebral artery, produces a recognizable pattern of deficits. Patients get ipsilateral facial numbness, contralateral body numbness, ataxia, Horner syndrome, dysphagia, and sometimes respiratory irregularities. The variability depends on exactly which branches are affected and how much tissue is involved. Some presentations are textbook. Most are not. One counterintuitive point that beginners often miss is that the medulla does not work in isolation. It receives heavy input from the pons, midbrain, hypothalamus, and even cortex. The respiratory pattern, for instance, is modulated by higher centers during speech, emotional states, and voluntary breath-holding. Damage higher up can also disrupt medullary function indirectly, which is why localization is sometimes tricky.
The downside of relying on medullary reflexes is that they can be blunted by medications. Opioids suppress the respiratory drive by acting on mu receptors in the medullary chemoreceptor areas. Benzodiazepines and sedatives add to this effect. In practice, this means a patient who looks stable can deteriorate quickly if you do not watch the respiratory rate and end-tidal CO2. The reflexes are still there, but they are dampened. If you are studying this for clinical purposes, the most practical approach is to link each nucleus to its function and then think about what happens when that function fails. The pre-Bötzinger complex affects breathing pattern. The nucleus ambiguus affects swallow and phonation. The rostroventrolateral medulla affects blood pressure stability. The area postrema affects nausea and vomiting. From there, you can build out the syndromes and management strategies. The medulla is not glamorous, but it is essential. It keeps you breathing while you read this sentence. It adjusts your heart rate as you move from sitting to standing. It coordinates your swallow when you take a sip of water. You can take it for granted until something goes wrong, and then it becomes the most important structure in the room. That is the reality of working with autonomic brainstem function.