Breaking Down Medical Language From the Ground Up
Medical terminology feels like a foreign language because it basically is one. Latin and Greek roots merged over centuries, and the result is a system where every word is constructed from three building blocks: a root, a combining vowel, and a suffix or prefix. If you learn the pieces, you don't have to memorize every single term. I spent years transcribing charts and decoding physician notes, and the first thing I ever did was stop trying to read whole words and start parsing them. The core mechanic is simpler than most people expect. Take a root like "cardi" — that's the heart. Attach "-logy" and you get the study of the heart. Attach "-megaly" and you get enlargement of the heart. The suffix does the heavy lifting here, telling you what's happening to the organ or tissue the root names. Without suffixes, medical language would be a list of nouns with no verbs, no conditions, no procedures. The suffix is what turns "hepat" into hepatomegaly, hepatitis, or hepatectomy.
What Does The Suffix Mean In Medical Terms
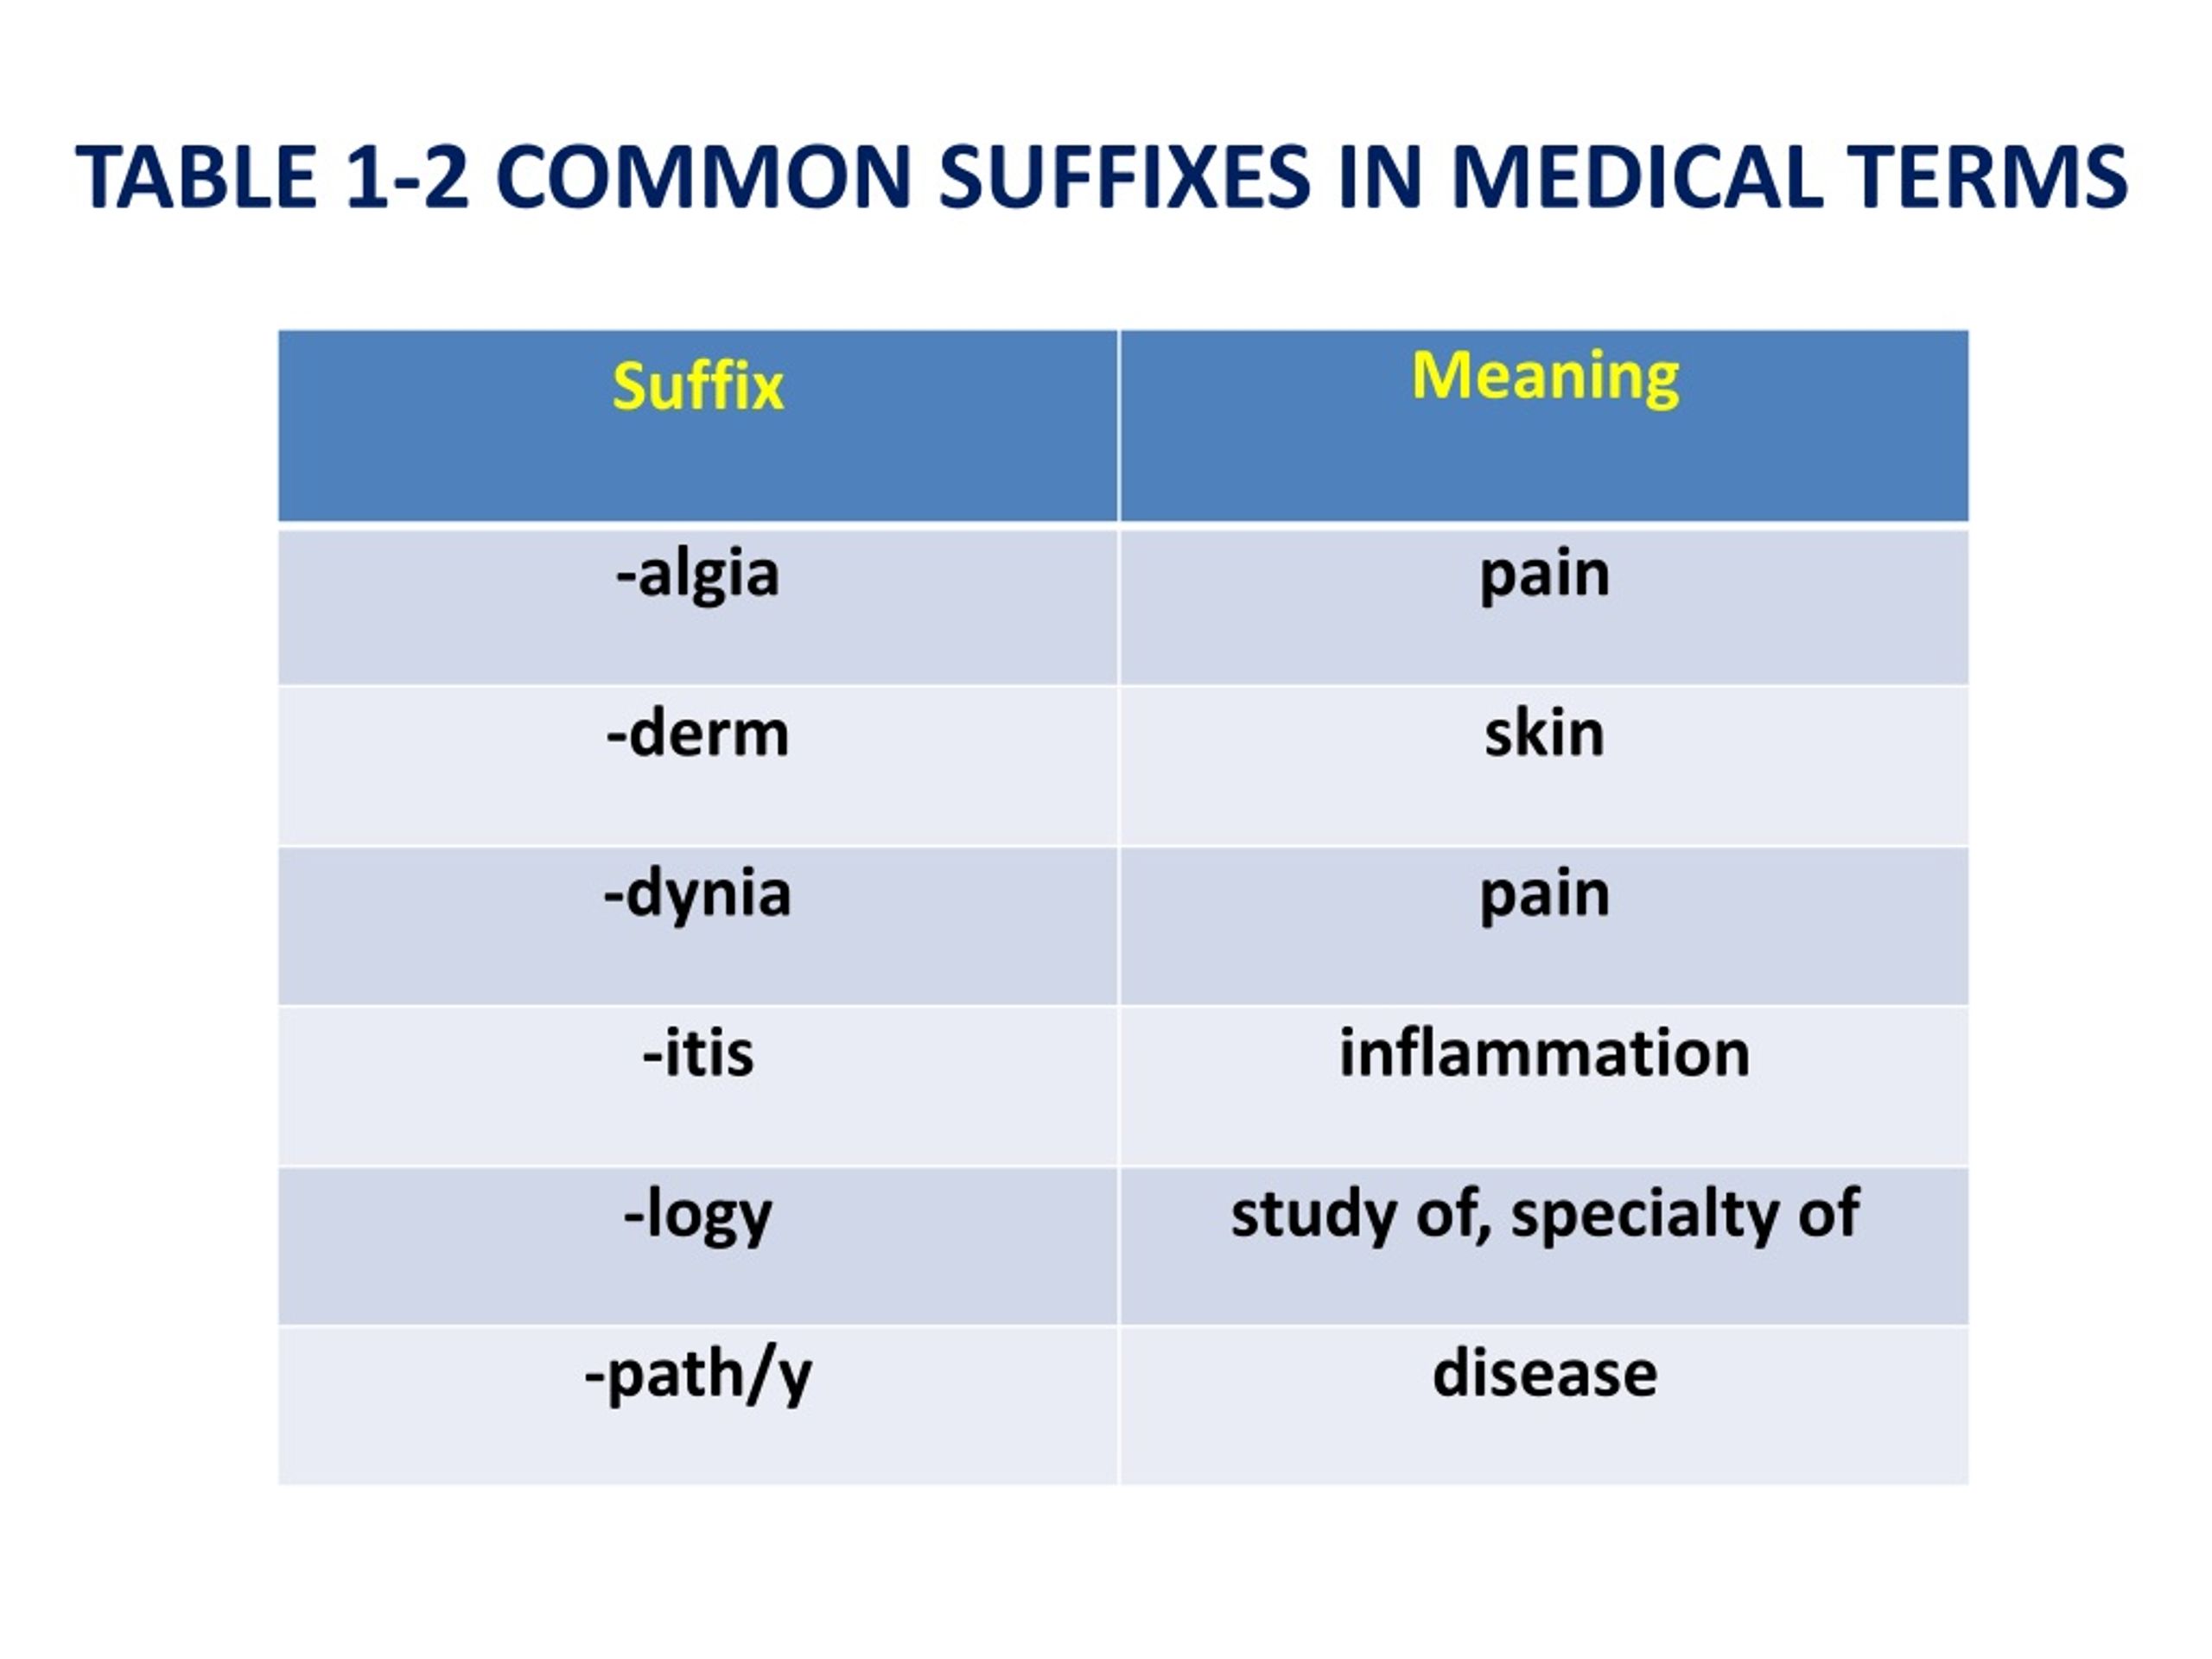
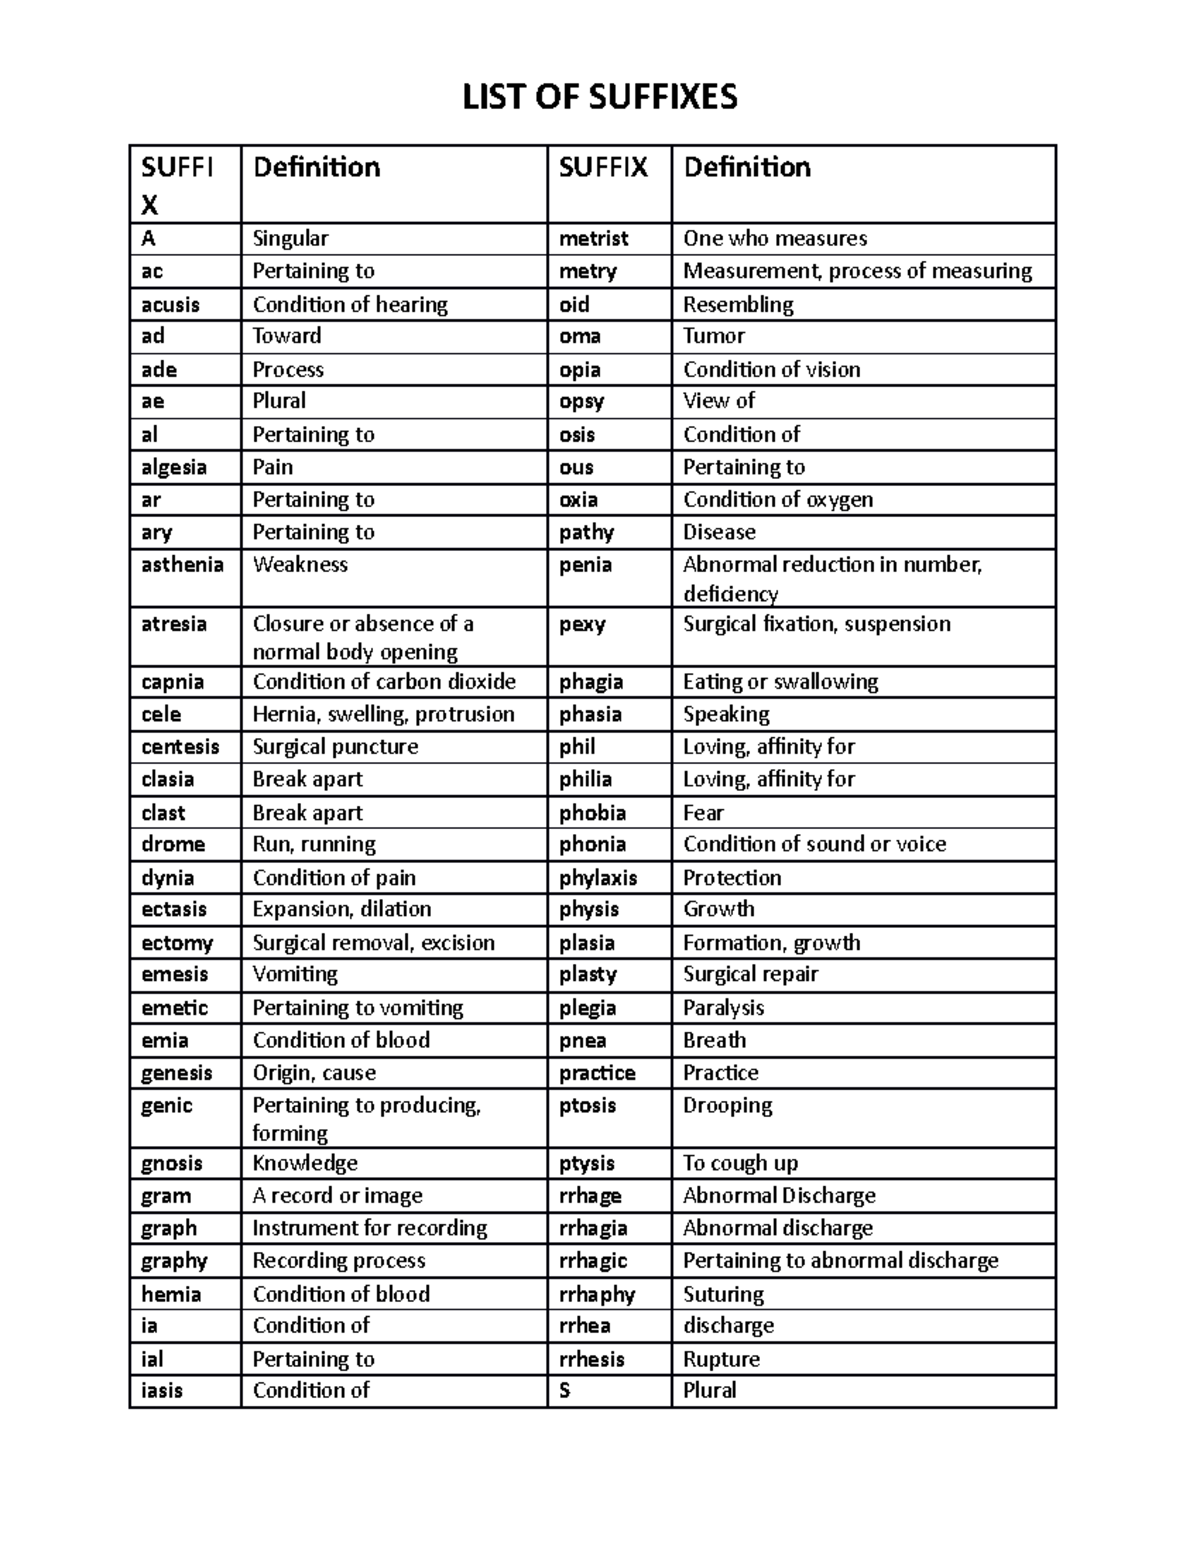
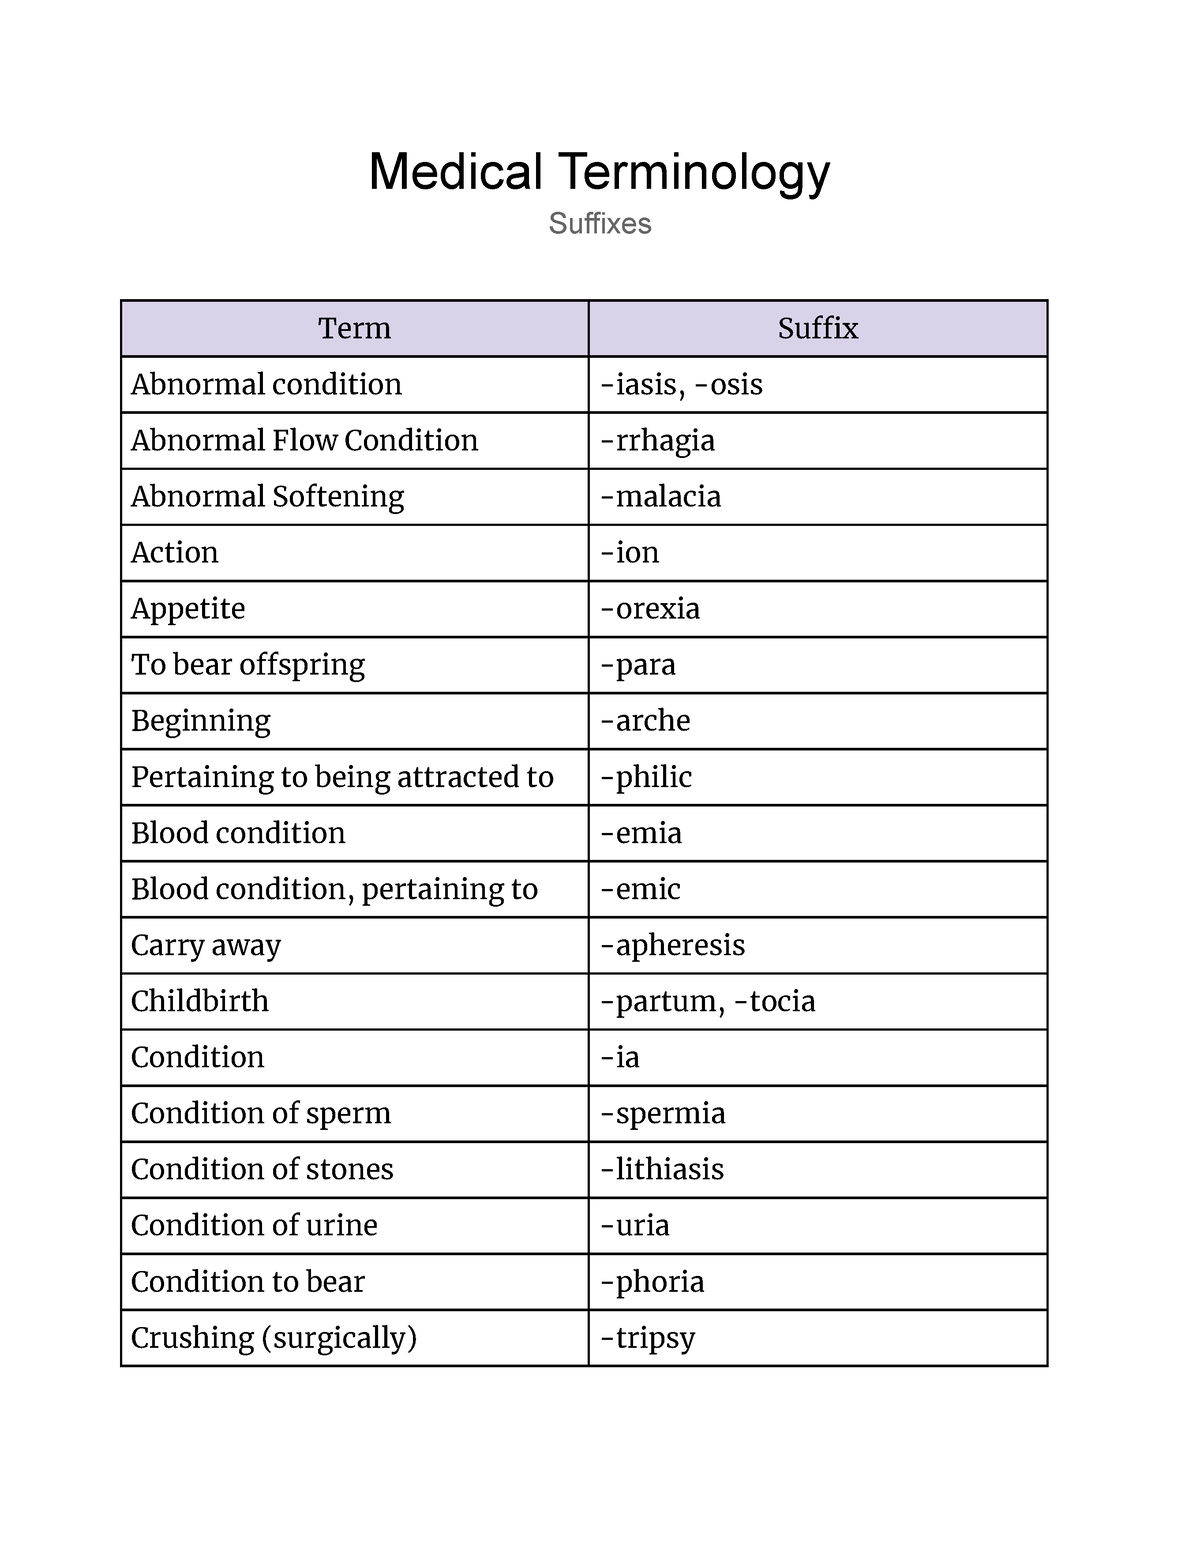
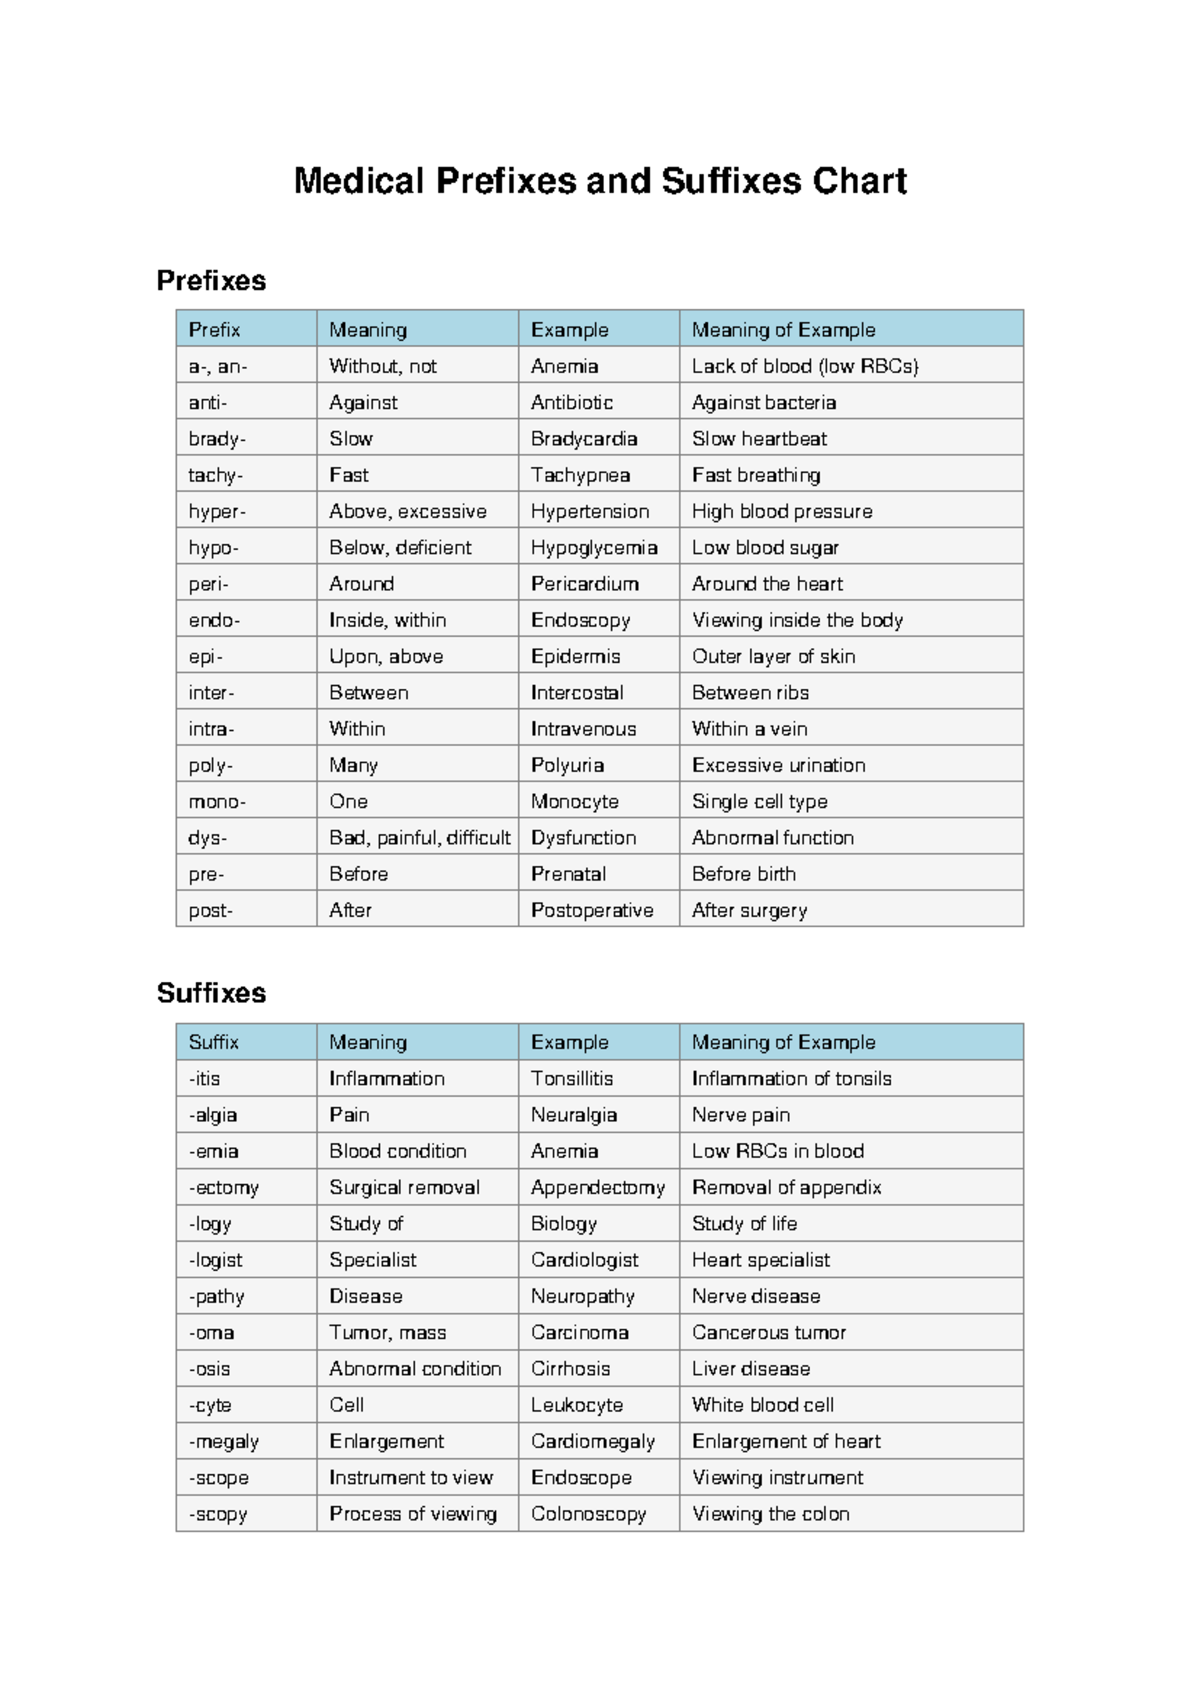
I need to be blunt about how this actually works in practice, because most guides get this wrong. Suffixes in medical terminology don't just describe conditions — they signal entire categories of clinical meaning. The suffix "-itis" doesn't mean "inflammation is present," it means "this term is describing an inflammatory condition." The distinction matters when you're reading quickly. Here's the thing most textbooks skip. Some suffixes are conditionals while others are procedural. "-ectomy" means surgical removal. "-otomy" means surgical incision. People treat these as interchangeable because both involve cutting, but they're completely different actions. I once saw a chart where a physician wrote "cholecystotomy" when the procedure was actually a "cholecystectomy." That's not a trivial swap — one is opening the gallbladder, the other is removing it entirely. A coding error from that mistake alone could cost thousands. The lesson is that suffix accuracy isn't academic, it's operational. The common suffix categories break down roughly like this. Condition suffixes include "-itis" for inflammation, "-megaly" for enlargement, "-pathy" for disease, and "-plasia" for abnormal growth. Procedural suffixes include "-ectomy" for removal, "-otomy" for incision, "-stomy" for creating an opening, "-scopy" for visual examination, and "-graphy" for imaging or recording. Diagnostic suffixes like "-sis" indicate a state or condition, while "-emia" points to a blood-related condition. There's overlap, and the lines blur sometimes, which brings me to the next point.
Combining vowels exist specifically to make pronunciation possible. You don't say "cardiology" as "cardiology" — wait, you do, but the "o" sits between the root and the suffix. When the root ends in a consonant and the suffix begins with one, you almost always insert "o." Cardi- + -logy becomes cardiology. Hepat- + -itis becomes hepatitis. But when the suffix starts with a vowel, the combining vowel drops. Hepat- + -ic becomes hepatic, not hepatonic. This rule has exceptions, and you'll hit them. I ran into a particularly annoying edge case last year. A physician documented "osteopenia" in a patient record but the clinical picture clearly indicated osteoporosis. Both suffixes end in "-penia" meaning deficiency, but the roots carry different implications. "Osteo-" refers to bone generally, and "penia" is deficiency, so osteopenia is a lower-than-normal bone density reading. Osteoporosis uses "-porosis" meaning a condition of breaking or pores. The suffix difference is subtle but clinically massive. I had to flag the chart for clarification because the treatment protocols diverge significantly between the two conditions. It taught me to never assume a suffix readout matches the clinical intent without cross-referencing. Advanced learners should pay attention to suffixes that change meaning based on the root they attach to. "-gia" means pain or flow depending on context. "Cardialgia" is heart pain, but "menorrhexia" and "menorrhagia" involve flow. The same applies to "-trophy" — "- dystrophy" with the prefix "dys-" means bad growth, but "atrophy" standing alone with prefix "a-" means absence of growth. The suffix isn't carrying the full meaning in either case. Context and prefix interaction matter just as much.
Get the Full Details
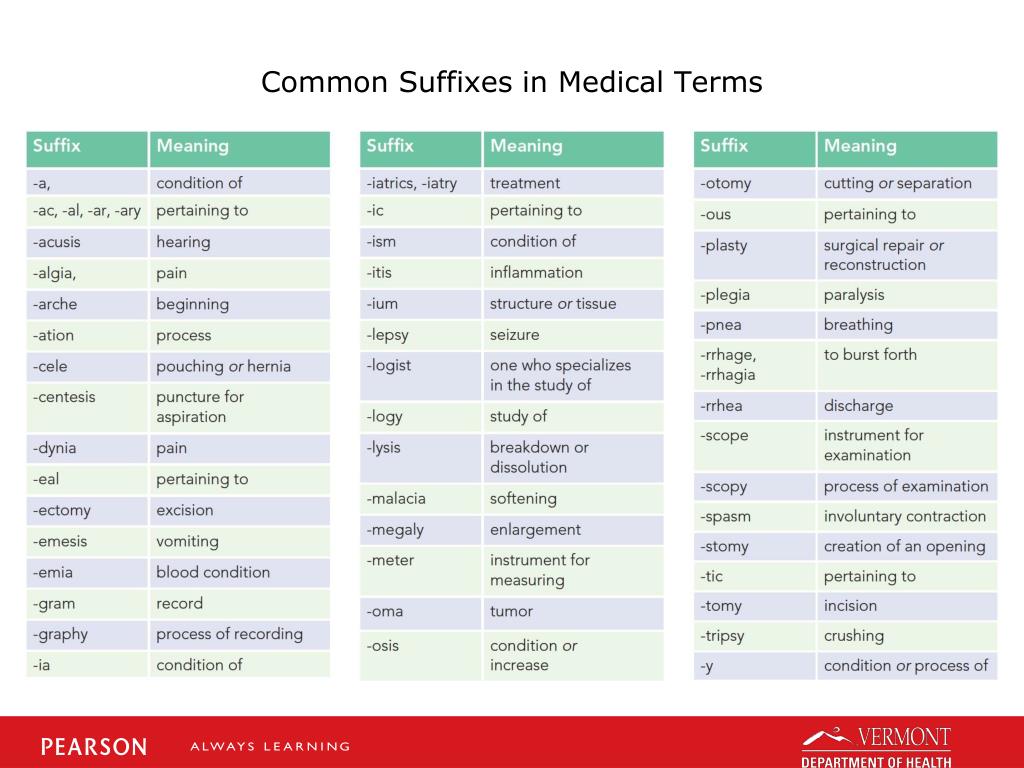
Another practical consideration: abbreviation culture in medical settings actively fights against proper suffix literacy. I've seen shorthand like "MI" for myocardial infarction, "COPD," "CHF" — these bypass the linguistic system entirely and become acronyms you either know or don't. The problem is that new staff and students often learn these as whole words rather than deconstructing them. When they encounter something unusual like "angiodysplasia," they don't know how to approach it because they've been trained to memorize rather than parse. There's also the issue of false friends in suffixes. "-cele" means hernia or swelling in gynecology (cystocele, rectocele), but in neurology "-cele" can refer to a sac or cystic space. "-rrhexis" means rupture in most contexts, but in older texts you'll occasionally see it used more loosely. And "-phobia" means fear, but when attached to medical roots in non-psychiatric contexts it sometimes just denotes an aversion that doesn't meet clinical thresholds. These aren't errors, they're just usage drift that accumulates over decades of medical literature. If you're building competency, start with the top twenty suffixes and drill them until you can recognize them instantly. That list alone covers roughly sixty percent of common terminology you'll encounter in any clinical setting. Learn "-itis," "-ology," "-ectomy," "-scopy," "-emia," "-pathy," "-al," "-ic," "-ous," "-sia," "-sis," "-megaly," "-plasia," "-penia," "-trophy," "-logy," "-gram," "-graphy," "-centesis," and "-stomy." Master those and you can decode terms you've never seen before. Add another fifteen or twenty and you'll handle the vast majority of documentation.
The real test isn't recognizing the suffix in isolation. It's parsing a full term under time pressure while also understanding the clinical implication. I used to time myself reading new admission notes, and the trick was to identify the suffix first, then the root, then any prefix, working backward from the end of the word. Most people read left to right and get tripped up by unfamiliar prefixes. Flip the approach and the suffix anchors you to the category of meaning immediately, which narrows your interpretation range before you even finish the word. One more thing worth noting: medical terminology keeps evolving. New suffixes enter usage through pharmaceutical nomenclature and procedural innovation. "-mab" for monoclonal antibodies, "-nib" for kinase inhibitors, "-vir" for antivirals. These are standardized suffix patterns now, but they're relatively recent additions. Textbooks published before 2015 often don't cover them adequately. Stay aware that the system isn't static. Bottom line on What Does The Suffix Mean In Medical Terms — it means everything. The suffix is the grammatical engine that gives each term its functional meaning. Roots name the subject. Suffixes name the action, condition, or procedure. Prefixes qualify. Get comfortable with the suffix system and medical language stops being a memory exercise and starts being a logical one.