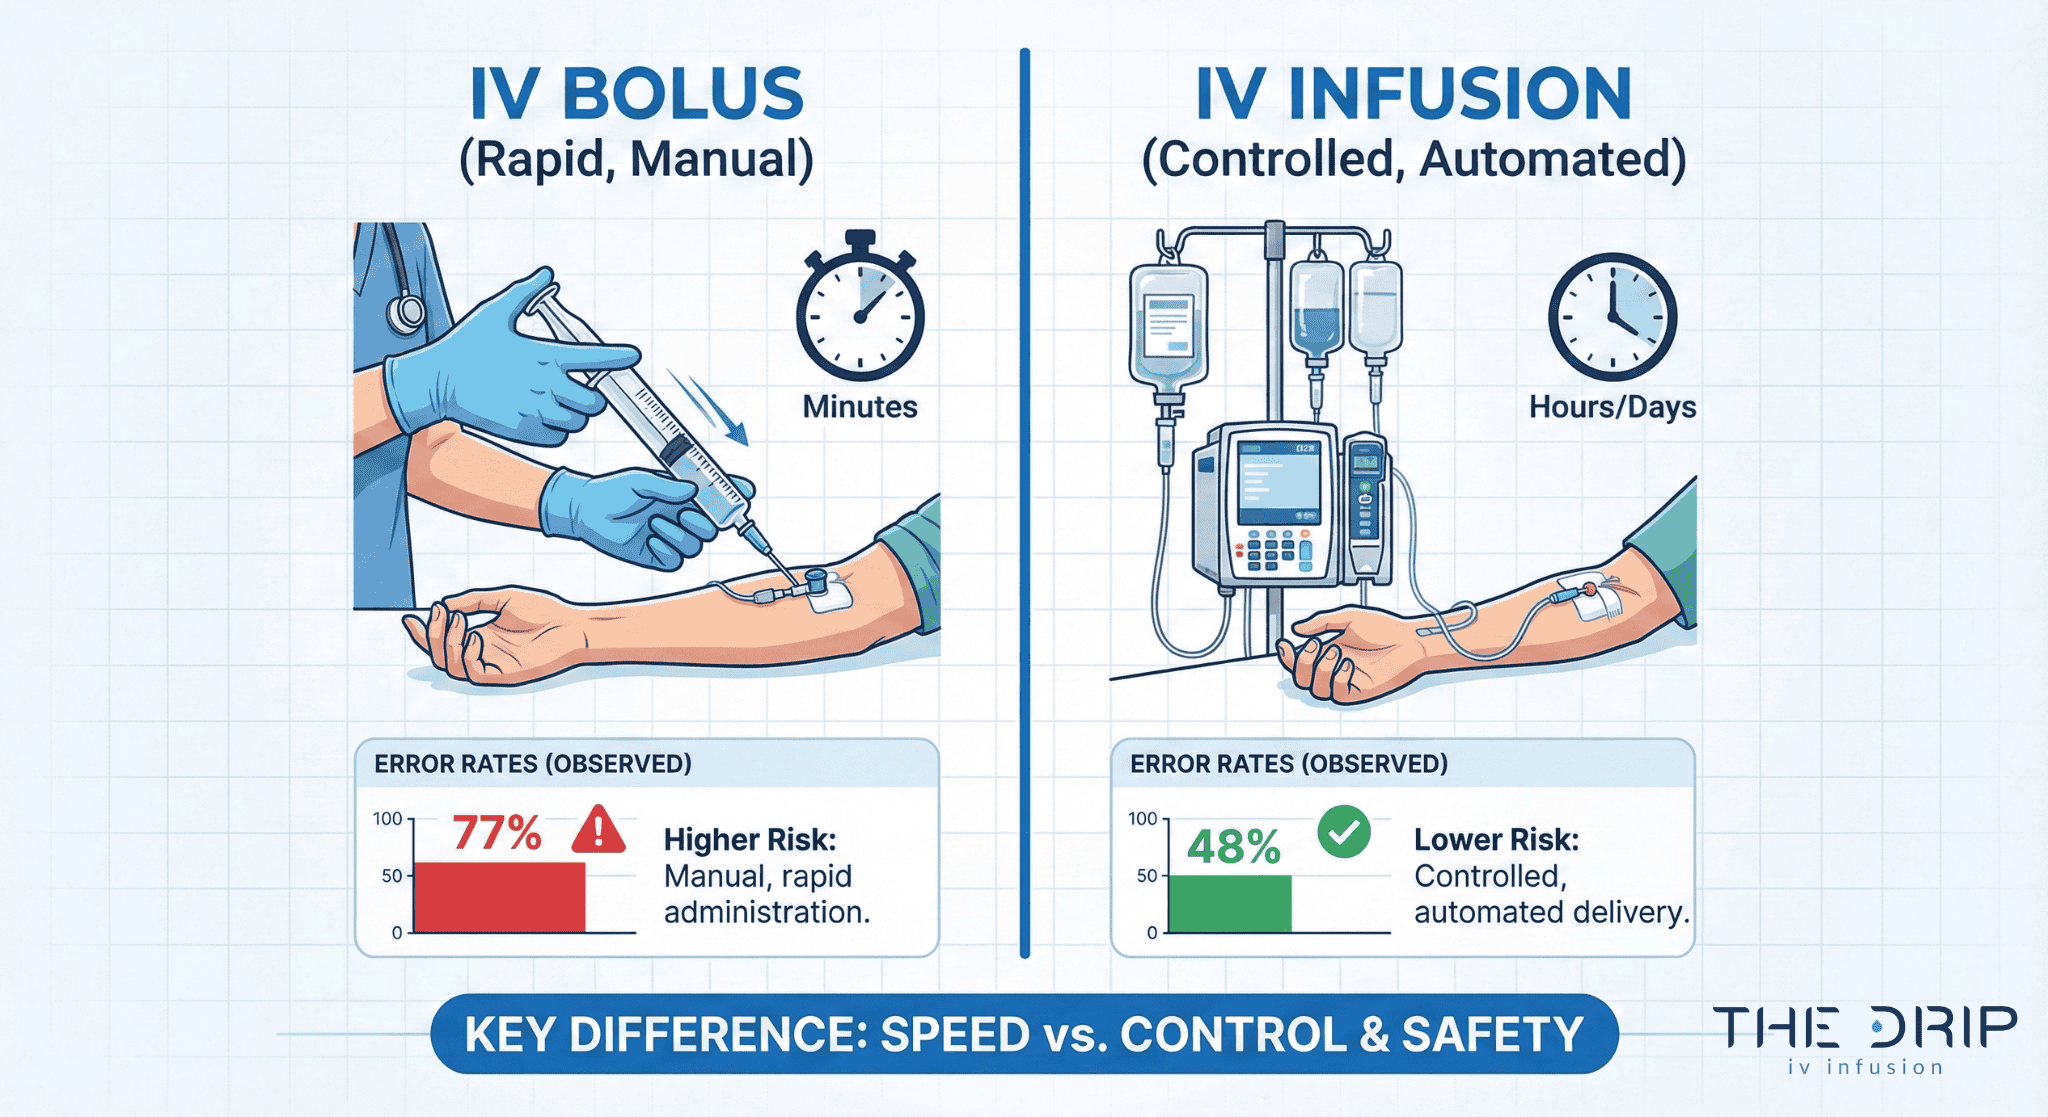
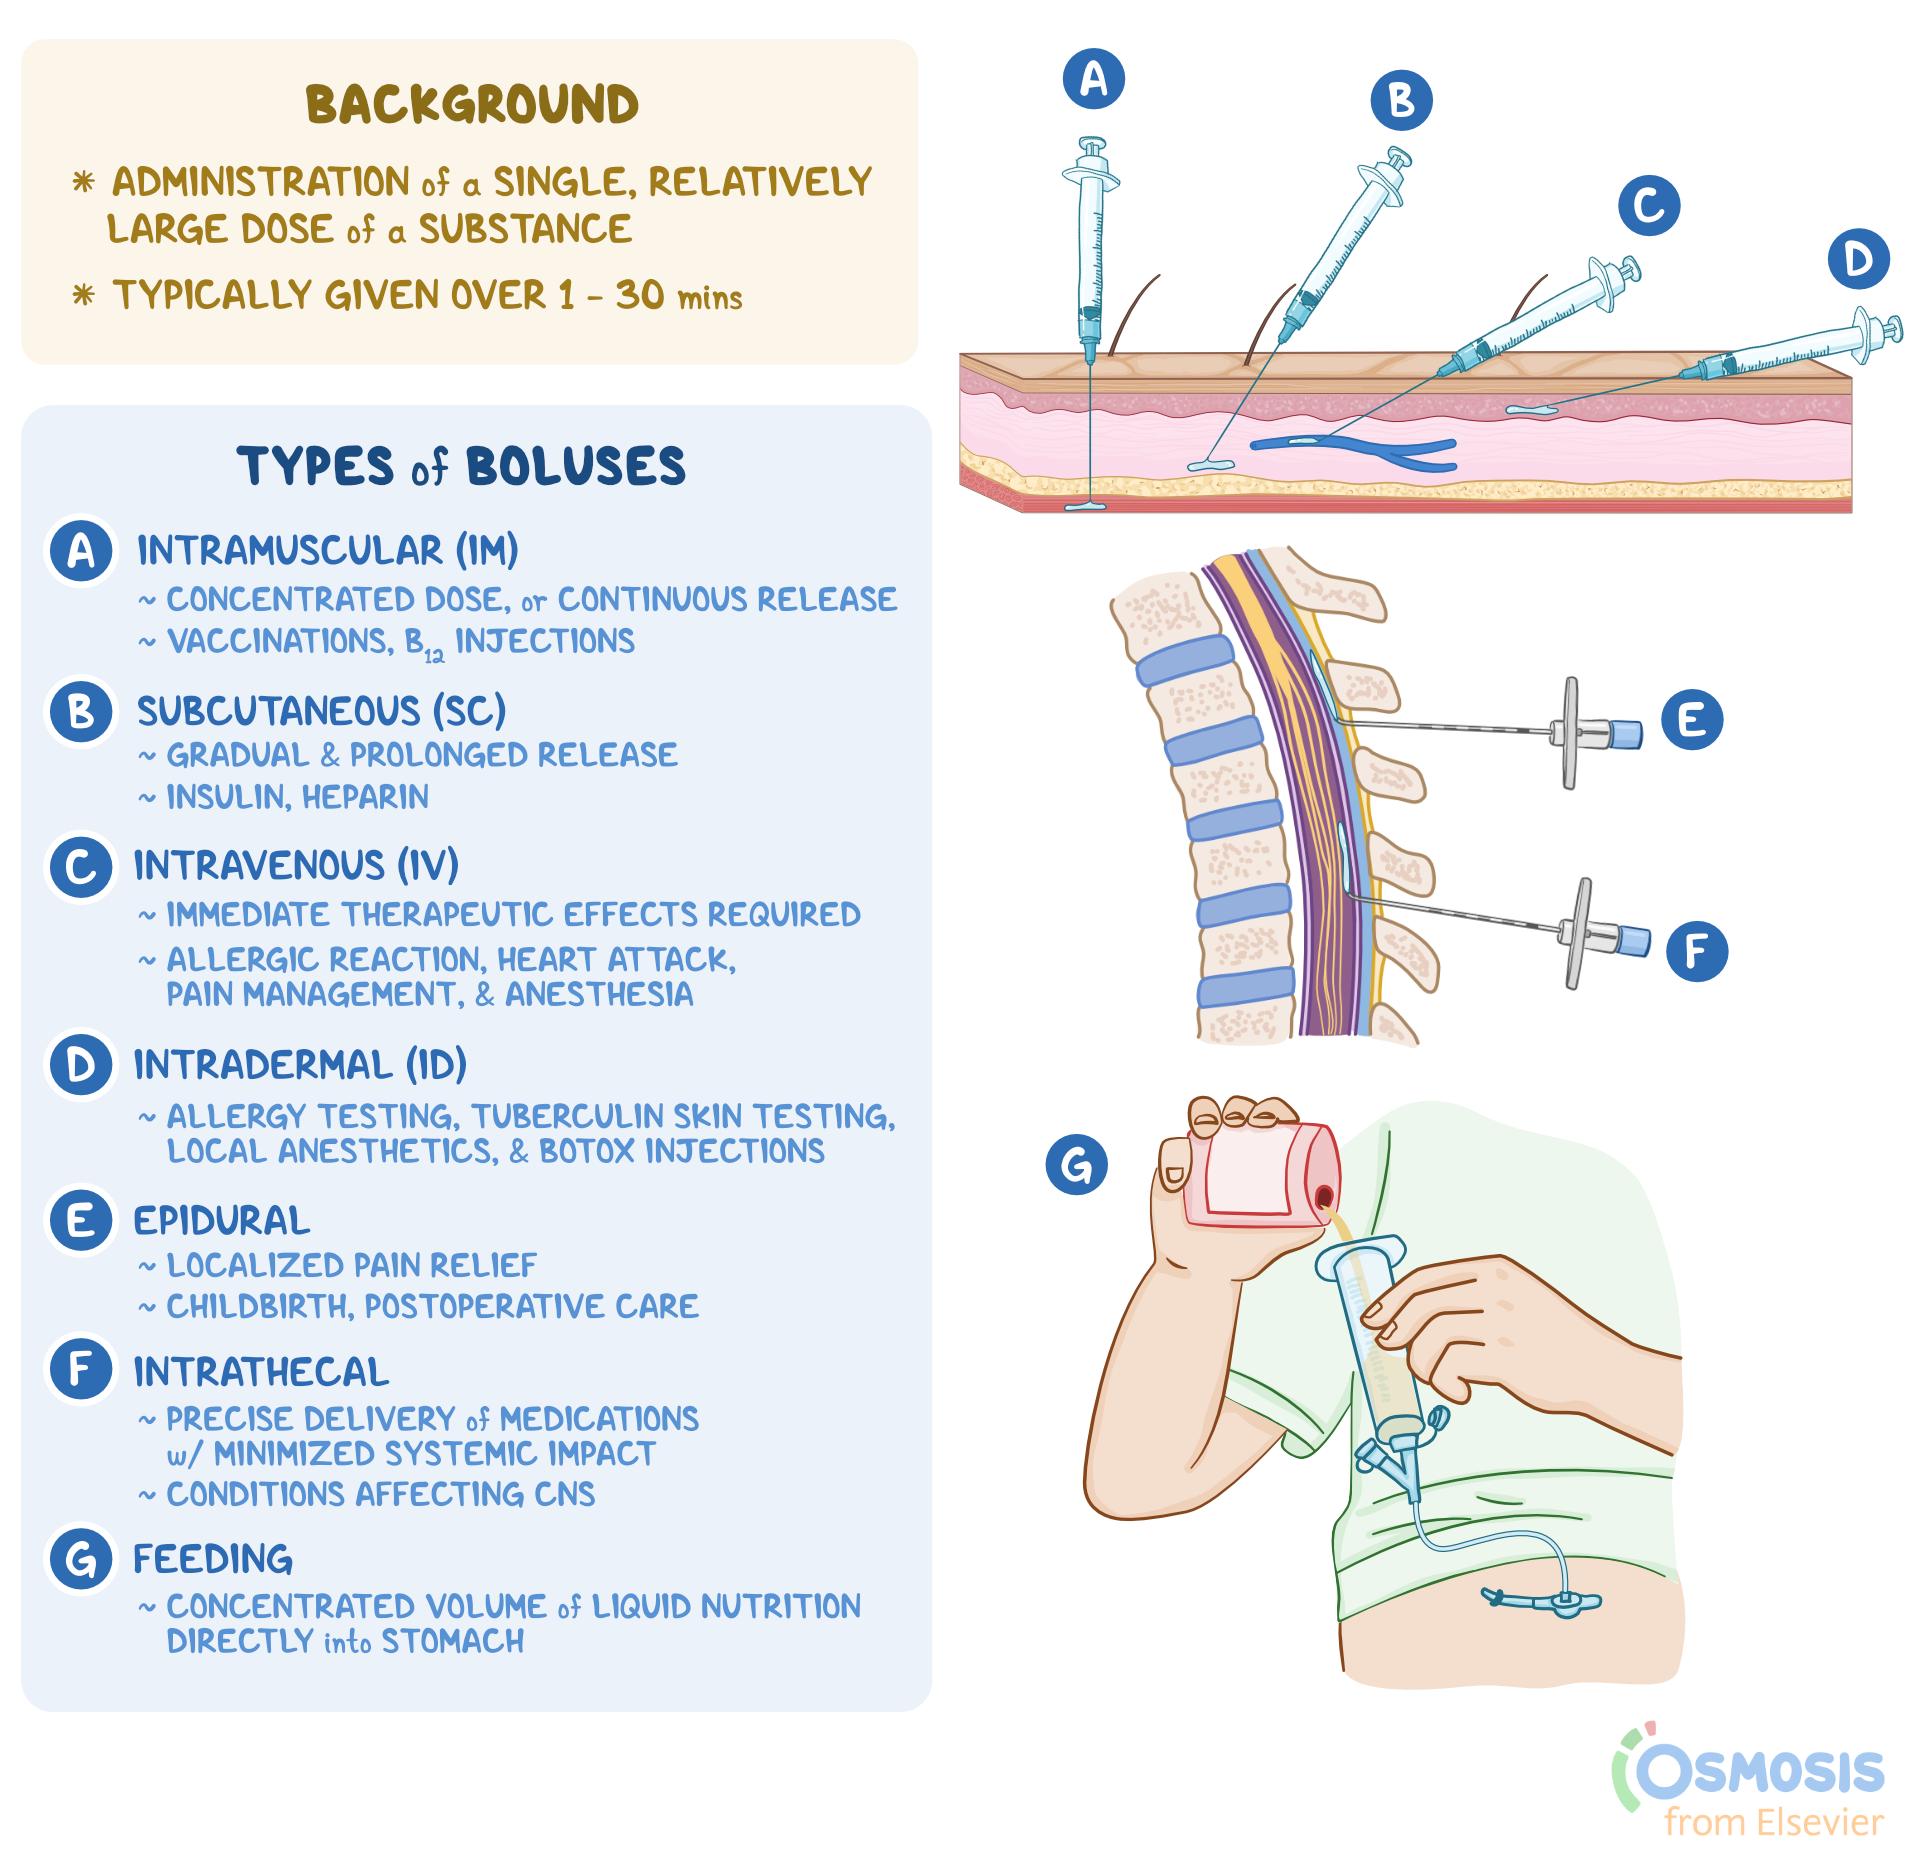
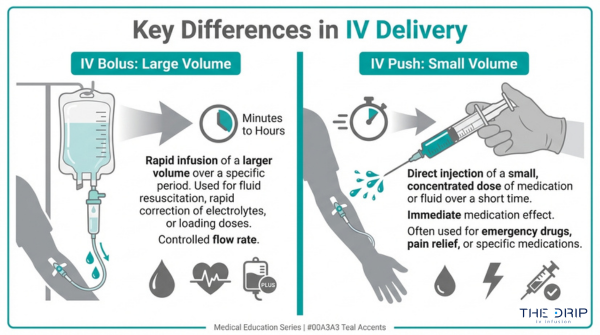
An IV bolus is the rapid delivery of a medication or fluid directly into a vein, usually over seconds to a few minutes. It bypasses the absorption phase entirely, so the drug enters the bloodstream immediately and produces a fast effect. This is different from an infusion, which drips steadily over hours.
What Is A Bolus IV
In practice, a bolus IV means pushing a measured dose through an existing IV line or injecting it into a syringe and administering it quickly. You'll see it documented as "IV push" or "stat bolus" on order sheets. The key word is speed and single-dose delivery.
I've watched nurses and doctors manage bolus doses in high-acuity settings, and the margin for error is small. A dose meant for 2 minutes accidentally pushed over 10 minutes changes the pharmacokinetics entirely. In one case, a potassium bolus was administered too rapidly, causing a transient arrhythmia that resolved only after stopping the push and monitoring rhythm. The lesson was straightforward: verify the rate before you break the seal on any vial.
When Bolus IV Makes Sense
Bolus IV is appropriate when you need immediate drug levels. Emergency medications like epinephrine in cardiac arrest, dextrose for severe hypoglycemia, or naloxone for opioid overdose are classic examples. Rescue antibiotics before culture results, antiemetics for intractable vomiting, and calcium gluconate for hyperkalemia also rely on bolus delivery.
Continuous infusion would be wasteful or too slow for these scenarios. The patient needs the effect now, not in an hour.
How to Prepare and Administer
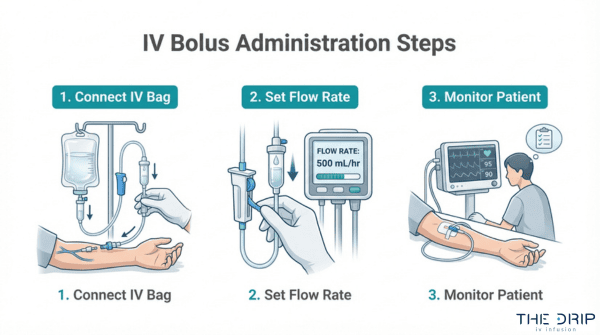
Start by confirming the order. Write it down. Verify the drug, dose, route, and rate. Check expiration dates and solution clarity. Draw up the medication into a syringe, purge the line, and attach it to the IV port closest to the patient. Clamp the infusion line if needed. Push the plunger at the rate specified in the drug monograph or protocol.
Typical bolus rates range from 1 to 5 minutes for most medications, though some drugs require slower pushes. Diazepam, for example, should be given over at least 5 minutes to reduce vein irritation and respiratory depression risk. Morphine bolus? Go slow, maybe 2 to 4 minutes, and watch the respiratory rate.
I once worked a shift where a routine bolus of IV magnet sulfate was nearly given unduly fast. The order read "give over 1 minute," but standard practice for that concentration is closer to 5 minutes. I flagged it, slowed the push, and the patient tolerated it without issues. The workaround was simply cross-referencing the hospital formulary and asking the pharmacist to confirm.
Pitfalls and Counter-Intuitive Insights
Beginners often assume faster is better for bolus IV. That assumption can be dangerous. Some drugs cause phlebitis, hypotension, or arrhythmias when pushed too quickly. The rate matters more than the volume.
Another common mistake is mixing bolus and infusion orders. If a patient is on a continuous drip and you need a bolus dose, you must account for the ongoing infusion rate when calculating total drug exposure over the next hour. Missing this can lead to accidental overdose.
Not every drug is suitable for bolus IV. Vesicants, certain antibiotics, and electrolyte concentrates may require dilution or slow infusion instead. Always check the compatibility guide before committing to a push.
Monitoring After Bolus IV
Watch the patient. Vital signs, symptom response, and adverse effects should be assessed within minutes of completion. Document the time, dose, route, and site condition. If the medication carries a black box warning or narrow therapeutic index, increase monitoring frequency accordingly.
Bolus IV is a powerful tool when used correctly. It delivers medicine fast, bypasses the gut, and buys time in emergencies. But it demands attention to rate, compatibility, and patient response. Get those three right, and the technique serves you well. Miss any of them, and the consequences can be immediate and severe.
Gallery What Is A Bolus Iv
What Is IV Bolus?
What is IV bolus? - Orion Health & Wellness Services
Bolus: What Is It, Different Types, Indications, and More | Osmosis
IV bolus vs push: Difference Between IV Bolus and IV Push
IV bolus vs push: Difference Between IV Bolus and IV Push