The Practical Reality of Controls in Experiments
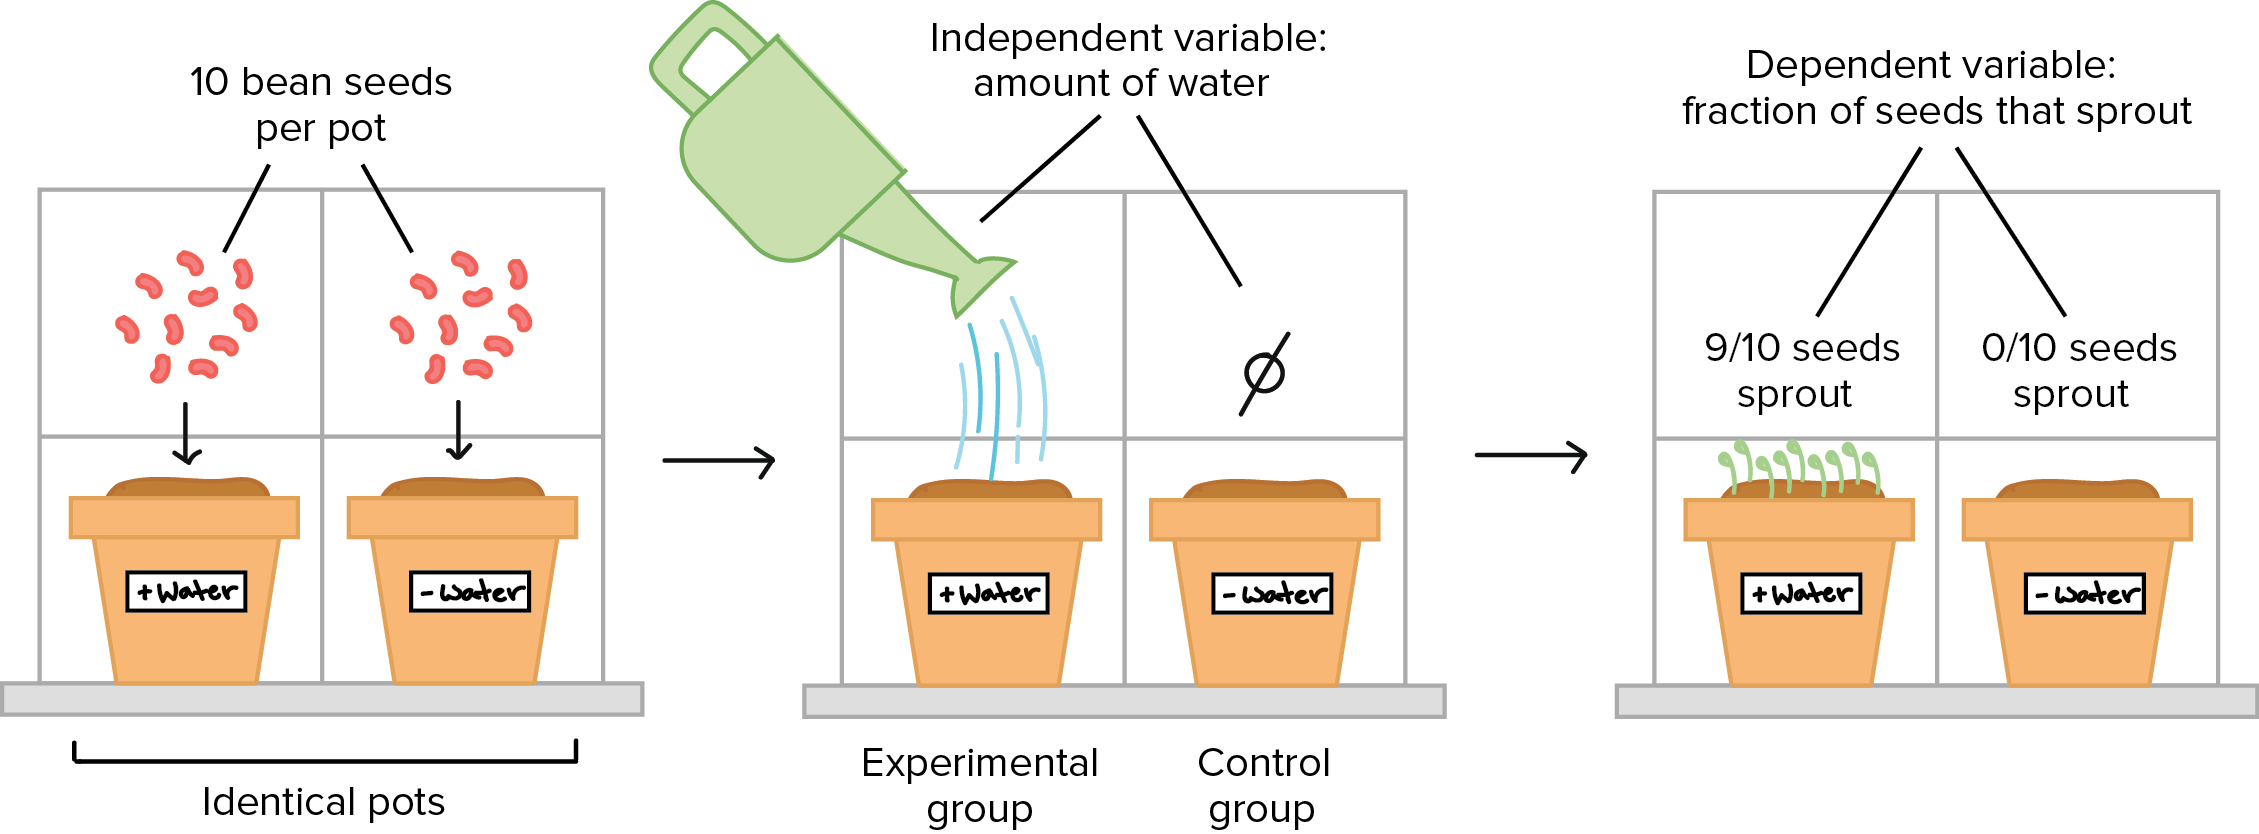
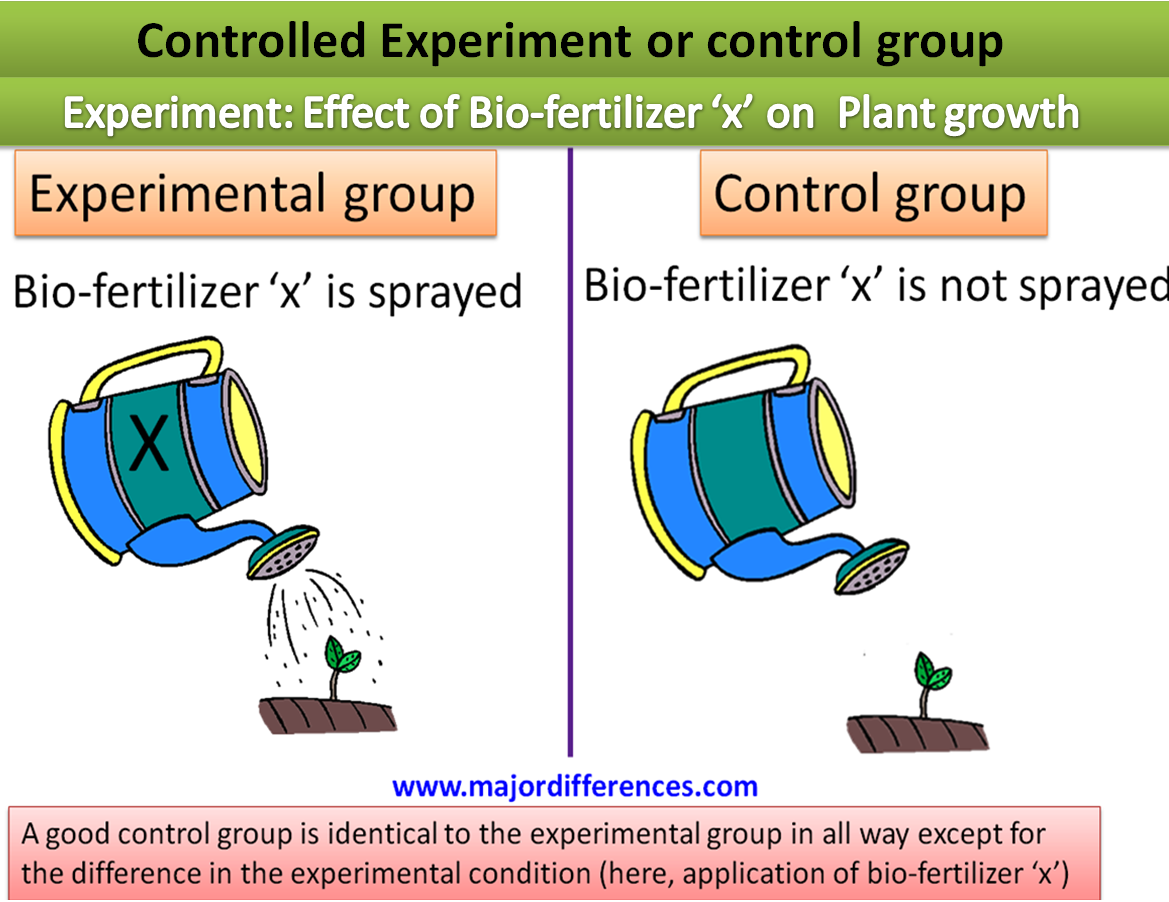
A control group is the condition where the experimental treatment is not applied. You measure it alongside the treatment group so you can isolate what actually changed. Without it, you have no baseline. Everything you observe could be noise, a time effect, or an environmental drift. Controls exist to rule those things out. The definition is simple. The execution is where people make expensive mistakes. I have watched researchers spend months on data collection only to realize the control group was exposed to a different light cycle, a different batch of reagents, or a different technician than the treatment group. By that point, the experiment was already compromised. You can detect some of these issues during analysis, but you cannot fix them after the fact.
What Is A Control In Experiment
A control is any condition held constant so the variable you are testing can be isolated. This includes a control group, a control condition, and sometimes a control measurement taken before the treatment starts. Positive controls confirm the system can respond. Negative controls confirm the system stays quiet without treatment. Sham controls account for procedural effects. Each type solves a different threat to validity, and choosing the right one matters more than most people realize. I ran a soil amendment trial a few years back where the treated plots were in one greenhouse section and the control plots were in another. I assumed the difference was negligible. It was not. The control section had a slightly higher ambient temperature due to a HVAC vent nearby. Plant growth in the controls ran faster, and the treatment effect looked smaller than it actually was. I caught it when I noticed the temperature log was inconsistent across sections. I moved everything to the same area on randomized benches and re-did the trial. It added six weeks to the timeline, but the revised data was publishable. The original data was not.
Why People Get Controls Wrong
The most common mistake is assuming the control automatically accounts for everything. It does not. A control only isolates the variable you deliberately keep constant between groups. If the control and treatment differ on an unmeasured factor, that factor becomes a confounder. You will never know what caused the result unless you measure and block for it. Another frequent error is using the wrong type of control for the question. A no-treatment control in a behavioral study may show that the procedure itself causes an effect, not the treatment. That is why sham controls exist. If you administer a drug via injection, your control should receive an injection of saline, not nothing. The needle stress, handling, and vehicle matter. They change the outcome independently of the active compound. I also see people skip controls in pilot work and then act surprised when the full study fails. Pilot data without a control is descriptive at best. It tells you whether the system works, not whether your treatment causes the effect you think it does. Do not treat pilot results as confirmation.
Get the Full Details

How to Design a Control That Actually Works
Randomization is the first requirement. Assign subjects or plots randomly to control or treatment conditions. This spreads confounding variables across groups and makes statistical comparison valid. Systematic assignment, like putting all large subjects in one group, destroys the purpose of the control entirely. Matching is useful when randomization is impractical, but it has limits. You can only match on variables you measure. Unmeasured differences remain uncontrolled. Use matching when sample sizes are small and randomization produces uneven groups, but acknowledge the limitation explicitly in your methods section. Blinding reduces measurement bias. If the person recording outcomes knows which group a subject belongs to, they may unconsciously record results in favor of the expected direction. Double-blinding, where neither the subject nor the measurer knows the assignment, is the gold standard for clinical work. Single-blinding helps in agricultural and industrial trials where blinding the treatment is impossible but blinding the assessor is feasible.
Replication within the control matters as much as replication in the treatment. A control with five samples and a treatment with fifty gives you no power to detect differences. Balance your sample sizes or use a statistical design that accounts for imbalance, like an ANCOVA with baseline covariates.
When Controls Fail Completely
Controls do not solve every problem. They are ineffective in exploratory research where the mechanism is unknown and you are generating hypotheses rather than testing them. They are also problematic when ethical constraints prevent a true control condition, such as withholding a proven treatment from a patient group. In those cases, you use an active control instead of a placebo, but you lose the ability to separate the treatment effect from the control treatment effect. Long-term studies introduce another failure mode. Controls drift over time. Subjects age, environments change, reagents degrade. A control measured at the start of a year-long study is not the same control at the end. You need interim controls or repeated baseline measurements to catch drift. I once saw a six-month toxicity study where the vehicle control showed increasing mortality halfway through due to a contaminated water supply. The treatment group looked fine because it was affected differently. The control data would have been discarded as noise if they had not caught it early. Regular monitoring of the control is not optional. Controls also add cost and complexity. Every additional control group consumes resources. In large-scale clinical trials, a placebo control can cost millions to run. Active-controlled non-inferiority trials are often more practical, though they answer a different question. Know what you are optimizing for before you design the control arm.
Analysis Without Overclaiming
Statistical comparison between control and treatment is the output, but the interpretation requires caution. A significant difference means the groups diverged. It does not tell you the size of the effect, the mechanism, or the practical importance. Always report effect sizes alongside p-values. A tiny effect can be statistically significant with enough sample size while being meaningless in practice. Check the control group first during analysis. If the control shows unexpected variation or a systematic shift, the treatment comparison is suspect. Investigate before publishing. I have reviewed papers where the control variance was three times larger than the treatment variance, and the conclusion rested entirely on a borderline p-value. Those results rarely replicate. Finally, document the control thoroughly. A methods section that says "control group received standard care" is useless. Standard care varies by location, by time, and by provider. Specify what the control received, how it was administered, and how it was monitored. Future readers and reviewers need enough detail to evaluate whether the control was adequate for the claim.



