So you want to understand what a gene actually is
Let's skip the textbook definition for a second. In practice, a gene is a stretch of DNA that your lab needs to identify, sequence, and interpret against a reference. That's the day-to-day reality. Everything else—the textbook language, the elegant diagrams—comes after you've already spent three hours trying to figure out why your variant caller is reporting nonsense at the edges of a locus. I remember working through a clinical exome dataset a few years back where we kept seeing false-positive pathogenic calls in a particular gene region. It turned out the reference genome had a gap there—a known artifact in GRCh37—and any sample with a deletion in that spot would get miscalled as homozygous reference. The workaround wasn't fancy. We anchored our analysis to GRCh38, used the decoy sequences, and re-ran the caller with stricter filters. Saved us about two weeks of headache. That's the kind of thing nobody tells you when they're introducing the concept.
What Is A Gene
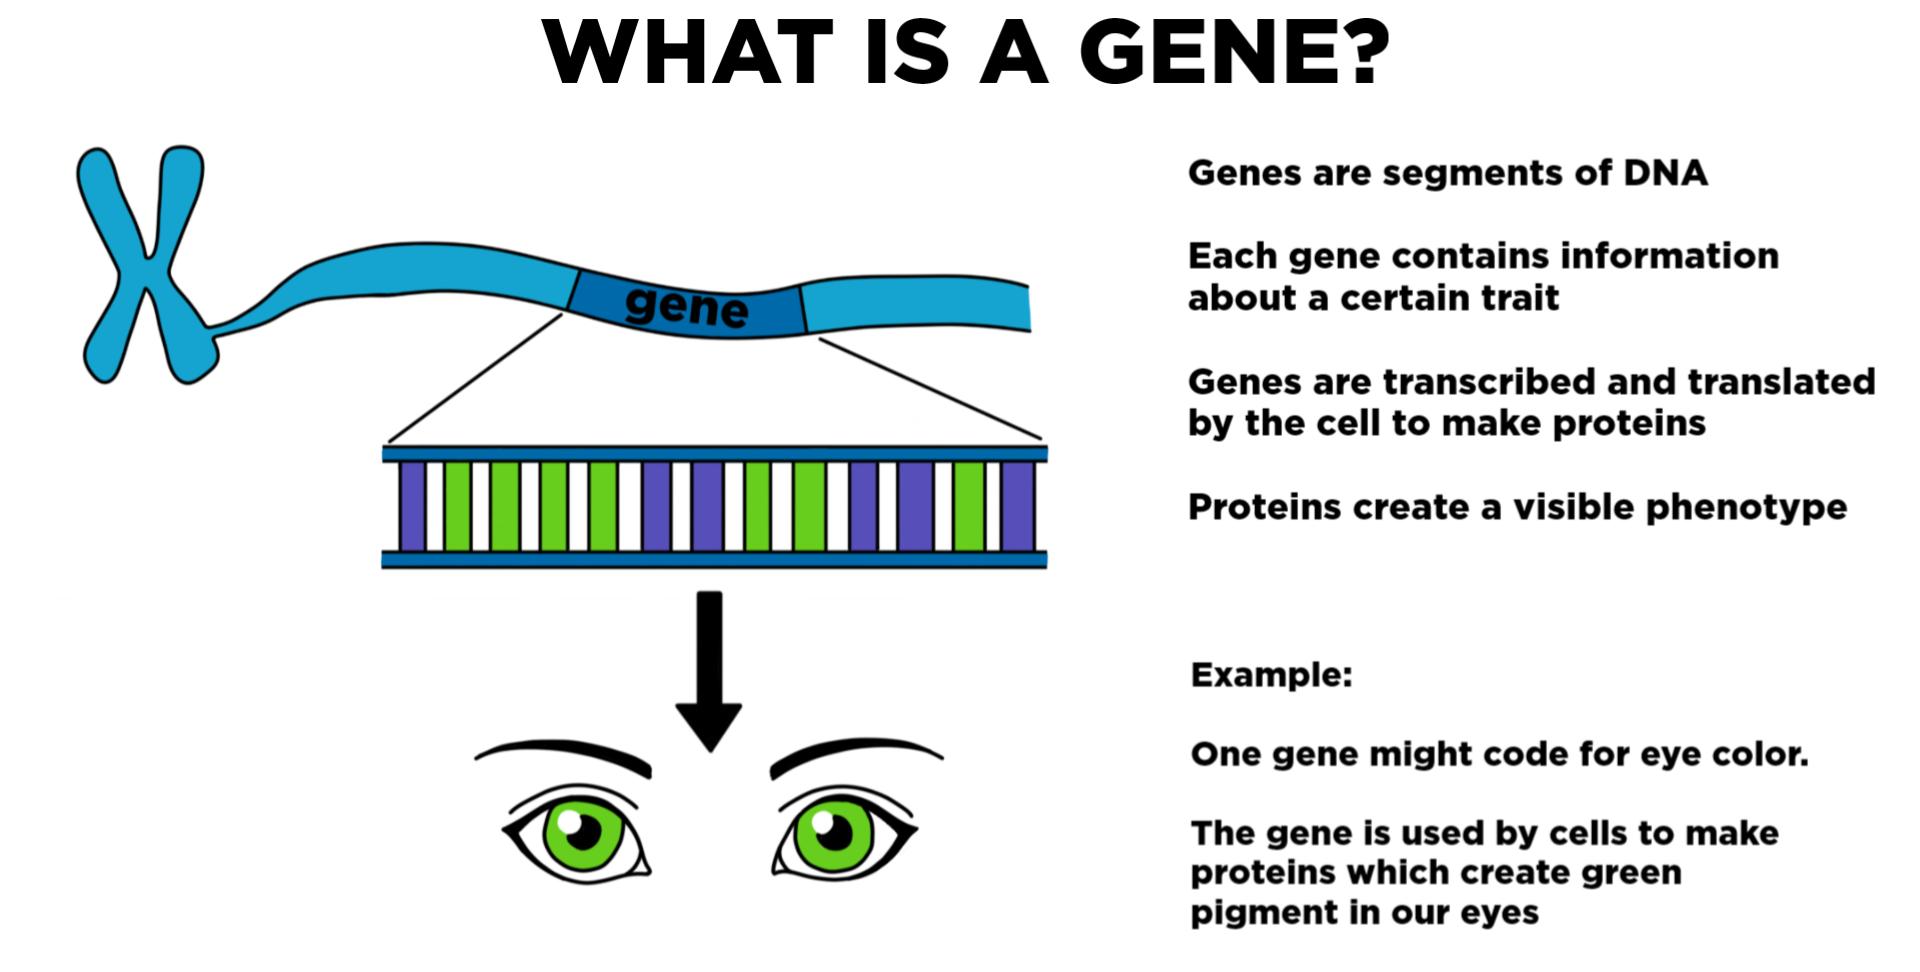
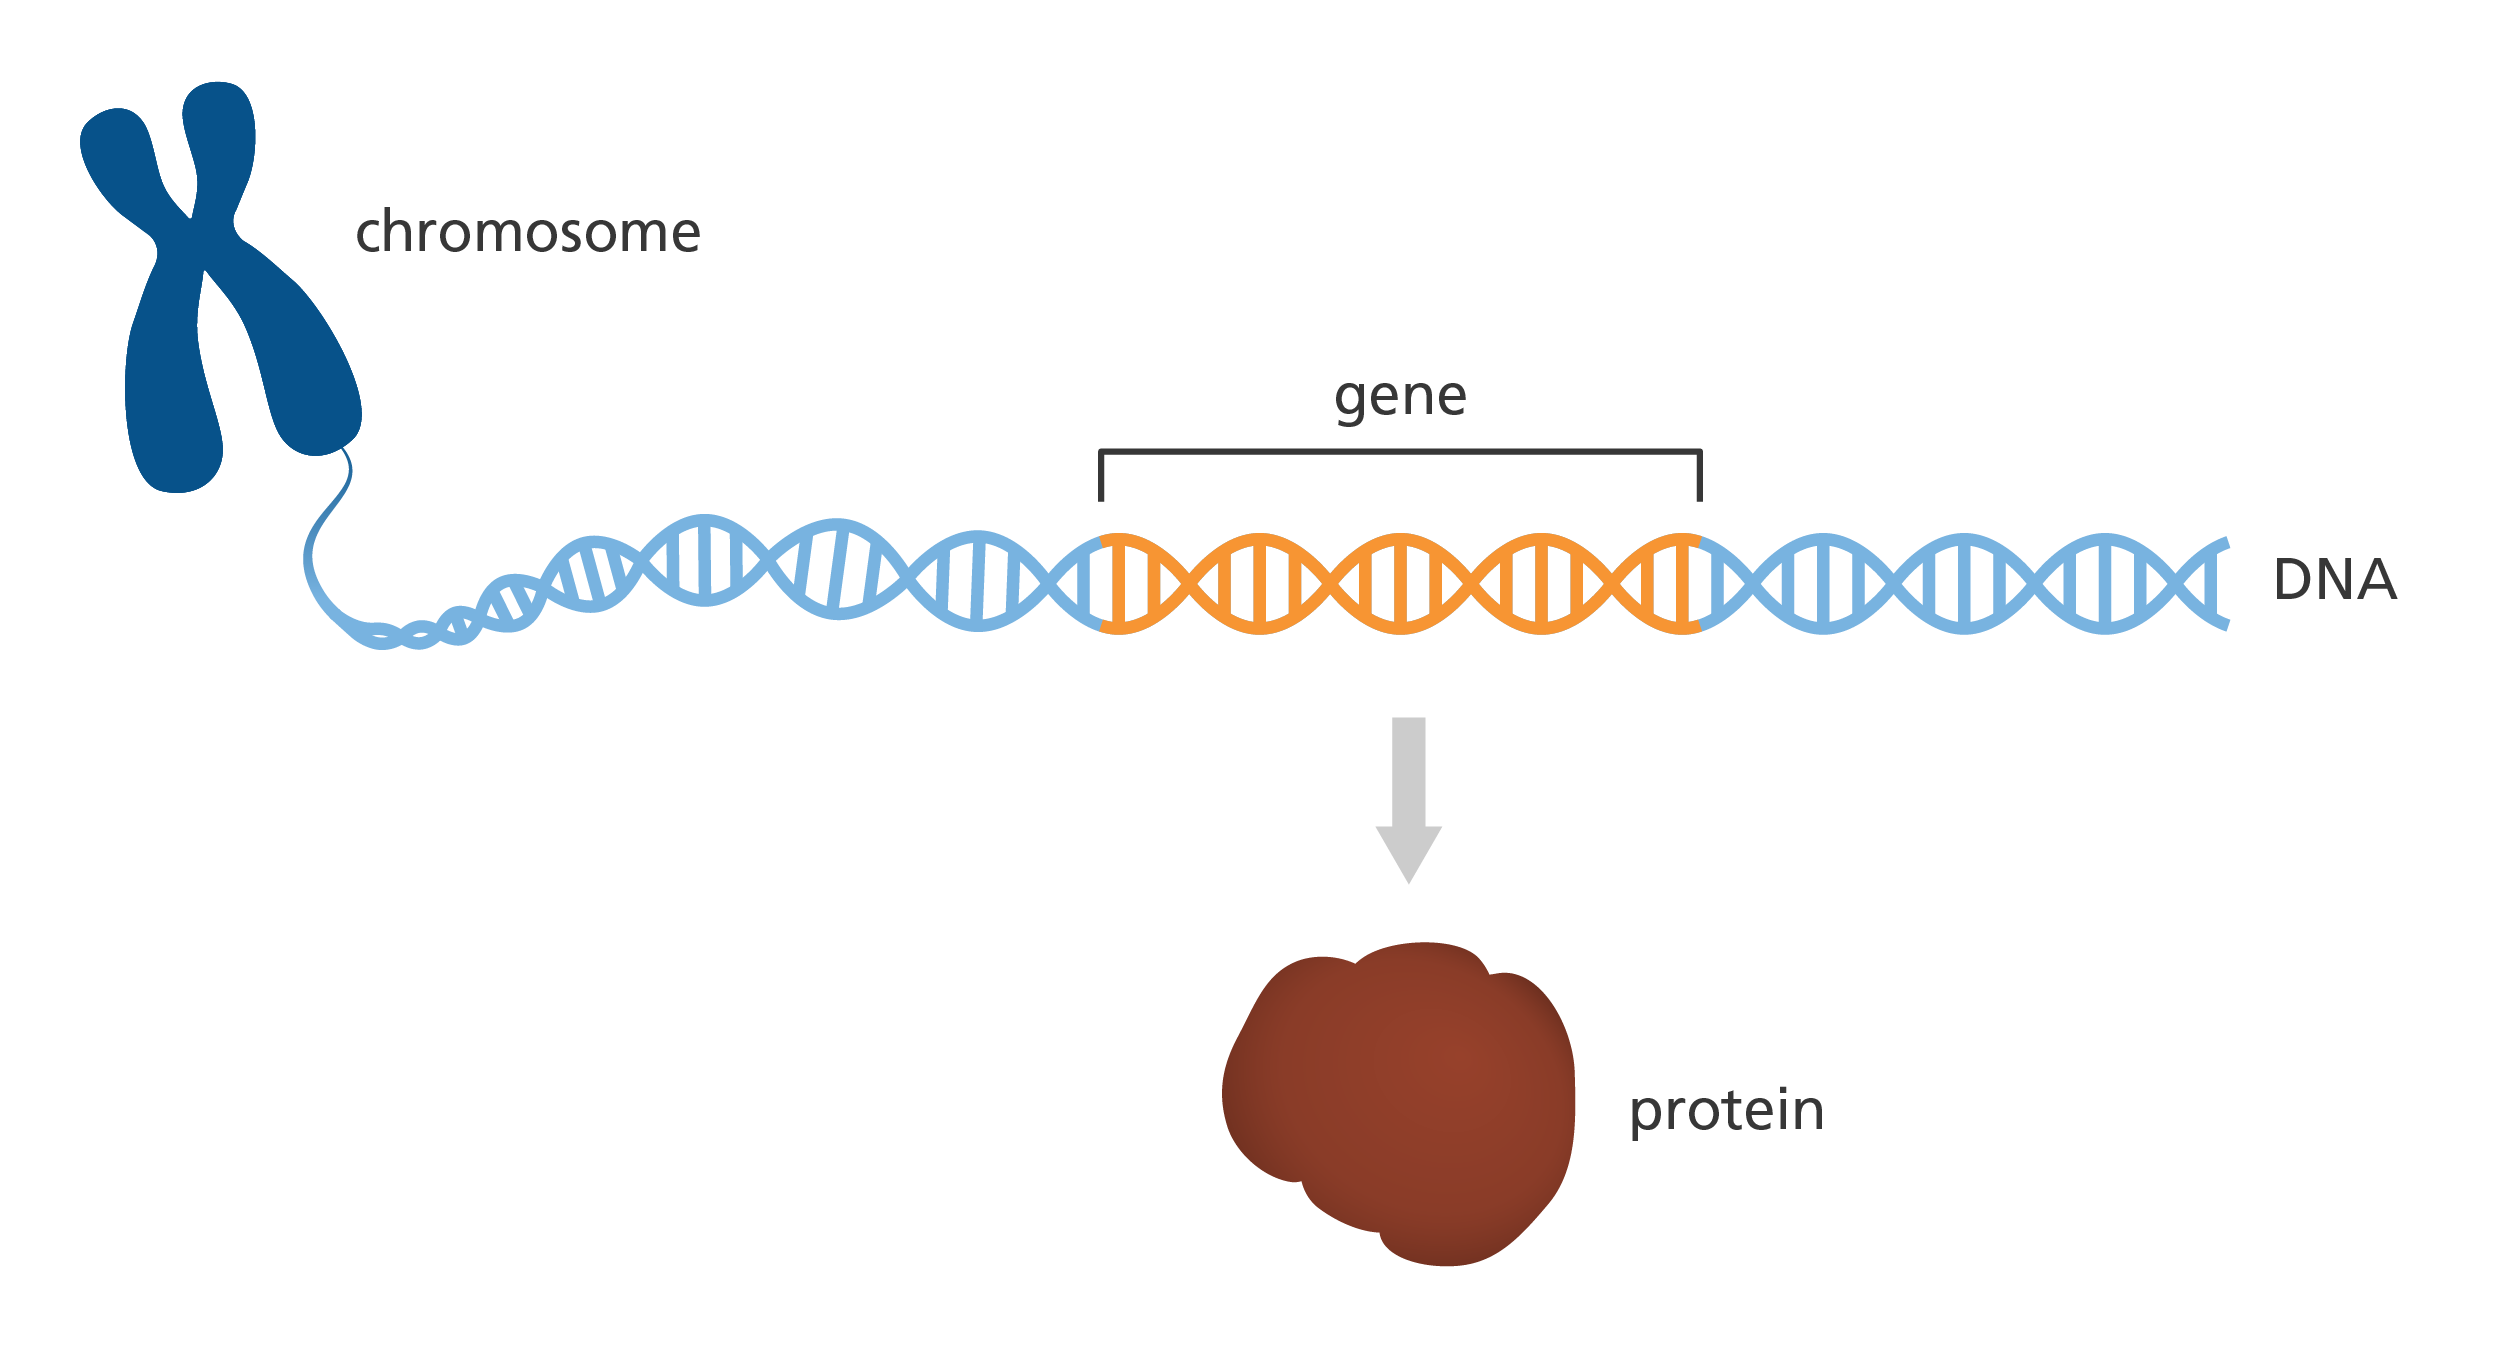
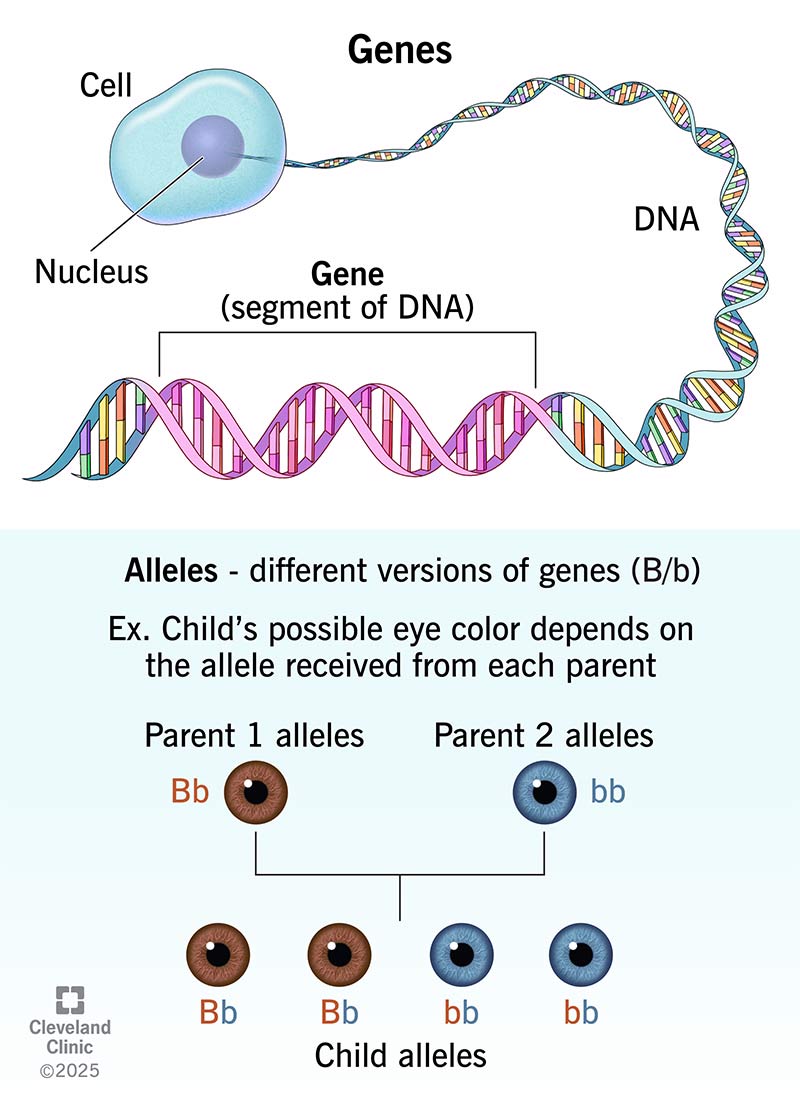
A gene is a functional unit of heredity made up of DNA. It contains the instructions for building one or more molecules—usually proteins, sometimes just RNA—that an organism needs to function. In humans, there are roughly 20,000 to 25,000 protein-coding genes, though the exact number shifts every time someone refines the annotation. Non-coding genes—like those producing transfer RNA, ribosomal RNA, and microRNA—are harder to pin down and account for another couple thousand at least. The structure is relatively straightforward in theory. You've got a promoter region that controls when and where the gene is expressed, then the coding sequence broken into exons and introns, followed by a polyadenylation signal at the tail end. Alternative splicing means a single gene can produce multiple protein variants by including or excluding different exons. This is where things get messy fast, especially if you're doing anything beyond basic documentation. In sequencing workflows, calling a gene isn't the same as defining one. Annotation databases like Ensembl, RefSeq, and GENCODE disagree with each other regularly on gene boundaries. I've seen the same locus called differently across three major references, and the discrepancies aren't minor—they affect which variants get classified as intronic versus exonic, which changes everything about how you interpret clinical significance. Always check which annotation build your pipeline is using and document it. It saves you from explaining to a clinician why your report says one thing and theirs says another.
One counter-intuitive thing about genes that trips people up: most of the human genome doesn't code for proteins. The commonly cited "junk DNA" figure has been revised significantly, but even so, the functional portion—regulatory elements, non-coding RNAs, structural regions—is scattered in ways that don't map neatly to the gene-centric view. You'll find enhancers hundreds of kilobases away from the genes they regulate, looping around chromatin to make contact. If you're analyzing variant data and only looking at the immediate vicinity of a gene boundary, you're missing a lot of what actually matters. Here's another nuance beginners miss. Genes aren't always on the same strand. Some overlap on opposite strands, some are nested inside introns of other genes, and in densely packed regions like the MHC locus, things get genuinely complicated. If you're designing primers or probes and don't account for strand orientation, your assay will fail or give you ambiguous results. I once spent a full day troubleshooting a qPCR assay that kept showing weird amplification curves before realizing the primer pair was picking up an antisense transcript from an overlapping gene. Redesigning with stranded specificity fixed it immediately. The practical side of working with genes involves understanding their limitations. Gene annotation is imperfect. Many genes, particularly in non-model organisms or in regions of the genome that are hard to sequence—repeats, pseudogenes, segmental duplications—still have uncertain boundaries. Calling variants in these regions is inherently noisy. Short-read sequencing struggles with long repetitive elements, and even long-read technologies have error rates that complicate gene-level interpretation. If you need high confidence in a specific gene region, targeted capture or PCR enrichment followed by deep sequencing is usually worth the extra cost compared to whole-exome or whole-genome approaches.
Get the Full Details
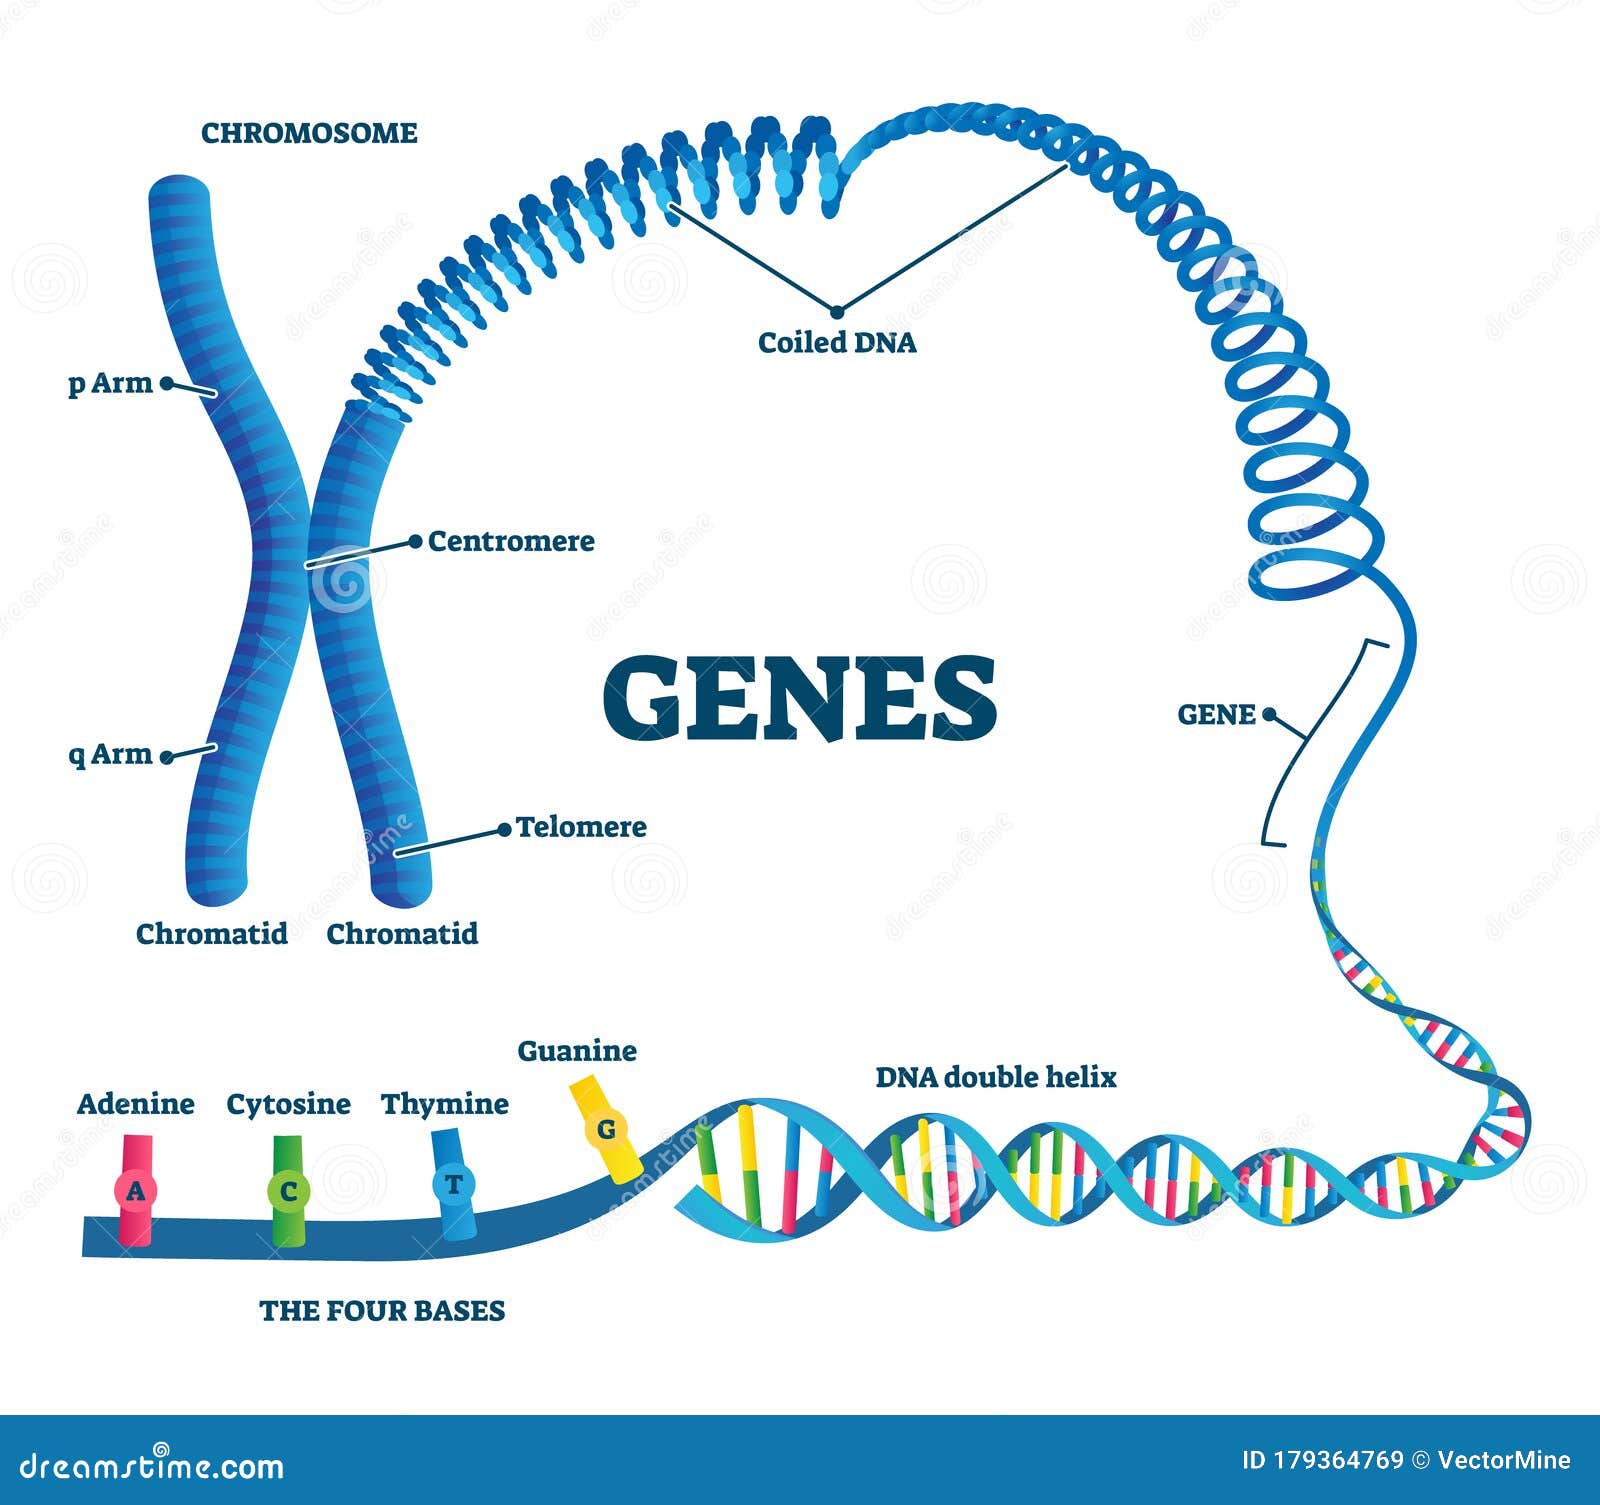
For someone just getting started, the best approach is to pick a well-annotated gene and follow it through a complete workflow. Pick something like CFTR or BRCA1—genes with extensive literature, clear clinical significance, and good reference data. Download a VCF from a public dataset, run it through an annotation tool like ANNOVAR or VEP, and trace each variant back to its gene features. You'll quickly learn more about what genes actually are in practice than you will from reading definitions. The field moves fast. New gene discoveries, revised annotations, and updated clinical guidelines come out constantly. What was considered a disease gene five years ago might have been reclassified, and new non-coding RNA genes are still being added to major databases. Staying current isn't optional if you're working with this material professionally.