Understanding Smooth Muscle: How It Actually Works
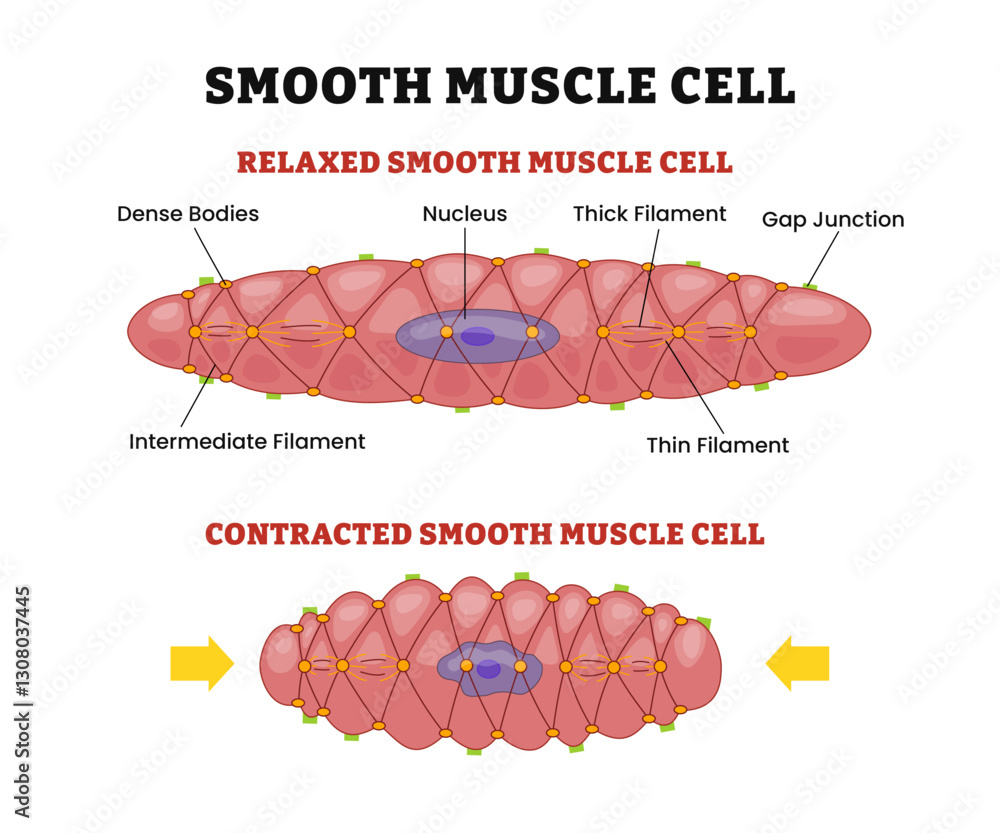
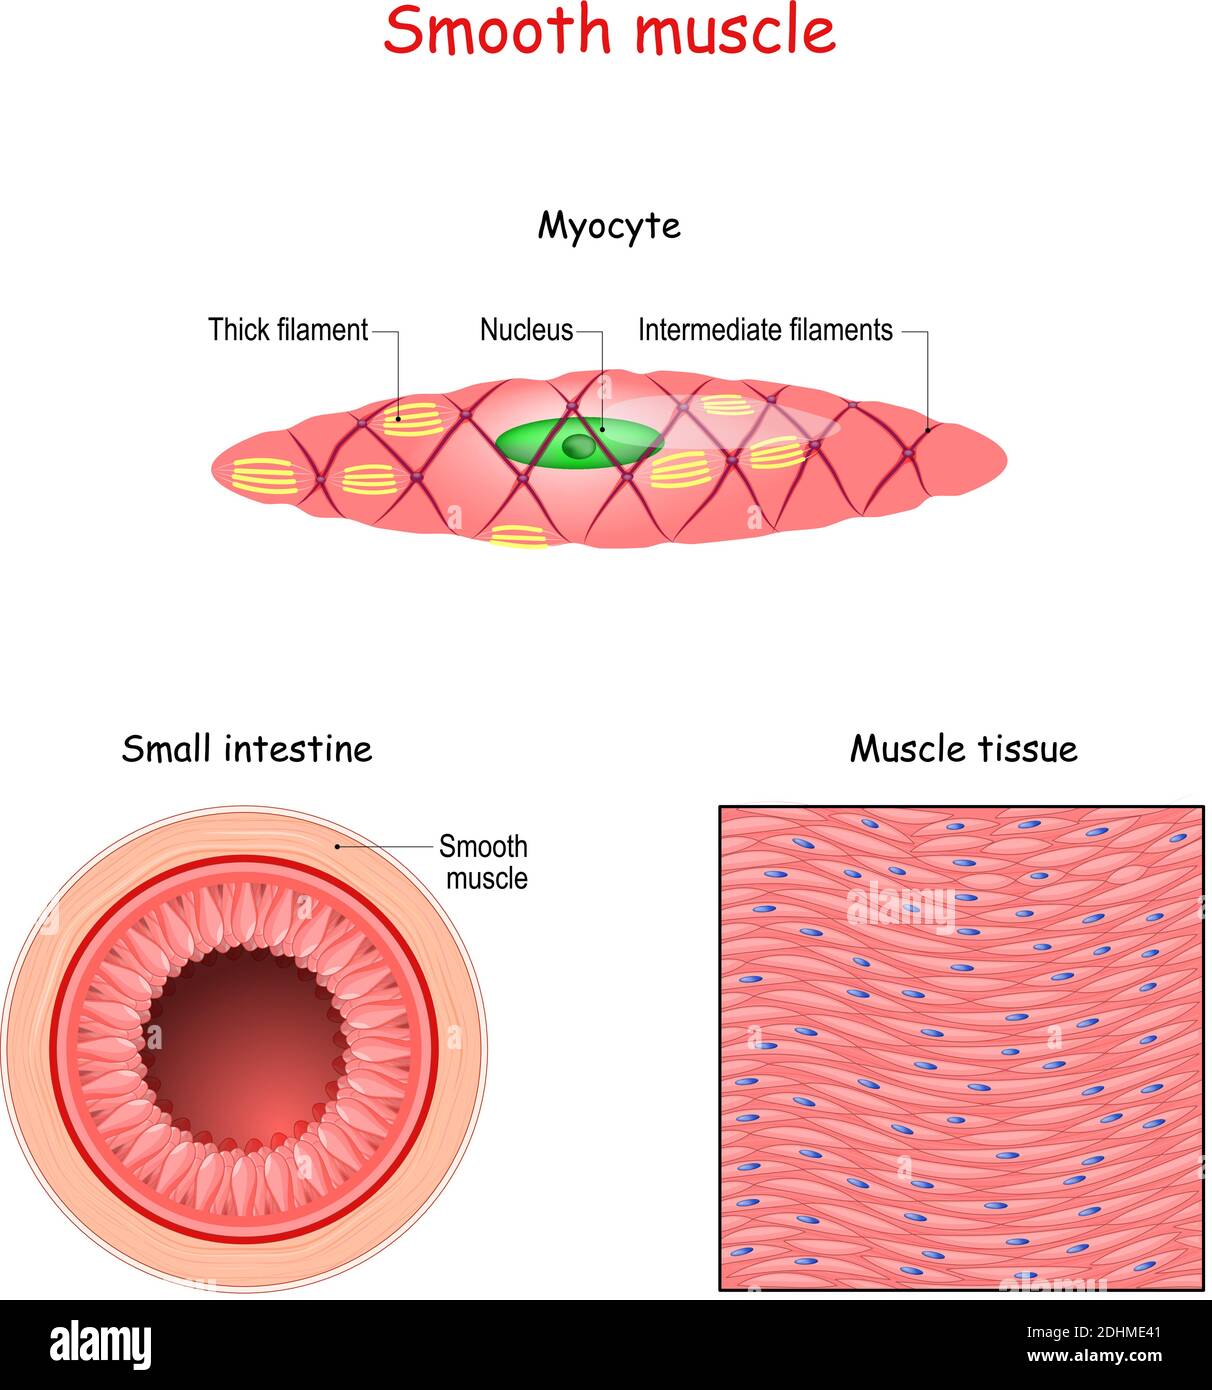
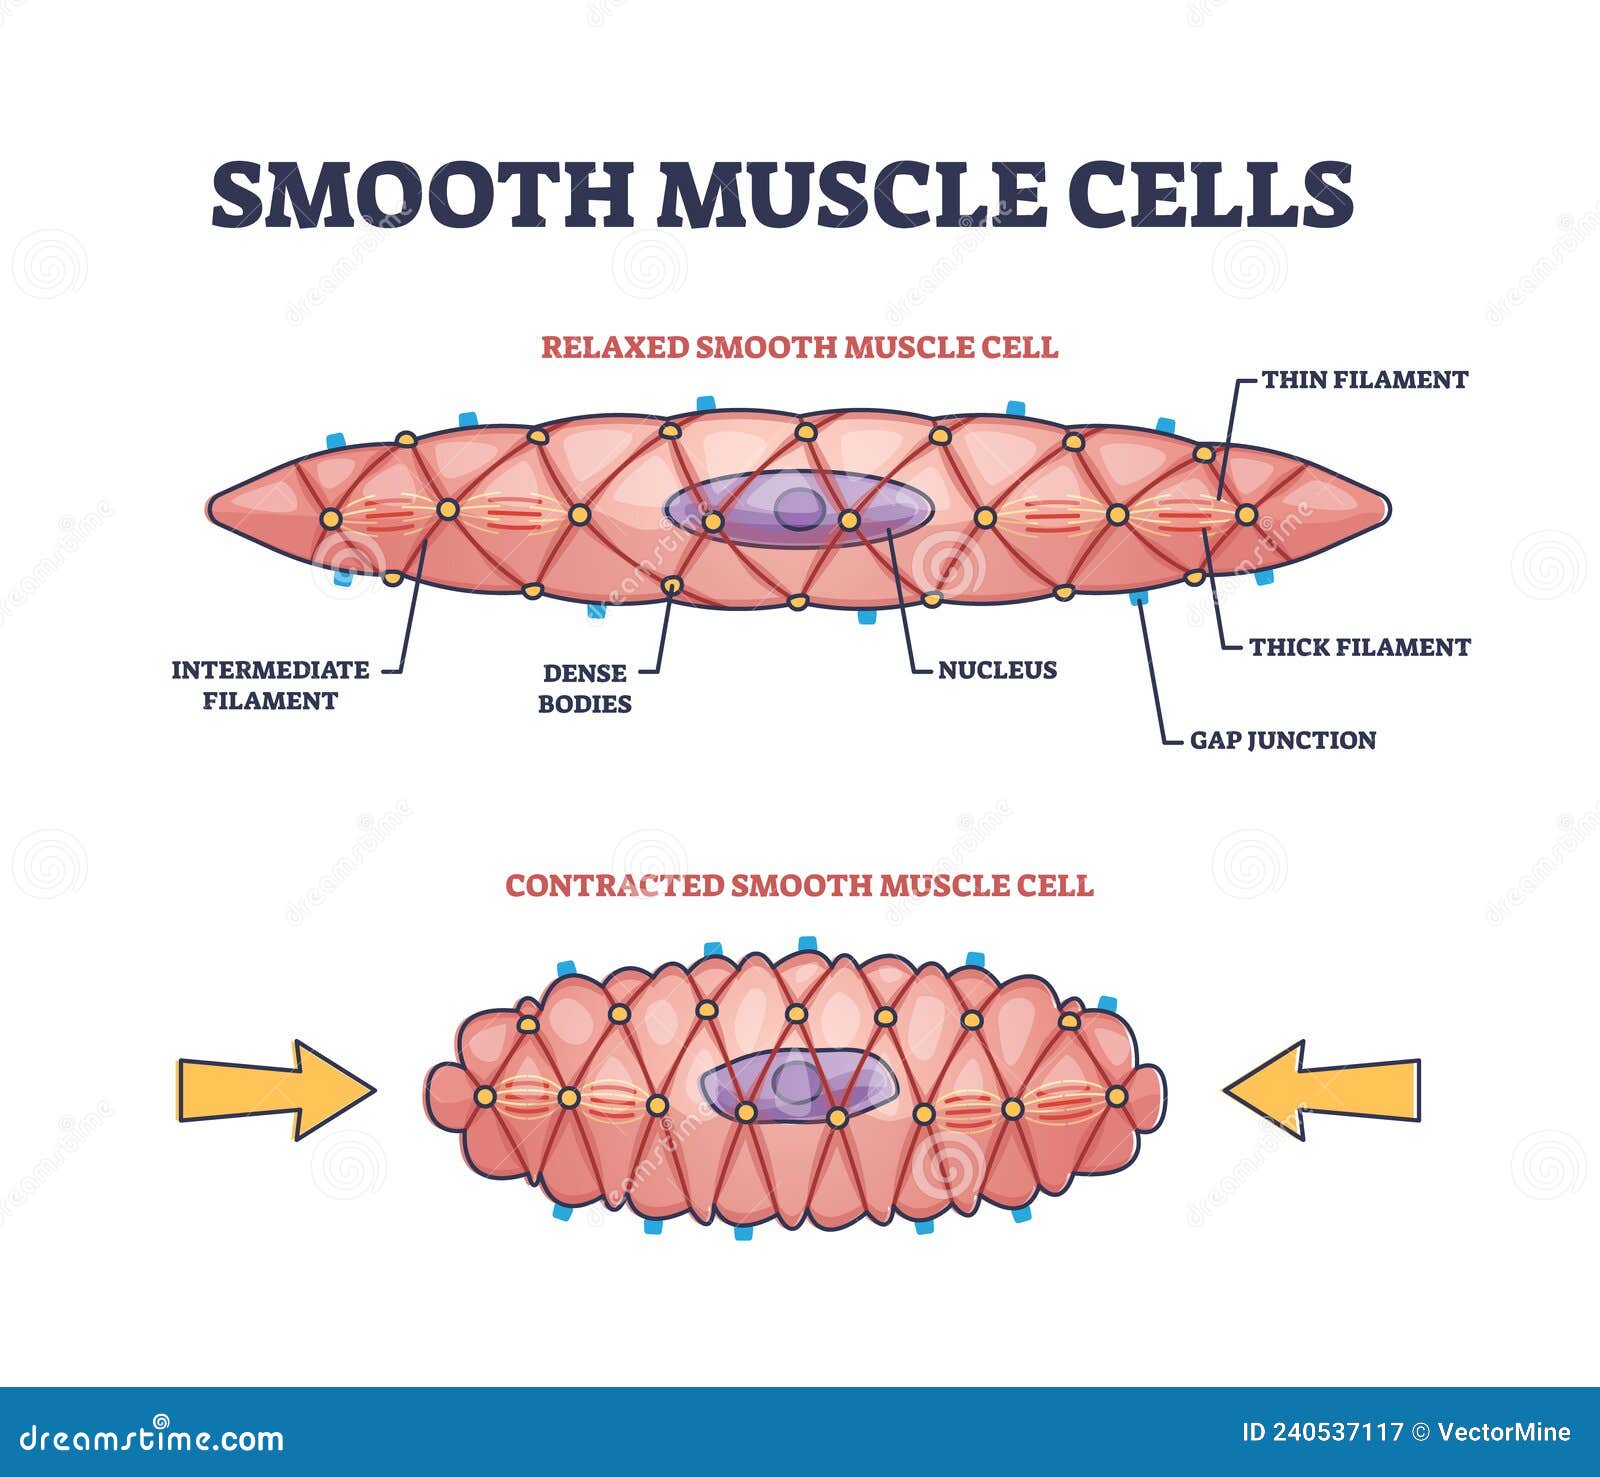
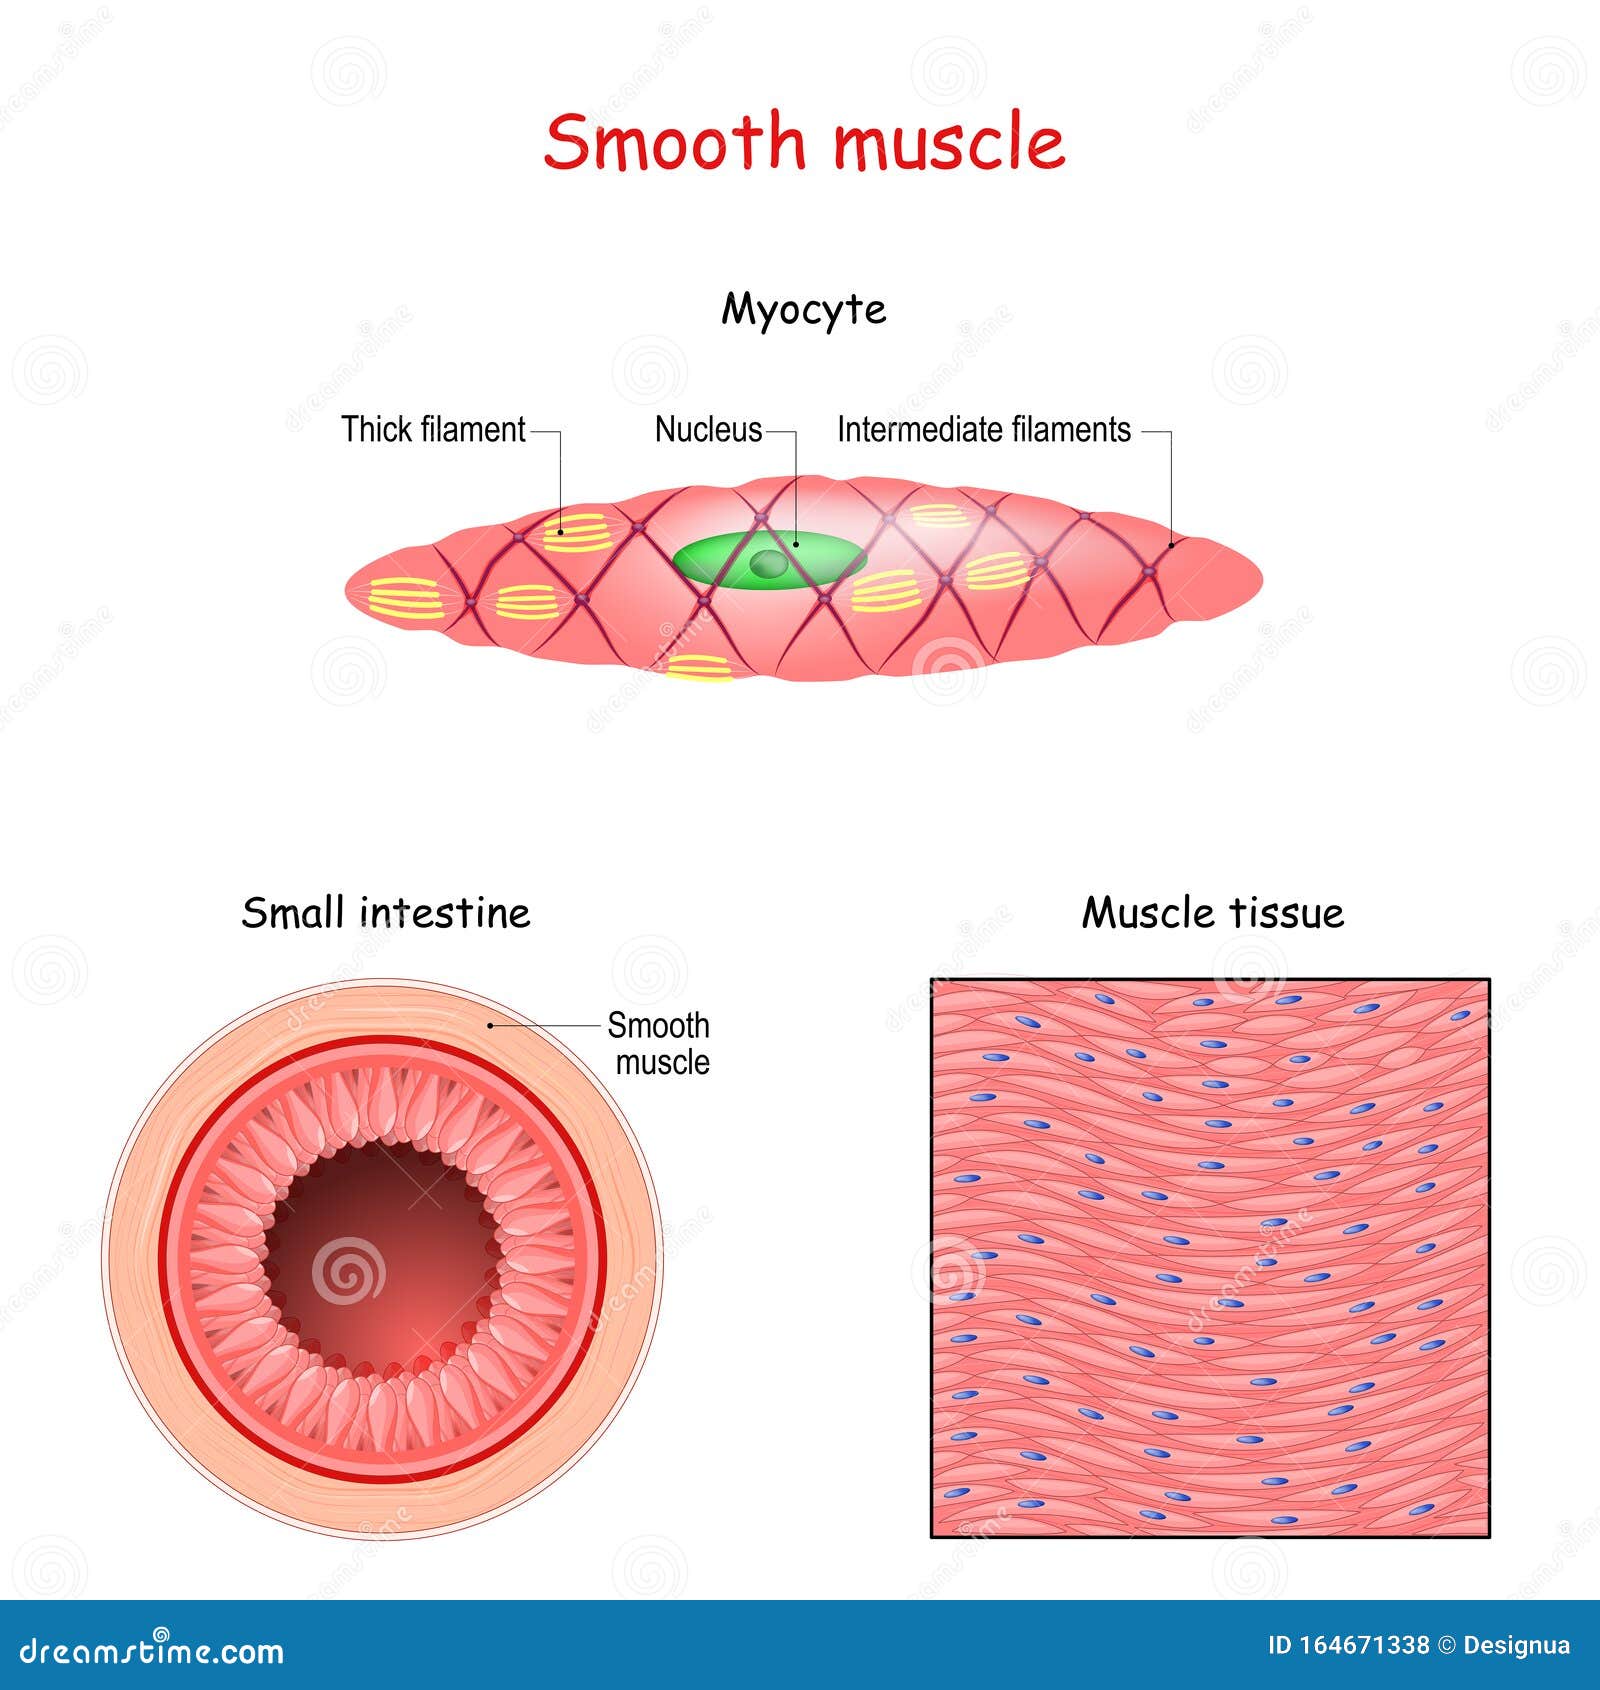
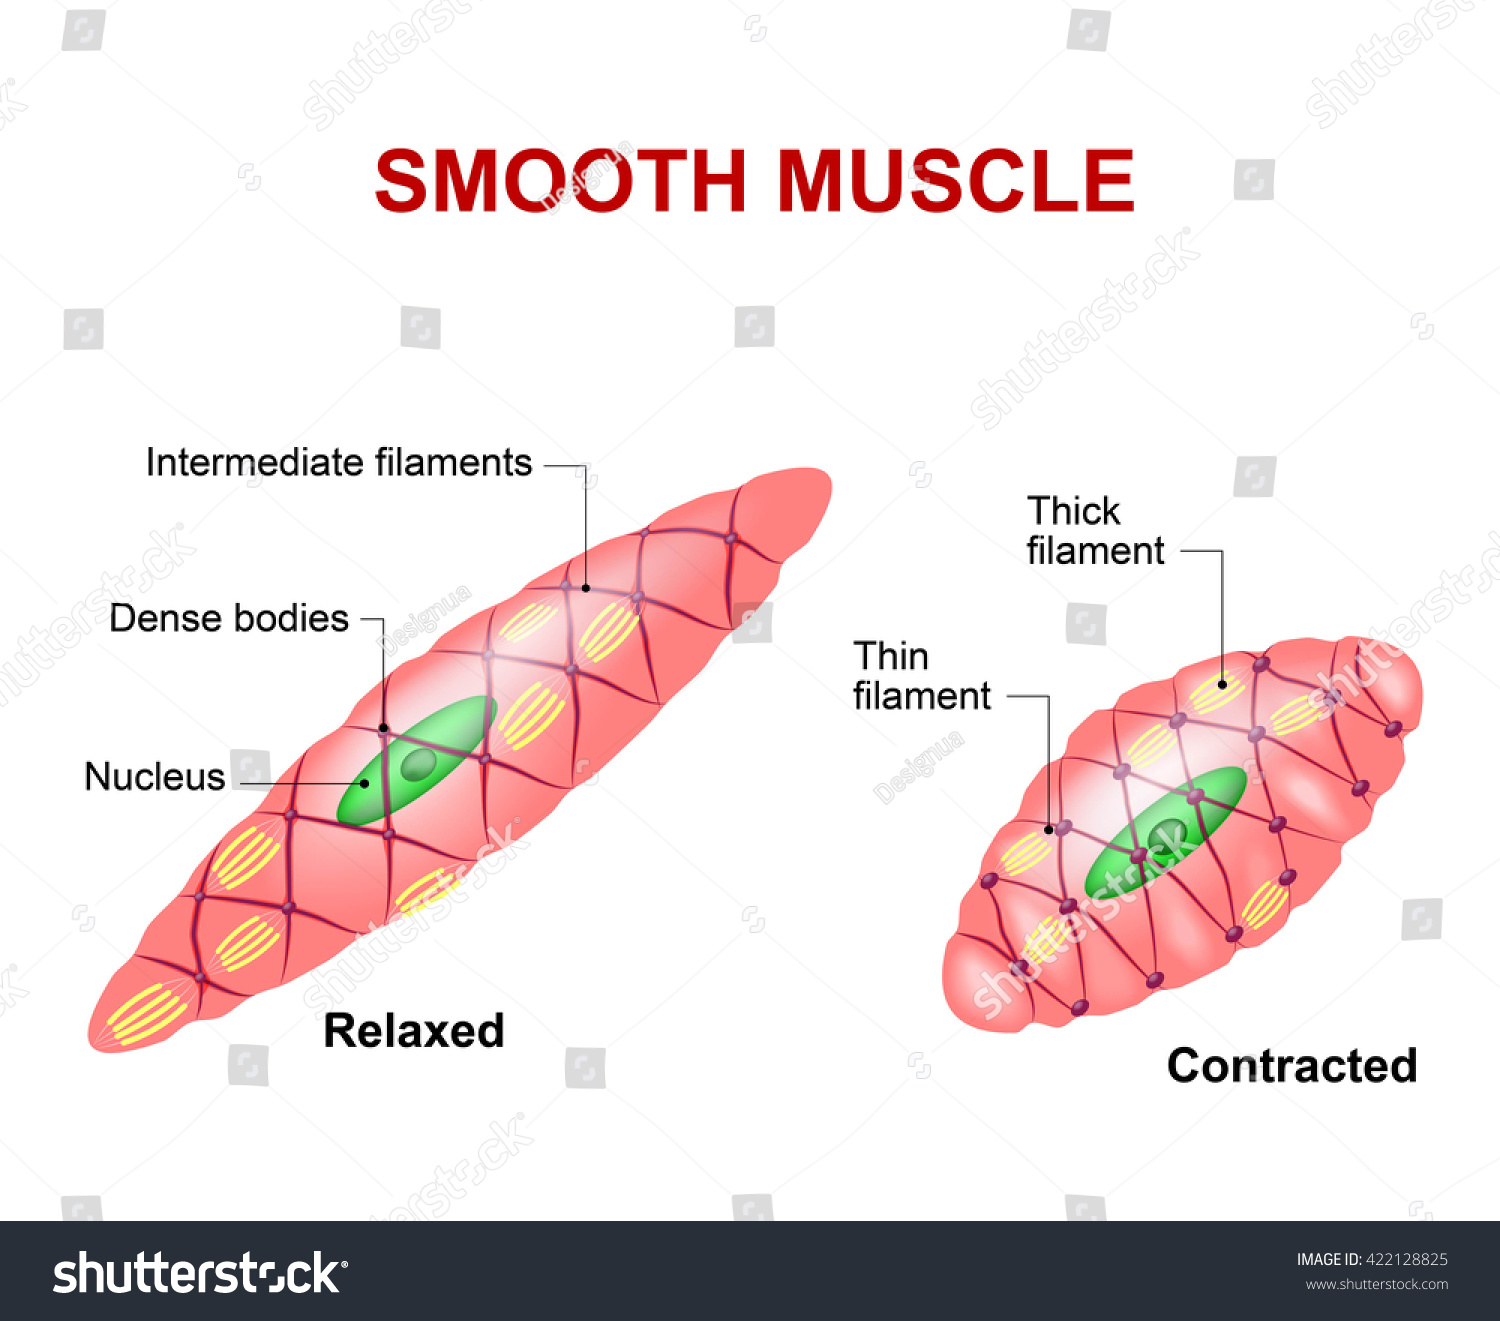
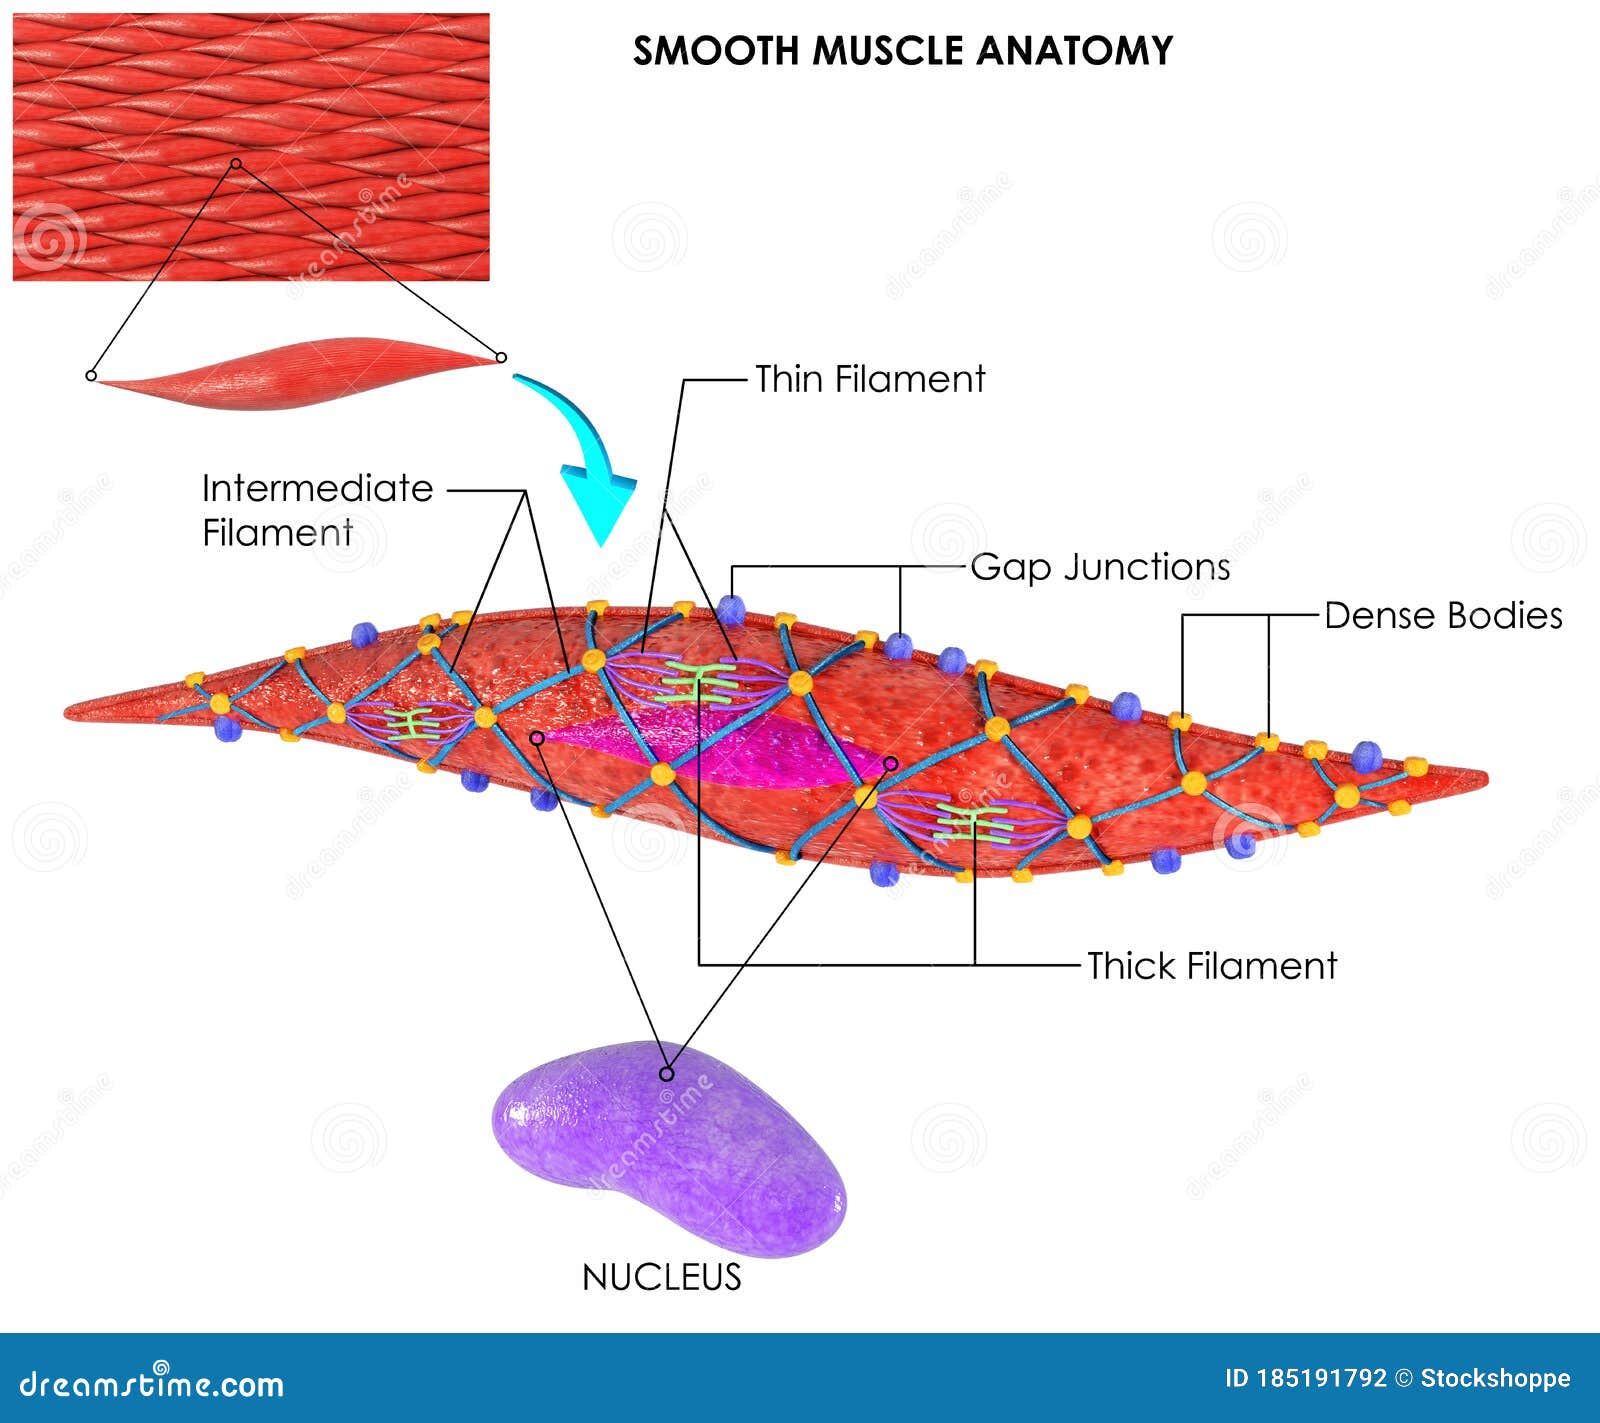
Smooth muscle is one of the three muscle tissue types in the human body, and it is the most misunderstood one. People hear "muscle" and immediately picture striated fibers attached to bone, contracting on command. That is not what smooth muscle does. It operates entirely outside voluntary control, and its behavior is significantly more complex than most introductory textbooks let on. Smooth muscle consists of spindle-shaped, non-striated cells found in the walls of hollow organs and structures. You will find it lining blood vessels, the gastrointestinal tract, the urinary bladder, the uterus, the bronchioles of the lungs, and the iris of the eye. Each cell contains a single central nucleus and lacks the organized sarcomere structure that gives skeletal and cardiac muscle their striped appearance under a microscope. The contraction machinery is still actin and myosin, but the arrangement is diffuse, anchored to dense bodies within the cell rather than aligned into repeating units. The mechanism of contraction in smooth muscle is fundamentally different from skeletal muscle. Instead of troponin regulating the interaction between actin and myosin, smooth muscle uses the calmodulin-myosin light chain kinase pathway. When intracellular calcium rises, it binds to calmodulin, and that complex activates myosin light chain kinase, which phosphorylates the myosin light chains to initiate cross-bridge cycling. This process is slower than skeletal muscle activation but can maintain tension for extended periods with far less ATP consumption. That is why vascular smooth muscle can sustain vasoconstriction for hours without tiring the way a bicep would if held flexed continuously.
One thing most people miss is that smooth muscle has multiple activation pathways. Neural input through the autonomic nervous system is only one of them. Hormones circulating in the blood can trigger contraction directly. Local chemical conditions like pH shifts, oxygen levels, and metabolite concentrations affect it. Mechanical stretch itself can initiate contraction through the myogenic response, which is especially important in blood vessels that regulate their own tone independently of nervous input. This multi-modal activation is why smooth muscle disorders are so difficult to treat with a single pharmacological approach. I spent considerable time dealing with smooth muscle pharmacology during a project involving drug delivery across the blood-brain barrier, and the sheer variability between different smooth muscle populations caught me off guard. Vascular smooth muscle in cerebral arterioles responded very differently to the same agonists compared to gastrointestinal smooth muscle, even when the receptor subtypes appeared similar on paper. The downstream signaling cascades diverged enough that dosing strategies valid for one tissue caused unexpected contractions in another. The workaround was mapping the actual functional response curves for each tissue type rather than relying on receptor binding affinities alone. Binding affinity does not reliably predict functional outcome in smooth muscle. Another critical detail that is often glossed over is the role of gap junctions. In single-unit smooth muscle, also called visceral smooth muscle, cells are electrically coupled through gap junctions, meaning a depolarization in one cell spreads to neighbors and produces coordinated contraction. This is typical in the gastrointestinal tract and the uterus. Multi-unit smooth muscle, found in the iris and the larger airways, lacks extensive gap junctions and each cell operates more independently, allowing fine graded control. Confusing these two types leads to incorrect predictions about how a given stimulus will affect the tissue.
The energy efficiency of smooth muscle is worth noting because it has practical implications. Smooth muscle can maintain a contracted state, known as latch state, with very low ATP usage. Once cross-bridges form, the myosin light chains can dephosphorylate while the bridges remain attached, allowing sustained tension without continuous cycling. This is why you do not get fatigue from your blood vessels constricting or your gut maintaining basal tone. But this same property becomes a liability in certain pathological conditions. Latch state can make pathological vasoconstriction extremely resistant to treatment because the tissue is holding tension metabolically cheaply. Calcium handling in smooth muscle also differs from what you might assume. Not all calcium triggering contraction comes from extracellular influx through voltage-gated or ligand-gated channels. Sarcoplasmic reticulum release plays a major role, and in some smooth muscle types, store-operated calcium entry becomes the dominant source during sustained stimulation. This is why blocking L-type calcium channels with drugs like nifedipine does not completely abolish smooth muscle contraction. The remaining calcium release pathways and sensitization mechanisms keep the tissue responsive, which explains why calcium channel blockers alone are sometimes insufficient for severe vasospasm. There are also sensitivity modulation mechanisms that do not exist in skeletal muscle. Rho-kinase signaling can increase the sensitivity of the contractile apparatus to calcium without raising intracellular calcium levels at all. This phenomenon, called calcium sensitization, is clinically significant because it means that increasing calcium entry is not the only way to produce contraction, and blocking calcium channels is not the only way to cause relaxation. Some vasoconstrictive states are driven primarily by Rho-kinase activation rather than changes in calcium concentration, which is why certain resistant hypertension cases do not respond well to standard calcium channel blocker therapy.
Get the Full Details
If you are studying this for practical purposes, whether clinical or research-oriented, the most useful framework is to think about smooth muscle along three axes: the type of tissue it is in, the dominant activation pathway in that context, and whether sensitization mechanisms are likely contributing to the observed behavior. A single blanket statement about how smooth muscle contracts will be wrong for at least one of those axes in most real situations. The structural differences between single-unit and multi-unit smooth muscle matter when interpreting experimental results or clinical responses. Electroneutral sodium-calcium exchangers, plasma membrane calcium ATPases, and the varying densities of different receptor subtypes all create tissue-specific behaviors that are impossible to predict from first principles alone. Empirical characterization remains necessary even when the molecular components appear to be the same on paper.