What Spermatogenesis Actually Looks Like From the Lab Bench
It sounds like a mouthful, but what is a spermatogenesis process really? At its core, it is the creation of sperm from germ cells inside the testes. The raw materials start as spermatogonia, stem cells that sit along the basement membrane of the seminiferous tubules. They divide, differentiate, and over roughly 64 to 74 days in humans, they become mature spermatozoa. That is the textbook answer. The reality is messier. I spent years working in a reproductive endocrinology lab running semen analysis protocols and helping clinics troubleshoot male infertility cases. The first thing you learn is that the textbook timeline assumes a perfect system. Real systems rarely cooperate. One of my early mistakes was assuming a single semen sample could give a reliable picture. It cannot. Sperm production is batch-manufactured, not continuous in a way that every batch comes out identical. A man might show low count in one sample, normal in the next, and everything in between again after. Guidelines say you need at least two samples, separated by two to three weeks, before drawing any conclusions. Skipping that step wastes everyone's time and leads to bad clinical recommendations.
What Is A Spermatogenesis Process and Why Does It Matter Clinically
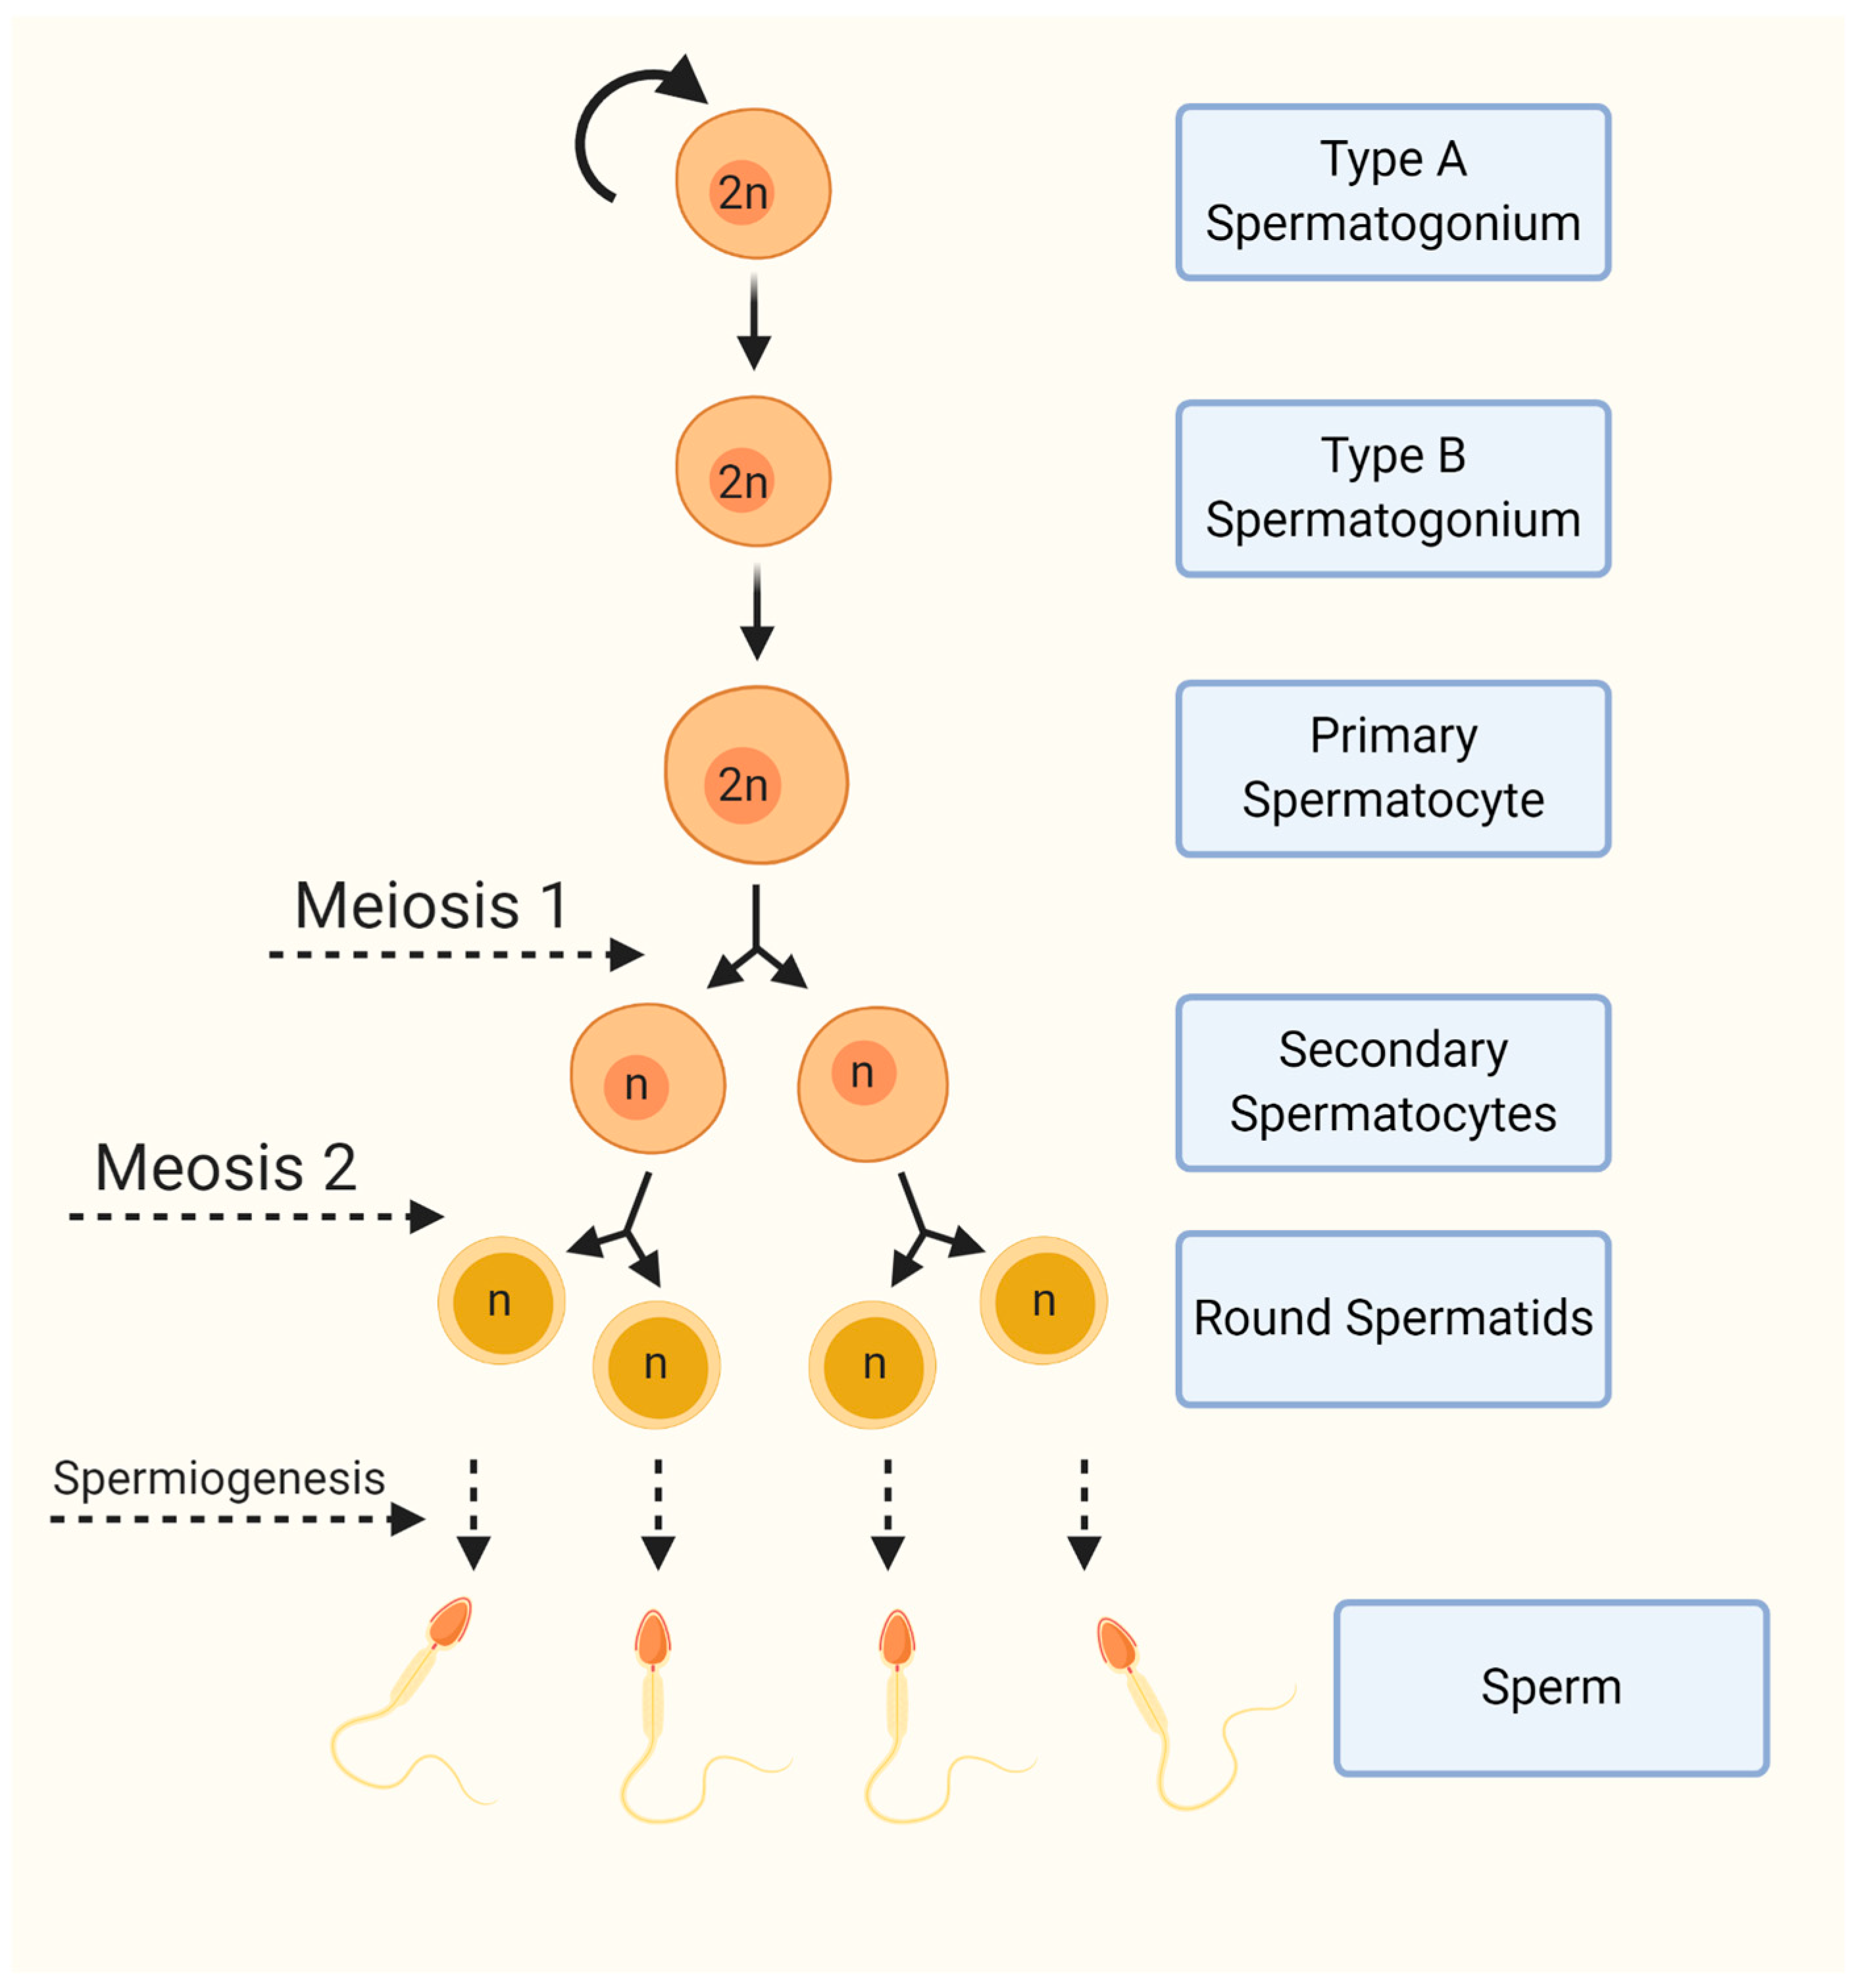
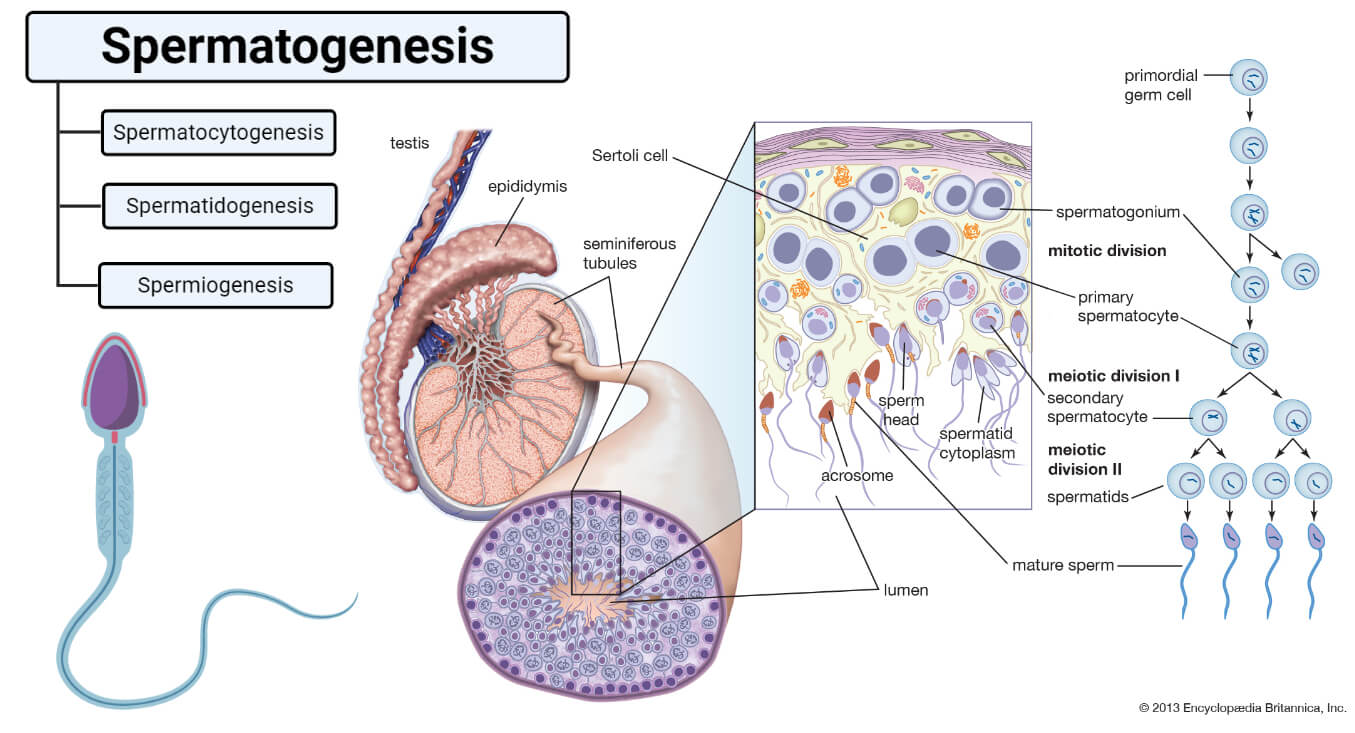
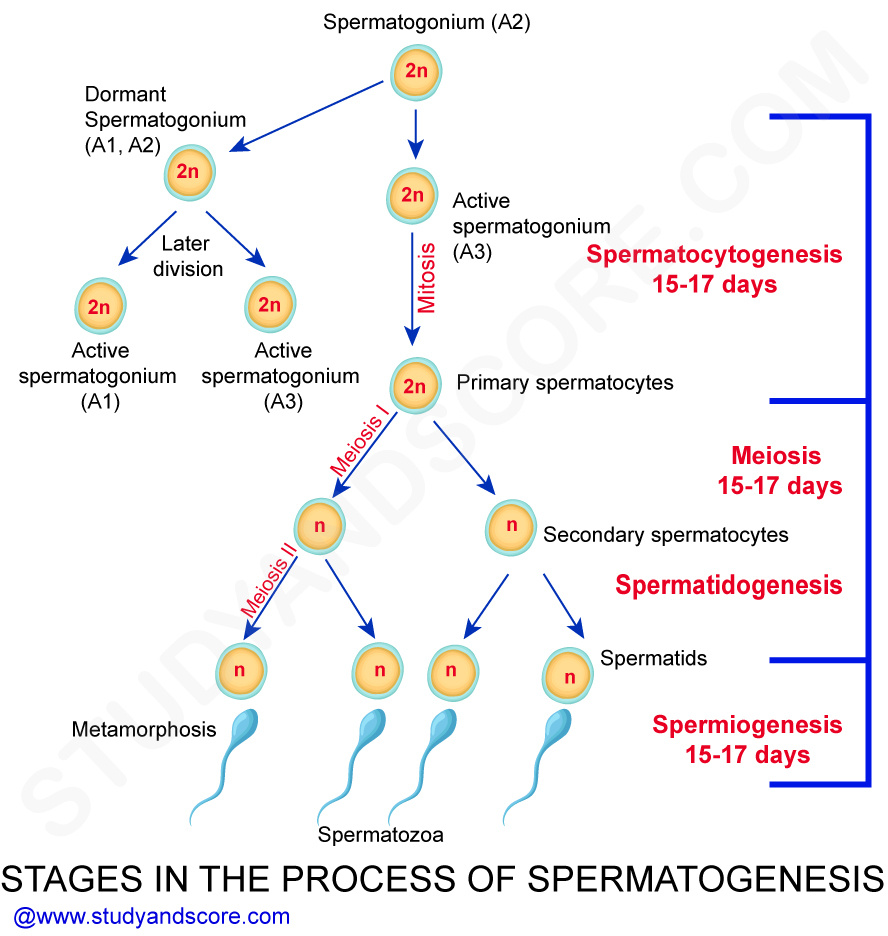
The process breaks down into three main phases. First is spermatocytogenesis, where spermatogonia undergo mitotic divisions to amplify their numbers. Some stay as stem cells. Others commit to becoming primary spermatocytes. Then meiosis kicks in. Primary spermatocytes divide into secondary spermatocytes, which quickly divide again into spermatids. This is the reduction division that cuts the chromosome count in half. Finally, spermiogenesis reshapes those round spermatids into streamlined sperm with tails, condensed nuclei, and acrosomes. No cell division happens during this last phase. It is all remodeling. Here is something people miss. The Sertoli cells are doing just as much heavy lifting as the germ cells themselves. Each Sertoli cell supports roughly a dozen developing germ cells at any given stage, and they provide structural scaffolding, nutrients, and the blood-testis barrier. If you compromise Sertoli cell function, the entire production line stalls, regardless of how healthy the germ cells are. Leydig cells sit nearby producing testosterone, and intratesticular testosterone needs to stay about 50 to 100 times higher than blood levels for normal spermatogenesis to proceed. That concentration gradient is maintained by specific transport proteins and enzymes, and it is fragile. I once had a case where a man's sperm parameters looked completely normal on paper, but his motility was non-existent under certain temperature conditions. We traced it back to a subtle environmental factor in his home lab during sample collection. He was bringing the sample in a coat pocket during a cold winter, and the temperature dropped well below the recommended 35 to 37 degrees Celsius range. Cold shock reduces motility dramatically and can permanently damage sperm if the exposure is prolonged. The fix was straightforward, but it took us three visits to catch it. Most clinics would have accepted that first sample and moved on.
Another counter-intuitive point that beginners consistently overlook is the relationship between abstinence period and sample quality. Longer abstinence does not equal better samples. Extended abstinence beyond seven days actually increases DNA fragmentation and oxidative damage in sperm. The recommendation sits between two and five days for most fertility assessments. Anything longer introduces artifacts that look like infertility but are really just collection protocol errors. Spermatogenesis takes a long time because it has to be precise. Errors in meiosis result in aneuploid gametes, and the body has quality control mechanisms that trigger apoptosis in defective germ cells. This is why conditions like varicoceles matter so much. Elevated scrotal temperature and oxidative stress from venous pooling damage developing sperm at multiple stages. The affected sperm often have fragmented DNA that standard semen analysis will not detect. You need specialized testing like the TUNEL assay or SCSA to catch it. There are limitations to what we can determine from standard protocols. Semen analysis gives us count, motility, and morphology, but it does not tell us about sperm function, DNA integrity, or epigenetic health. A man can pass a normal semen analysis and still have underlying issues that affect fertility or offspring health. This is a known gap in the field, and research into advanced sperm assessment is moving slowly because the technology is expensive and not yet standardized across labs.
Get the Full Details
If you are looking for a practical entry point into understanding this topic, the World Health Organization laboratory manual for semen examination remains the standard reference. The fifth edition came out in 2010, and the sixth edition updated many thresholds. The full document is available through the WHO website, and it is the closest thing we have to an authoritative how-to guide for anyone working in this space. No shortcuts around it if you want accurate results.