AAV Vectors in Practice
What Is Aav Gene Therapy
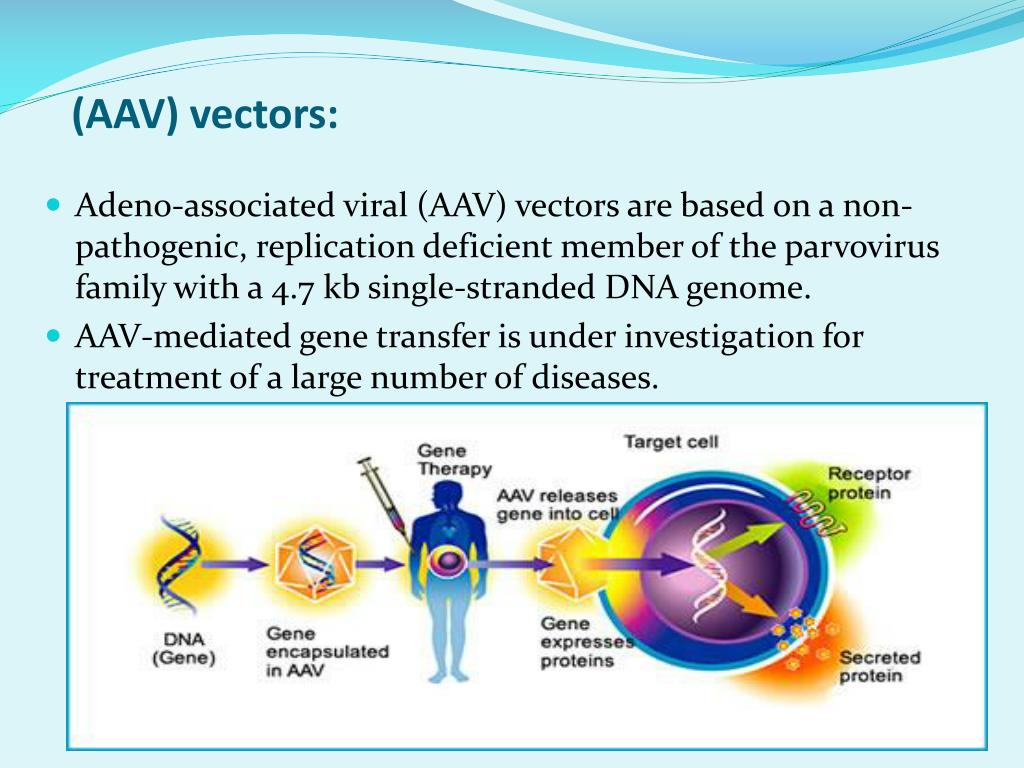
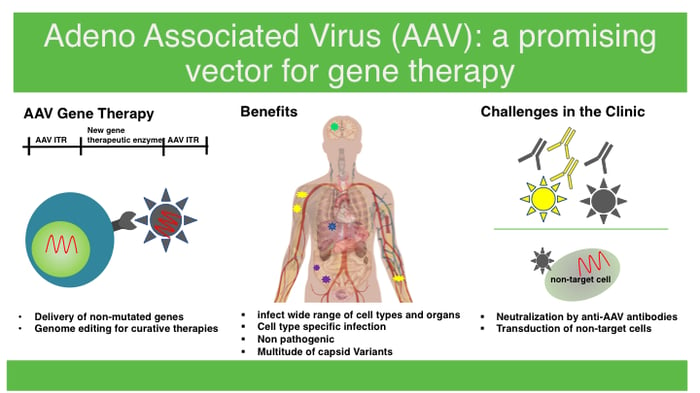
Adeno-associated virus gene therapy uses a modified AAV vector to deliver functional genetic material into target cells. The virus is stripped of its ability to replicate and instead carries a therapeutic transgene under control of a promoter. Once inside the cell, the DNA can integrate into the genome at a low frequency or persist as an episome, depending on the serotype and payload design. This approach has enabled approved treatments for conditions like spinal muscular atrophy and inherited retinal disease. The most commonly used serotypes are AAV2, AAV5, AAV8, and AAV9. Each has distinct tropisms that determine which tissues they preferentially transduce. AAV8 and AAV9 show broad systemic distribution after intravenous delivery, while AAV2 and AAV5 are more restricted. Selecting the right serotype matters more than most people initially realize. I spent months optimizing a liver-directed AAV8 construct for a study and kept hitting a wall with transgene silencing. The vector titer looked fine on qPCR, but protein expression dropped off after six weeks in primates. The issue turned out to be CpG density in the transgene cassette triggering innate immune recognition. We swapped to a synthetic codon-optimized promoter and replaced the CMV enhancer with a liver-specific one, which stabilized expression for over a year. That was a costly lesson in not trusting the sequencing to tell the whole story.
How the Delivery Actually Works
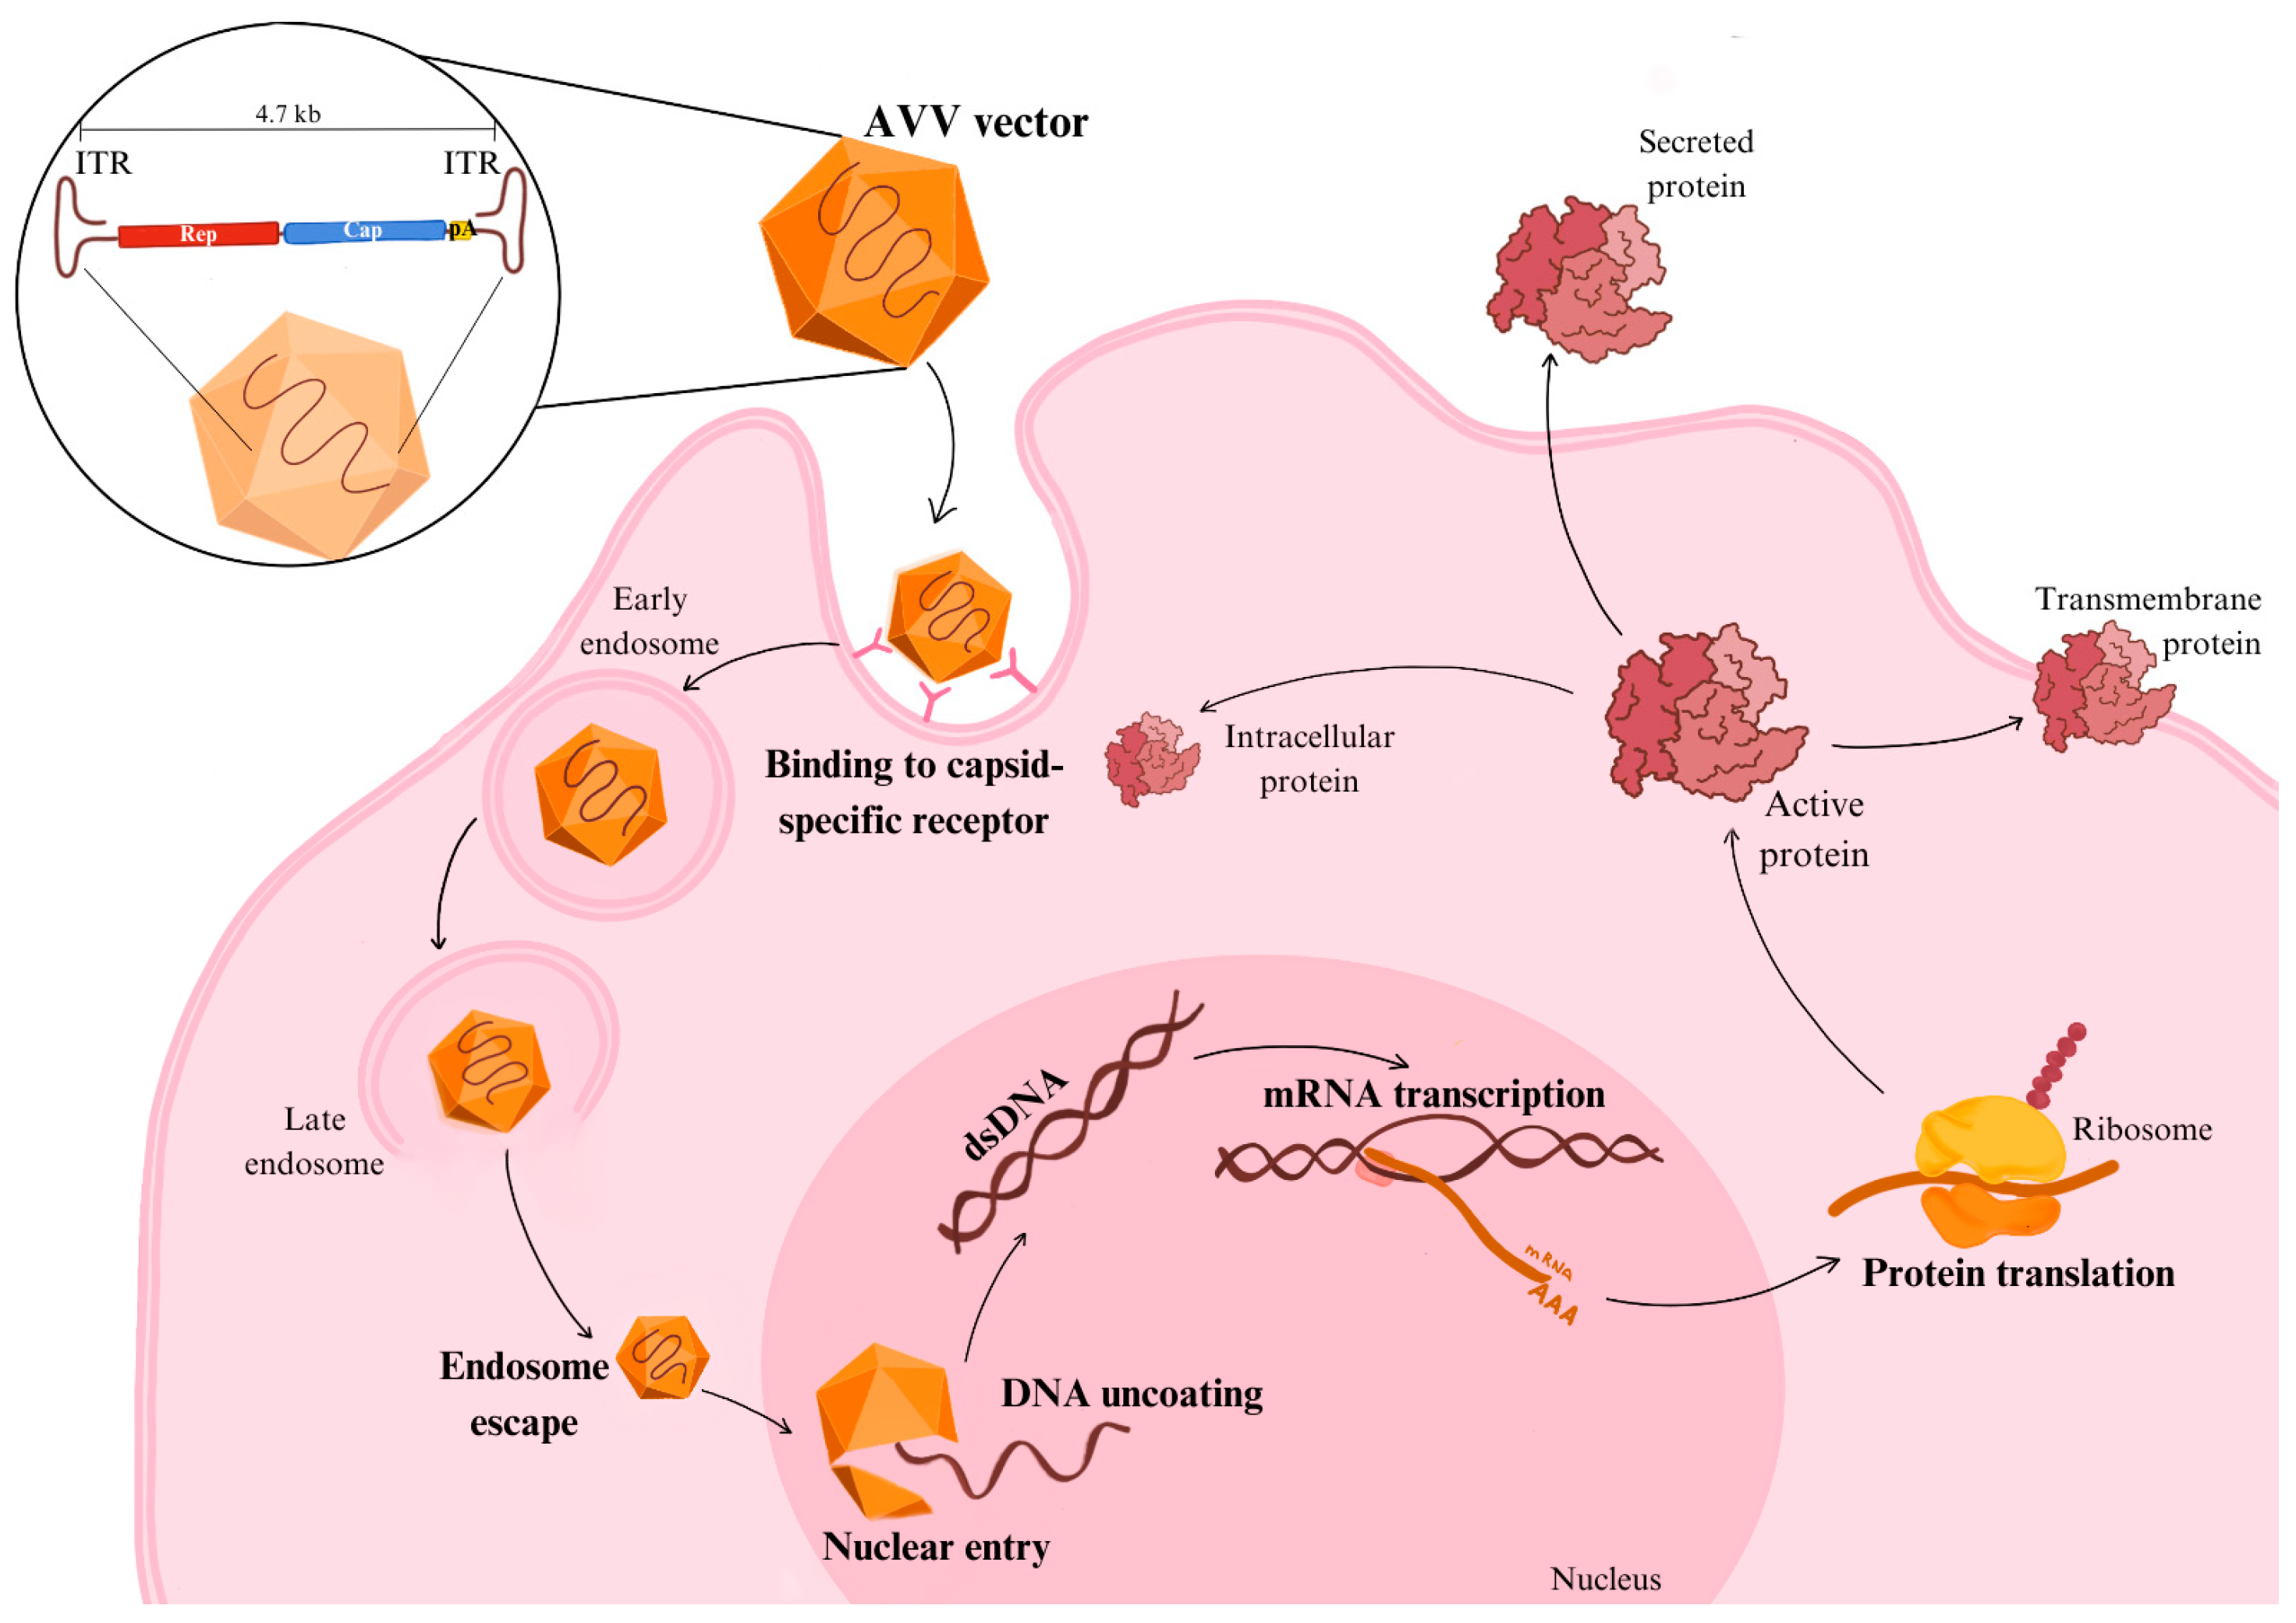
Manufacturing an AAV vector involves three plasmids co-transfected into HEK293 cells. One carries the transgene flanked by inverted terminal repeats, another provides the viral rep and cap genes, and the third supplies helper functions from adenovirus. After 48 to 72 hours, the cells are harvested and the virus is purified through a combination of ultracentrifugation and chromatography steps. The final product needs to meet stringent purity specifications because residual host cell DNA and empty capsids can trigger immune responses. Empty capsids are a real problem. Depending on your production process, anywhere from 20 to 60 percent of your particle count may be empty shells that carry no therapeutic payload. Regulatory agencies now expect you to report the ratio of full to empty capsids, and a high empty fraction can compromise both efficacy and safety. Sucrose gradient ultracentrifugation still remains the gold standard for separation, though alternative methods like ion-exchange chromatography are gaining traction.
Common Pitfalls and Nuances
One thing beginners often miss is that AAV does not produce productive infection in non-dividing cells in the way lentivirus does. It forms stable episomal vectors primarily. This means your expression level depends heavily on promoter strength and chromatin environment at the integration site, which is essentially random and infrequent. For applications requiring sustained long-term expression without integration, AAV is still a solid choice, but you should not expect the same level of durability as you would with integrating vectors. Another counter-intuitive point is that higher doses are not always better. Immune clearance becomes a significant factor at elevated vector doses. Pre-existing neutralizing antibodies against common serotypes are found in a large portion of the population, and even in antibody-naive subjects, a strong innate immune response can clear transduced cells within days. This is particularly relevant for systemic administration where liver and spleen sequestration can reduce the effective dose reaching your target tissue. Vector genomes can recombine if your transgene contains repetitive sequences or if you design constructs with overlapping homology arms. I have seen teams accidentally create recombinant AAV particles that carry unexpected deletion products, which then show up as faint bands on gel analysis and skew your potency data. Running a careful PCR survey across the junction regions before scaling up production saves a lot of headaches downstream.
Get the Full Details
Practical Workflow Overview
If you are starting from scratch, the typical timeline is roughly three to four months for a first-in-class AAV construct. Vector design and plasmid preparation take about two weeks. Cell culture and transfection require three days, followed by harvest and lysis. Purification through CsCl gradient or affinity chromatography takes another two to three days. You then need to characterize the product for titer, potency, endotoxin levels, and mycoplasma contamination, which adds another one to two weeks. Quality control metrics you should be tracking include quantitative PCR for vector genome titer, capsid ELISA for total particle count, and a functional assay to confirm transgene expression. The ratio between these two titer measurements tells you your full-to-empty capsid ratio. Anything below 80 percent full capsids is worth investigating further before moving into in vivo studies.
Limitations You Need to Accept
AAV gene therapy has clear constraints that cannot be ignored. The packaging limit is approximately 4.7 kilobases, so your therapeutic cassette including promoter, transgene, and polyadenylation signal must fit within that window. Larger genes require split-vector approaches or dual-AAV strategies, which introduce additional complexity around co-transduction efficiency and potential reconstitution of functional virus. Immunogenicity remains the biggest unresolved challenge. Both cellular and humoral immune responses can limit the duration and magnitude of expression. Repeat dosing is currently very difficult because pre-existing antibodies against the serotype neutralize subsequent administrations. Research into capsid engineering and immunomodulation protocols is ongoing, but there is no universally accepted solution yet. For some indications, AAV is simply the wrong tool. If you need transient expression, lentiviral or mRNA-based approaches may be more appropriate. If your target tissue is difficult to access or the required dose would exceed safe systemic exposure limits, local or regional delivery strategies need to be evaluated carefully. AAV is not a universal solution, and recognizing when another platform fits better is as important as knowing how to use it well.