Understanding Agonists in Pharmacology
I deal with receptor pharmacology mostly in a clinical and research context. The term comes up constantly in med school, residency, and when you're reading papers on drug development. It's one of those foundational concepts that people gloss over early on and then pay for later. An agonist is a molecule that binds to a receptor and activates it, producing a biological response. That's the basic textbook definition. The more useful way to think about it is in terms of two properties: affinity (how well it sticks to the receptor) and efficacy (how well it actually turns the receptor on once bound).
What Is An Agonist and How Does It Differ From Other Ligands
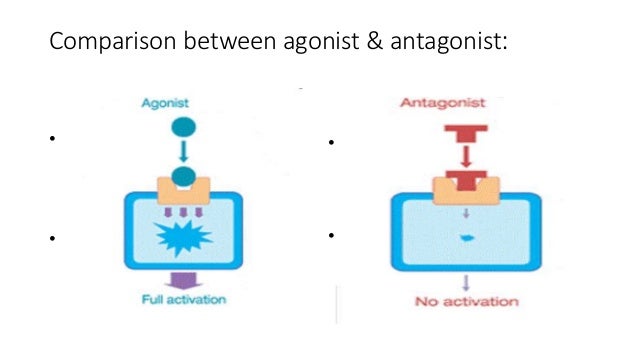
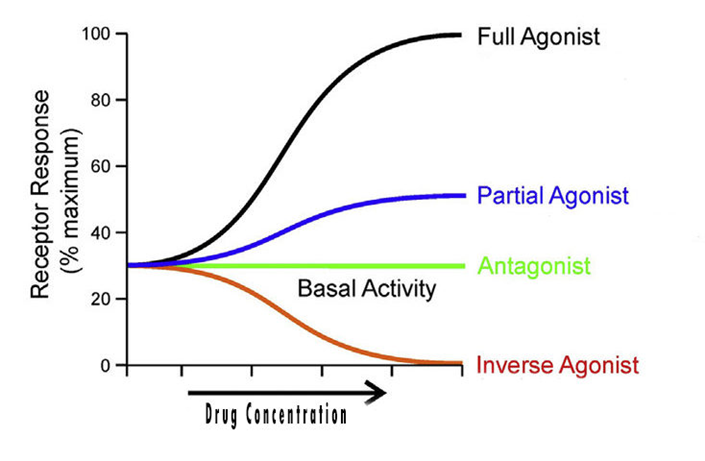
Not everything that binds to a receptor does something. An antagonist binds without activating anything. It just occupies the seat. A partial agonist binds and activates, but only produces a submaximal response even when all receptors are occupied. An inverse agonist goes the opposite direction — it stabilizes the receptor in an inactive state and reduces any baseline activity the receptor might have. The difference between a full agonist and a partial agonist matters enormously in practice. Take buprenorphine. It's a partial agonist at the mu-opioid receptor. That means no matter how much you give, you hit a ceiling effect. The respiratory depression risk plateaus. That's why it's useful in opioid use disorder treatment — it's hard to overdose on in the traditional sense, and it actually blocks full agonists like heroin from binding effectively because of its high affinity. I've seen people miss that interaction entirely and wonder why a patient on buprenorphine wasn't responding to standard pain protocols. The workaround is stacking short-acting full agonists at higher doses or using non-opioid adjuvants. It's not intuitive until you've worked through a few cases. Another thing beginners consistently get wrong is assuming that potency equals efficacy. They're independent. A drug can be extremely potent (active at nanomolar concentrations) but have low efficacy, meaning it maxes out at a weak response. Conversely, a less potent drug can be a full agonist with high intrinsic efficacy. When you're reading dose-response curves, the Emax tells you about efficacy. The EC50 tells you about potency. Don't conflate them.
There's also the concept of spare receptors, which complicates the picture further. Some systems have more receptors than needed to produce a maximal response. In those cases, a partial agonist might actually produce a near-full response simply because the system has receptor reserve. I ran into this when reviewing data on beta-2 adrenergic agonists in airway smooth muscle. The in vitro data suggested modest efficacy, but clinically the bronchodilation was robust. Once I accounted for receptor density differences between the assay system and the target tissue, the numbers made sense. The practical takeaway is that agonist classification isn't just academic taxonomy. It directly affects dosing strategies, side effect profiles, and drug interactions. If you're interpreting clinical data or designing a study, always note whether you're dealing with a full, partial, or inverse agonist and whether your model system has spare receptors. Getting either wrong will throw off your conclusions.