The basics nobody bothers explaining well
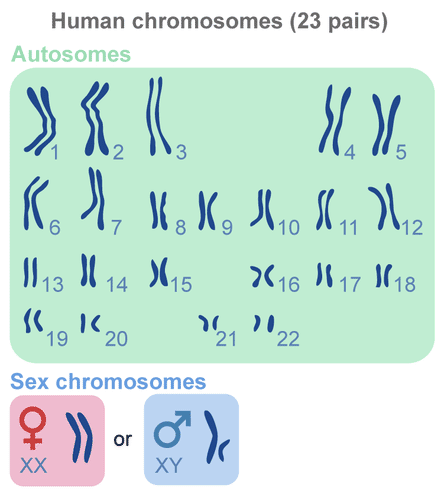
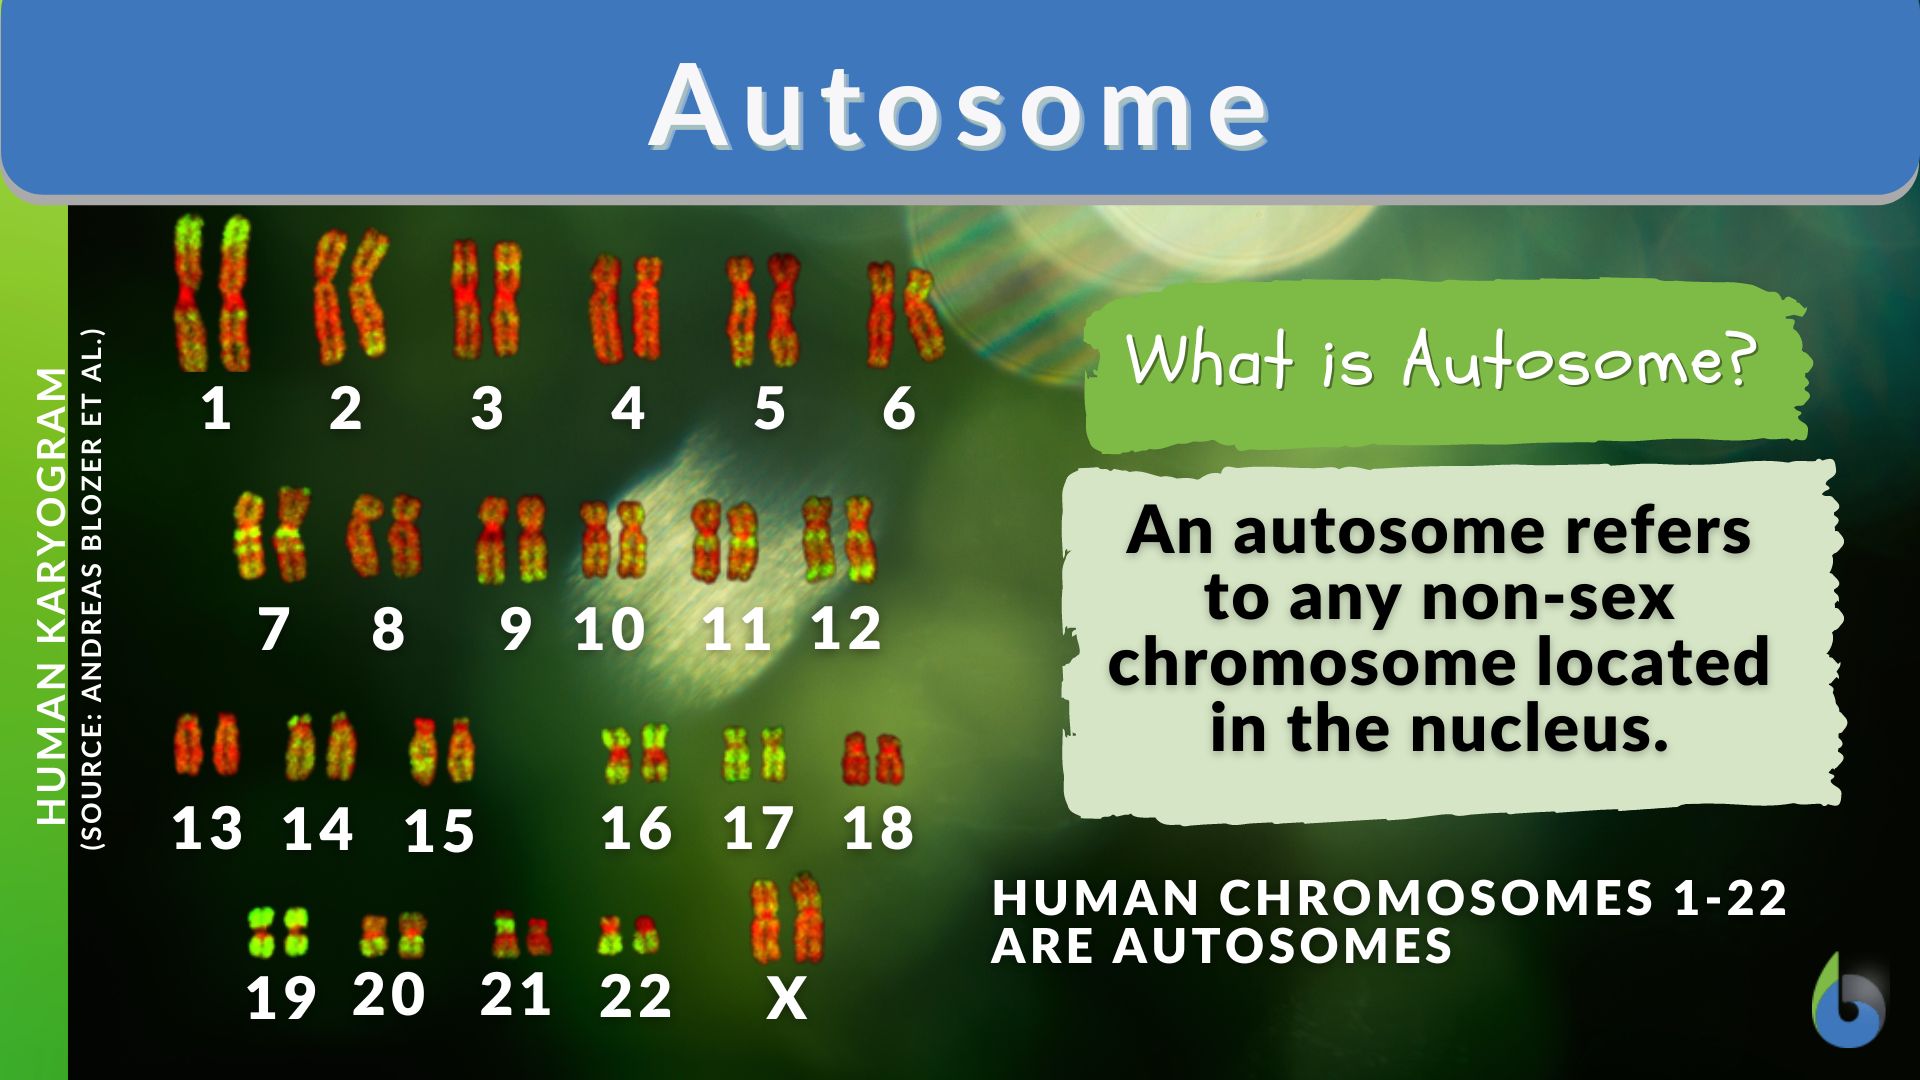
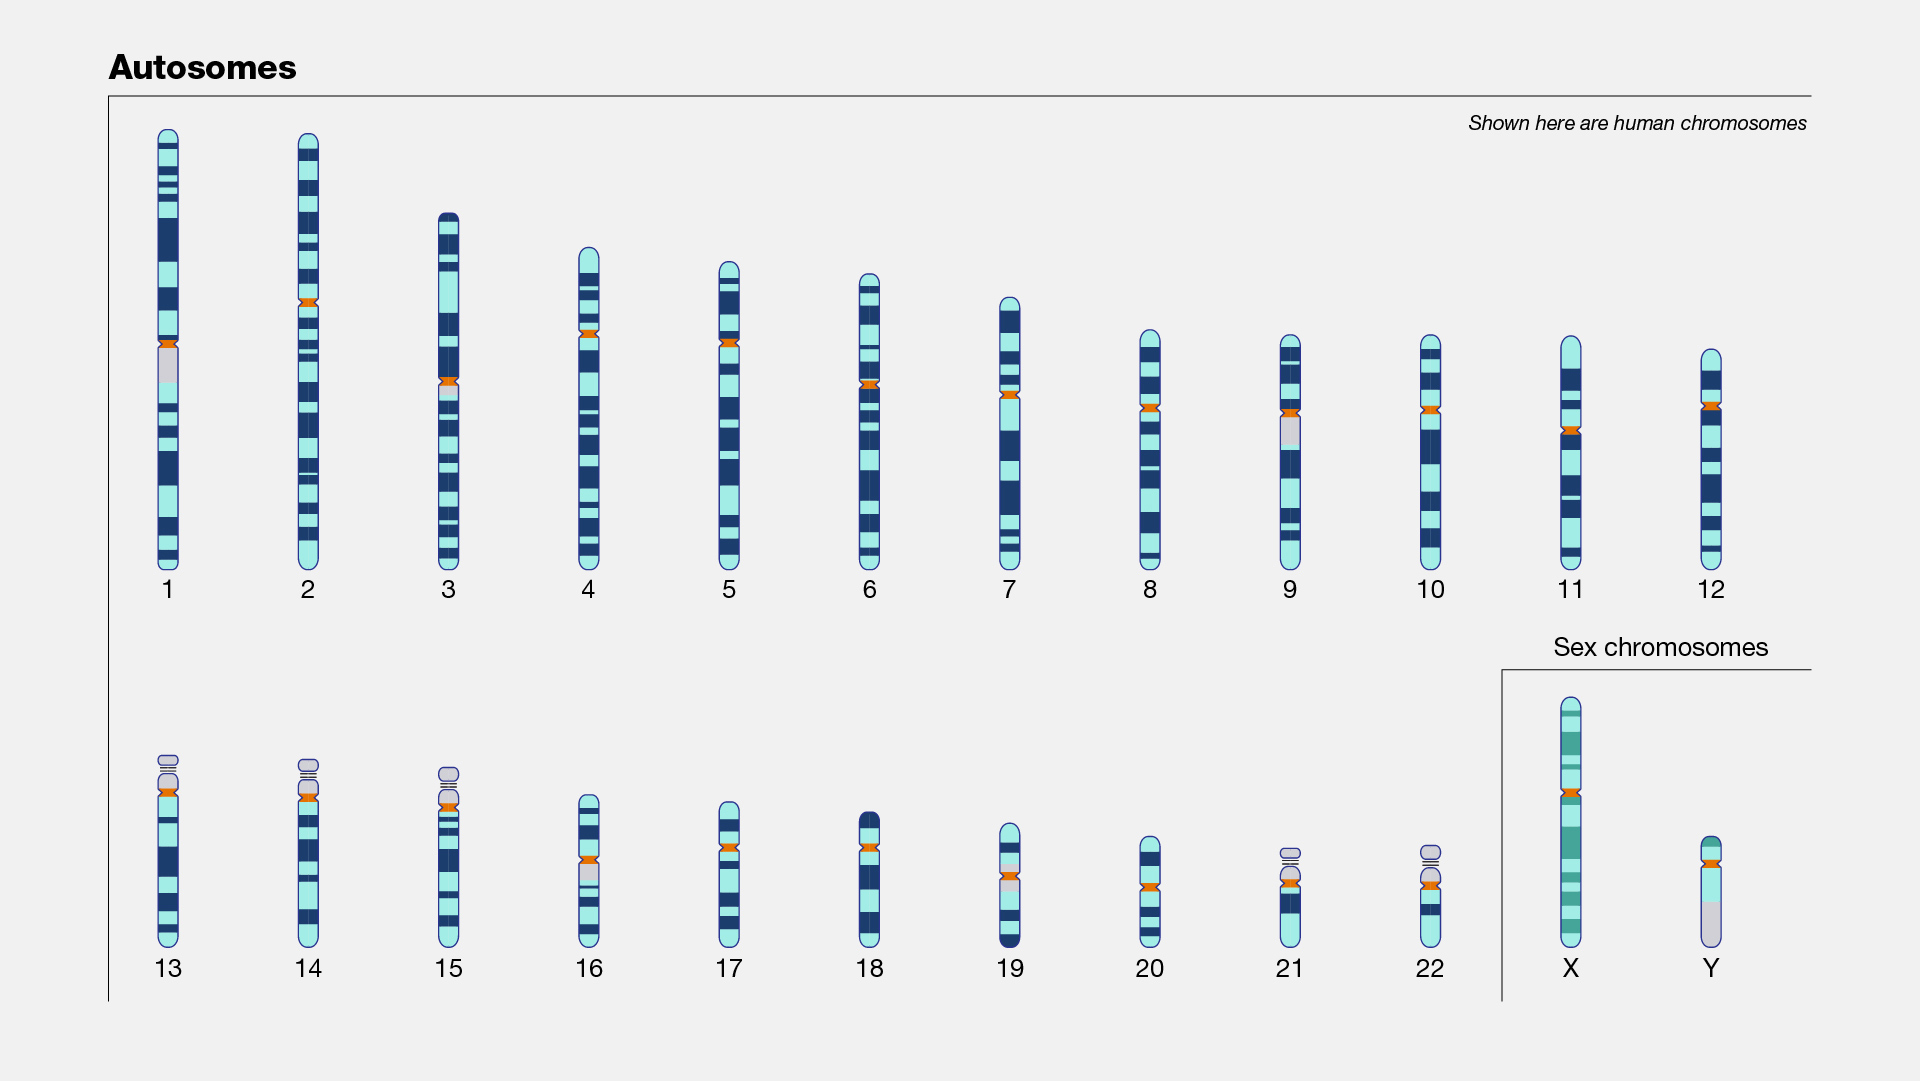
An autosome is simply any chromosome that isn't involved in determining sex. In humans, that means chromosomes 1 through 22. You have two copies of each one — one from your mother, one from your father. The remaining pair, X and Y, are the sex chromosomes. That's it. That's the entire definition.Most people encounter autosomes in the context of genetic testing or karyotype analysis. When a lab runs a chromosomal microarray or a whole genome sequence, they're looking at both autosomes and sex chromosomes simultaneously, but the interpretation pipelines treat them very differently. Sex chromosomes get special handling because of dosage compensation and the fact that males and females have different complements. The reason the autosome/sex chromosome split exists isn't just taxonomic convenience. It comes up constantly in clinical genetics when you're calling copy number variants. A deletion on chromosome 7 gets classified differently than a deletion on the X chromosome. Autosomal recessive disorders follow one pattern. X-linked disorders follow another. Getting this wrong in a report can genuinely mislead a clinician. I worked on a project a while back where we were parsing CNV calls from array data, and I hit a real problem. The variant calling pipeline was annotating a duplication on chromosome 15 as a simple autosomal gain. But that region overlaps the Prader-Willi/Angelman critical zone, and the imprinted region behaves completely differently depending on whether you inherited it from your mom or your dad. A standard autosomal annotation completely missed the parental origin implication. The workaround was to layer in methylation-specific data and run a parent-of-origin phasing step specifically for chromosome 15q11-q13. It added about forty minutes to the pipeline but saved us from issuing a clinically misleading report.
Autosomes in practice
When you're actually working with autosomal data, there are a few things that will bite you if you don't expect them. Copy number normalization is trickier on autosomes than people realize. GC bias correction matters more on larger chromosomes. Chromosome 1 has a different GC distribution profile than chromosome 22, and if your normalization doesn't account for chromosome-specific bias, you'll get false positives at the margins of large chromosomes. I've seen entire chromosomes show artifactual copy number shifts just because the batch had slightly different library prep conditions. Segmental duplications on autosomes are a nightmare for mapping. Chromosomes 1, 9, and 16 are particularly bad. The reads from duplicated regions map ambiguously, and most standard pipelines either discard them or assign them randomly. This means you can miss real deletions or duplications in those areas. The workaround is to use a graph-based reference genome or a tool like DELLY that accounts for structural variation explicitly rather than relying on a linear reference.
Ploidy assumptions break down. Most callers assume diploidy for autosomes. That's usually fine. But in cancer samples, autosomes frequently show complex aneuploidy. If you're analyzing tumor data with a germline-focused pipeline, you'll get garbage results on autosomes just as much as on sex chromosomes. Use a somatic CNV caller and feed it matched normal tissue when you can.
Get the Full Details

Common mistakes
Reporting autosomal variants without considering penetrance. Just because a variant falls on an autosome doesn't mean it follows simple dominant or recessive inheritance. Variable penetrance is extremely common on autosomes and will make your segregation analysis look wrong if you don't account for it. Ignoring population frequency filters. An autosomal variant that's present at 2% frequency in gnomAD is almost certainly benign for a rare disease workup. But people still report these because the variant is novel in their specific cohort. Check the population databases before you file a report. Using the wrong reference build. Autosome numbering hasn't changed between GRCh37 and GRCh38, but the coordinate systems have shifted significantly in some regions. If you're lifting over variants between builds, use a proper chain file. Simple coordinate won't handle the gaps and fixes correctly.
When autosomes aren't enough
Exome sequencing captures autosomal coding regions reasonably well but has known blind spots. Pseudogenes, highly homologous regions, and GC-rich areas on autosomes still get poor coverage. If you're investigating a condition where the causal gene is in one of these regions — and there are several on chromosomes 1 and 17 — you'll need supplemental testing. Sanger sequencing or targeted long-read approaches are the standard fallback. Whole genome sequencing is better but doesn't solve everything. Structural variants in repetitive autosomal regions still struggle. And cost is still a factor if you're doing population-scale screening rather than diagnostic work on already-suspected cases.