The Standard Position Every Anatomy Student Gets Wrong
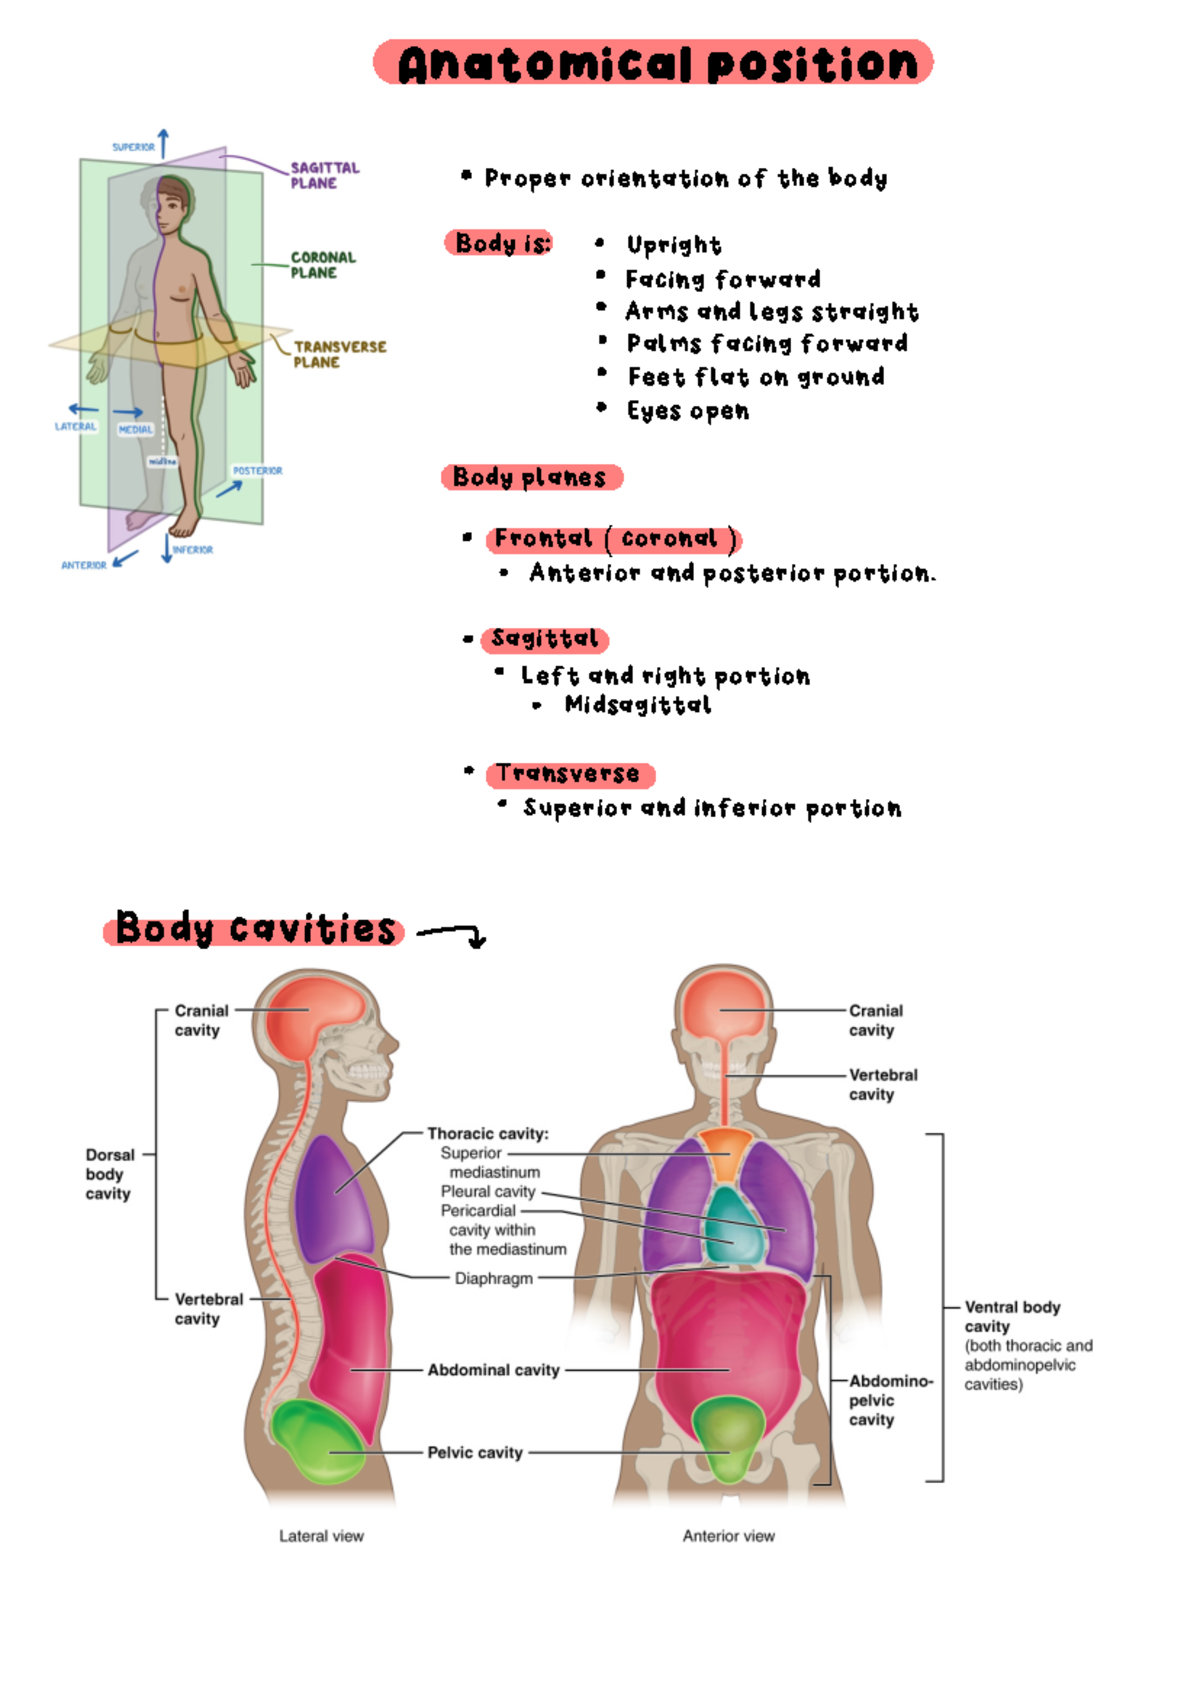
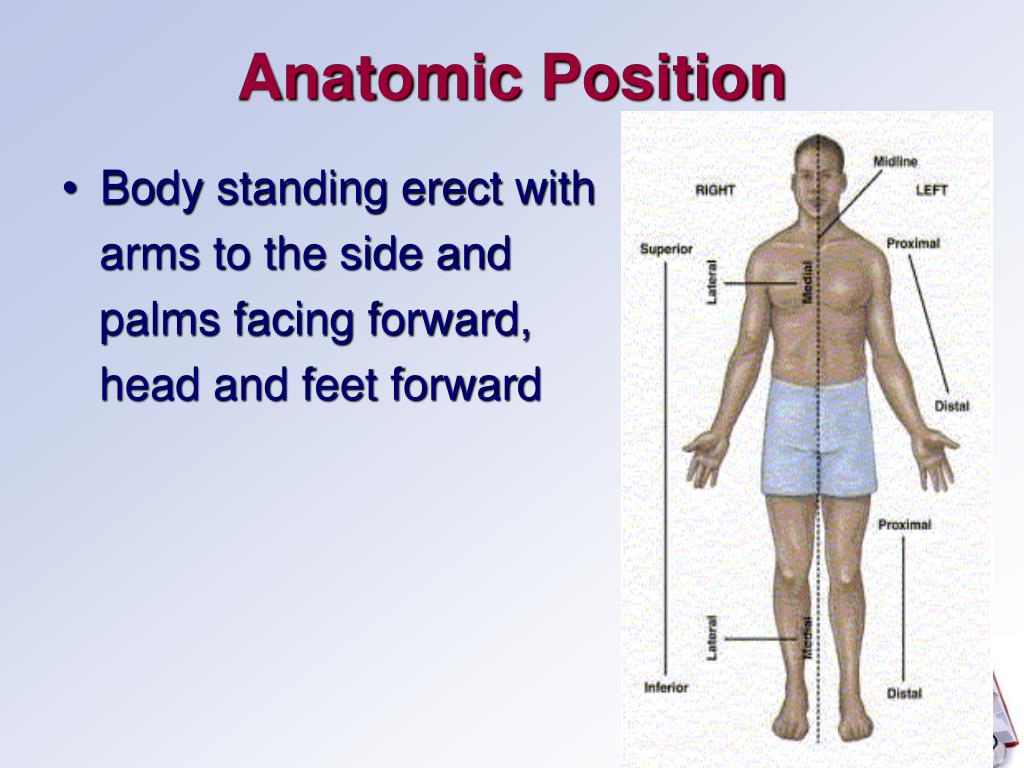
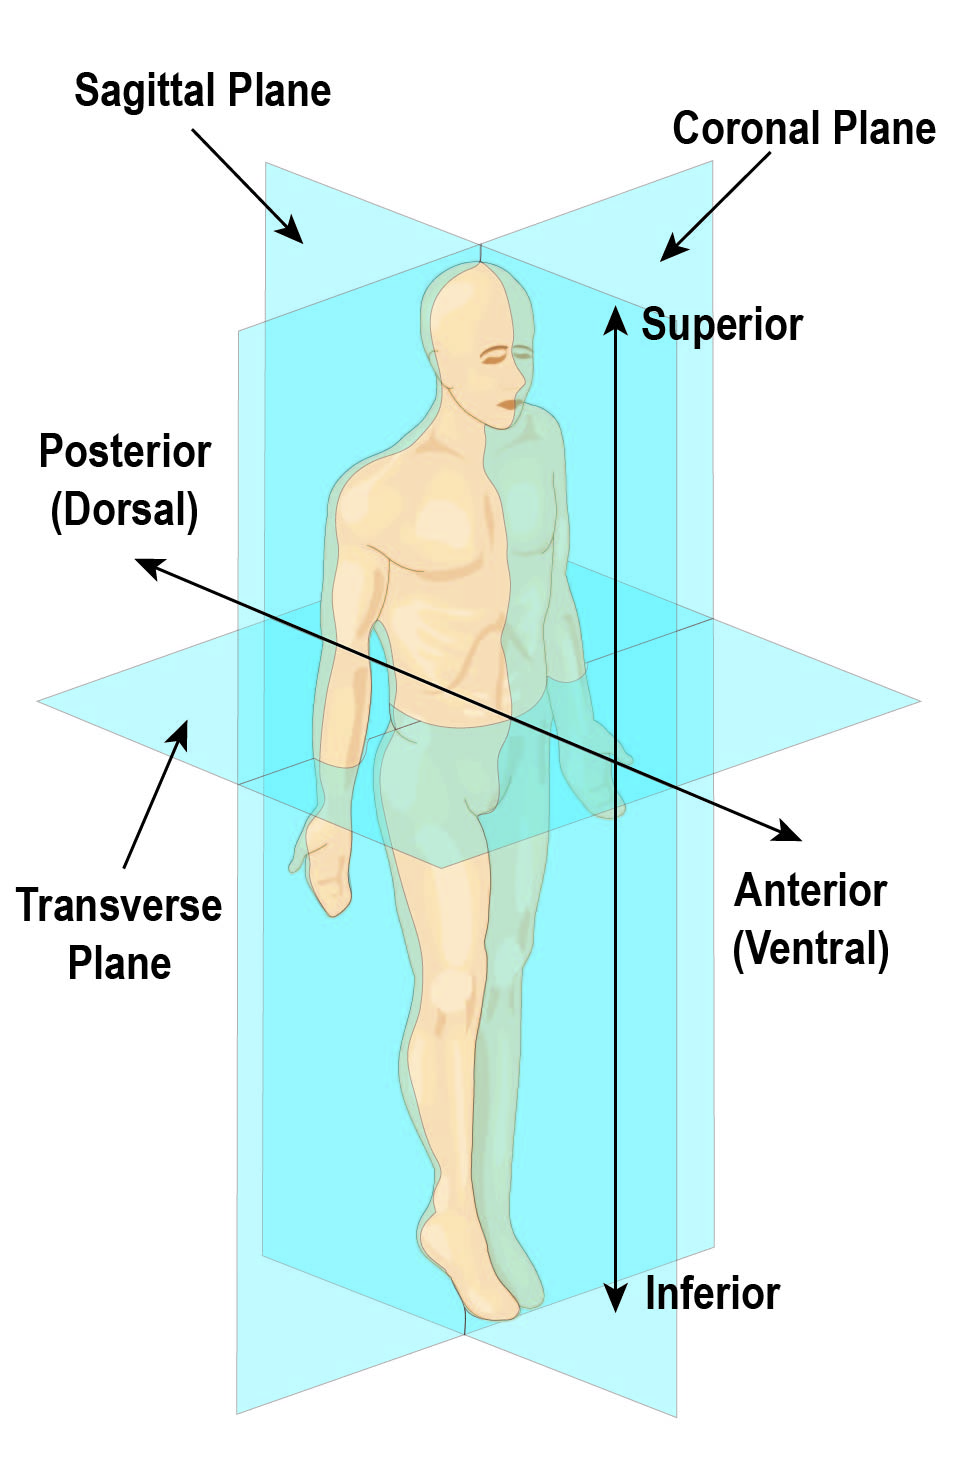
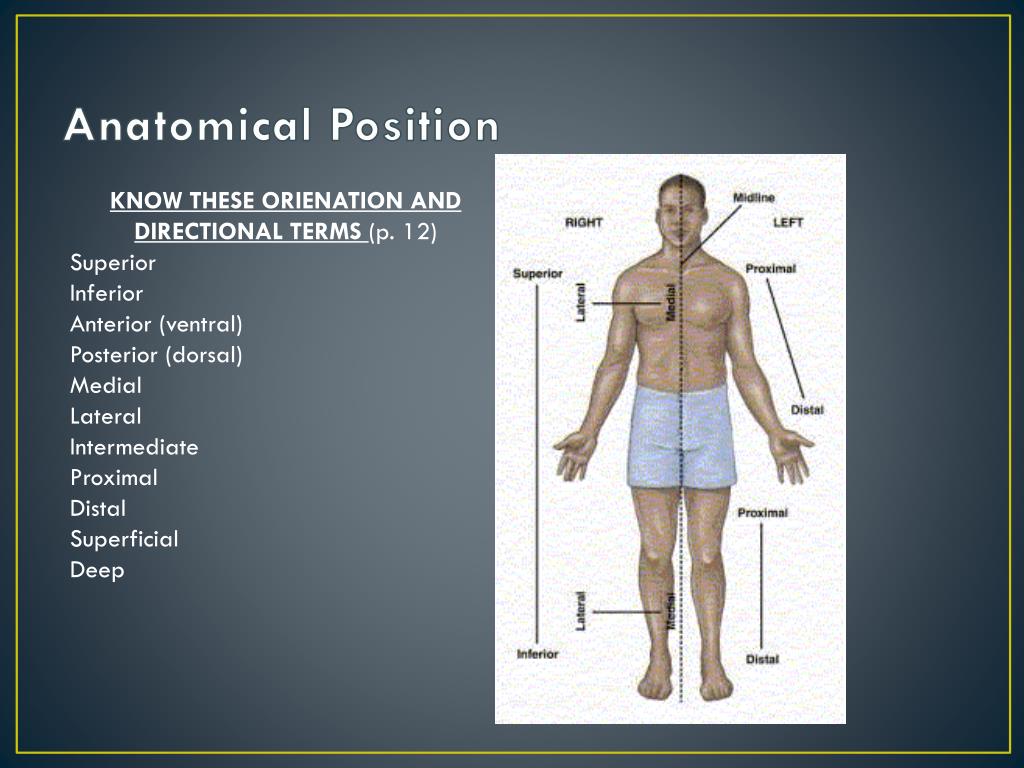
The anatomical position is the universal reference frame used in medicine, biology, and biomedical imaging. The body stands upright, eyes looking forward, arms at the sides, palms facing anteriorly, feet parallel and flat on the floor. That's it. But the devil is in the details, and most people gloss over them. Everything in human anatomy is described relative to this one standardized posture. If you're reading a radiology report that mentions "anterior cruciate ligament" or a surgical paper describing a "lateral incision," those directional terms only make sense if both people are imagining the same body orientation. Without this convention, you'd have surgeons and radiologists arguing about what "medial" means because one was looking at a supine patient and the other at a standing one. The hands are the part people get wrong most often. Palms forward. Not sideways. Not pronated. In the anatomical position, the radius and ulna are in supination, which puts the thumb laterally and the palm facing anteriorly. This matters because during embryological development, the upper limb actually rotates 90 degrees externally. That's why the thumb ends up lateral in the standard position rather than medial like you might naively expect.
Practical Issues I've Run Into
When I was calibrating a 3D scanning setup for a biomechanics lab, we had a subject who kept defaulting to a neutral hand position instead of full supination. The resulting surface model had the palmar fascia and flexor tendon paths completely misoriented relative to standard anatomical atlases. We couldn't register the scan to any reference database without manual correction. The workaround was straightforward but tedious: we placed small reflective markers on the volar aspect of each hand and used software constraints to force the virtual model into proper anatomical alignment before exporting. Saved us from having to rescansubjectby subject, which would have added about four hours to an already tight schedule. Another edge case that comes up frequently: amputees and patients with congenital limb differences. The standard anatomical position assumes a complete bilateral set of limbs. When you're documenting surgical approach for a transhumeral amputee, do you reference the remaining stump's orientation or the absent limb's expected position? The answer is the absent limb's position. Prosthesis design, clinical documentation, and imaging protocols all use the full theoretical anatomy as the frame of reference. I've seen prosthetists skip this and end up with socket orientations that feel natural to the patient but are recorded incorrectly in the medical chart, creating confusion for anyone reading the record later.
Common Pitfalls and Advanced Nuances
Here's something beginners rarely catch: the anatomical position is not the same as a neutral standing posture. In everyday life, most people stand with a slight knee bend, relaxed shoulders, and hands in a comfortable neutral position rather than full supination. The anatomical position is deliberately rigid and somewhat uncomfortable precisely because it needs to be reproducible. You wouldn't want two anatomists describing the same structure and having different mental images just because one slouched while the other stood at attention. The feet detail is another quiet landmine. "Feet parallel" means the long axis of each foot points forward, not splayed outward or pigeon-toed. In gait analysis and orthopedic assessment, foot progression angle is measured relative to this baseline. A deviation of more than 5 degrees from the anatomical norm is clinically significant and tracked over time. Also worth noting: the anatomical position uses standard anatomical terminology (Terminologia Anatomica), not colloquial descriptions. "Arm" specifically means the brachium region between shoulder and elbow. The forearm is the antebrachium. In casual speech people call the whole upper limb from shoulder to hand "the arm," which creates real problems in clinical documentation. I've read operative reports where "arm incision" was ambiguous enough to require a follow-up clarification because the surgeon meant forearm but wrote arm.
Get the Full Details
Limitations You Should Know About
The anatomical position works well for static descriptions and standard imaging planes. It breaks down when you're dealing with dynamic movement, extreme body positions during surgery, or comparative anatomy across species. In primate anatomy especially, the homologous structures don't map cleanly onto human anatomical terminology because quadrupedal locomotion places different rotational demands on the upper limb. You'll find textbooks struggling with this when they try to describe bat wing or whale flipper anatomy using human-centric directional terms. For clinical practice, the position also becomes problematic with patients who cannot stand. ICU patients on ventilators, trauma cases in supine position, and sedated surgical patients are all described using anatomical terms despite not being in the anatomical position. This requires mental rotation, which is where errors creep in. The solution isn't to abandon the standard—it's to be explicit about patient positioning in every report. "Patient supine, left side elevated" should appear in operative notes the way coordinate system labels appear in engineering drawings. If you need to describe anatomical relationships in non-standard positions, the best approach is to state the patient's actual position first, then translate findings back to anatomical terminology with that framing. Don't try to invent a new position system. The existing one is universal for a reason, and stepping outside it without clear documentation just creates ambiguity.