Understanding Decompression Sickness in Practice
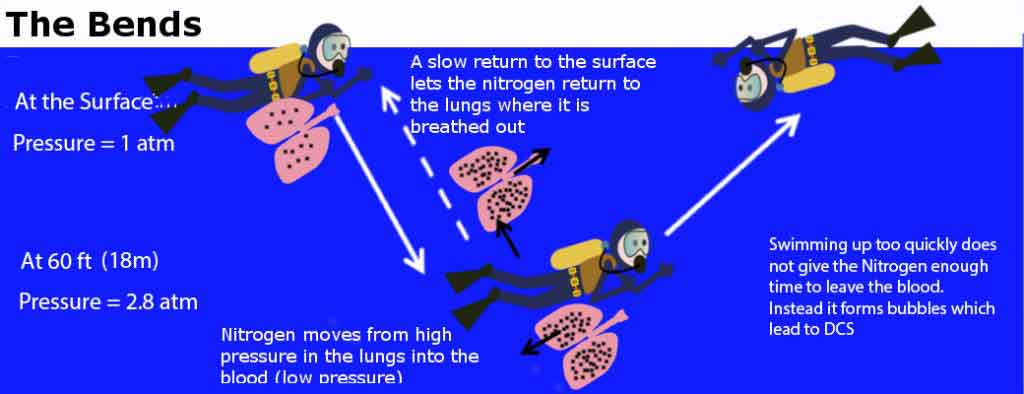
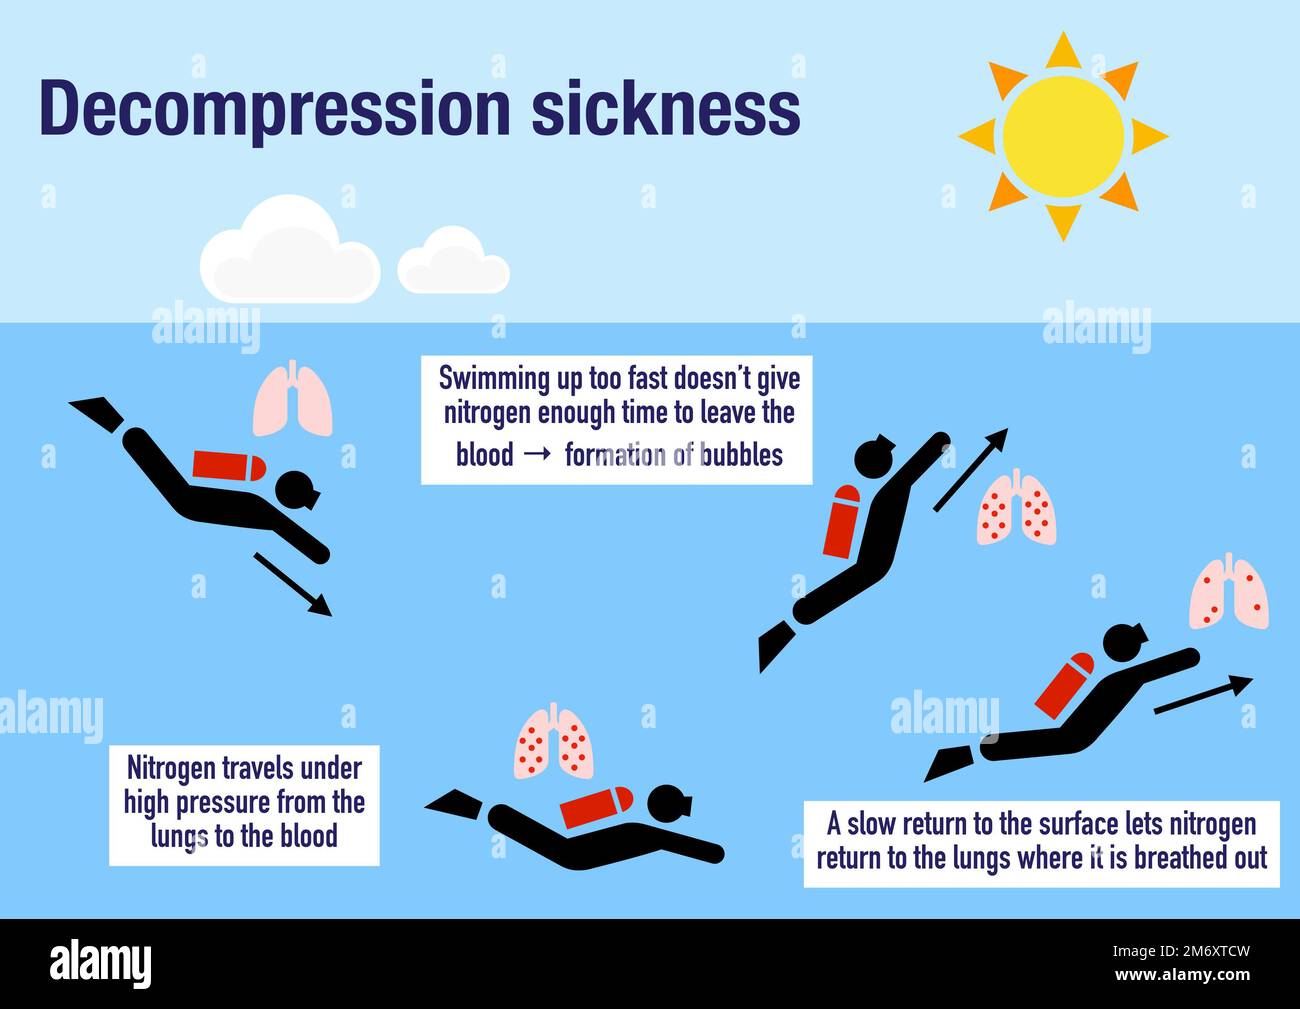
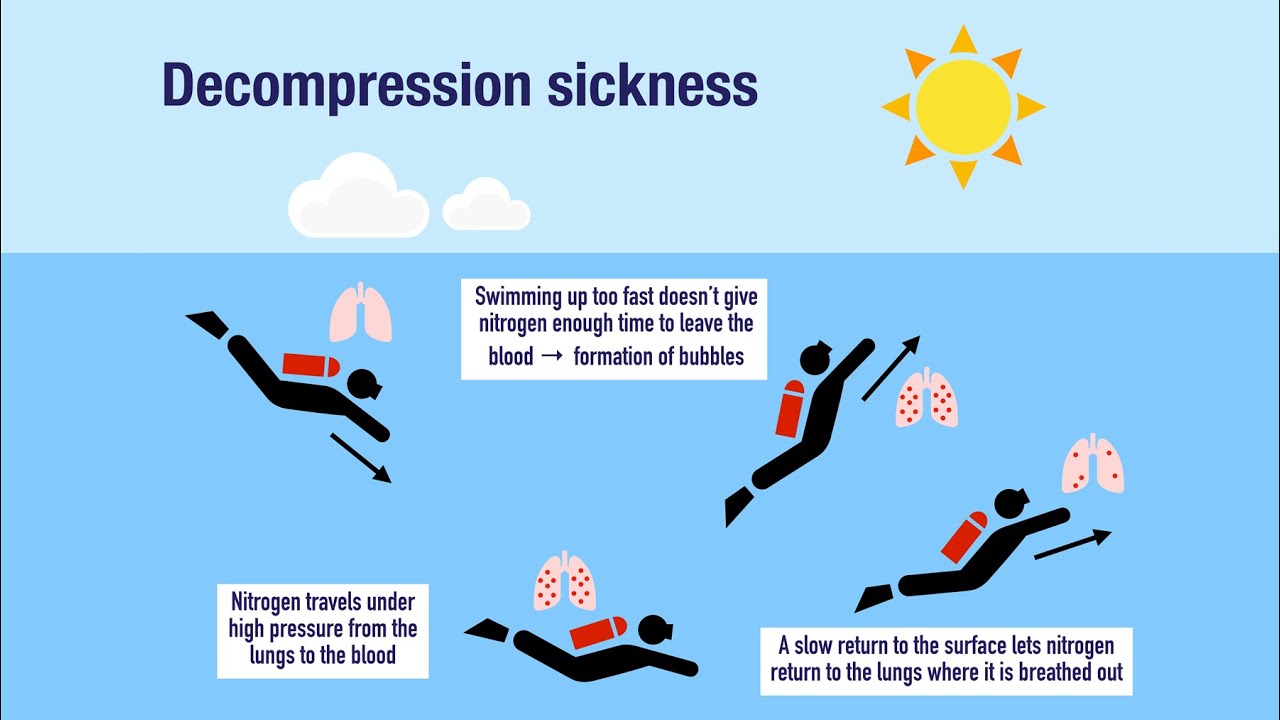
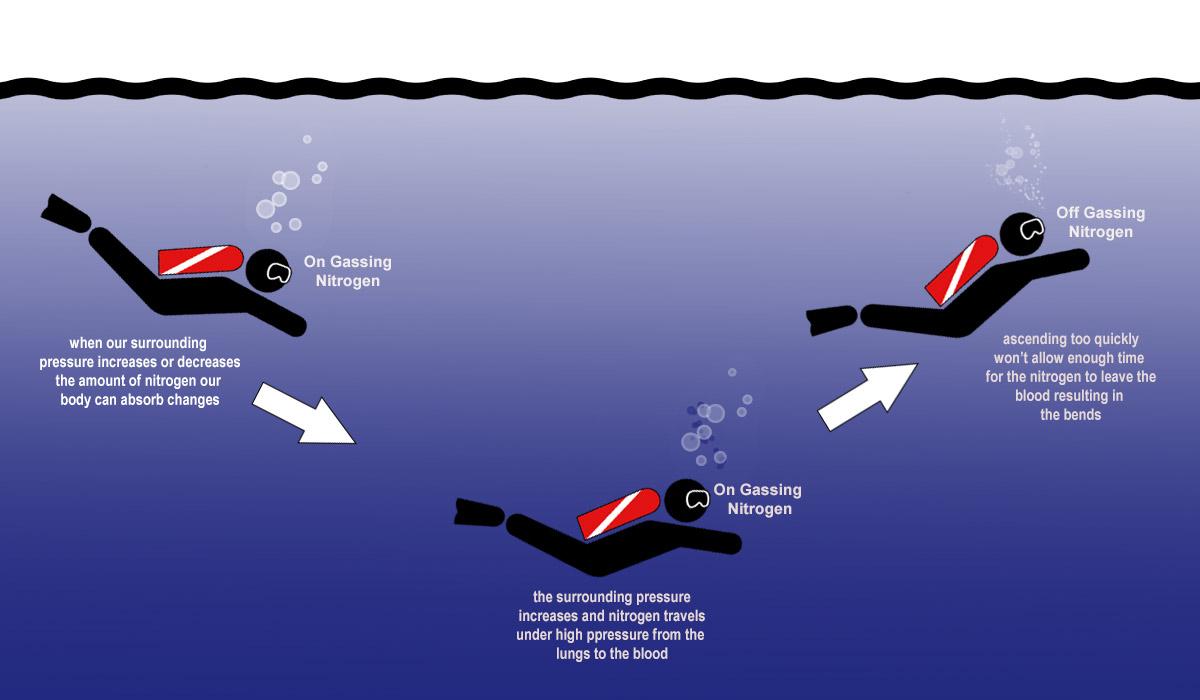
Decompression sickness, commonly called bends disease or DCS, happens when dissolved gases come out of solution inside your body as you move from high pressure to low pressure too quickly. This is not theoretical. It is a mechanical process that follows physics you can calculate, but one that does not forgive mistakes. The disease occurs because your tissues absorb inert gas—usually nitrogen—at depth. When you ascend, that pressure drops. If the drop happens faster than your blood and lymph can carry the gas back to your lungs for exhalation, the gas forms bubbles in your joints, nerves, bloodstream, and organs. Joint pain is the classic symptom. You feel it deep in your elbows, knees, shoulders, or hips. But that is the mild end of things. Type II DCS involves neurological symptoms: tingling, weakness, paralysis, dizziness, hearing loss, or shortness of breath. The spinal cord is actually the most commonly affected area, not your joints. That fact surprises most people I train.
Onset can be rapid, within minutes of surfacing, or delayed several hours. Delayed onset is the real trap because people feel fine at the surface and go home instead of getting evaluated. A friend of mine once had a 90-minute window where he drove himself to the hospital after a dive because he assumed his tingling fingers were just cold. By the time he arrived, he could barely walk. He recovered with hyperbaric treatment but it was unnecessarily close.
The Physics Behind It
Henry's Law governs how much gas dissolves in liquid under pressure. At thirty meters of seawater, the ambient pressure is about four atmospheres. Your blood and fat tissue hold roughly four times the nitrogen they hold at the surface. On ascent, that gas has to leave your tissues safely through your bloodstream and lungs. The critical variable is ascent rate. Standard recreational diving limits this to nine meters per minute or slower. Many dive computers beep at you for going faster, but those alarms are not always reliable. I have seen units that lag by ten seconds. Ten seconds at a fast ascent rate means you may have already exceeded safe limits without knowing it.
Get the Full Details
How It Actually Feels and Presents
The pain from DCS is hard to miss but easy to misidentify. Divers often describe it as a deep ache that worsens with movement, not a surface-level sting. It does not feel like a normal muscle cramp. A cramp resolves with stretching. The bends pain does not. Neurological DCS can present subtly. Numbness in the toes, a weird sensation when walking, bladder dysfunction, or unexplained fatigue. I once had a diver who complained only of extreme exhaustion after a night dive. No joint pain at all. He had been clearing the drains and assumed he was just tired. He was wrong. He needed recompression within two hours or risk permanent damage. Rash-like skin markings, called cutis marcia, appear in some cases. Itching, mottling, or a marbled appearance on the shoulders and upper chest. This is not an allergic reaction. It is bubble-related.
Prevention and Real-World Controls
The standard approach uses no-decompression limits based on depth and time. Tables and dive computers generate these. But these tools assume you are a healthy adult breathing compressed air at sea level. They do not account for a few real-world factors. Fat tissue absorbs nitrogen much more slowly than blood and muscle. If you are lean, you load and unload gas faster. If you have higher body fat, your decompression profile is actually safer on long, deep dives because your tissues absorb nitrogen slowly. This is counter-intuitive for most divers who assume being overweight makes DCS more likely. It does not work that way. Body composition matters more than weight alone. Another overlooked factor is repeat diving. Your tissues stay supersaturated after a dive. If you surface, spend a couple hours on land, and dive again, your second exposure starts from a higher baseline of dissolved gas. My standard rule is to add fifteen minutes to your no-decompression limit on any repetitive dive, even if your computer says you are clean. That buffer accounts for the residual nitrogen without needing complex calculations.
Hydration status changes your risk. Dehydrated blood is thicker. Bubbles form more easily and travel slower. I always make sure my team drinks at least half a liter of water before a dive and another liter after. It is a small thing that reduces risk more than most people expect.
When Conventional Limits Fail
Even when you follow every rule, DCS can occur. Recreational divers report it regularly at shallow depths and short durations. The myth that DCS only affects deep or technical divers is dangerous. I have treated cases from dives under six meters lasting twenty minutes. There is no safe threshold. The human body varies, and sometimes bubbles form regardless of your profile. Altitude diving changes everything. After a dive, ascending to altitude increases the pressure gradient between your tissues and the outside air. A dive that is perfectly safe at sea level becomes risky at elevation. The standard workaround is to wait at least twelve hours before flying if you have done a single no-decompression dive, and eighteen to twenty-four hours after multiple or repetitive dives. If you are flying to altitude, plan accordingly.
Treatment Reality
The only effective treatment for symptomatic DCS is recompression in a hyperbaric chamber using oxygen. There is no pill, supplement, or home remedy that removes bubbles once they are in your tissues. IV fluids help. Positioning the patient on their left side with the head slightly down improves blood flow to the heart and brain. Warmth matters too. Hypothermia slows circulation and worsens outcomes. If you suspect DCS, you call emergency services and get the patient to a facility with a hyperbaric chamber. The U.S. Navy Recompression Treatment Table 6 is the standard protocol, but commercial chambers use modified versions. Time is the main variable. Treatment within the first few hours yields the best outcomes. Each hour of delay reduces recovery probability slightly. After twenty-four hours, permanent damage becomes significantly more likely. One practical tip that most divers miss: keep the patient lying flat. Do not let them sit up or stand. Bubbles can travel to the brain if posture changes during the initial phase. This is why ambulances place DCS patients on stretchers and keep them horizontal during transport.
The Bottom Line
Decompression sickness is preventable most of the time, but prevention requires discipline, not just good intentions. Dive computers are aids, not guarantees. Your body changes from day to day based on hydration, fatigue, temperature, and previous dives. The tables assume ideal conditions. They do not get ideal conditions. If you dive, learn the signs beyond joint pain. Learn when to treat a symptom as an emergency rather than a minor inconvenience. And always know the location of the nearest hyperbaric facility before you enter the water. The Divers Alert Network maintains a searchable list online. Save it on your phone before you go.