Cognitive Behavioral Therapy is the most prescribed form of psychotherapy in modern practice, and for the most part that reputation is earned through results rather than marketing.
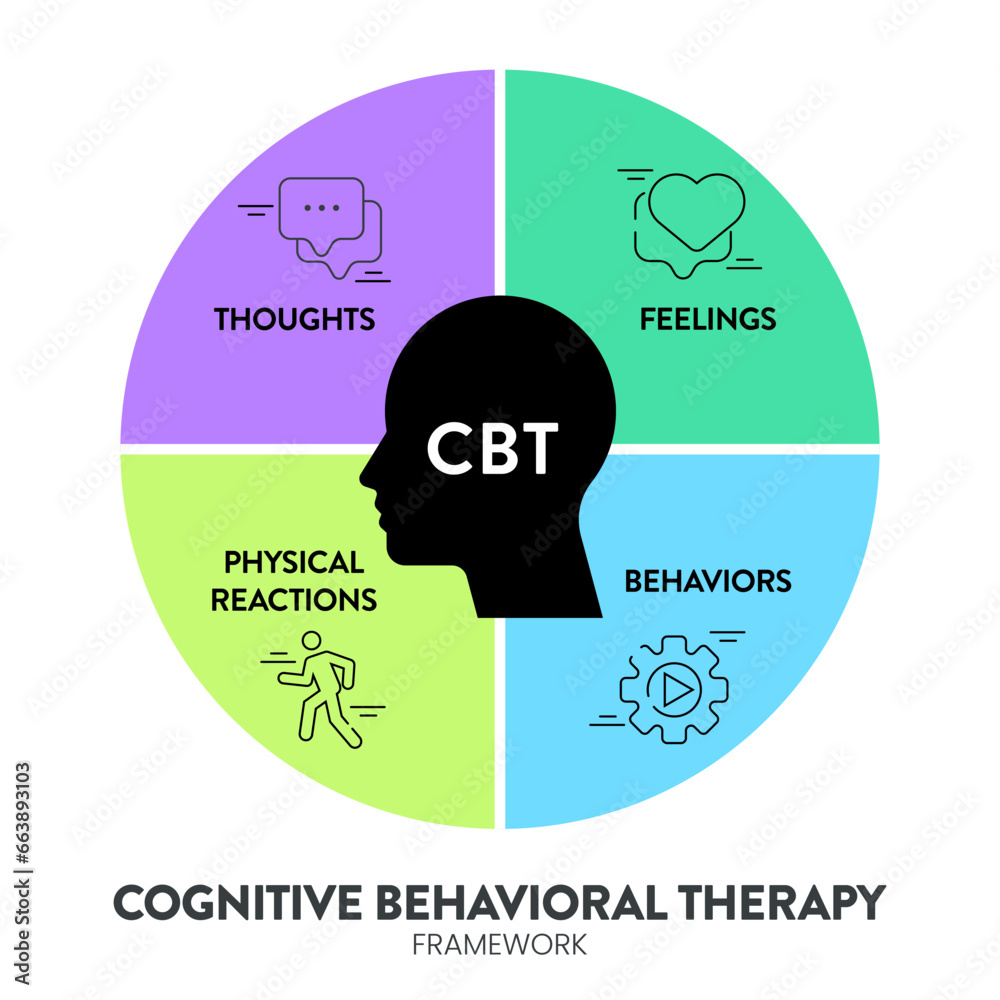
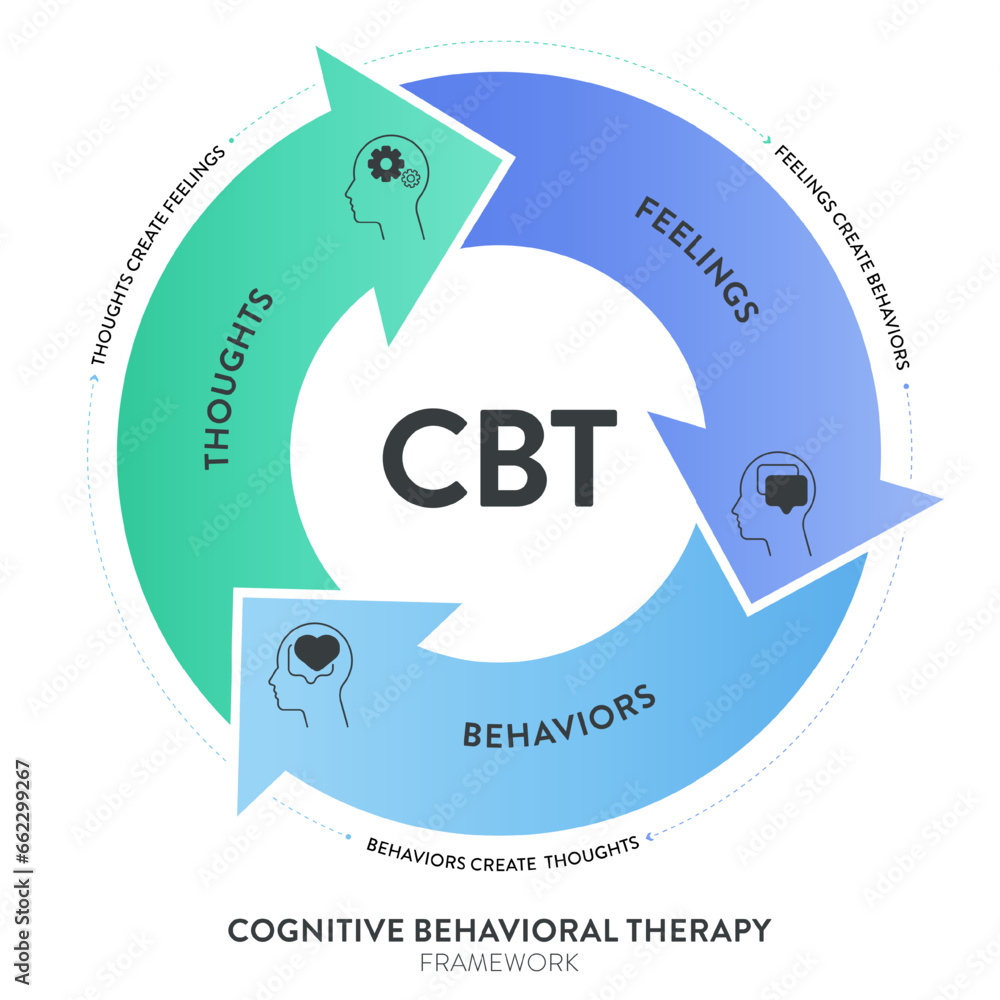
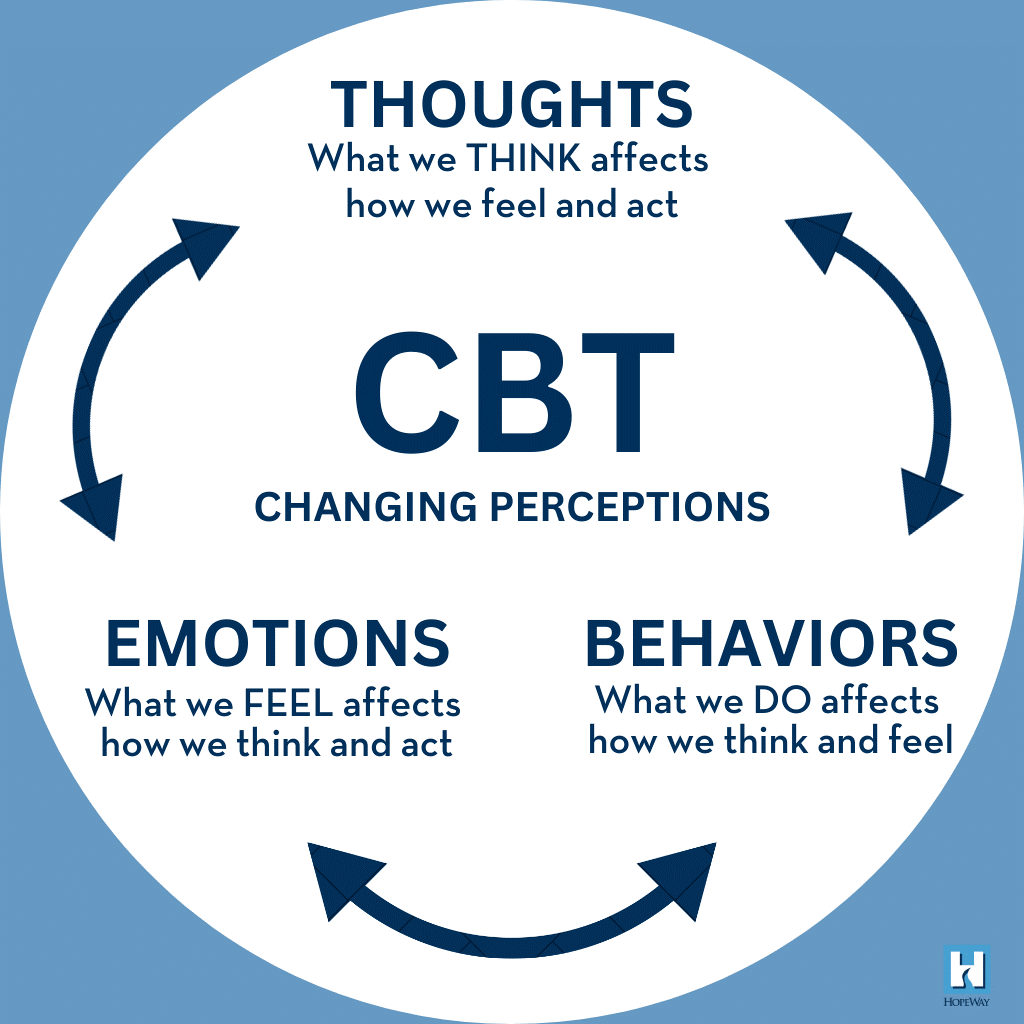
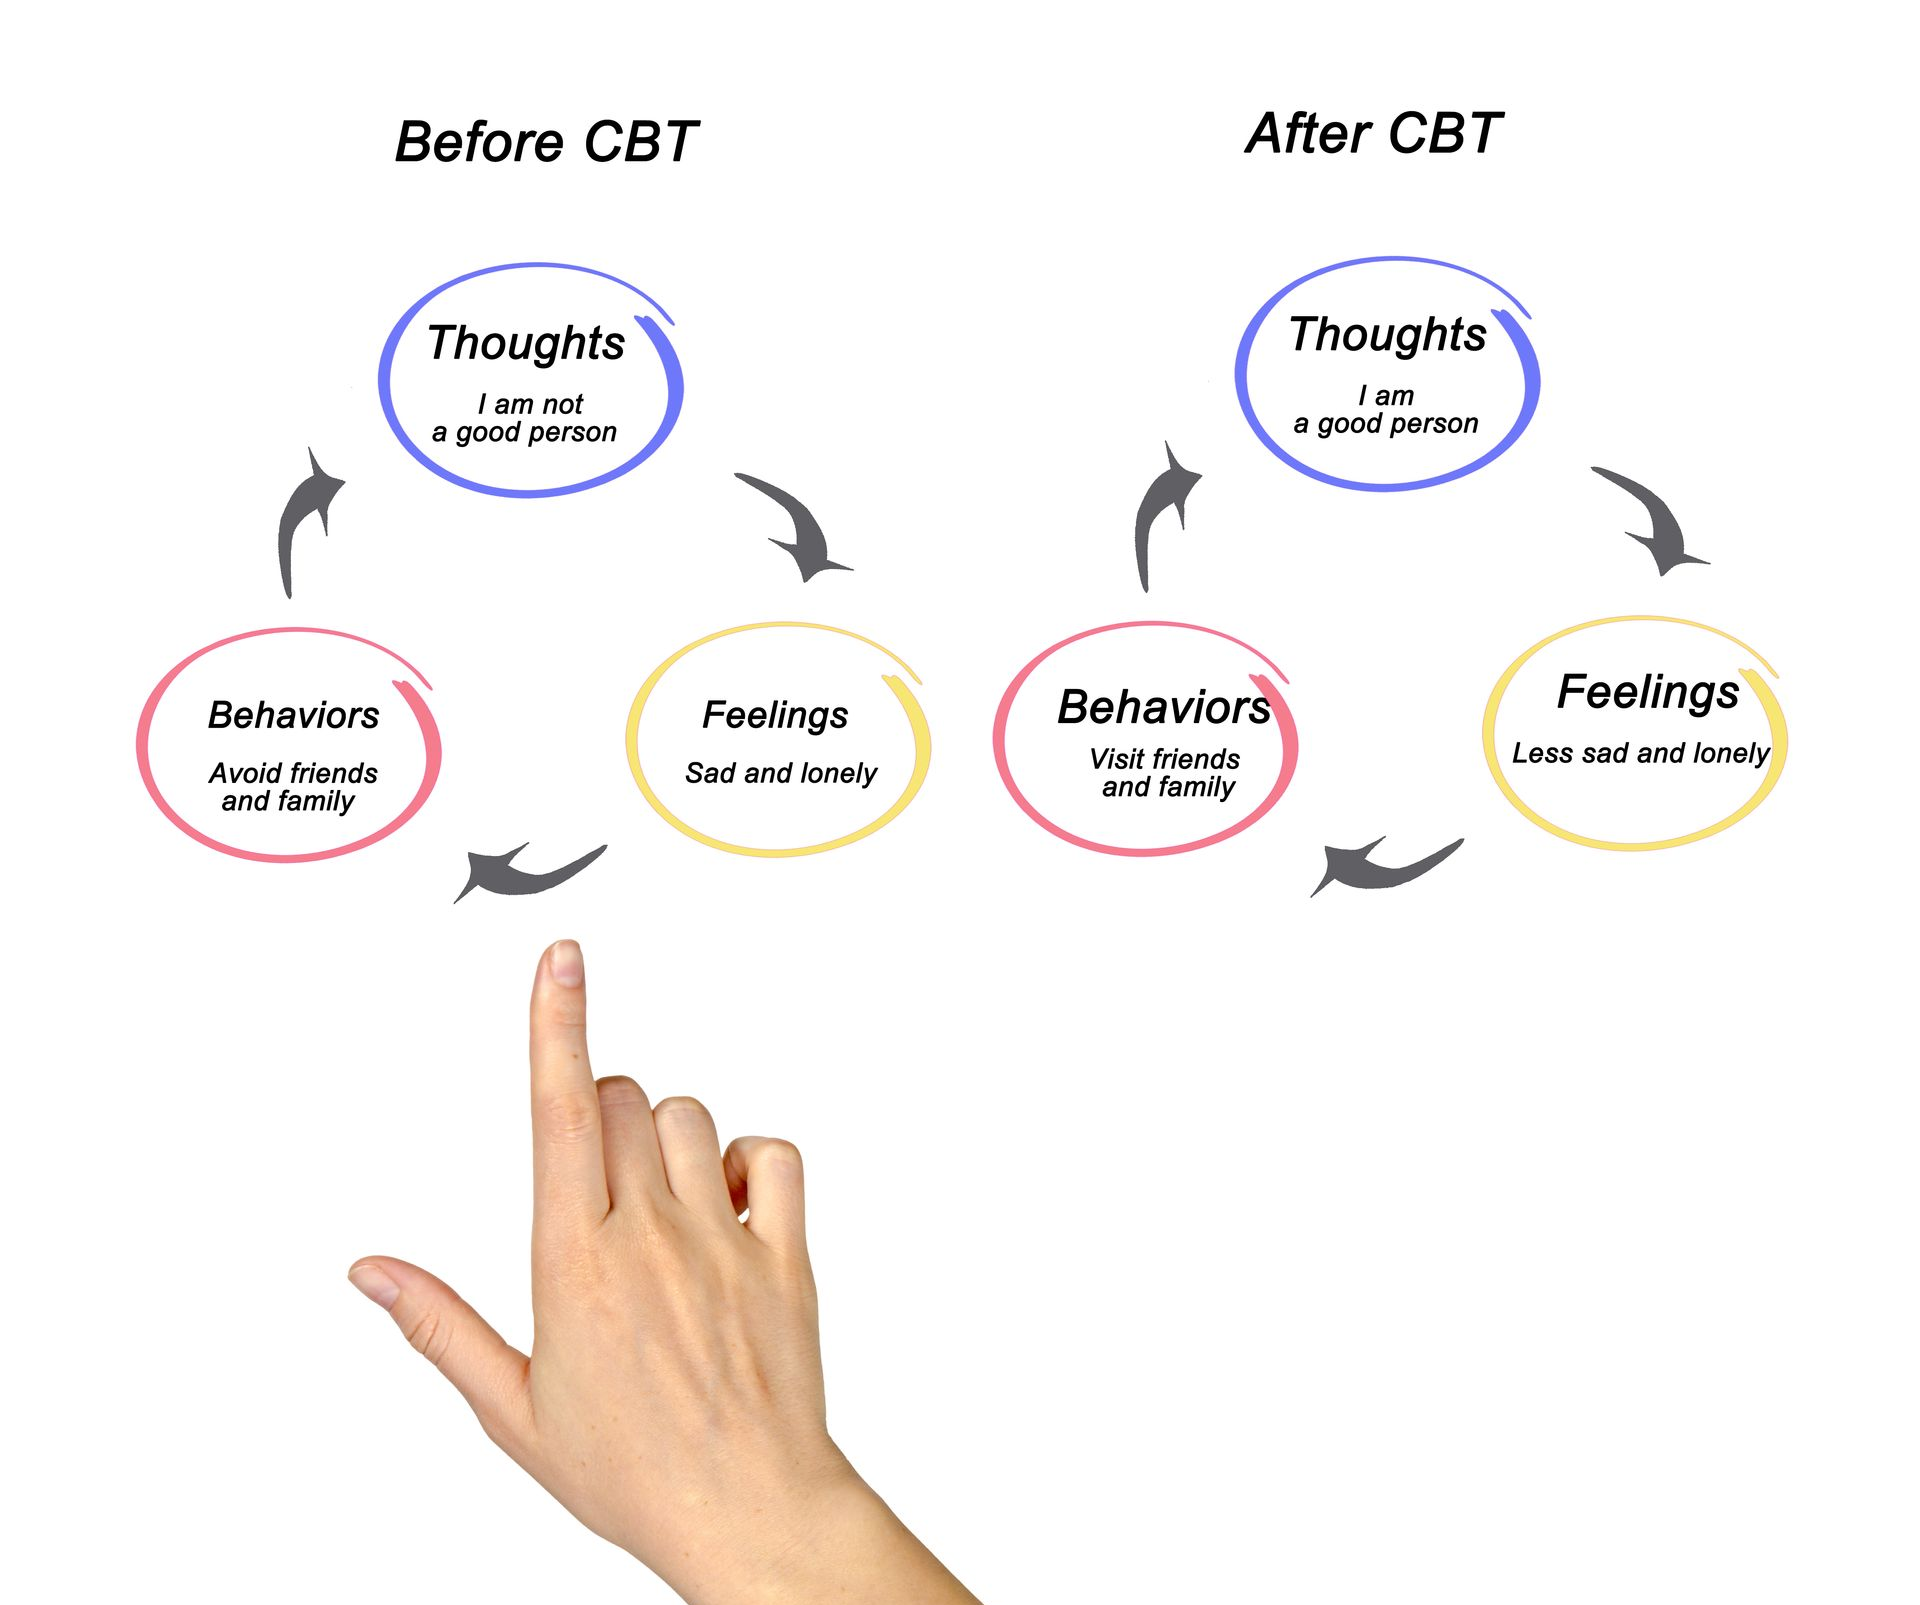
The basic mechanism is straightforward. Thoughts, feelings, and behaviors are treated as interconnected nodes. If you change one of them deliberately, the others shift along with it. The therapist helps you identify patterns where your thinking distorts reality, then you work through those distortions using structured exercises. That is the outline on paper. The actual sessions are less polished than the textbooks make them look. I spent several years working closely with clinicians who specialized in CBT protocols, and one thing that comes up repeatedly is the gap between how CBT is taught and how it plays out with real clients. Clients do not always recognize their own cognitive distortions. Some can label them on a worksheet. Most cannot do that on the spot during a live emotional spike. The workaround that actually works in practice is starting with behavioral activation before diving into the cognitive restructuring. Get the person moving, get their nervous system regulated a bit, and then the thought work lands better. I watched a clinician lose an entire session trying to do Socratic questioning with a client who was already in a panic state. Five minutes of grounding and breathing brought the client back to a place where the cognitive work was even possible. Skipping that step is a common failure mode.
What Is Cbt Therapy Good For
CBT has the strongest evidence base for depression and anxiety disorders. Generalized anxiety disorder, panic disorder, social anxiety, specific phobias, obsessive-compulsive disorder, post-traumatic stress disorder, and major depressive disorder all have robust clinical support. It is also used effectively for insomnia, chronic pain management, irritable bowel syndrome, and certain eating disorders. The treatment typically runs between twelve and twenty sessions for standard protocols, though severe or complex cases extend well beyond that range. The counter-intuitive part most people miss is that CBT is not purely a thinking exercise. A lot of the mechanism works through behavioral experiments where the client tests predictions against reality. "If I speak up in the meeting, everyone will think I am incompetent." The therapist assigns the client to speak up and then examines the actual outcome. More often than not, the predicted catastrophe does not materialize. That disconfirmation is what rewires the fear response over time. You cannot talk your way out of a conditioned fear response alone. You have to act differently and gather new evidence. Another nuance that gets glossed over is the role of homework. Without between-session practice, CBT is roughly half as effective, maybe worse. The sessions provide the framework and the skills. The homework is where the skills get installed. A typical cognitive restructuring assignment might involve keeping a thought record three times a day for a week. A behavioral activation plan for depression might involve scheduling one small activity per day and tracking mood before and after. This is where the real work happens outside the therapist's office.
CBT is not universally good for everything. It struggles with conditions rooted in deep personality structure, complex trauma that involves dissociation, or situations where the primary issue is external rather than internal. If someone is in an abusive relationship or living in unsafe housing, sitting down to examine cognitive distortions about their circumstances is not helpful. The problem is the circumstance, not the thinking. In those cases, the therapist needs to pivot toward safety planning and practical support before any cognitive work is appropriate. I saw a case where a therapist kept pushing thought records with a client whose depression was directly tied to ongoing financial ruin and family conflict. The client improved once the therapist switched to collaborative problem-solving around concrete stressors. The CBT framework got in the way of addressing the actual problem. CBT also has limits with severe depression where psychopathology is so entrenched that patients lack the cognitive bandwidth for structured work. At that level, medication combined with therapy often produces better outcomes than CBT alone. Similarly, clients with high resistance to self-monitoring or who do not see the value in homework tend to stall out quickly. There is no workaround for motivation. If the client is only there because someone else told them to go, progress will be slow or nonexistent. The format is also more structured and directive than other therapies, which is a strength for some people and a dealbreaker for others. Clients who prefer open-ended exploration or who want to spend sessions processing emotions without being given worksheets sometimes find CBT too rigid. That is a legitimate preference. It does not mean CBT is wrong for them, but it does mean it may not be the best fit.
Get the Full Details

If you are considering CBT, the most practical step is to find a licensed therapist who explicitly lists CBT as a primary modality and ask about their typical session structure and homework expectations. A good CBT therapist will give you a clear roadmap of what the process looks like, not vague promises about healing. You should also know that progress is not linear. Early sessions often feel tedious because you are learning a new skill set. The relief usually comes mid-treatment once the techniques start working on autopilot.
Getting Started With CBT
Finding a provider is the first hurdle. In most regions, you can search directories through professional organizations like the Association for Behavioral and Cognitive Therapies. Insurance plans often list covered providers, though coverage varies widely. Self-help resources exist but they are not a substitute for guided therapy when symptoms are moderate to severe. Books like David Burns' Feeling Good or the CBT workbook by Leahy are useful supplements, not standalone treatments for clinical conditions. Before your first session, write down the specific problems you want to address. CBT thrives on clear targets. Vague complaints like "I feel bad" are harder to work with than "I avoid social situations because I fear judgment" or "I wake up at 3am and cannot sleep because my mind races with worst-case scenarios." Concrete goals make the treatment measurable. Expect the therapist to ask questions that feel repetitive at first. That is normal. They are building a cognitive map of your patterns. The repetition is not inefficiency. It is calibration.