Understanding FiO2 on Mechanical Ventilation
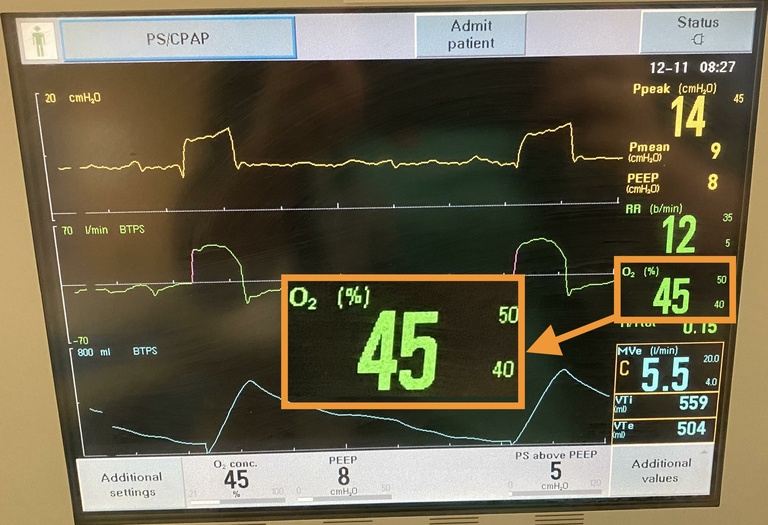
FiO2 is simply the fraction of inspired oxygen being delivered to the patient through the ventilator circuit. The range runs from 21 percent on room air up to 100 percent pure oxygen, though most clinicians rarely push beyond 60 percent for any sustained period. You set it at the ventilator panel, the machine mixes air and oxygen through an electronic blending valve, and the result travels through the tubing to the patient's airway. The setting matters because it directly controls arterial oxygenation alongside PEEP and recruitment strategies. A common mistake I see residents make is treating FiO2 as the only lever for hypoxemia. It isn't. When a patient's oxygenation drops, cranking FiO2 to 100 percent while ignoring the PEEP level or assessing whether there's significant shunt is one of those quick-and-dirty approaches that can cause more harm than good over the long run. Oxygen toxicity becomes a real concern above 50 to 60 percent FiO2 over extended periods. The lung absorbs reactive oxygen species at higher concentrations, leading to inflammation and potential ARDS exacerbation. This is why the ARDSNet protocol emphasizes keeping FiO2 below 60 percent whenever possible while adjusting PEEP to maintain acceptable saturation targets.
Here's a practical scenario I dealt with recently. A septic patient on volume control ventilation was saturating at 88 percent on FiO2 of 80 percent and PEEP of 12. The instinctive move would be to increase FiO2 further, but the patient was already near the ceiling. Instead, I increased PEEP to 14, added a 30-second recruitment maneuver, and rechecked the ABG. The PaO2 improved from 58 to 74 mmHg, allowing us to drop FiO2 back down to 60 percent within an hour. Increasing FiO2 past 80 percent at that point would have been the wrong answer, even though it might have briefly improved the number on the monitor. The blending accuracy of modern ventilators is generally reliable within plus or minus 3 percentage points, but older machines or those with damaged oxygen sensors can drift. I've seen cases where the display read 50 percent while the actual delivered FiO2 was closer to 38 percent because the pneumatic valve had degraded. An inline oxygen analyzer is the only way to verify what the patient is actually receiving, and they should be used whenever FiO2 settings are above 60 percent for more than a few hours. There are situations where high FiO2 is unavoidable. Cardiac arrest codes, severe pulmonary hemorrhage, or patients on extracorporeal membrane oxygenation often require 100 percent oxygen during critical phases. The rule about oxygen toxicity applies to sustained exposure, not brief rescue scenarios. But once you're past the emergency window, the goal should always be to titrate down to the lowest FiO2 that maintains target oxygenation — typically a SpO2 between 92 and 96 percent for most ICU patients, or a PaO2 in the 60 to 80 mmHg range.
One counter-intuitive point that beginners often miss: FiO2 and PEEP interact in a non-linear way. Doubling your FiO2 does not double your oxygenation. In a patient with significant intrapulmonary shunting, you might increase FiO2 from 40 percent to 100 percent and only see a 10 to 15 mmHg rise in PaO2, because blood flowing through collapsed alveoli never contacts the extra oxygen. That's where PEEP becomes the more effective intervention — by recruiting collapsed lung units, it increases the surface area available for gas exchange, which then allows FiO2 to do its job more efficiently. The other thing worth noting is that FiO2 calculations for things like the P/F ratio and the oxygenation index are straightforward, but they each have limitations. The P/F ratio collapses as a useful metric when FiO2 exceeds 60 percent because the relationship between alveolar and arterial oxygen tension becomes unpredictable with high inspired concentrations. In those cases, clinicians rely more on trend data and direct ABG values rather than trying to force the ratio into a severity classification. If you're learning to manage ventilators, spend time understanding how FiO2 fits into the bigger oxygenation equation before memorizing individual settings. The number itself is trivial. Recognizing when changing it will help versus when it won't is what separates competent practitioners from the rest.
Get the Full Details