Understanding Blood Pressure Readings
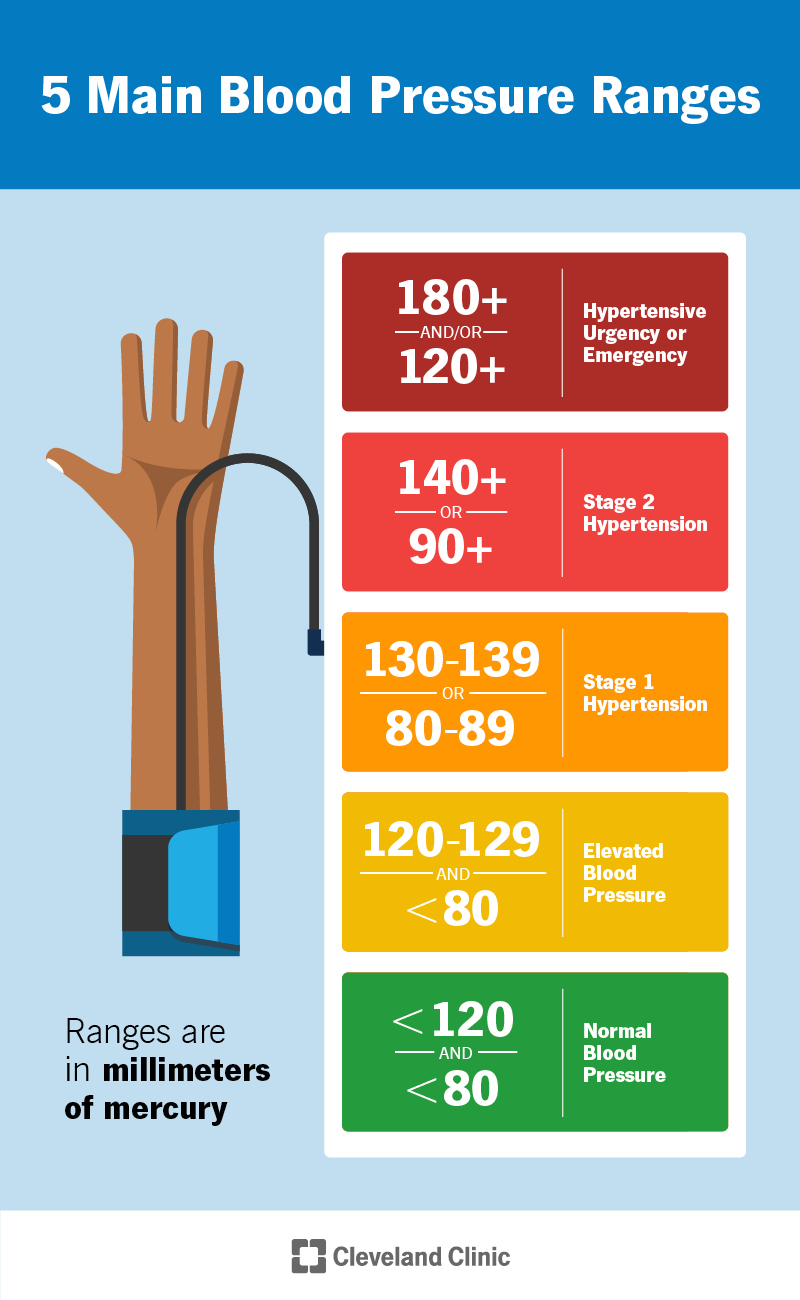
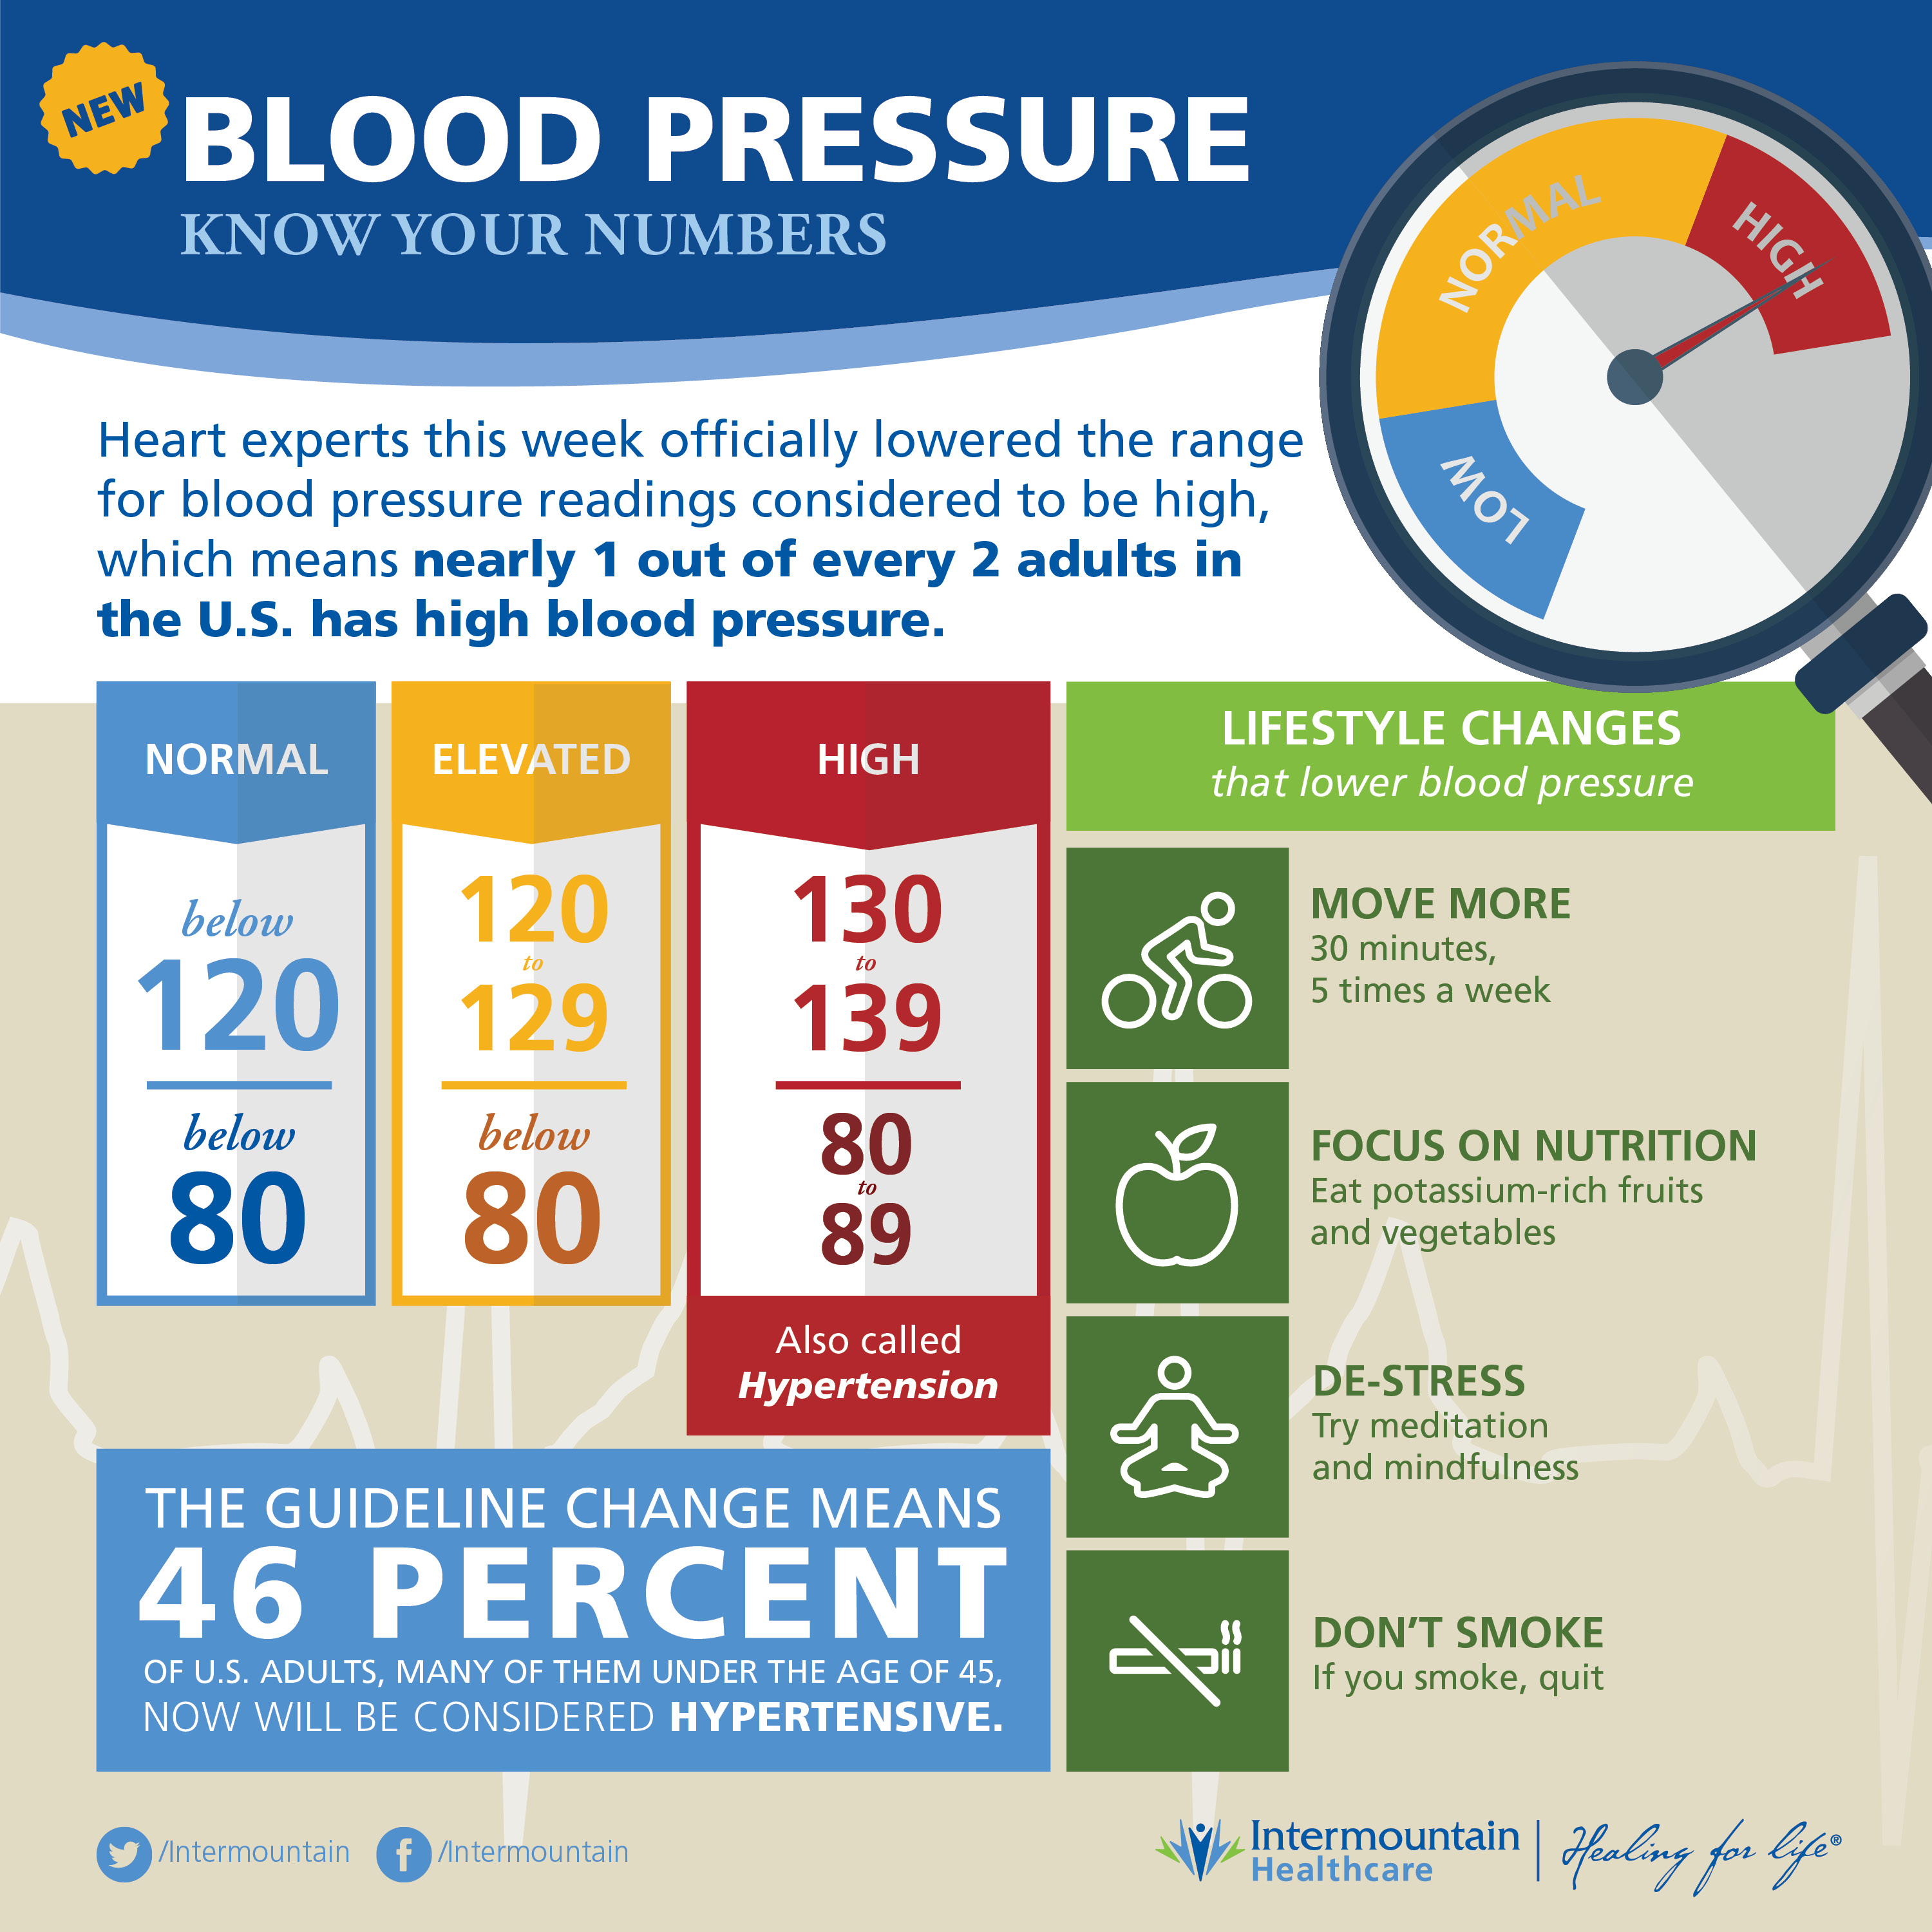
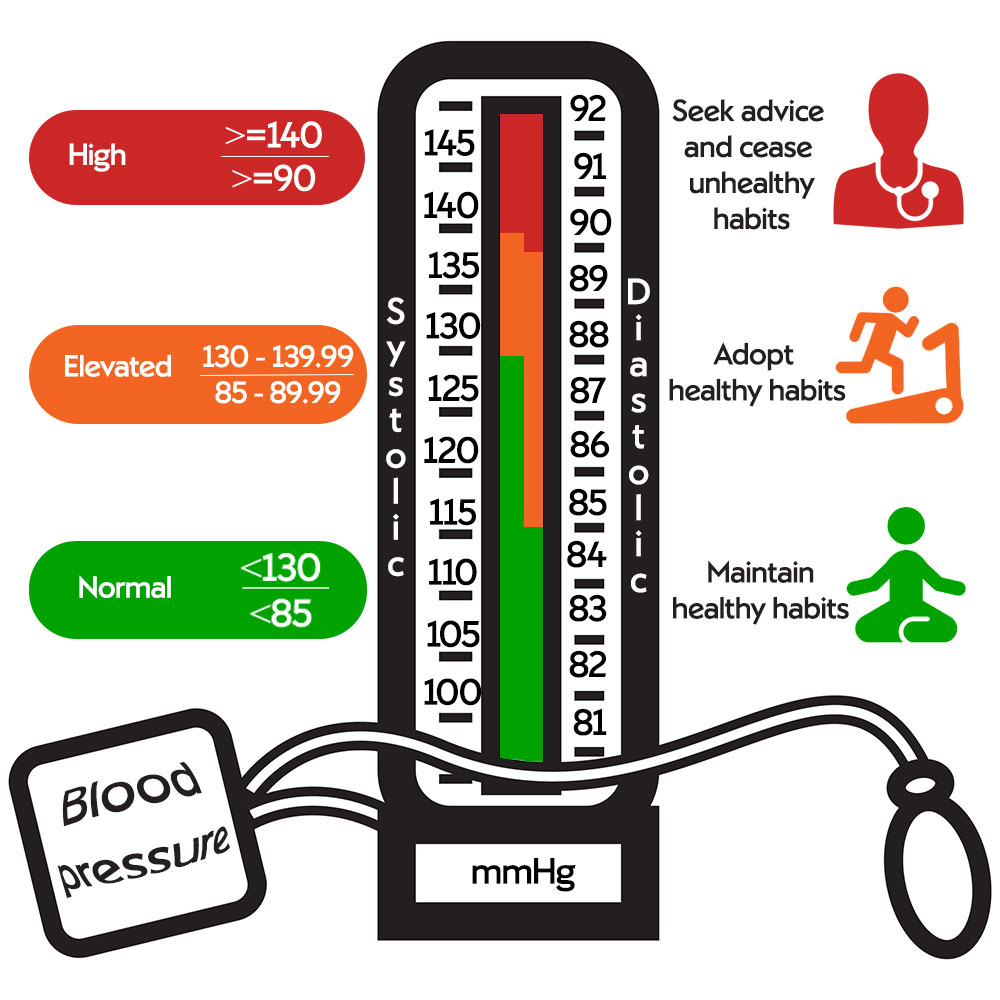
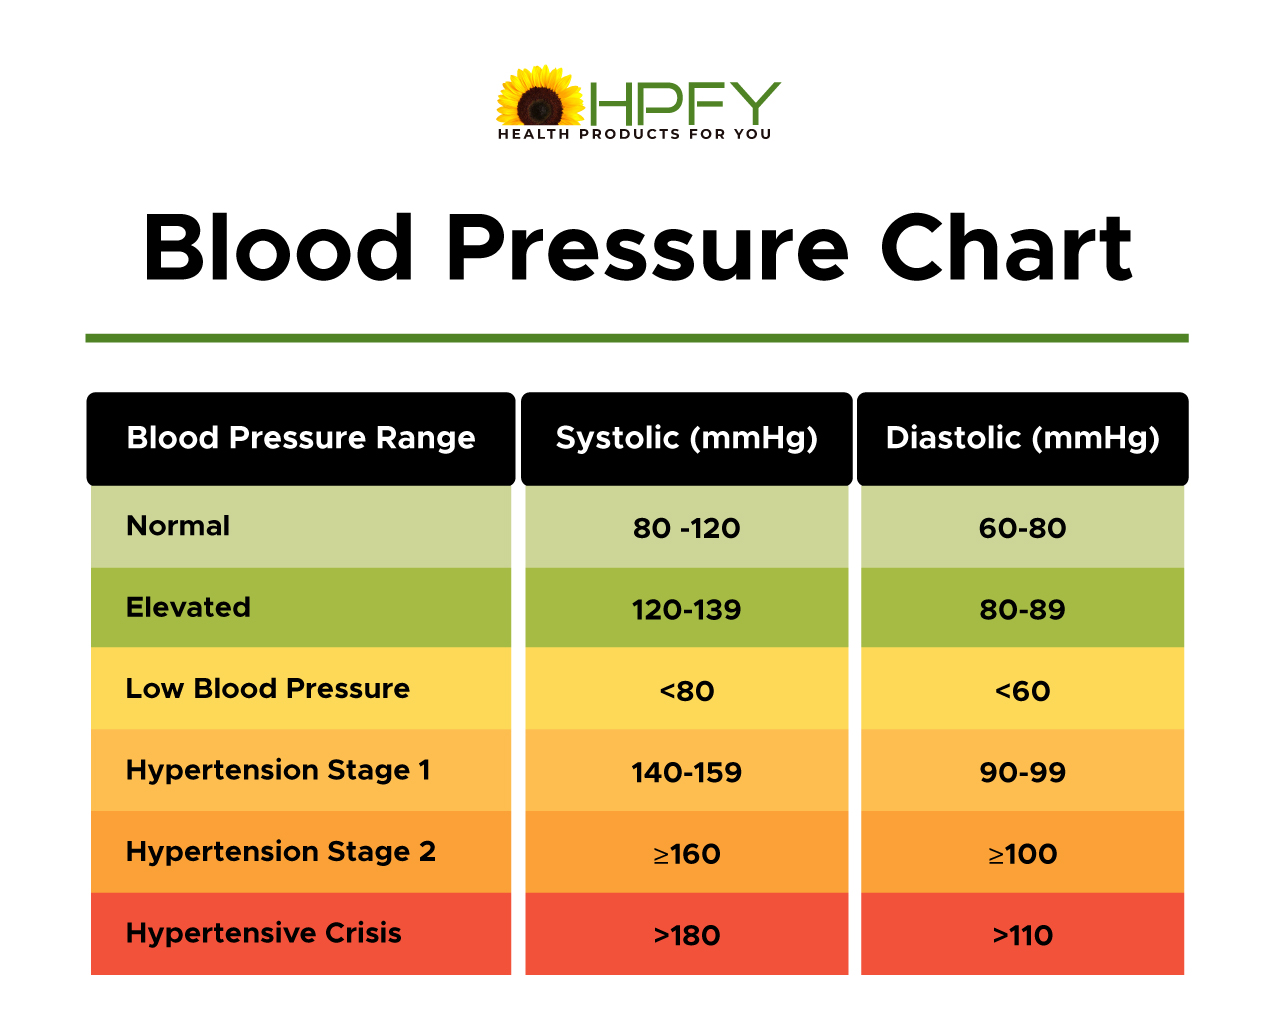
Most people stare at the two numbers on their home monitor and have no idea what they're actually looking at. The top number—systolic—measures the pressure in your arteries when your heart contracts. The bottom number—diastolic—measures the pressure when your heart rests between beats. That's the basic anatomy of it. Nothing dramatic, just physics inside your circulatory system.What Is Good Blood Pressure Numbers varies depending on who you ask and what guidelines they're following, but the general framework hasn't shifted much in the last decade. The American Heart Association and most clinical guidelines use these categories: Normal blood pressure sits below 120 over 80. That's the benchmark. Elevated is when systolic lands between 120 and 129 and diastolic stays below 80. Stage 1 hypertension kicks in at systolic 130–139 or diastolic 80–89. Stage 2 is systolic 140 or higher, or diastolic 90 or higher. Hypertensive crisis—that's the red alert territory—is anything above 180 systolic or 120 diastolic, and you should seek immediate medical attention if you see those numbers. But here's where the simple chart falls apart in practice. A single reading tells you almost nothing useful. I've seen patients panic over a 142 over 91 reading taken after rushing up three flights of stairs, carrying groceries, and checking their phone simultaneously. That number is noise. Blood pressure fluctuates constantly throughout the day. It's tied to stress, recent caffeine intake, bladder fullness, room temperature, even how you're positioned in the chair. The American College of Cardiology recommends taking multiple readings across different days before making any diagnosis, and many clinicians want to see at least a week of logged data.
How to Actually Get Reliable Readings
Here's what I learned from years of managing my own hypertension tracking that most people skip. Sit quietly for five minutes before you take a reading. Feet flat on the floor, back supported, arm resting at heart level. Don't talk during the measurement. Use a validated upper-arm cuff—wrist monitors and finger clips are convenient but frequently inaccurate, and the error margins can swing your reading by 10 to 20 millimeters of mercury, which is the difference between normal and hypertensive in borderline cases. I took readings twice daily for six months before my cardiologist felt comfortable adjusting my medication. Morning, before coffee or medication. Evening, before dinner. Same arm, same cuff, same chair. I logged every single one in a spreadsheet with notes about that day's stress level, sleep hours, and exercise. The pattern that emerged was completely different from what I assumed. My baseline was actually solid—averaging around 118 over 76—but I had consistent spikes in the late afternoon that correlated with work stress and skipped lunch. Fixing the lunch timing dropped my afternoon averages by roughly 8 points systolic without changing a single medication. One edge case worth mentioning: white coat syndrome and its reverse, masked hypertension. White coat hypertension happens when your numbers spike only in clinical settings due to anxiety. Masked hypertension is the opposite—you walk into the doctor's office calm and read fine, but your blood pressure runs high during your actual daily life. I discovered mine through home monitoring. My clinic readings consistently came back as prehypertensive, maybe 130 over 82. At home, averaged across weeks, they were closer to 138 over 90. That discrepancy mattered because it changed the treatment approach entirely. If I'd only gone by office visits, I might have been told to wait and watch. Instead, we addressed it proactively.
Common Mistakes People Make
The biggest error is treating one bad reading as a diagnosis. Your blood pressure is not a single number. It's a distribution. Look at the average over time, not the outliers. Another frequent mistake is using the wrong cuff size. An oversized or undersized cuff can throw off readings by significant amounts, and most people buy home monitors without checking whether the cuff matches their arm circumference. Measure your arm, check the manufacturer's size chart, and replace worn-out cuffs—elastic degrades over 12 to 18 months of regular use. There's also the problem of over-monitoring. I've seen people take readings every hour and spiral into anxiety, which ironically raises their blood pressure further. That creates a feedback loop that makes the data worse, not better. Twice a day, consistent schedule, is the sweet spot for most people. Unless your doctor has given you a different protocol.
Get the Full Details
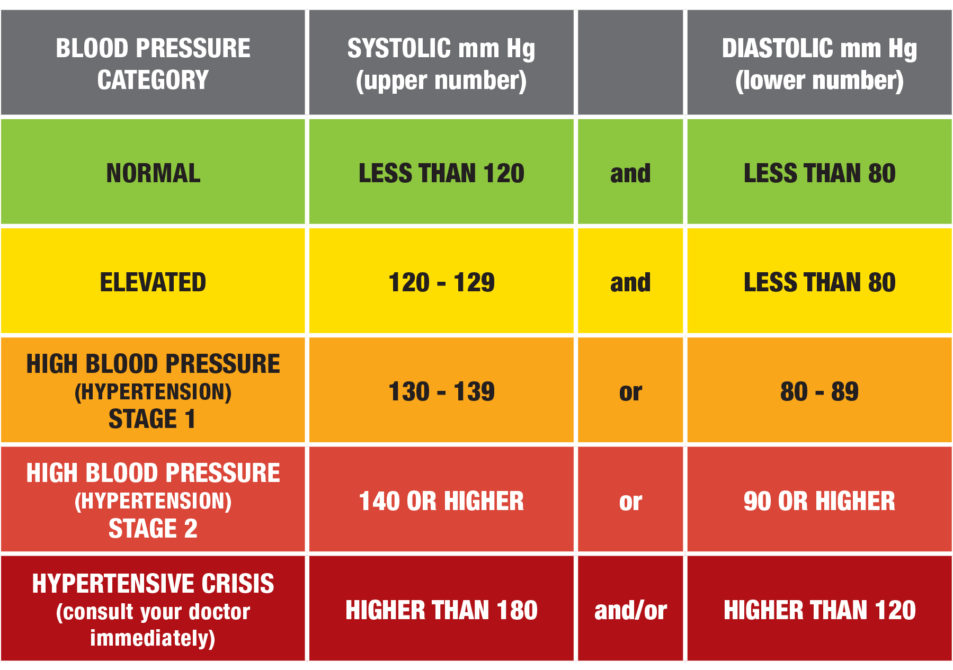
When Numbers Don't Tell the Whole Story
Normal range blood pressure doesn't automatically mean optimal cardiovascular health. Pulse pressure—the gap between systolic and diastolic—matters too. A pulse pressure above 60 can indicate arterial stiffness, which is a risk factor independent of the absolute numbers. A reading of 160 over 90 and a reading of 160 over 100 carry different implications even though the systolic is identical. The wider gap in the first reading suggests less compliant arteries. Another nuance that rarely gets discussed: orthostatic hypotension. Some people, particularly older adults or those on certain medications, experience significant blood pressure drops when standing up. I track this by taking a reading sitting down, then standing and rechecking at one minute and three minutes. A drop of 20 systolic or 10 diastolic within three minutes is clinically significant and changes how doctors approach treatment. Lowering blood pressure in someone with orthostatic issues can push them into dizziness and fall risk territory. It's a genuine tradeoff that generic guidelines don't capture. Home monitors also have a known limitation with irregular heart rhythms like atrial fibrillation. Many affordable monitors will give you a reading anyway, but the numbers are unreliable in those cases. My wife has AFib and her monitor flags irregular pulses, but the actual pressure values it displays can be off by enough to be misleading. She relies on periodic clinical measurements instead, and her cardiologist reviews her data with that caveat in mind.
The practical takeaway is straightforward. Get a validated upper-arm monitor, learn proper technique, track consistently over weeks not days, and bring your log to your doctor rather than a single scary number. Blood pressure management isn't about hitting perfection on one reading. It's about understanding your personal baseline and spotting real trends. Most people who do that correctly find that the average case is less alarming than the worst single reading makes it look.