Understanding the Tool Behind the Screenshots
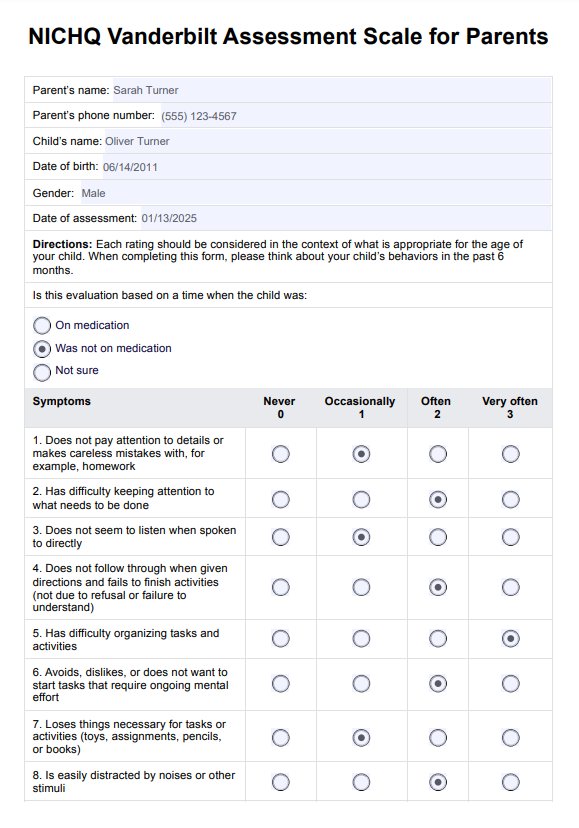
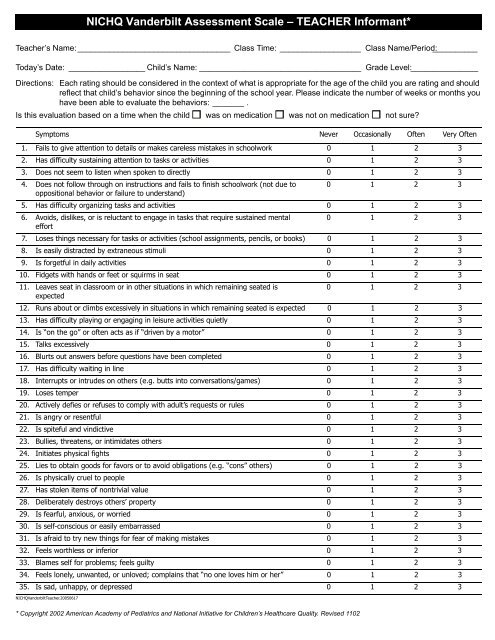
You've probably seen it floating around parenting forums and school counselor emails. A multi-page PDF with checkboxes and rating scales. People link it casually, then disappear into the comments. I spent a few years working closely with pediatric behavioral health teams who relied on this instrument daily, so I know where the friction points are and where it actually holds up. The core idea is straightforward. It's a rating scale designed to capture ADHD symptomatology across home and school settings, while also screening for common co-occurring conditions like oppositional defiant disorder, anxiety, and depression. Parents fill out one section, teachers fill out another, and a separate performance piece measures academic output speed and accuracy. That last part is what most people skip, which is exactly why their picture of the child is incomplete.
What Is Nichq Vanderbilt Assessment Scale
It is a free, publicly available symptom assessment tool developed originally by Dr. James Swanson and colleagues at the University of California, Irvine, and later adopted and distributed by the NICHQ (the former Centers for Child Health and Behavior Transformation, known in the field simply as NICHQ). It translates DSM symptom criteria into parent and teacher report forms that clinicians use as part of a broader diagnostic evaluation, not as a standalone diagnostic instrument. There is no paywall. You can find the current forms on the NICHQ website or through major pediatric organizations. Print them or fill them digitally. Both work fine. I typically hand parents the blank version before the intake visit so they have a day or two to reflect on behaviors across different contexts.
How It Actually Works in Practice
Each version covers the nine DSM criteria for inattention and the nine for hyperactivity-impulsivity. The parent form and teacher form both ask you to rate frequency on a zero to two scale: never, sometimes, often. Items map directly onto the DSM list. A score of two on a criterion counts as present. If at least six of the nine symptoms in either domain hit that threshold, plus evidence that those symptoms cause impairment in at least two settings, you cross the clinical cutoff. Then there is the functional impairment section. This is where the scale diverges from a simple checklist. It asks about grade retention, classroom behavior problems, difficulty with peers, and overall functioning. Those functional ratings matter because DSM requires evidence of cross-setting impairment for a diagnosis. The scale surfaces that data without requiring a separate interview. The academic performance portion is a timed reading and math task. The child reads a passage aloud while the examiner marks miscues, then completes a short arithmetic sheet. This is not a cognitive test. It is a performance screener. It catches kids who are masking in conversation but falling apart on timed academic tasks. I once sat through an intake where the parent and teacher reports looked borderline, almost normal. The academic sheet revealed the child was performing nearly two grade levels below placement. That changed the entire conversation.
Get the Full Details

A Real Problem I Faced and How I Handled It
Years ago I was working with a school district that had adopted the scale across multiple sites. One site started returning forms where parents were consistently selecting the middle rating, sometimes, for nearly every item. The data looked deceptively clean. No flagging. No clinical cutoffs hit. But when I dug in, the kids in question were clearly struggling. The problem was response bias, specifically a mild acquiescence pattern where parents defaulted to the middle option to avoid conflict or because they were unsure what often meant for their specific child. The workaround was not to discard the forms. I added a brief rater instruction at the top of the parent section before distribution, explicitly defining the scale anchors. Never means not at home or school during the past six months. Sometimes means less than half the time. Often means more than half the time. That simple clarification shifted the data quality noticeably. We saw a drop in middle-weighted responses and a corresponding rise in clinically meaningful flags at the next cycle. It is a small change, but it is the kind of thing that gets overlooked until your caseload starts looking artificially empty.
What Beginners Miss
Most people treat the Vanderbilt as a diagnostic shortcut. It is not. It is a screening and monitoring tool that must be embedded in a comprehensive evaluation. That includes clinical interview, developmental history, ruling out medical causes, and collateral information from multiple sources. A high score on the scale does not equal an ADHD diagnosis. A low score does not rule it out either. Sensitivity and specificity hover around the eighties, which is decent but far from perfect. Another thing that trips people up is the dual-rating design. You need both parent and teacher forms for anything reliable. I have seen clinicians accept a single form and draw conclusions that the data does not support. Cross-setting impairment is a diagnostic requirement, not a suggestion. If you only have one rater, you are missing half the picture. Co-occurring condition screening is built into the scale through supplemental items, but the thresholds there are not validated for independent diagnosis. They signal. They do not confirm. If the oppositional or anxiety subscales light up, follow up with a structured interview or a dedicated instrument like the Conners or the SCARED, not a referral based on a checkbox cluster.
The Practical Limitations
The scale assumes a certain level of rater literacy. Parents who are English language learners, or who have low literacy, will produce noisy data on this form. I have seen entire sections become unreliable because the respondent was translating the concepts mid-item. In those cases, a brief walkthrough of the rating anchors before distribution, or switching to an interviewer-administered version, makes a real difference. Age range is another boundary. The standard forms target children roughly between six and twelve. Adolescents require modified forms, and even then the psychometric properties shift. Older kids may underreport symptoms due to internalization, which shows up as flat parent scores with severe teacher scores. That mismatch is clinically informative, but it breaks the simple cutoff logic. The academic performance subtest is easy to mishandle. If you do not standardize the timing or the instructions, the scores become arbitrary. Different examiners will produce different outputs if they rush the reading portion or allow variations in how the math sheet is presented. I enforce a strict script and stop the timer at the exact signal, no exceptions, because even a fifteen second advantage or disadvantage skews the interpretation.

Where It Falls Apart Entirely
Do not use this scale alone to make eligibility decisions for individualized education programs. It was never designed for that. IEP teams need psychoeducational evaluations, cognitive testing, and academic achievement data. The Vanderbilt can supplement that process, but it cannot replace any of it. I watched a district try to use aggregated Vanderbilt scores to justify program placement across a building, and the state auditor flagged it within a quarter. The legal and clinical basis was thin. It also has limited utility in adult populations. The forms are normed for children and adolescents. Adults with ADHD require adult-specific instruments like the ASRS v1.1 or the Wender Utah Rating Scale. Using the Vanderbilt with an adult is a guess, not a practice.
Alternatives Worth Knowing
If you need something with broader age coverage, the Conners 3 spans ages six through sixty-five and includes more extensive normative data. It costs money and requires training, but the depth is different. For a free tool aimed at older teens, the free adult ADHD self-report scale from WHO is a better fit. For pure efficiency in a busy pediatric clinic, the Vanderbilt remains hard to beat because it covers symptoms, impairment, and a quick academic check in a single packet. When I need rapid monitoring of treatment response over a semester, I stick with the Vanderbilt. The forms are short enough that compliance stays high, and the dual-rater design keeps me honest about whether changes are visible across environments. That reliability matters more than any fancy metric on paper.