Understanding Blood Pressure Readings in Practice
Most people get confused when they first start checking their numbers at home. The readings jump around, the machines beep at you, and suddenly you're Googling at 11pm wondering if 138 over 88 means you're going to drop dead. It's less dramatic than the internet makes it seem, but there are details that matter. The standard answer you'll find everywhere is that normal blood pressure sits below 120 over 80 millimeters of mercury. That's the baseline, the target, the number your doctor probably mentioned once during a six-minute visit. But reading between the lines of actual clinical practice, normal isn't a single point. It's a range that shifts depending on age, context, and how the measurement was taken.What Is Normal Blood Ressure and Why It Matters More Than You Think
Systolic pressure measures the force when your heart contracts and pushes blood out. Diastolic pressure measures what's left in your arteries while your heart rests between beats. Both numbers tell different stories, and neither one should be ignored.
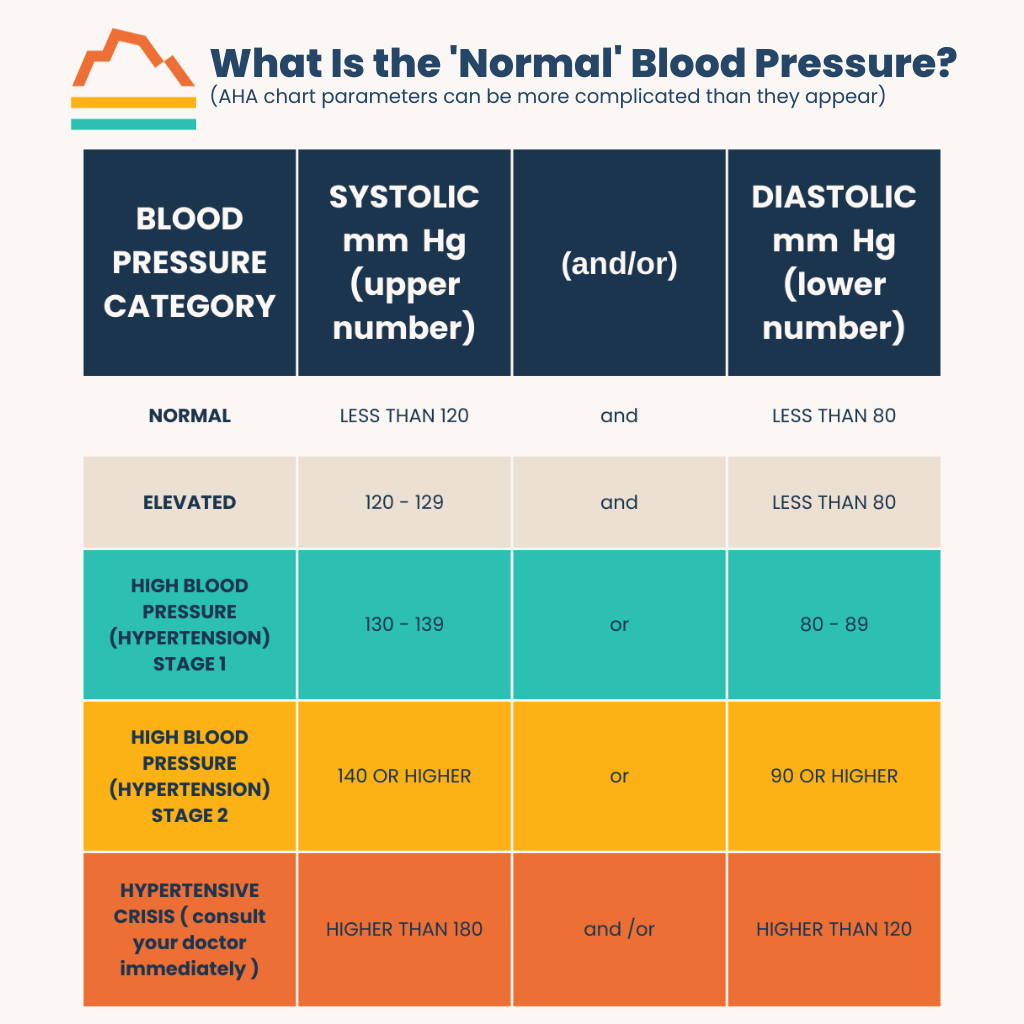
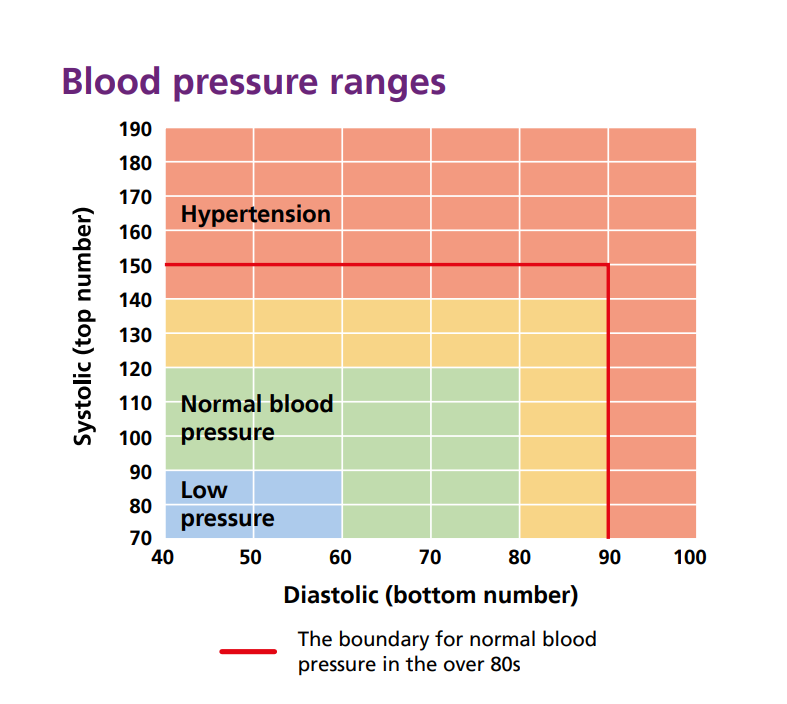
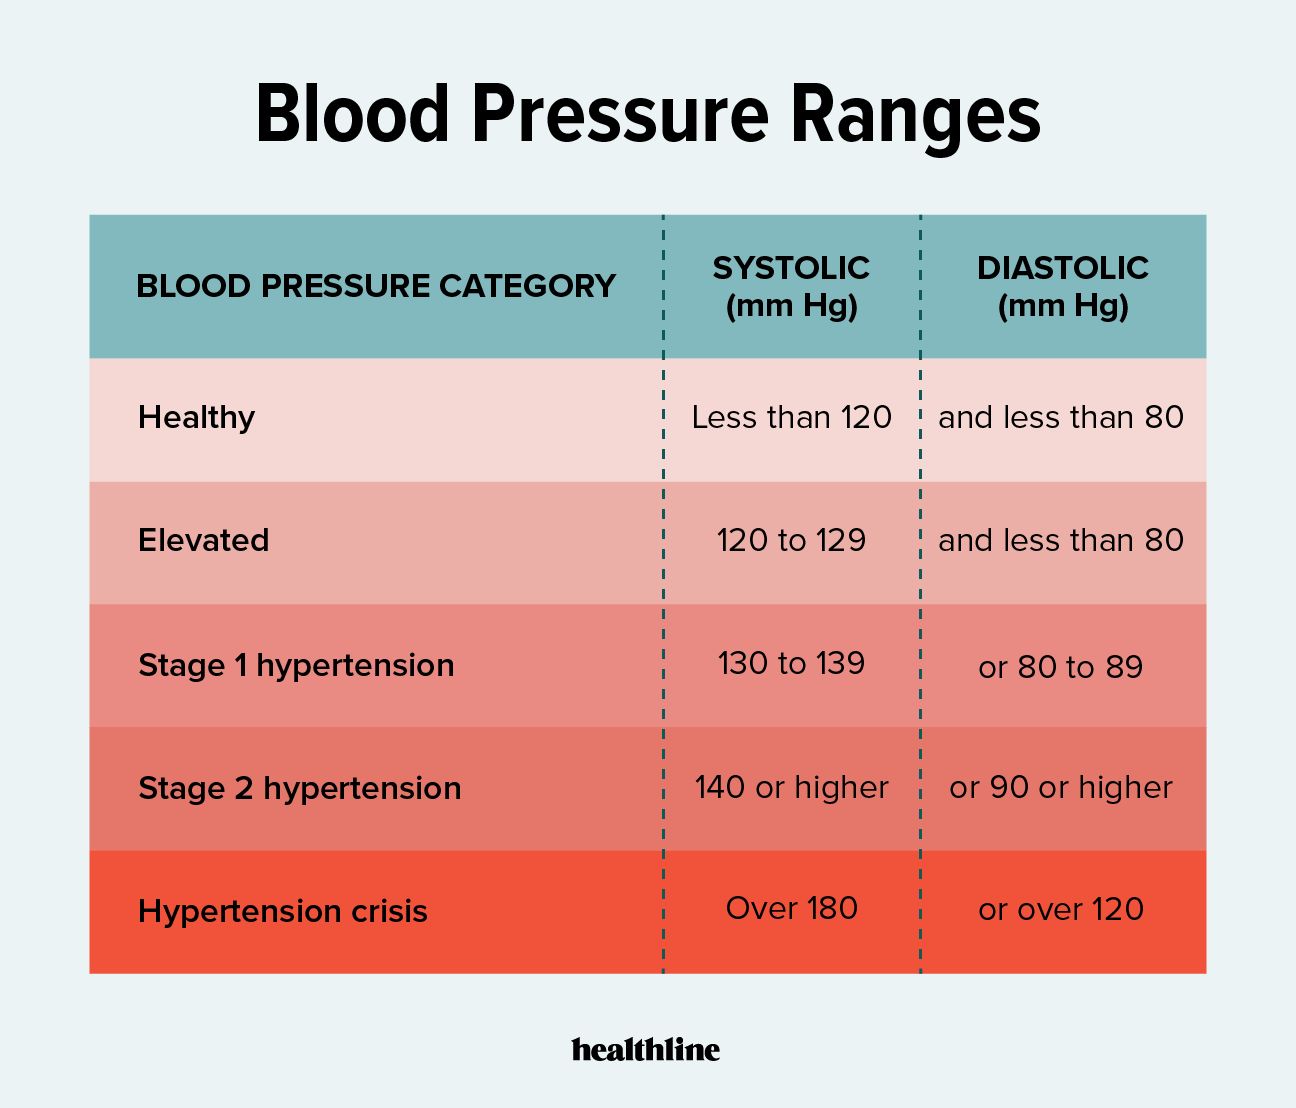
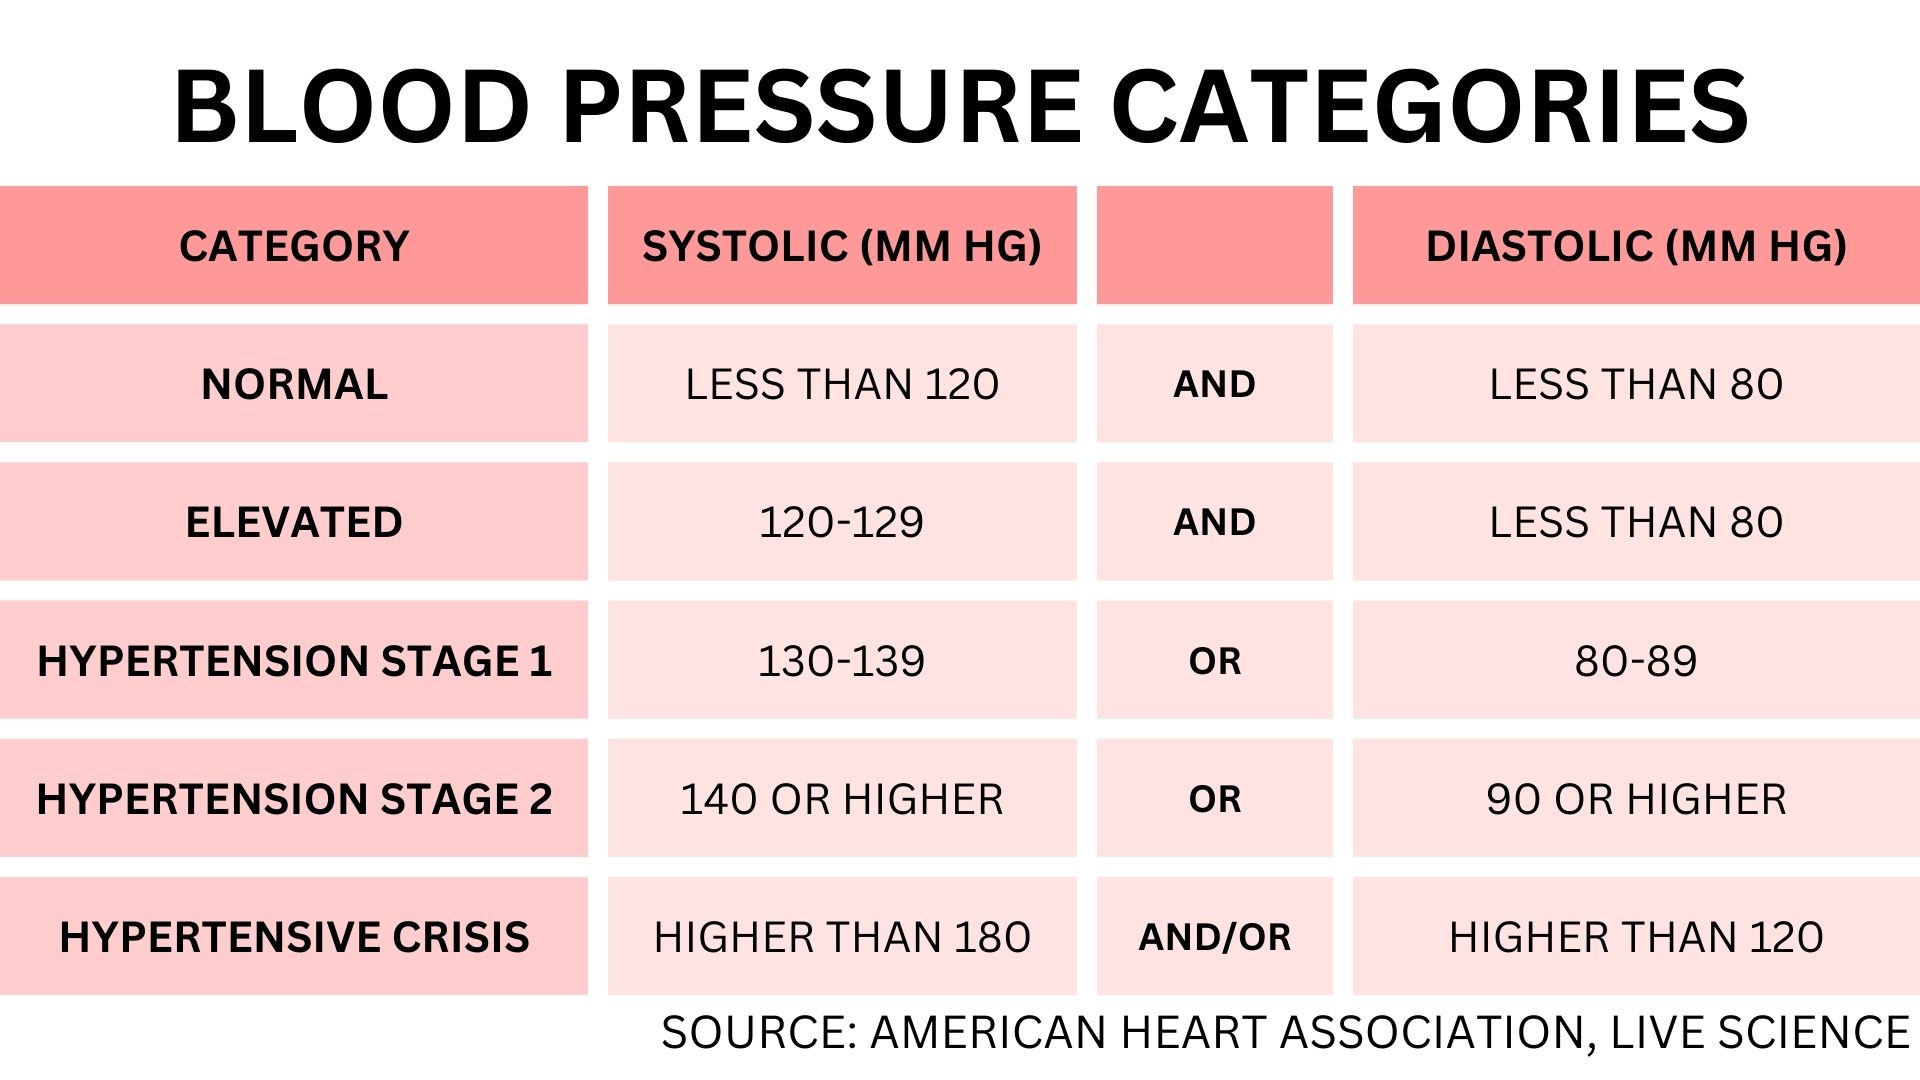
Here's what most consumer guides leave out: a single reading means almost nothing on its own. I spent years watching people obsess over one bad measurement and then completely ignore consistent trends. The real signal comes from averaging multiple readings taken under consistent conditions. The method that actually works is straightforward but people skip steps. Sit quietly for five minutes before measuring. No phone scrolling, no talking, feet flat on the floor, arm supported at heart level. Take two readings a minute apart and average them. Do this morning and evening for a full week. Discard day one if it looks wildly off — that's usually just the "white coat effect" bleeding into your home readings. I learned this the hard way back in 2014. A patient came in with home readings consistently showing 145 over 92. Prescribed medication immediately, standard protocol. Three weeks later they came back and the numbers were fine — 122 over 76. Turns out they were taking the readings right after walking up two flights of stairs from their parking garage, still holding their breath slightly, phone in the other hand checking email. Their resting blood pressure was normal. The problem wasn't hypertension, it was technique. We adjusted the measurement protocol and never touched medication. Saved them three years of side effects and a thousand dollars in co-pays. The edge case nobody warns you about is isolated systolic hypertension. This shows up most often in people over sixty. Your top number runs high, maybe 150 or 160, but the bottom number stays normal, maybe 78 or 82. The arteries stiffen with age and the systolic reading climbs while diastolic holds steady or even drops. This is clinically significant and absolutely requires attention, but it's easy to dismiss because "the bottom number is fine." It's not fine to ignore. Another counter-intuitive thing: orthostatic hypotension. Some people have normal blood pressure sitting down but their numbers crash when they stand up. If you're experiencing dizziness on standing, that's worth tracking separately. Take a reading while seated, then immediately after standing, and again after one and three minutes standing. A drop of 20 points systolic or 10 points diastolic within three minutes of standing is the clinical threshold. This changes the entire management approach. Blood pressure categories as defined by the American Heart Association and ACC: Normal: below 120 over 80 Elevated: systolic 120-129 and diastolic below 80 Stage 1 hypertension: systolic 130-139 or diastolic 80-89 Stage 2 hypertension: systolic 140 or higher or diastolic 90 or higher Hypertensive crisis: systolic over 180 and/or diastolic over 120 Those categories exist on paper. In practice, treatment decisions don't follow them rigidly. A healthy 72-year-old with stage 1 hypertension might get monitored for months before any medication is considered. A 45-year-old with the same numbers and a history of kidney disease might start ACE inhibitors the same week. The numbers are a starting point, not a verdict. The biggest limitation of home monitoring is device quality. Cheap wrist monitors are unreliable. Cuff-based upper arm monitors are significantly more accurate, but even those vary between brands. I recommend looking for devices validated by the Stride BGDP program or the British Hypertension Society. The validation list is publicly available and takes about two minutes to check. An unvalidated monitor can be off by 10 to 15 points, which is the difference between "lifestyle changes" and "start medication." Cuff size matters more than people realize. Using a standard cuff on a larger arm can add 5 to 10 points to your reading. Using a small cuff on a thin arm can do the same in reverse. Measure your arm circumference at the midpoint between shoulder and elbow. If it's over 33 centimeters, you likely need a large cuff. This is something I see misconfigured constantly in clinical settings, not just at home. If your numbers consistently run above 130 over 80, the first intervention is almost always lifestyle. Sodium reduction, aerobic exercise, weight management, limiting alcohol. These interventions typically lower systolic pressure by 5 to 11 points depending on baseline. That's not trivial. For someone sitting at 148 over 92, that kind of reduction could keep them off medication entirely. When lifestyle changes aren't enough, medications work well for most people. Thiazide diuretics, ACE inhibitors, ARBs, calcium channel blockers — each has a different mechanism and different side effect profile. The first-line choice depends on comorbidities, race, age, and kidney function. There's no universal best option. If your readings hit 180 over 120, that's a hypertensive crisis and you should seek emergency care immediately, especially if you have symptoms like chest pain, shortness of breath, back pain, numbness, weakness, change in vision, or difficulty speaking. Without those symptoms, wait five minutes and recheck. If it's still that high, contact a healthcare provider the same day. The numbers are useful, but they're only one piece of the picture. Context matters. Consistency matters more than perfection. And the person interpreting them should be looking at trends, not isolated data points.