What Actually Makes Drug Delivery Systems "Novel"
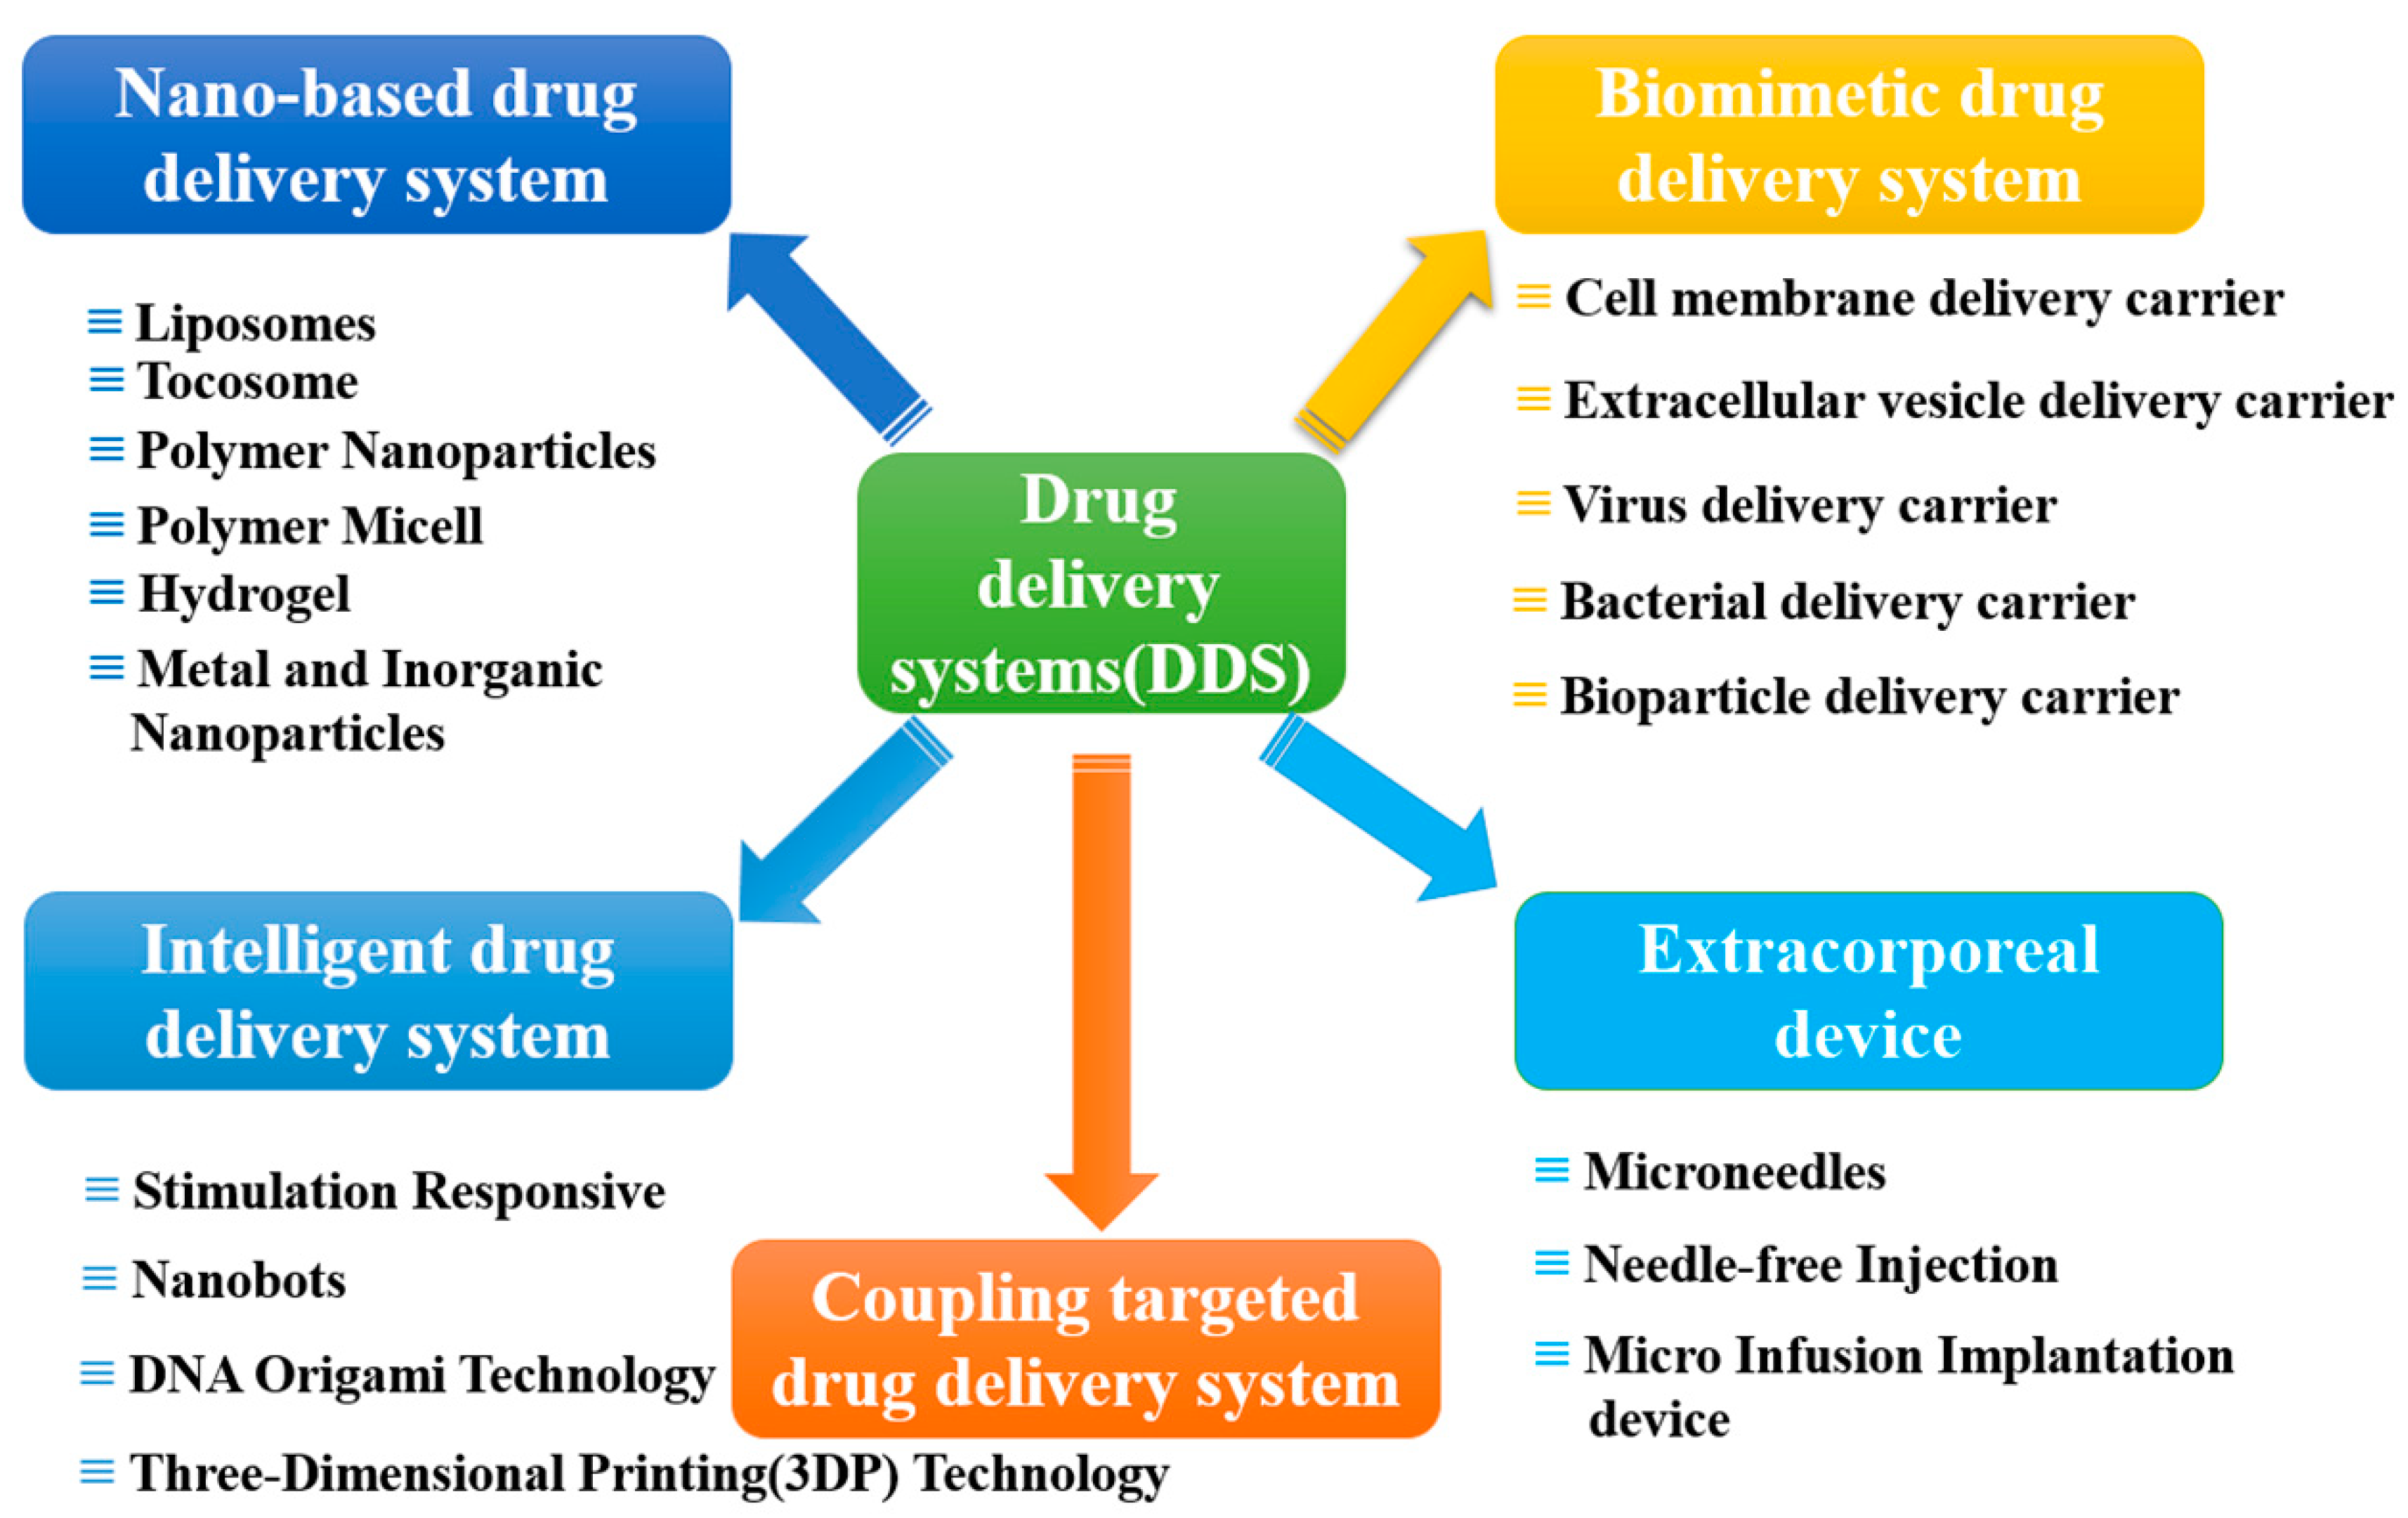
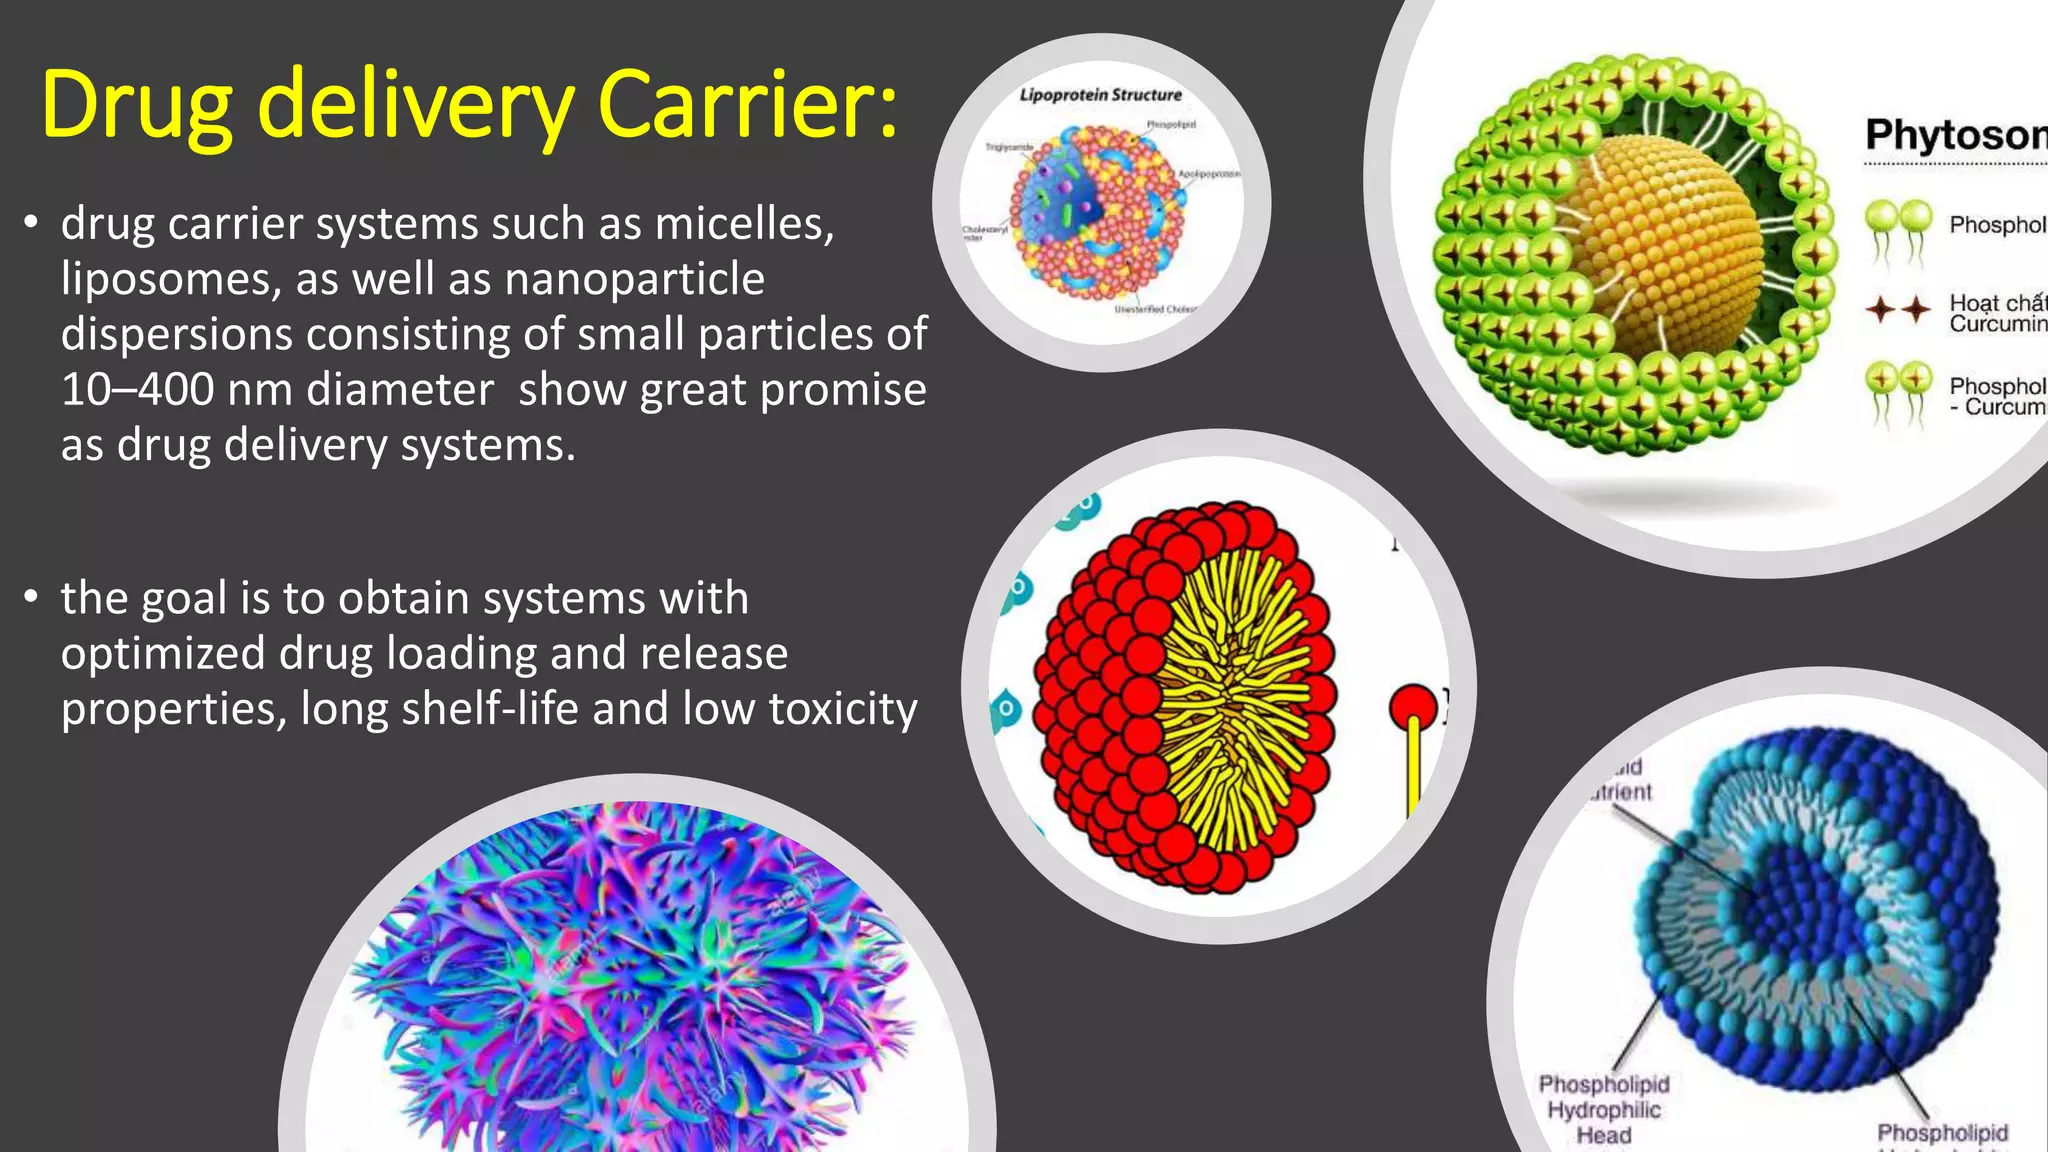
A novel drug delivery system is any approach that changes how a drug gets into the body, where it goes once it's there, or how long it stays active. This isn't about discovering a new molecule. It's about rebuilding the delivery mechanism around an existing one. Oral bioavailability of a compound is nearly zero because it degrades in stomach acid? That's a formulation problem. The drug works but only causes liver toxicity at therapeutic doses? Again, formulation. These systems have been evolving steadily for decades, but the real shift happened when people stopped treating the carrier as an afterthought and started designing it with the same rigor as the active ingredient itself. The term gets thrown around loosely in grant proposals and investor decks, but in practice it refers to platforms like liposomes, polymeric nanoparticles, micelles, dendrimers, solid lipid nanoparticles, and targeted conjugates. The underlying principle is usually one of three things: improved solubility for poorly water-soluble drugs, targeted accumulation at a specific tissue or cell type, or controlled release over an extended timeframe. Sometimes all three simultaneously. I spent about four years working on PEGylated liposomal formulations for oncology applications. The basic chemistry is straightforward — phospholipids self-assemble into bilayers in aqueous solution, you encapsulate the drug in the aqueous core or intercalate it in the lipid bilayer depending on whether it's hydrophilic or hydrophobic, then size-reduce it through extrusion or homogenization. What the textbooks don't tell you is how much the process parameters matter. A 10-degree Celsius difference in temperature during the thin-lipid hydration step can shift your encapsulation efficiency from 85 percent down to 40 percent. Not a rounding error. That's the difference between a viable batch and a failed one.
The counter-intuitive part that people miss is that smaller isn't always better for targeting. There's a real trade-off. Liposomes under about 50 nanometers get rapidly cleared by renal filtration before they can accumulate in tumor tissue through the EPR effect. The sweet spot for most passive targeting applications sits around 100 to 150 nanometers. But here's the thing nobody puts in introductory material — the surface charge matters just as much as size. Slightly negative or near-neutral zeta potential prevents opsonization and extends circulation time. Positive surfaces get cleared within minutes by the reticuloendothelial system. I once ran a side-by-side stability study where two batches with identical size distributions but zeta potentials of minus 8 millivolts and plus 5 millivolts had completely different pharmacokinetic profiles in vivo. The positive one was essentially gone before it reached the target tissue. Another edge case that caught me off guard early on involved drug leakage during lyophilization. We were working with a hydrophilic anticancer agent encased in DSPC-based liposomes. The formulation looked perfect in liquid form — uniform size, high encapsulation, stable for months at 4 degrees Celsius. Then we tried to lyophilize it for long-term storage because the sponsor wanted a dry powder reconstitutable at the point of use. The first three attempts resulted in greater than 60 percent drug loss. The problem wasn't the freezing step. It was the phase transition of the lipid bilayer during ice sublimation. When the temperature drops below the gel-to-liquid crystalline phase transition temperature of the lipid, the bilayer becomes rigid and fractures under osmotic stress from the expanding ice crystals. Our workaround was adding 8 percent w/v sucrose as a cryoprotectant and controlling the annealing step to grow larger ice crystals that cause less mechanical damage. That dropped the leakage to under 8 percent. The sucrose replaces water molecules at the lipid headgroup region and maintains bilayer integrity during the drying process. It's a well-documented phenomenon but the practical execution is finicky. Here's where the field gets messy. Novel drug delivery sounds impressive until you hit regulatory questions. The FDA and EMA now expect extensive characterization data for any novel delivery system — particle size distribution by multiple methods, polydispersity index, zeta potential, residual solvent analysis, endotoxin levels, sterility validation, and stability data under ICH conditions. A typical lipid nanoparticle product goes through at least three rounds of analytical method validation before you can even file an IND. The characterization alone can consume six to nine months of a project timeline. Most startups underestimate this by a factor of three.
Scale-up is another area where academic prototypes fall apart. You can make 50 milliliters of uniform liposomes in a university lab with a bath sonicator and a hand-extruder. Making 500 liters that meets the same specifications requires high-pressure homogenizers, closed-system hydration loops, and in-line sizing and temperature monitoring. The economics change drastically. A formulation that costs $200 per gram at lab scale might cost $2,000 per gram at pilot scale if you're not careful about yield losses during filtration and concentration steps. I've seen projects die because the CMO quoted a manufacturing cost that made the commercial pricing impossible. There are also genuine limitations to these systems. Liposomal drugs don't solve every pharmacokinetic problem. If a molecule has poor membrane permeability regardless of carrier, encapsulation won't fix that. Polymeric nanoparticles can trigger complement activation-related pseudoallergy in some patients, which is why you need thorough safety pharmacology early in development. And the targeted delivery promise — ligand-conjugated particles seeking out specific receptors — still underperforms in clinical settings compared to preclinical models. Tumor heterogeneity means not all cells express the target receptor, and the increased interstitial pressure in solid tumors actually impedes deep particle penetration. You get accumulation at the periphery but not throughout the mass. For applications where conventional extended-release formulations already work well — say, a drug with a 12-hour half-life that patients tolerate orally — novel delivery systems add cost and complexity without proportional benefit. The regulatory burden alone can add years to development. I'd recommend considering them primarily when you have a genuine solubility bottleneck, a narrow therapeutic window that demands precise release control, or a molecule that would otherwise be unusable due to first-pass metabolism. Otherwise you're solving a problem that doesn't exist and spending money to do it.
Get the Full Details

The technology itself is sound and continues to advance. RNA interference therapeutics wouldn't exist without lipid nanoparticle delivery. Doxorubicin liposomes reduced cardiotoxicity significantly compared to the free drug. Newer approaches like extracellular vesicle mimetics and peptide-based delivery vectors are showing promising selectivity. But the day-to-day reality of working with these systems is mostly quality control, analytical characterization, and debugging manufacturing processes. The glamour fades quickly once you're troubleshooting batch-to-batch variability in encapsulation efficiency at 2 AM.