Understanding Novel Drug Delivery Systems in Practice
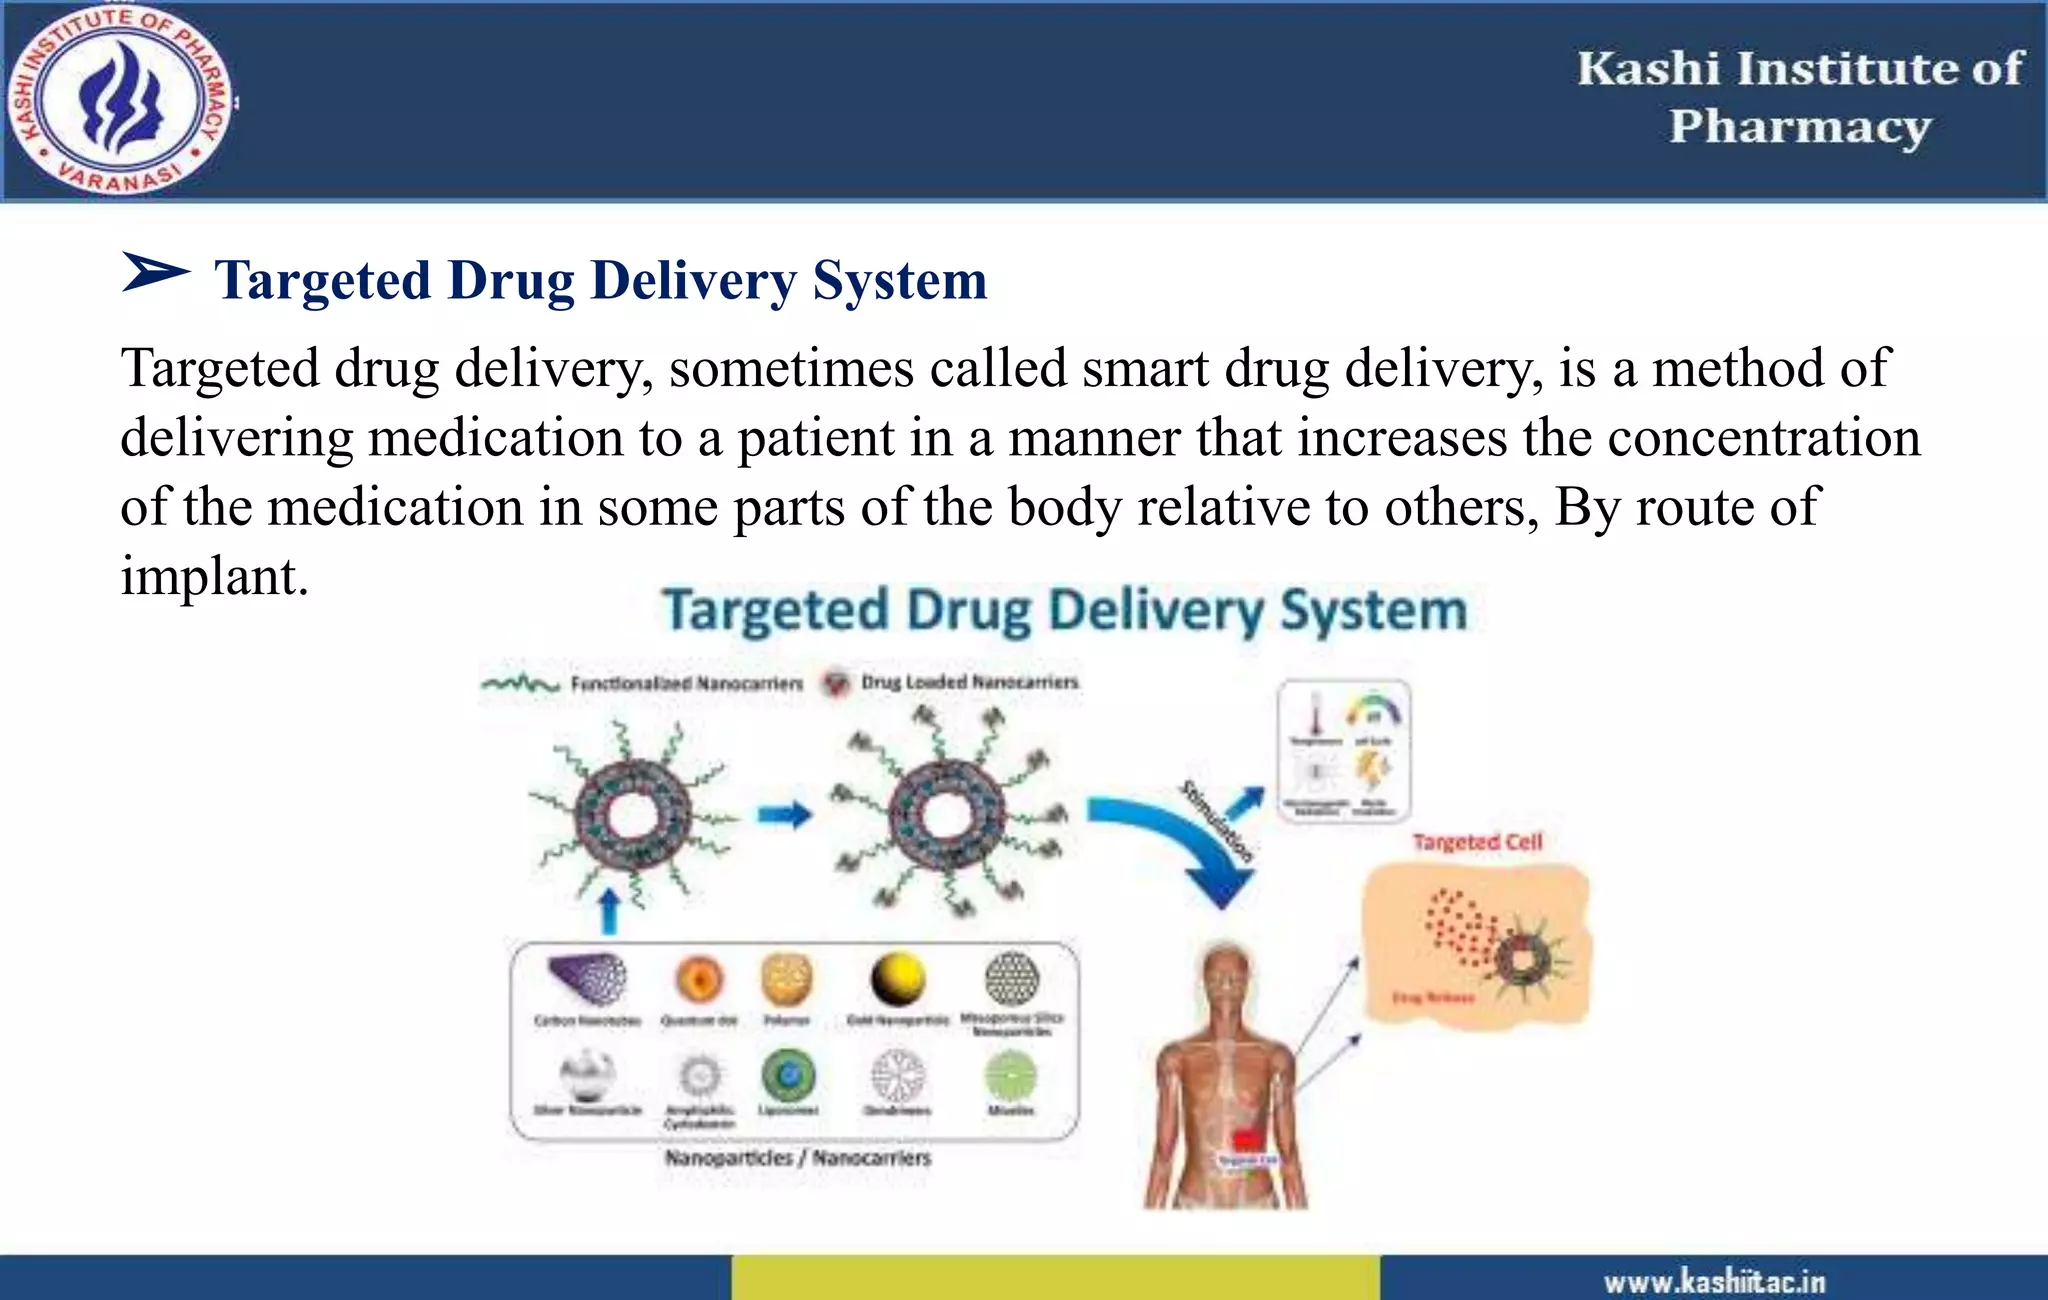
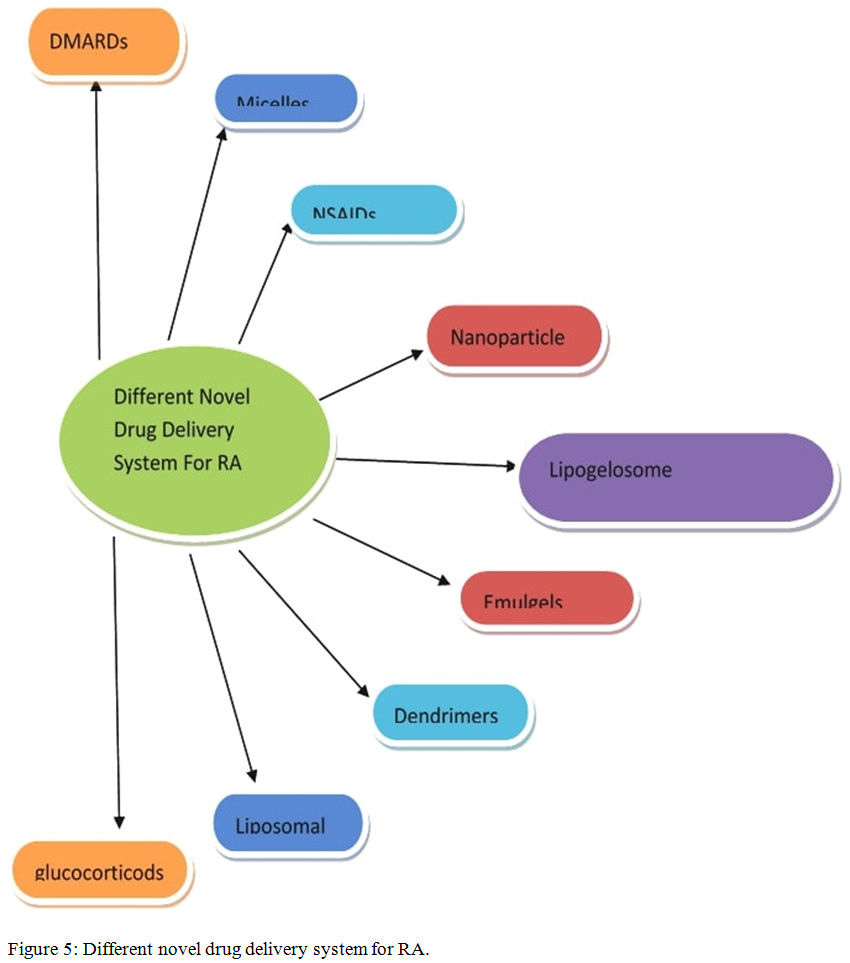
Most conventional oral drugs spend more time circulating everywhere than hitting their target. A standard immediate-release tablet dissolves quickly in the gut, enters systemic circulation, and then gets distributed throughout the body. That is fine for something like ibuprofen. It fails miserably for chemotherapy agents, biologics, and drugs with poor aqueous solubility. This is the problem novel drug delivery systems address. The term covers engineered platforms designed to control where, when, and how fast a drug is released. A novel drug delivery system is any non-traditional method of getting a drug into the body. Liposomes encapsulate a drug inside a spherical lipid bilayer. Polymeric nanoparticles carry medication within a solid matrix made from materials like PLGA or chitosan. Hydrogels are cross-linked polymer networks that absorb large amounts of water and can release drug over extended periods. Transdermal patches bypass first-pass metabolism entirely. Each platform serves a different purpose. Some improve solubility. Some extend half-life. Some target specific tissues. None of them are universally better. They are tool-specific. I spent several years working on liposomal formulations for oncology compounds, so I speak from experience when I say the theory looks clean on paper and falls apart during scale-up. A typical lab batch of 50 milliliters might show excellent encapsulation efficiency and uniform particle size. Manufacturing the same formulation at 10 liters revealed that the extrusion process created batch-to-batch variation in particle distribution. We had to adjust the pressure cycling parameters and add a secondary filtration step. The encapsulation efficiency dropped from 92 percent to about 78 percent. You learn quickly that what works in a beaker does not automatically work in a bioreactor.
How These Systems Actually Work
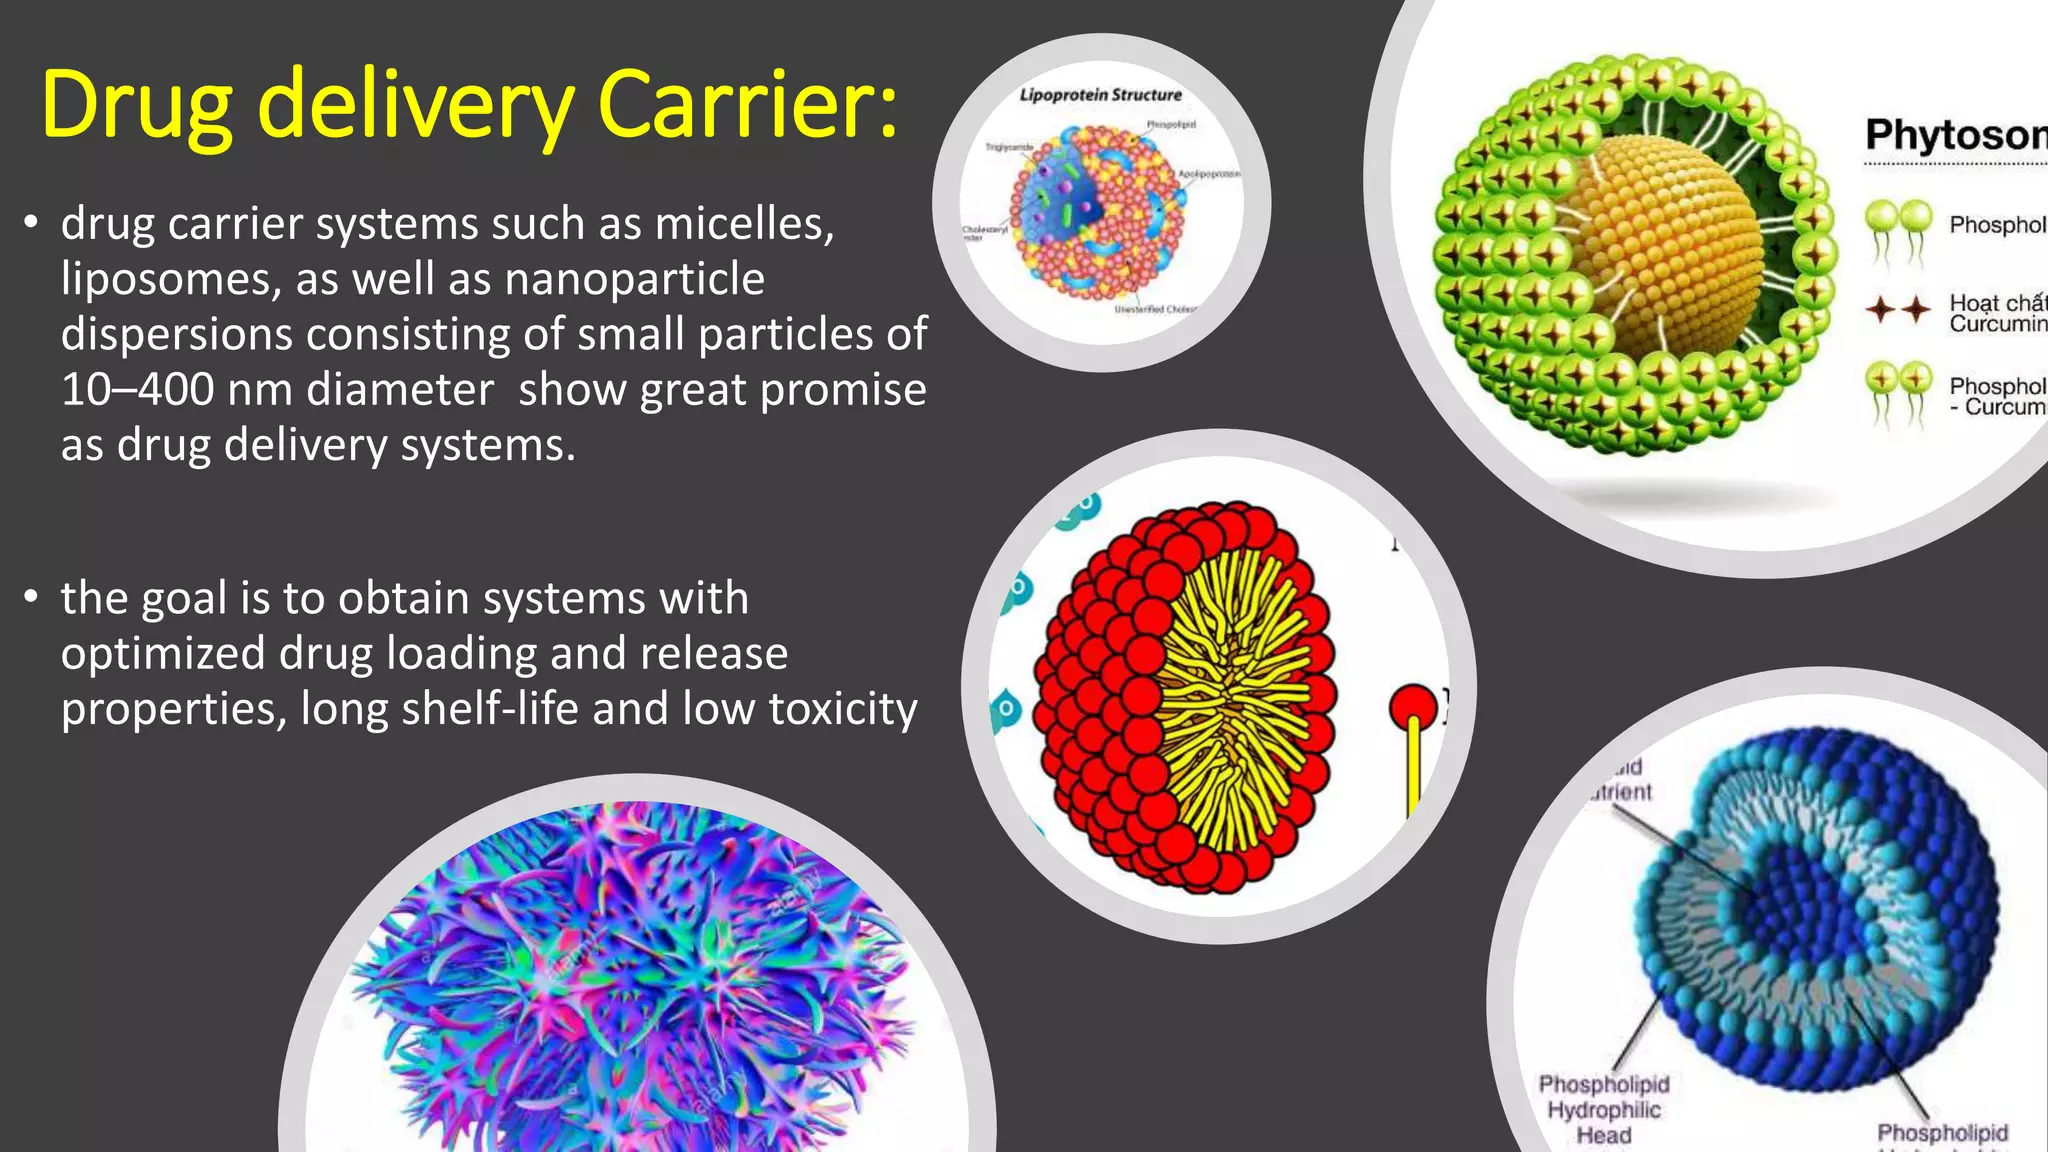
The mechanisms vary significantly by platform. Liposomes rely on the lipid bilayer structure, which mimics cell membranes. The drug sits inside the aqueous core or partitions into the lipid layer depending on whether it is hydrophilic or hydrophobic. Release happens through membrane degradation or fusion with target cells. Polymeric nanoparticles typically use diffusion or matrix erosion. PLGA degrades through hydrolysis of its ester bonds, which is pH-dependent and temperature-sensitive. That means your storage conditions matter. Store PLGA nanoparticles at room temperature instead of refrigerated, and you might see accelerated degradation within weeks. Micelles form spontaneously from amphiphilic block copolymers above their critical micelle concentration. The hydrophobic core solubilizes poorly water-soluble drugs. This is genuinely useful for compounds like paclitaxel. The famous Taxol formulation used cremophor EL as a solubilizer, which caused severe hypersensitivity reactions. The later albumin-bound nanoparticle version, Abraxane, eliminated that problem entirely. It was not a chemical modification of paclitaxel. It was a delivery system change. Transdermal delivery operates on Fick's law of diffusion. The drug must traverse the stratum corneum, the outermost layer of skin, which acts as a formidable barrier. Only molecules under roughly 500 Daltons with appropriate lipophilicity pass through efficiently. That is why most transdermal products deliver hormones, nicotine, or fentanyl. You cannot simply slap a patch on someone and expect a large molecule like insulin to work that way. The skin blocks it. This is not a failure of the patch. It is a fundamental limitation of the route.
Platforms and Their Real-World Tradeoffs
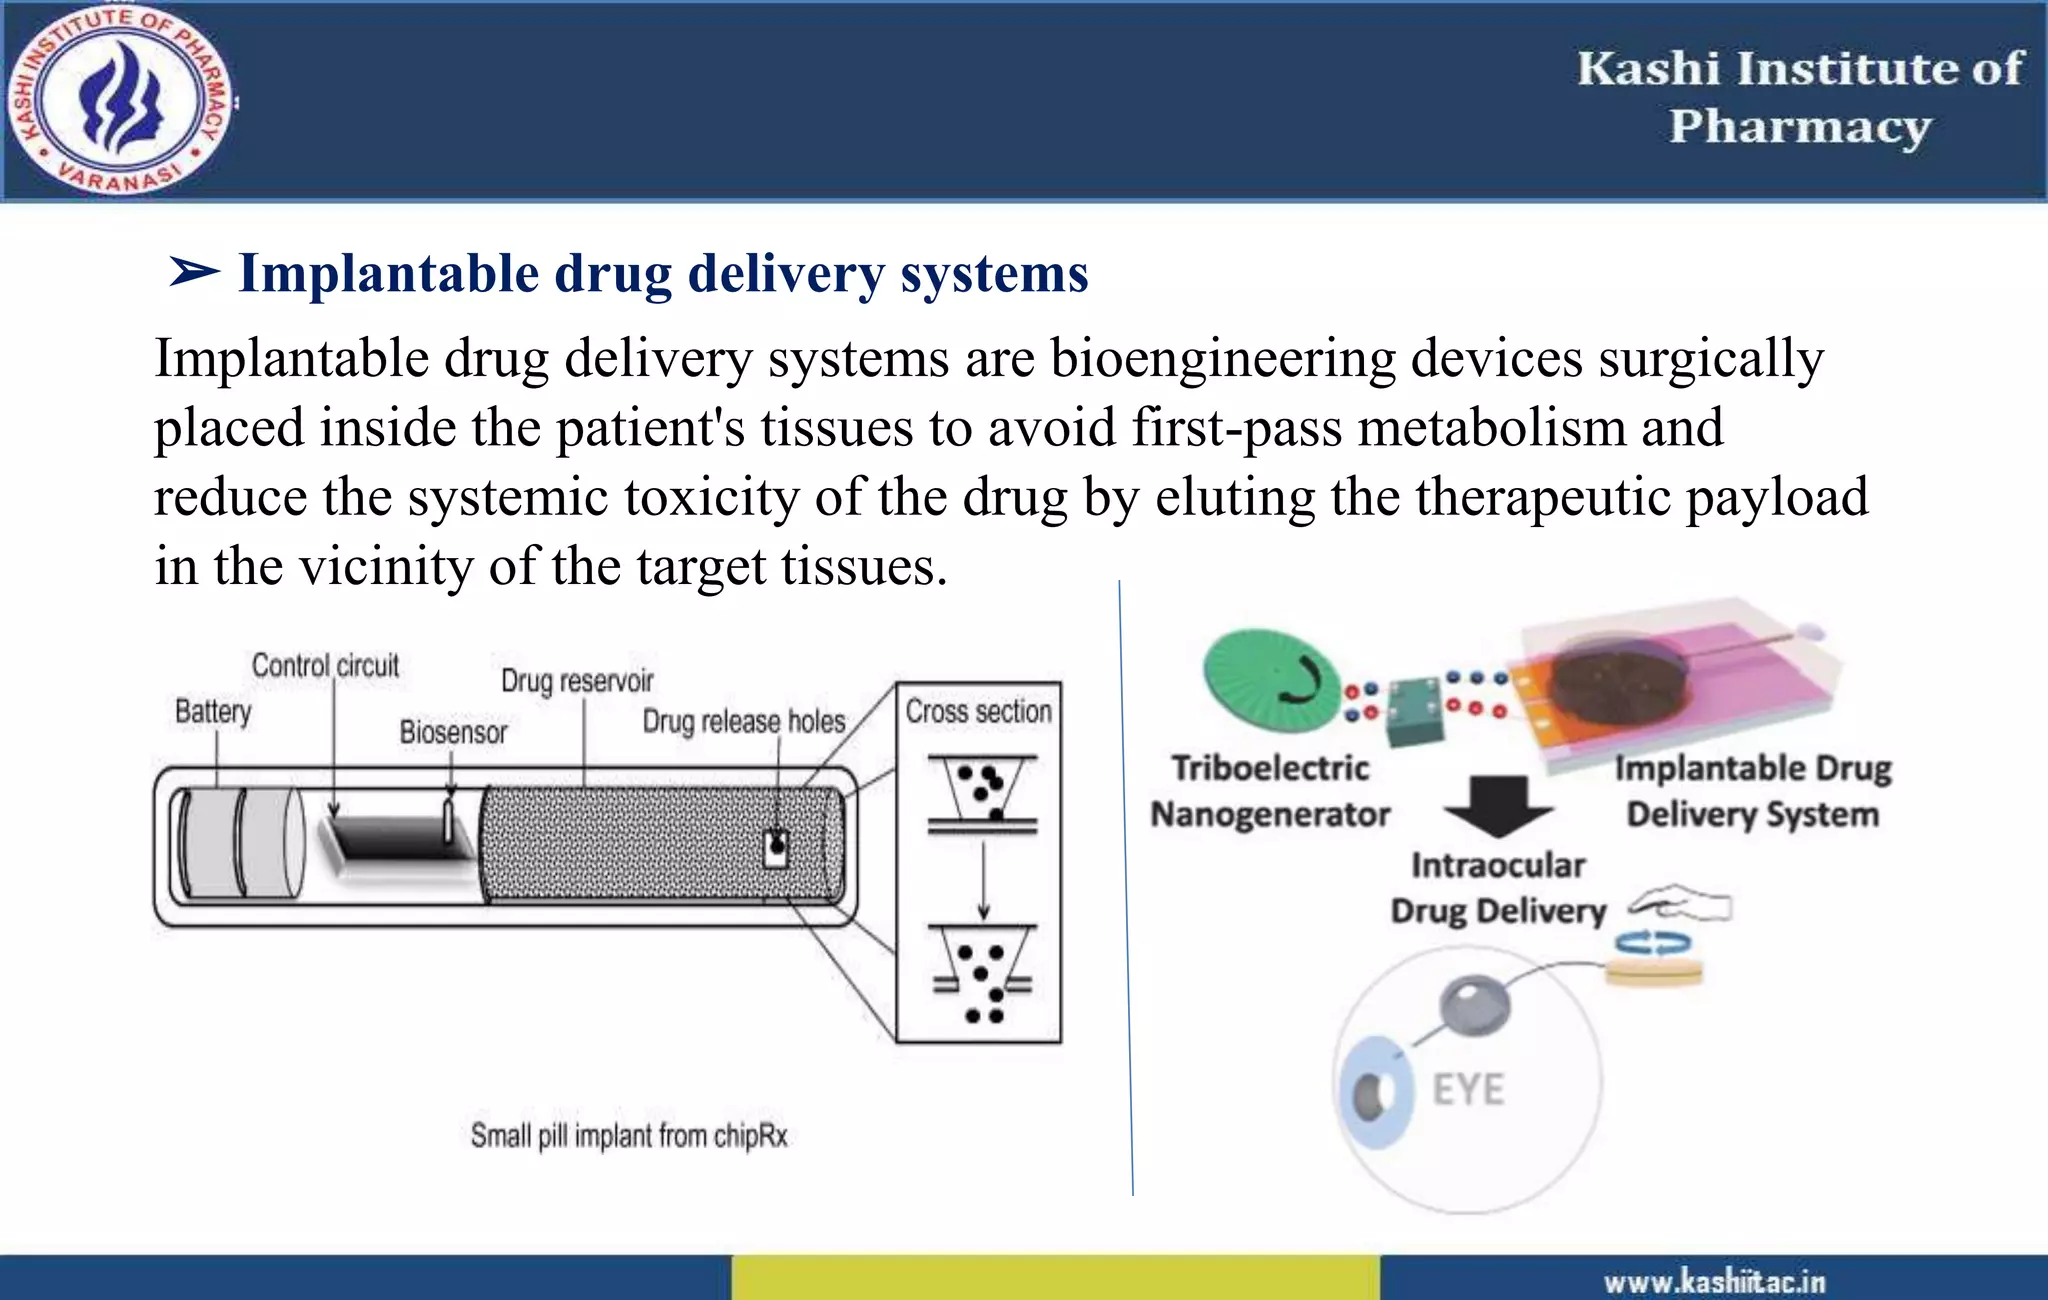
Liposomal doxorubicin, marketed as Doxil, demonstrated that PEGylation reduces uptake by the reticuloendothelial system. This extends circulation time from minutes to hours. The tradeoff is a different toxicity profile. Hand-foot syndrome became a dose-limiting side effect that did not appear with conventional doxorubicin. You gain reduced cardiotoxicity but lose a tolerable safety margin elsewhere. The therapeutic index shifts. It does not necessarily improve overall. Nanoparticle systems face a characterization bottleneck that slows development considerably. Dynamic light scattering gives you hydrodynamic diameter. Zeta potential tells you surface charge. Neither tells you the exact drug loading in the core versus the surface. You need high-performance liquid chromatography combined with sizing exclusion chromatography for that. Most labs skip the second step because it adds time and cost. That shortcuts the quality control process, and you end up with batches that look fine on paper but perform inconsistently in vivo. Sustained-release implants represent another category. They are solid devices placed subcutaneously or intramuscularly that release drug over months. The hormonal contraceptive implant is a well-known example. The advantage is patient compliance. One insertion covers months of dosing. The disadvantage is irreversibility. If a patient has an adverse reaction, you cannot stop the release quickly. Surgical removal is required. This is an important clinical consideration that gets overlooked during early development phases.
Get the Full Details
Another underappreciated issue involves food effects. Many oral novel delivery systems have been tested under fasting conditions during clinical trials. When introduced to the market, patients take them with food. This changes gastric emptying time, bile salt concentration, and intestinal motility. I encountered a formulation that showed consistent absorption in fasting volunteers but demonstrated 40 percent variability in fed subjects. The fed-state variability was unacceptable for a drug with a narrow therapeutic index. We had to add a food-effect study extension before regulatory submission. That added nine months to the timeline.
Common Pitfalls During Development
The first mistake is assuming that improving delivery solves the underlying pharmacology. A sophisticated nanoparticle formulation cannot compensate for a compound with poor target binding affinity. You still need a good pharmacodynamic profile. The delivery system optimizes exposure. It does not create activity from nothing. I have seen three separate projects derail because teams invested heavily in formulation work while the underlying molecule showed weak efficacy in early disease models. The formulation was excellent. The drug was not. Nothing about better delivery fixed that. The second mistake is ignoring manufacturing reproducibility during early research. Formulating a candidate at the milligram scale in a university lab is straightforward. Translating to Good Manufacturing Practice production introduces variables that are nearly impossible to control early on. Mixing kinetics, temperature gradients, and sterilization methods all change the final product characteristics. Gamma irradiation, commonly used for terminal sterilization, can degrade polymeric carriers. Ethylene oxide leaves residues. Sterile filtration may alter particle size distribution. Each sterilization choice affects the product differently. Plan for this before you invest in preclinical toxicity studies, or you will revisit those studies multiple times. A third problem involves immunogenicity, particularly with repeated dosing. PEGylated liposomes can trigger complement-related adverse reactions on repeated administration. This is called accelerated blood clearance. The immune system develops antibodies against the PEG coating. Subsequent doses get cleared faster. The drug exposure drops. This was documented with Doxil and has appeared with other PEGylated platforms. Researchers sometimes overlook this because single-dose studies look perfectly normal. Multiple-dose regimens reveal the problem. Test accordingly.
Regulatory and Commercial Reality
Novel drug delivery systems face a longer regulatory pathway than conventional formulations. The FDA requires comprehensive characterization including particle size distribution, polydispersity index, zeta potential, drug content uniformity, release kinetics, and stability data under ICH guidelines. You must demonstrate that the delivery system itself does not introduce new toxicity. Excipients that are generally recognized as safe at low concentrations may behave differently at the higher doses found in nanoparticle formulations. This is a regulatory gray area that causes delays. The cost implications are significant. Developing a novel delivery system from concept to market approval typically costs between 50 million and 200 million dollars depending on the platform and indication. This assumes no major setbacks. Setbacks are common. A promising formulation failed in Phase II clinical trials because the drug precipitated out of the carrier during storage at ambient temperature during summer months in a tropical testing site. The formulation was stable at 25 degrees Celsius but not at 30 degrees. That gap between laboratory stability and real-world distribution conditions is exactly the kind of problem that catches developers off guard. The market landscape is shifting. Generic versions of some liposomal products are approaching patent expiration. This creates opportunities for follow-on formulations but also increases competitive pressure. Companies developing novel delivery systems need a clear differentiation strategy. Simply improving bioavailability by 20 percent may not justify the additional development cost if a cheaper generic alternative exists. The bar for clinical significance is higher than the bar for statistical significance.
Where the Field Is Actually Headed
The most active research areas involve stimuli-responsive systems that release drug in response to specific triggers. pH-sensitive carriers exploit the slightly acidic environment of tumor tissue. Enzyme-cleavable linkers respond to elevated matrix metalloproteinase levels in inflammatory conditions. Thermosensitive hydrogels transition from liquid to gel at body temperature, enabling injectable sustained-release Depot formulations. These concepts are sound. Several have reached clinical evaluation. Most have not yet demonstrated meaningful advantage over established delivery platforms in head-to-head trials. Combination approaches are gaining attention. A nanoparticle that targets a specific receptor and responds to an internal stimulus represents the logical next step. This is technically demanding. Targeting requires ligand conjugation. Stimuli-responsiveness requires careful material selection. Both requirements introduce formulation complexity. Each added component adds another variable that must be characterized and controlled. The result is a development timeline that expands significantly compared to a simpler delivery system. Microfluidic manufacturing is one practical advancement worth noting. It enables precise control over particle size and encapsulation efficiency during production. Traditional methods like thin-film hydration and solvent evaporation produce broad size distributions requiring downstream processing. Microfluidics can produce narrow distributions in a single step. The equipment is expensive. The throughput is lower than batch processing. But the consistency is substantially better, which matters enormously for regulatory approval and manufacturing reproducibility.
The bottom line is that novel drug delivery systems are powerful tools for specific problems. They do not solve every drug development challenge. The best formulations emerge from matching the right platform to the right drug with realistic expectations about what can be achieved. I have seen excellent scientists waste years on formulations that addressed solubility but introduced toxicity, or solved targeting but failed at scale. Pick your constraints carefully. Know which problems your delivery system is actually designed to solve. Everything else is incremental optimization work.