Peptide Therapy Explained Without the Hype
Peptide therapy involves using short chains of amino acids to trigger specific biological responses in the body. That's the textbook version. The reality is messier, more variable, and frankly less magical than most clinics want you to believe. I've spent years working around these compounds, watching people get disappointed, and figuring out what actually moves the needle versus what's just expensive urine. When someone asks what is peptide therapy, the honest answer starts with understanding that peptides are signaling molecules. They're smaller than proteins but larger than single amino acids, usually sitting somewhere between two and fifty amino acid residues. Their whole job is to bind to receptors on or inside cells and tell those cells to do something. That's it. The marketing around them has inflated this mechanism into something resembling a cure-all, but the biology doesn't lie — you're modifying signaling pathways, not rewriting your DNA or replacing hormones outright.
What Is Peptide Therapy Actually Used For
The peptides that see the most clinical and off-label use fall into a few rough categories. Recovery peptides like BPC-157 and TB-500 are probably the most common starting point. They're used for tissue repair, gut healing, and inflammation modulation. Growth hormone secretagogues like CJC-1295, Ipamorelin, and GHRP-2 stimulate your pituitary to release more growth hormone. The results are modest compared to actual HGH, and the cost-benefit analysis is questionable for most people. Immune-modulating peptides like Thymalin and Epitalon see occasional use but the evidence base is thin. Metabolic peptides like Semaglutide have gotten a lot of attention recently, though those are prescription drugs with their own complications. I remember running into a patient who wanted to stack BPC-157 with TB-500 for a chronic shoulder issue that had lasted eight months. Both compounds individually have some data behind them, but together they did absolutely nothing beyond what either would have done alone. The problem was that the shoulder wasn't a soft tissue problem anymore — it was structural damage with impingement. No peptide is going to fix a torn rotator cuff. I told them to get an MRI first, which turned out exactly as I expected. They ended up needing surgery. The peptides were a waste of maybe four hundred dollars between them. Don't skip the diagnostic step. Peptides don't fix everything, and they definitely don't fix mechanical problems.
How It Actually Works in Practice
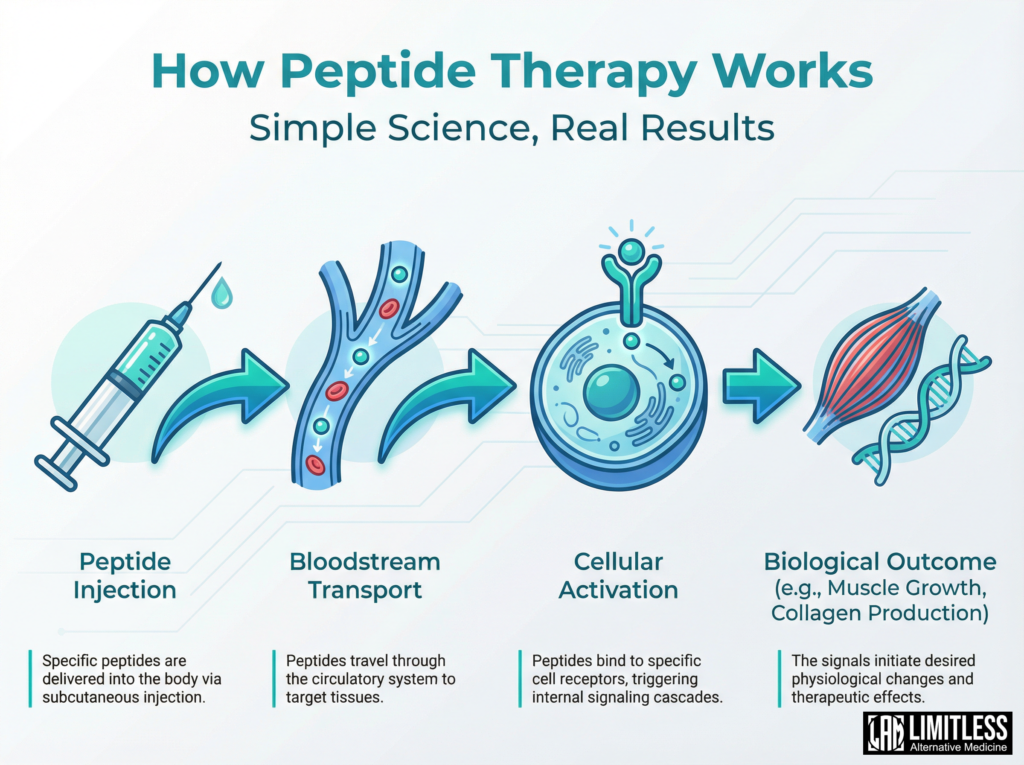
The administration side is where most people go wrong. Most peptides require subcutaneous injection. That means a small insulin-style needle, into the fat layer just under the skin. The abdomen is the standard site because it's consistent and relatively pain-free. You reconstitute the lyophilized peptide powder with bacteriostatic water, draw up the dose, and inject. The whole process takes maybe ninety seconds once you've done it a few times. The hard part isn't the injection itself — it's managing expectations about what the injection will actually accomplish. Pemotido therapy is not fast. Most compounds require weeks to months before any noticeable effect shows up. BPC-157 might show some early signs in three to four weeks for acute issues, but chronic conditions often need eight to twelve weeks minimum. Growth hormone secretagogues usually take six to eight weeks before you see changes in body composition, and even then the changes are in the single-digit percentage range for most people. If someone is promising you dramatic results in two weeks, they're either lying or selling you something completely different. One thing nobody talks about enough is peptide stability. Once you reconstitute a peptide, it starts breaking down. Even stored in the fridge with bacteriostatic water, most reconstituted peptides are only stable for about four to six weeks. After that, the potency degrades and you're essentially injecting expensive contaminated water. I've seen people go through entire courses of reconstituted peptides that sat in a syringe for two months because they weren't tracking usage. Always label your vials with the reconstitution date and throw anything older than six weeks away. The money you save by reusing old batches isn't worth the inconsistent dosing.
Get the Full Details

The Quality Problem Nobody Wants to Discuss
This is probably the most important section and the one most people skip. The peptide industry outside of prescription pharmaceuticals is largely unregulated. Research chemical companies operate in a space where there's very little third-party testing happening. A study by the Journal of Pharmaceutical Sciences found that a significant percentage of peptides sold by online vendors had incorrect dosages, contamination, or were completely wrong compounds. I've personally had clients send vials out for mass spectrometry testing and come back with results showing the actual peptide content ranged from thirty percent to one hundred and twenty percent of what was labeled. Sometimes the vial contained zero of the named compound and something else entirely. If you're going to do this, invest in third-party testing. Companies like Janoshik and Prohesion do HPLC and mass spec verification for a few hundred dollars per batch. It's not cheap, but it's infinitely cheaper than poisoning yourself with a contaminated product or wasting months on a compound that isn't even in the vial. I always tell people to pick vendors who provide current Certificates of Analysis, not ones who just claim purity on their website. The difference between a company that publishes its COAs and one that doesn't is usually the difference between knowing what you're injecting and hoping for the best.
Side Effects and What Can Go Wrong
Peptides aren't harmless just because they're peptides. Common side effects from growth hormone secretagogues include water retention, numbness or tingling in the extremities from fluid shifts, increased appetite, and elevated blood sugar. BPC-157 is generally well-tolerated but can cause fatigue and headaches in some people. The long-term safety data for most non-prescription peptides is essentially nonexistent because nobody has funded the studies. That doesn't mean they're dangerous, but it also means nobody can confidently say they're safe over extended periods. The bigger risk comes from the injection practice itself. Using non-sterile technique, reusing needles, or injecting into muscle instead of subcutaneous fat can cause abscesses, nerve damage, or localized tissue necrosis. I've seen all three. Keep it clean, use a fresh needle every time, and learn proper injection technique before you start stacking compounds. A quick YouTube video won't cut it — find a nurse or someone with actual injection experience and watch them do it properly. The difference between a clean subcutaneous hit and a botched intramuscular injection is the difference between a tiny red dot and an abscess that needs incision and drainage. There's also the hormonal cascade issue that people overlook. When you're stimulating growth hormone release with peptides like Ipamorelin or GHRP-2, you're affecting IGF-1 levels, insulin sensitivity, and cortisol dynamics. For someone with a pre-existing metabolic condition or a family history of diabetes, this matters. I had a client whose fasting glucose jumped from a healthy 82 to 118 after six weeks on a GH secretagogue stack. We dropped the compounds and it came back down in three weeks, but it was a close call. Get baseline bloodwork before starting anything and retest at the eight-week mark. Fasting glucose, IGF-1, and a comprehensive metabolic panel will tell you if your body is handling the therapy correctly or if you should stop.
A Realistic Assessment
Peptide therapy can be useful in specific situations. Post-injury recovery where conventional treatments have plateaued. Age-related decline in growth hormone where TRT isn't an option or isn't sufficient. Certain gastrointestinal issues where BPC-157 has shown genuine promise in the literature. But for the vast majority of healthy people looking for an edge, the return on investment is poor. The cost per month runs anywhere from two hundred to eight hundred dollars depending on the protocol, and the results are incremental at best. You'll spend less money and get better results from optimizing sleep, nutrition, and training programming. The peptides that actually deserve attention right now are the GLP-1 agonists like Semaglutide and Tirzepatide, but those are prescription medications with substantial clinical backing and regulatory oversight. They're also expensive and come with their own side effect profile including nausea, gallbladder issues, and potential muscle loss if protein intake and resistance training aren't dialed in. The newer oral semaglutide formulations are making access easier but the core issues remain the same — this is prescription-grade pharmacology, not a supplement stack. If you're serious about exploring this, find a licensed provider who actually checks your labs and doesn't just write prescriptions after a fifteen-minute consultation. The telehealth clinics that mail you peptides based on an online questionnaire are optimizing for volume, not outcomes. Your health is worth more than a fast online form. Track your data, test your products, and keep your expectations realistic. Peptides are tools, not miracles, and treating them like anything else will cost you money and possibly your health.