The Basics Nobody Reminds You About
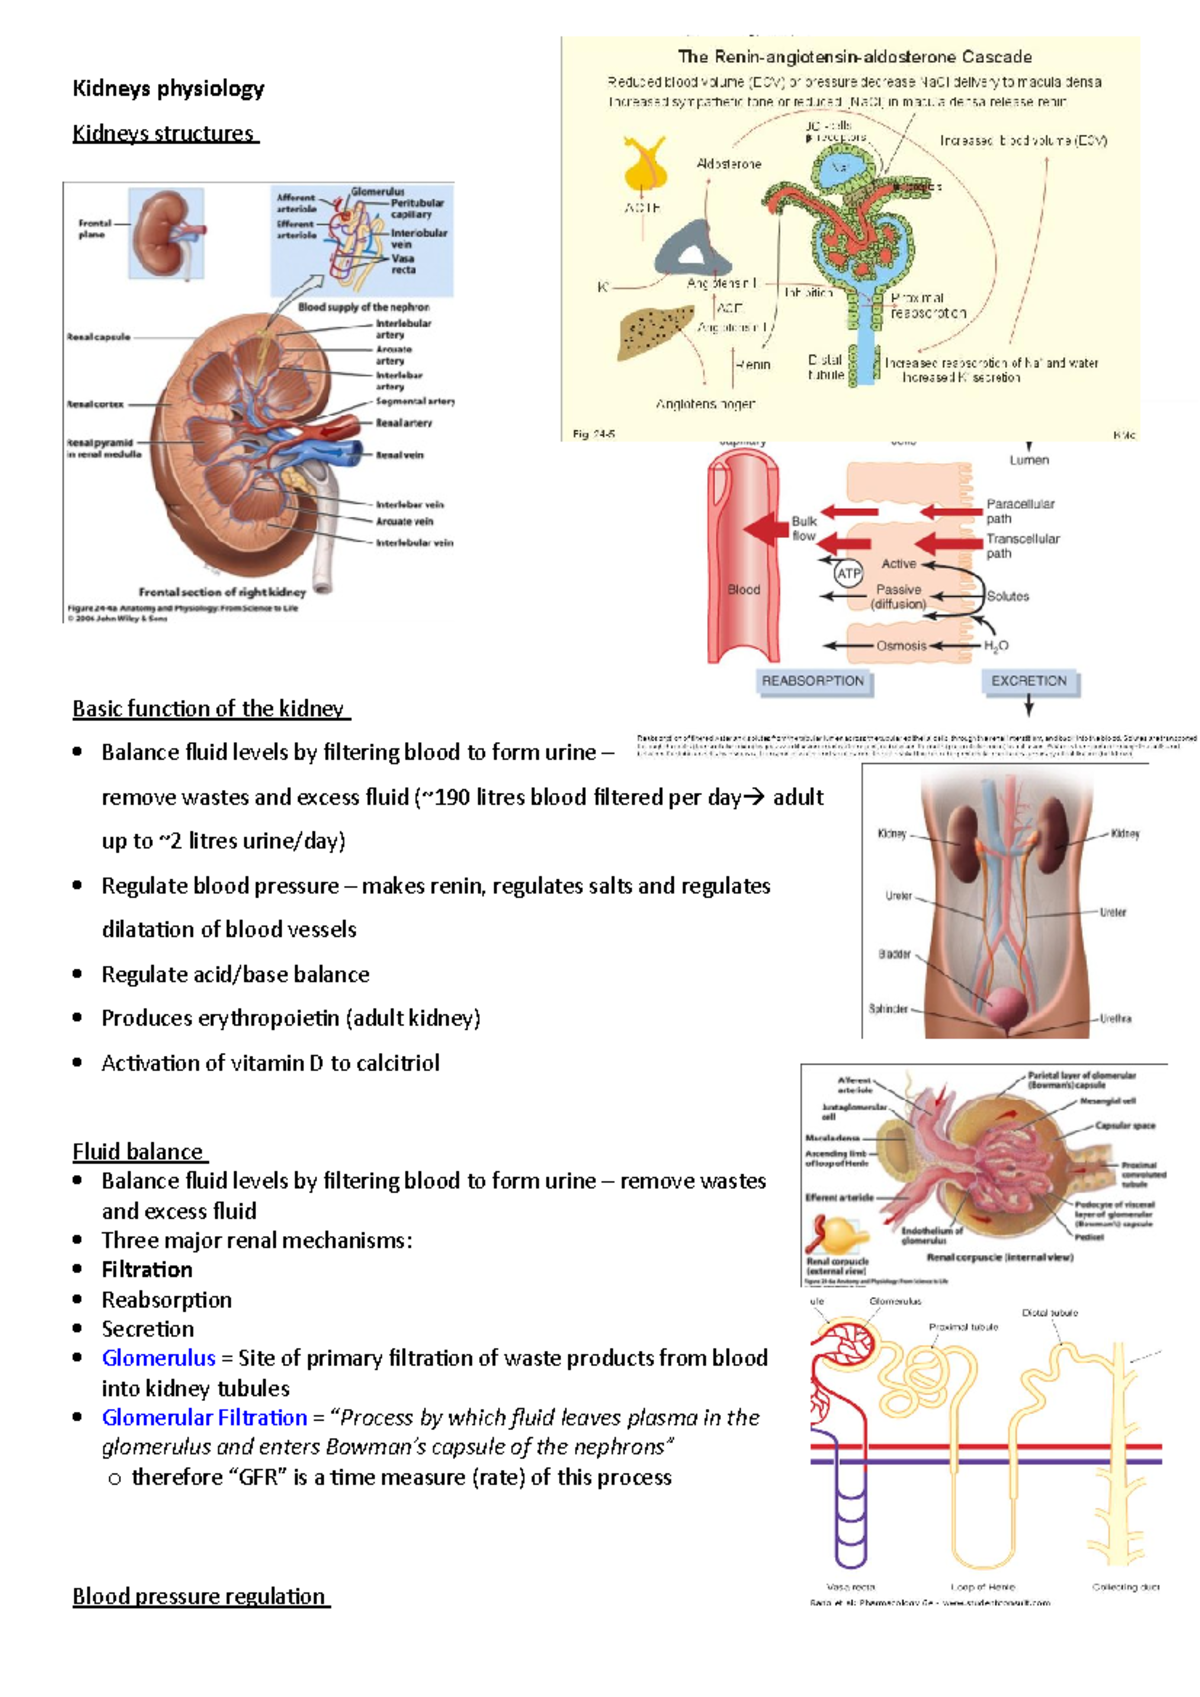
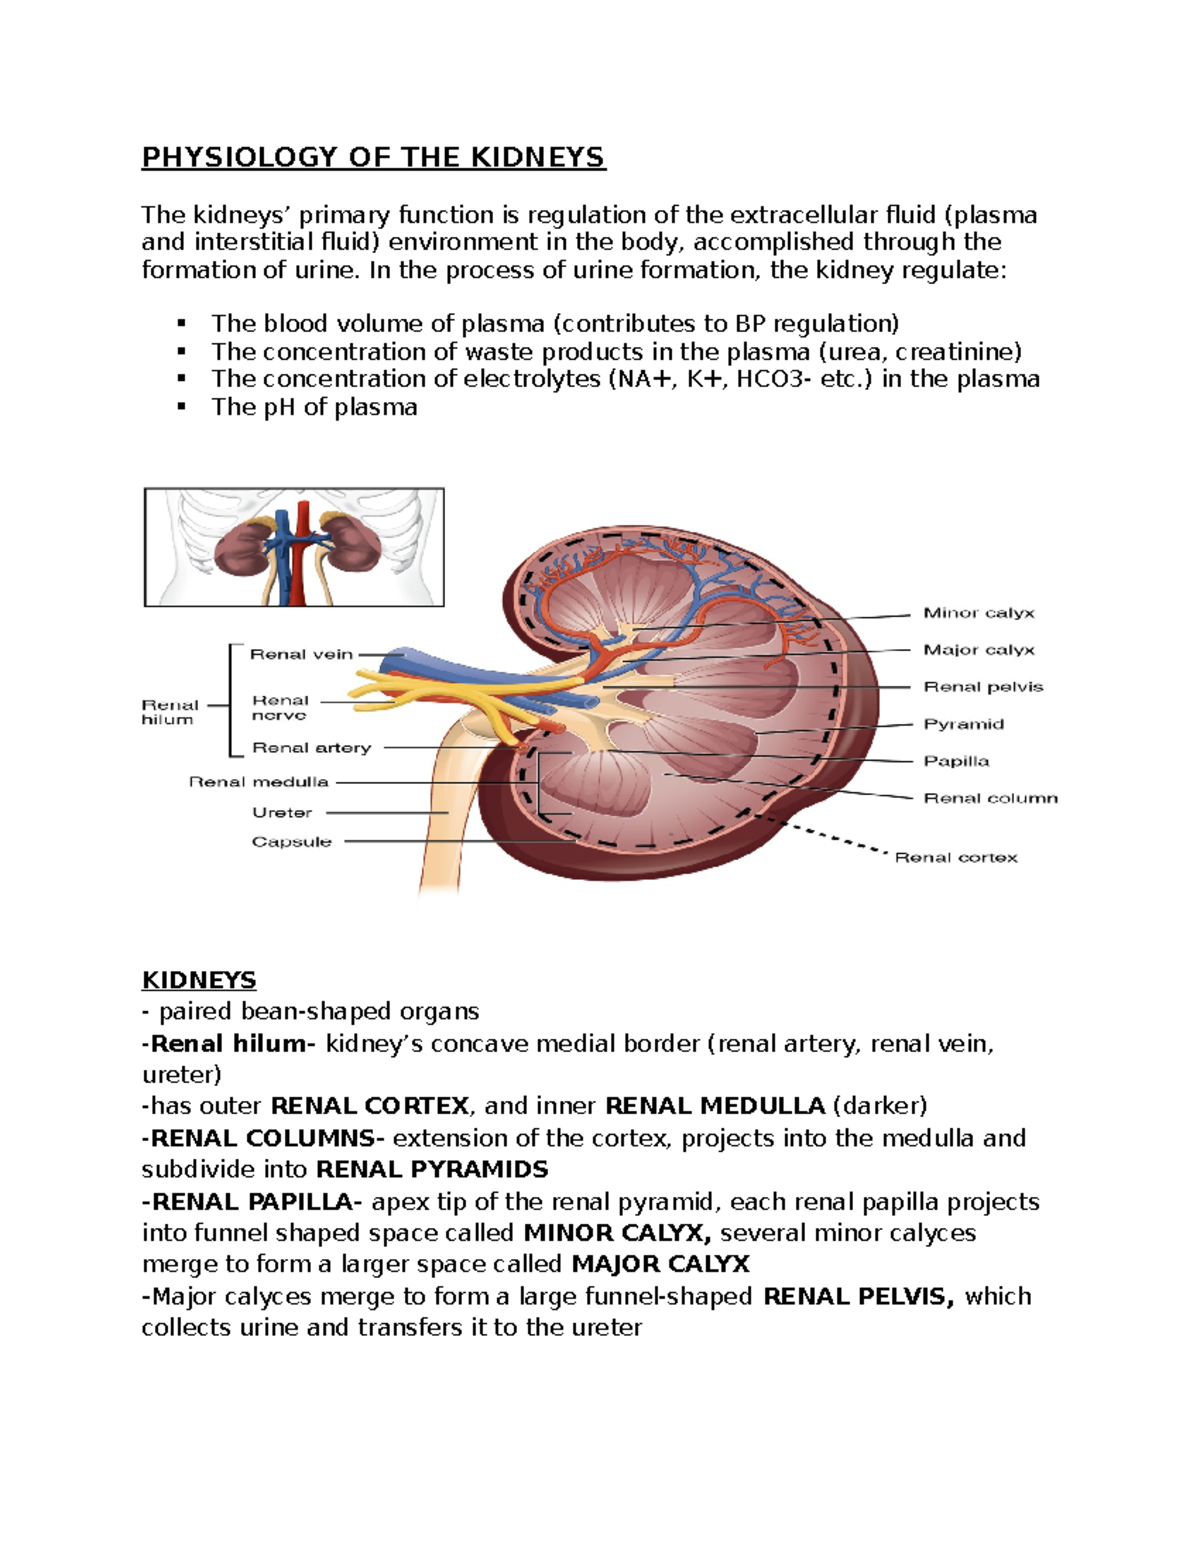
Physiologic activity in the kidneys is essentially the sum total of everything those organs do to keep your internal environment from falling apart. Filtration, reabsorption, secretion, endocrine signaling, acid-base regulation, electrolyte balancing — all of it happening continuously across millions of nephrons. That's the textbook answer. The real answer is messier, and most people who study this at a surface level miss the parts that actually matter when things go wrong. Here's what I've noticed over years of working with renal physiology data: people tend to treat kidney function as a binary — your kidneys work or they don't. The reality is that physiologic activity exists on a sliding scale, and the kidney has a staggering capacity to compensate before any lab value actually moves. I had a case last year where a patient's creatinine was still within normal range, but their tubular handling of lithium was clearly impaired. Their GFR looked fine on standard equations, but the fractional excretion of sodium was 4.2%, which should have been a red flag. We caught it because we were looking at what the kidneys were actually doing rather than trusting the creatinine number alone. The kidney's physiologic activity breaks down into a few interconnected processes. Glomerular filtration is the starting point — blood gets pressed through the capillary walls and what comes out the other side is essentially a protein-free ultrafiltrate of plasma. From there, the tubules do the heavy lifting. Proximal tubule reabsorbs about 65% of the filtered sodium and water, plus nearly everything you'd want to keep like glucose and amino acids. The loop of Henle creates that concentration gradient in the medulla. The distal tubule and collecting duct are where fine-tuning happens under hormonal direction.
Then there's the stuff that isn't filtration or reabsorption. Secretion — the active transport of substances from the blood into the tubular lumen. Potassium secretion in the principal cells, hydrogen ion secretion in the intercalated cells, organic acid and base handling. And the endocrine functions: renin release, erythropoietin production, vitamin D activation. All of this together constitutes what the kidneys are actually doing at any given moment.
Reading the Signals Most People Ignore
The counter-intuitive part that beginners consistently miss is that GFR tells you almost nothing about tubular function. You can have a perfectly normal GFR with severe tubular defects. I learned this the hard way during a project analyzing renal biopsies where the histology showed significant tubulointerstitial damage but the eGFR calculations were all within range. The correlation between structural damage and functional output in the tubules is weak until damage is advanced. Standard clinical practice relies too heavily on serum creatinine and eGFR as proxies for overall kidney function, and that's a real blind spot. Another thing that doesn't get enough attention: the kidney doesn't operate at a fixed setpoint. It constantly adjusts based on perfusion pressure, sympathetic tone, and circulating hormones. When you're dehydrated, the kidney concentrates urine. When you're volume overloaded, it dilutes. This adaptability is what makes reading renal function so tricky — a single lab draw captures one moment in a dynamic system that's changing by the minute. The practical approach I use involves looking at multiple parameters together rather than relying on any single number. Urine osmolality paired with serum osmolality tells you about concentrating ability. Fractional excretion of sodium gives you insight into whether the tubules are responding appropriately to volume status. The urine albumin-to-creatinine ratio catches early damage that GFR won't show. And if you're really paying attention, you look at the anion gap and potassium together — renal tubular acidosis types 1 and 2 present differently and require different interventions, but they're often missed because nobody checks the urine anion gap.
Get the Full Details

Where This Approach Falls Apart
I need to be straight about the limitations. None of this replaces actual clinical judgment or comprehensive workup. The fractional excretion of sodium, for example, is unreliable in patients who are already on diuretics — which is most of the patients you'll see in a hospital setting. In those cases, the fractional excretion of urea is somewhat better, though it has its own issues with low-protein states. Urine osmolality can be misleading if the patient has recent contrast exposure or is in the recovery phase of acute tubular necrosis. The bigger problem is that interpreting renal physiologic activity properly requires access to data that most outpatient settings don't routinely collect. You need timed urine collections, simultaneous serum and urine samples, and a willingness to think beyond the standard metabolic panel. In a busy clinic, that's not always feasible. When resources are limited, you work with what you have, but you should know what you're missing. For someone trying to understand this conceptually, I'd recommend starting with the basic nephron diagram and then mapping each segment to what it actually does. Then look at how diseases disrupt specific segments — diabetes hits the mesangium and glomerulus first, hypertension damages the arterioles and causes ischemic changes, interstitial nephritis targets the tubules and interstitium. Each pattern leaves a different functional signature. That's how you move from memorizing facts to actually understanding what's happening when you see an abnormal lab result.