What This Stuff Actually Is
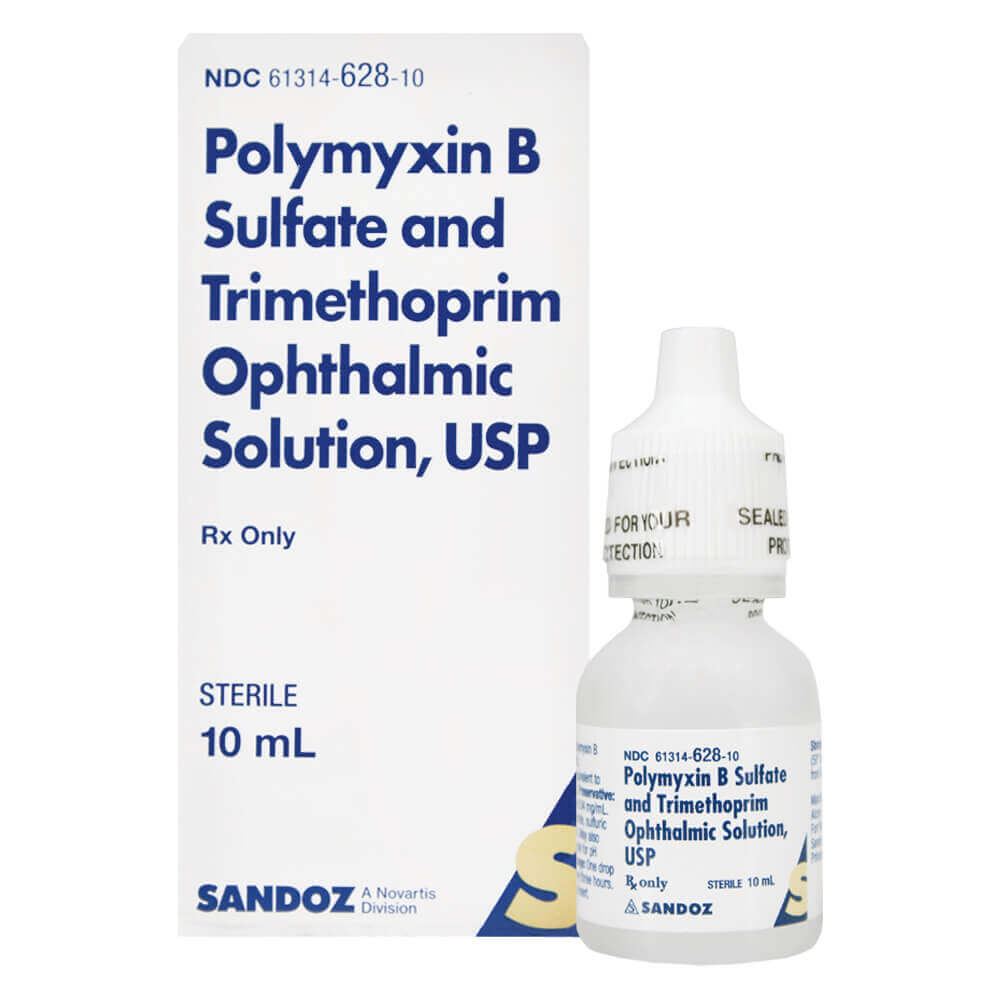
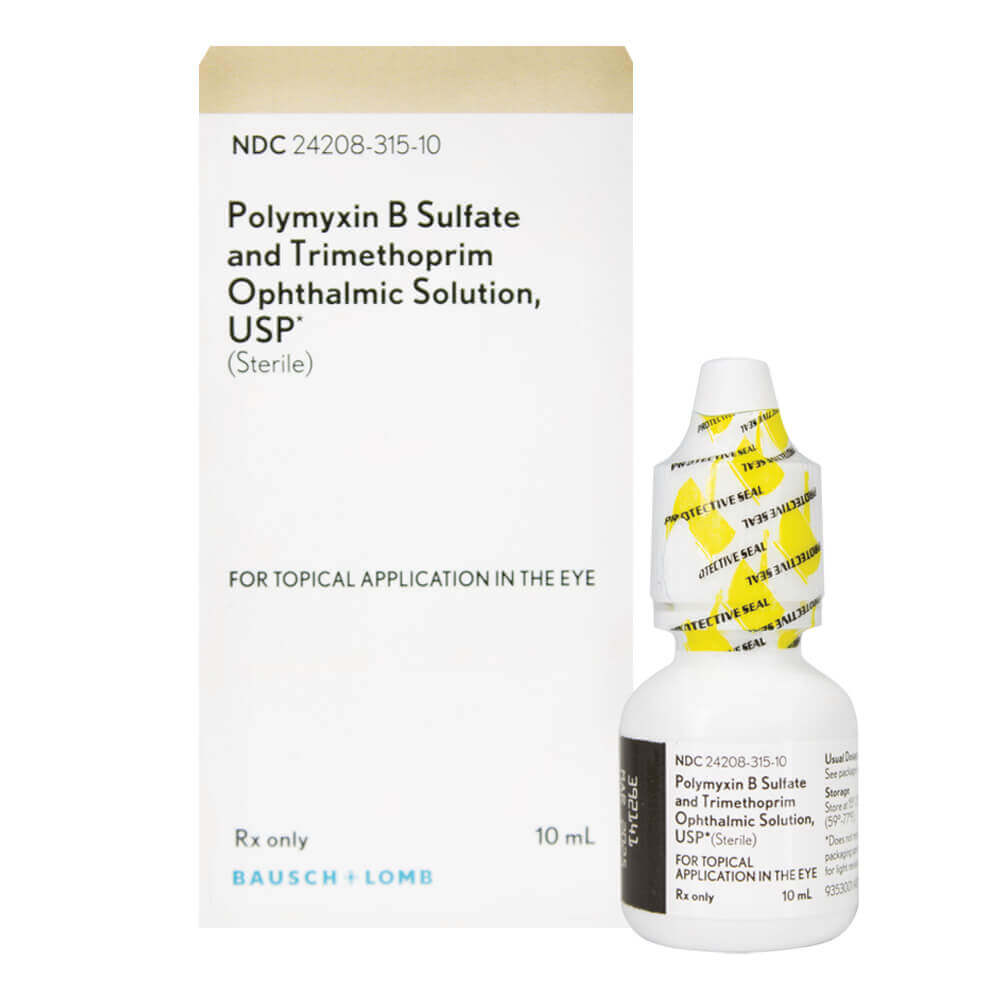
Polymyxin B sulfate and trimethoprim ophthalmic solution is a combination antibiotic eye drop used to treat bacterial conjunctivitis and other superficial eye infections. It pairs two different antibiotic mechanisms together — polymyxin B targets the cell membranes of gram-negative bacteria while trimethoprim interferes with folate synthesis in a broader range of organisms. The result is a decent broad-spectrum coverage for common ocular pathogens. It's prescribed mainly for conjunctivitis caused by susceptible bacteria like Staphylococcus aureus, Klebsiella, E. coli, Proteus, and some Pseudomonas species. You'll see it ordered more often in the acute bacterial pink eye cases where the provider wants coverage without jumping straight to fluoroquinolones. It's not a first-line treatment for keratitis or any deep ocular infection. That requires something more aggressive. I've been compounding and reviewing ophthalmic prescriptions for years, and honestly this one sits in a weird middle ground. It works fine for straightforward conjunctivitis. The problem is dosing compliance and preservation issues that most people don't think about until they're dealing with a complaint.
The typical dosing regimen is one to two drops in the affected eye every two to four hours during the acute phase, then tapered down as symptoms improve. Most patients get labeled for a seven to ten day course. The trick is getting them to actually use it consistently during those first few days when the eye is red and irritated enough that they want relief but also sensitive enough that putting anything in there feels awful. One thing I ran into repeatedly — and this is the edge case that catches people off guard — is the preservative. This solution usually contains benzalkonium chloride at 0.005 percent or thereabouts. That's standard. But patients who wear contact lenses absolutely cannot keep them in while using this. The BAK gets absorbed into the soft lens material and essentially sits against the cornea like a low-grade chemical burn. I had a patient come back after three days with worsening discomfort and a diffuse punctate keratopathy on slit lamp that was textbook BAK toxicity, not the original infection getting worse. She'd been dropping the solution and immediately reinserting her contacts because she hated wearing glasses during the day. The workaround is straightforward but you have to tell the patient explicitly: remove lenses before instilling, wait at least fifteen to twenty minutes before reinserting, and preferably just switch to glasses for the duration of the treatment course. Fifteen minutes isn't going to cut it if they've been wearing daily disposables all day already — the lens is saturated. Twenty minutes minimum, thirty if they can manage it.
Here's the counter-intuitive part most people miss about this combination. The polymyxin B component is a large polypeptide molecule. That means it has poor corneal penetration on its own. It works primarily on the ocular surface and in the tear film. Trimethoprim penetrates better but still doesn't achieve significant intraocular concentrations. So if you're treating something like a corneal ulcer, this is the wrong drug. Period. You'd be applying surface-level coverage to a problem that extends deeper. Fluoroquinolone monotherapy or fortified antibiotics are the actual choices there. Another nuance: resistance patterns matter more with this combo than you'd think. Trimethoprim resistance in S. aureus has been climbing steadily. Polymyxin B resistance is less common but not irrelevant, especially in Pseudomonas strains from chronic or prior-antibiotic-exposed eyes. If the culture data shows resistance to either component, the combination loses its synergistic advantage and you're just giving the patient a drug with two mechanisms and one effective pathway. That's not catastrophic but it's not optimal either. The solution is typically supplied as a 10 mL bottle with concentrations of polymyxin B sulfate 10,000 units per mL and trimethoprim 0.5 percent. Some compounding pharmacies prepare it fresh because the combination isn't widely available as a commercial product in all regions. If you're getting it from a compounding source, ask about the preservative system and the expiry dating. A lot of compounded ophthalmic solutions carry a 28-day beyond-open date, sometimes less depending on the preservative and storage conditions. That's a real constraint if the patient is only using one drop twice a day after the acute phase — they might be near the end of the bottle while the solution is already past its stable window.
Get the Full Details

Storage matters more than patients realize. Keep it at controlled room temperature, not in the bathroom cabinet where humidity and temperature fluctuate daily. I've seen bottles left on a windowsill in summer and the solution turned noticeably cloudy by the end of the week. That's degradation, not contamination, but it's a signal the product integrity is compromised. For side effects, the usual suspects apply: transient burning or stinging on instillation, which most patients report within the first minute and then it fades. Occasional conjunctival hyperemia, bitter taste if the drop drains through the nasolacrimal duct — that's normal and not dangerous. Allergic reactions to either component or the preservative are rare but documented. If the redness and itching actually worsen after starting the drops rather than improving, consider hypersensitivity and discontinue. Pregnancy category considerations: neither component is absolutely contraindicated but there isn't robust safety data for either in pregnancy. Trimethoprim is a folate antagonist, which raises a theoretical concern in the first trimester. Not a hard stop in my experience, but it's something the prescribing provider should factor in. For nursing, minimal systemic absorption occurs from ophthalmic use but it's still present, and trace amounts could pass into breast milk. Again, not a clear contraindication, but worth flagging.
Drug interactions are minimal with ophthalmic administration since systemic absorption is low, but if the patient is on oral warfarin there's a theoretical interaction with trimethoprim affecting metabolism. The risk from eye drops is probably negligible, but I've seen it listed in the prescribing information and it comes up occasionally in pharmacology reviews. The main limitation of this solution is that it's simply not strong enough for serious infections. Anyone with a corneal defect, suspected keratitis, post-surgical prophylaxis with higher-risk organisms, or immunocompromised status should be evaluated by an ophthalmologist rather than managed with this as monotherapy. It's a surface infection drug, not a deep tissue drug. Using it beyond its indications is where problems show up — delayed appropriate treatment, false reassurance from partial symptom improvement, and ultimately worse outcomes when the infection was never going to respond to this particular spectrum. If you need something broader for confirmed or strongly suspected Pseudomonas involvement in a contact lens wearer, a fluoroquinolone like ciprofloxacin or ofloxacin drops are the more reliable choice. They penetrate better, cover Pseudomonas more consistently, and don't have the same corneal penetration ceiling that polymyxin B has.
Pricing varies widely depending on whether it's a branded product, a generic, or a compounded formulation. Commercial versions run roughly forty to eighty dollars for a 10 mL bottle without insurance. Compounded versions from a good pharmacy can be twenty to forty dollars. Insurance coverage for ophthalmic antibiotics is usually decent under pharmacy benefits, but prior authorization sometimes comes up with the combination products depending on the plan. Bottom line: it's a reasonable option for uncomplicated bacterial conjunctivitis when the suspected organisms fall within the susceptibility range. It's not a universal solution, it has real limitations on penetration and spectrum, and compliance with the dosing schedule and contact lens restrictions is where most practical failures happen. Pick the right case, use it correctly, and it does its job. Push it beyond what it's meant for and you'll see it fail.