Understanding Pulse Rate Desaturation Index in Sleep Medicine
PRDI stands for Pulse Rate Desaturation Index. It counts how many times per hour your heart rate drops in response to a drop in blood oxygen during sleep. It is one of the metrics automated scoring engines pull from overnight polysomnography data, and it has become a standard part of sleep lab reporting alongside AHI and RDI. Here is how it actually gets calculated. The device records your oxygen saturation via pulse oximetry and simultaneously tracks your pulse rate. When the SpO2 drops by a set threshold — usually 3 percent or 4 percent depending on the software — the algorithm looks at whether the pulse rate concurrently decreases. If it does, that event gets counted. Divide the total number of those paired events by hours of recorded sleep and you have the PRDI. The threshold and time-delay parameters can vary between vendors, which is why two labs might report slightly different numbers for the same patient.
What Is Prdi In Sleep Study And Why It Matters Clinically
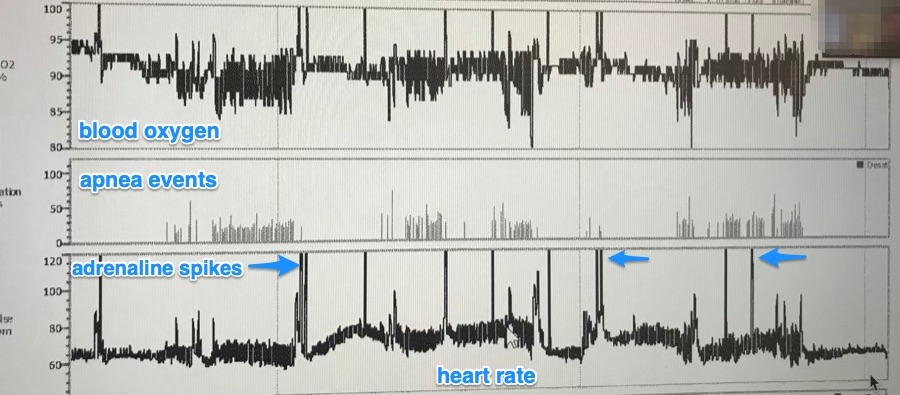
The index matters because it captures autonomic responses that standard oxygen desaturation indices sometimes miss. A patient can have significant sleep-disordered breathing that triggers sympathetic surges without always producing oxygen drops steep enough to meet conventional thresholds. The PRDI catches those events by pairing the desaturation with the cardiac response. It is especially useful in borderline cases where the AHI sits in that gray zone between mild and moderate. I ran into this exact problem last year with a patient whose AHI was 11 and RDI was 14, both sitting firmly in mild territory, but their PRDI was 38. Their oximetry trace looked relatively calm on visual inspection. The pulse rate however was spiking repeatedly with each respiratory effort related event. Those events were not causing dramatic desaturations, but they were clearly disrupting sleep architecture and straining the cardiovascular system. The PRDI told the full story that AHI alone was leaving out. The workaround I used was to pull the raw pulse oximetry and ECG traces and manually annotate the events using the standard 3 percent desaturation criterion paired with the accompanying tachycardic response. The automated scoring had been filtering those events out because the desaturation threshold was set too high on that particular run. Lowering it to 3 percent and adding a pulse rate correlation rule brought the manual count in line with the PRDI of 38. That changed the treatment recommendation from CPAP to oral appliance therapy with closer follow-up rather than dismissing the case as mild.
There are limitations worth noting upfront. PRDI is not a standalone diagnostic criterion. The American Academy of Sleep Medicine scoring manual does not include it as a primary outcome measure for establishing severity. Some automated algorithms also struggle with motion artifact, peripheral perfusion issues, or patients on certain medications that blunt heart rate variability. In those situations the PRDI can be artificially low or completely unreliable. If your patient has poor signal quality, do not trust the number. Re-run the study with a better probe placement or use a different sensor. It adds maybe twenty minutes to setup time but saves you from making a clinical decision on garbage data. Another pitfall beginners miss is confusing PRDI with PDII. PDII is the Peripheral Arterial Dilation Index, which scores flow-limiting upper airway events based on limb blood flow rather than heart rate changes. They measure different physiological phenomena and should not be treated as interchangeable. Mixing them up in a report will raise eyebrows with any board-certified sleep medicine physician who reads it. If you are looking at raw PSG data and need to understand what the report is telling you, focus on the combination of metrics rather than any single number. PRDI alongside AHI, ODI, and the respiratory disturbance index gives you a more complete picture of both respiratory disruption and its downstream physiological effects. That is where the real clinical value sits.
Get the Full Details