Professionalism in healthcare isn't about wearing a blazer over your scrubs
I worked as a nurse manager for about twelve years before moving into compliance work, and honestly, the gap between what people think professionalism means and what it actually does in a hospital is massive. You'll hear administrators talk about "professional image" and "communication skills" in orientation videos, but those things don't stop a surgeon from writing a prescription in pen at 3 AM during a code blue. What actually matters is consistency under pressure, and the people who understand that are the ones who never end up in incident reports. Here's a real example I dealt with recently. A new respiratory therapist I was supervising would give perfect, textbook answers to patients during assessments but then turn around and spend twenty minutes on her phone in the supply closet arguing with a coworker about shift swaps. She wasn't being unprofessional with patients, so she thought she was fine. She wasn't. I sat her down and walked through the fact that every single interaction in that building counts as a professional one, and patients will often piece together what they've seen across multiple touchpoints. That therapist didn't have a patient complaint against her, but she had a reputation problem among the nursing staff, and reputations in healthcare matter more than you'd think. People route around the ones they don't trust.
What Is Professionalism In Healthcare
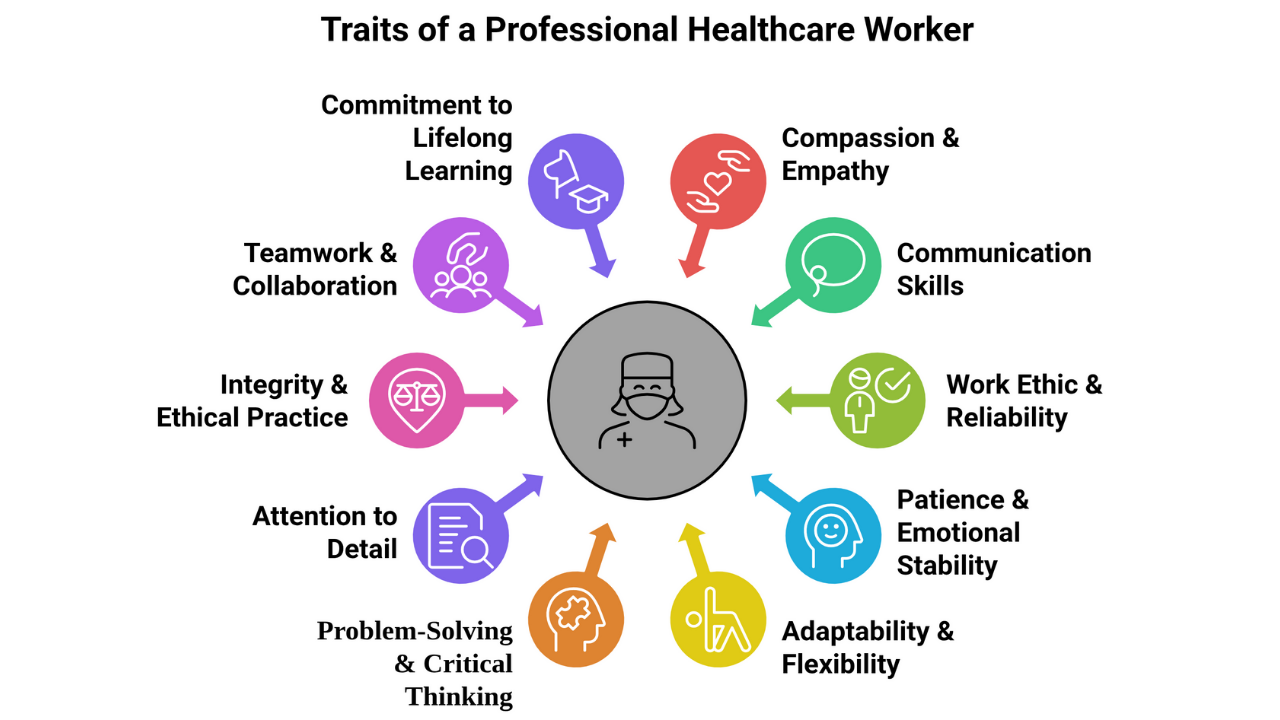
At its core, what is professionalism in healthcare, it's the consistent application of clinical competence combined with behavioral accountability across every interaction, whether anyone is watching or not. It's not a personality trait. It's a set of observable actions that can be measured, documented, and enforced. The definition sounds simple, but the execution is where most programs fail because they try to teach it as a soft skill instead of a operational requirement. The counter-intuitive part that beginners miss is that professionalism in healthcare is actually easier to enforce in some areas than others. Communication breakdowns during handoffs can be measured. Documentation timeliness can be audited. Punctuality is binary. But the stuff everyone focuses on—like "being nice"—is almost impossible to standardize and therefore almost impossible to evaluate fairly. Hospitals that build professionalism programs around measurable behaviors instead of vibe-based assessments see significantly fewer repeat incidents. I've seen turnover drop by about eighteen percent in units where we switched to behaviorally anchored rating scales instead of the old "does this person seem professional?" evaluations that everyone knew were subjective garbage. Another thing nobody warns you about: professionalism gets weaponized. I've watched managers use "professionalism" as a catch-all complaint against nurses who asked for reasonable accommodations, raised safety concerns, or simply had different communication styles. That's not professionalism enforcement. That's control disguised as policy. The distinction matters because once you've conflated compliance with conformity, you lose the ability to actually identify when someone is crossing a real line versus when they're just not performing the gendered or cultural version of professionalism that management expects. The workaround I used was to require that every professionalism complaint be tied to a specific, documented behavior with a timestamp and an impacted patient or colleague. Vague complaints went nowhere. The ones that met that bar actually got addressed, which meant we spent less time managing drama and more time fixing real problems.
The practical framework most people skip
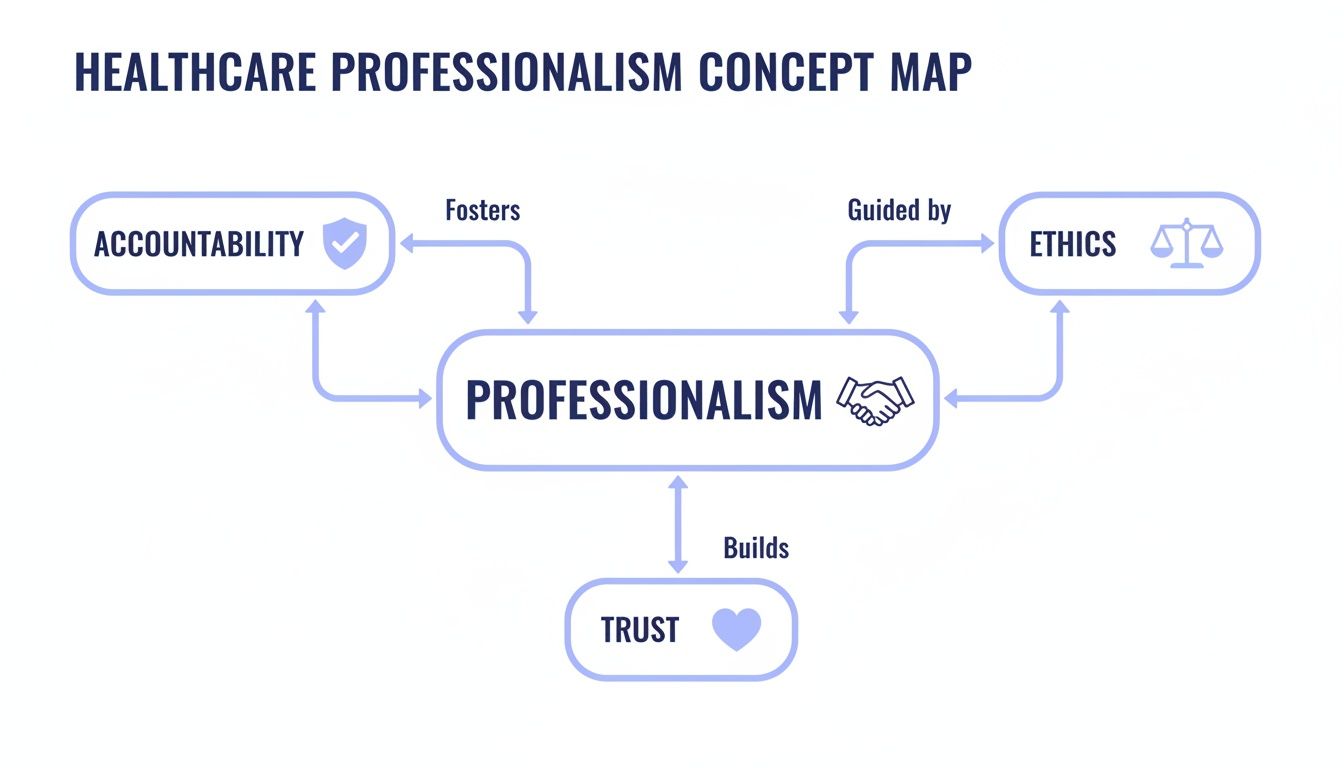
Understanding the concept is one thing. Applying it when you're exhausted, understaffed, and dealing with a family member who is yelling at you because their father has been waiting four hours for pain medication is another. That's when the framework matters. Start with the three domains that actually predict professional failure in clinical settings: reliability, boundary management, and accountability. Reliability covers showing up on time, completing your documentation, following through on commitments to colleagues, and not abandoning tasks mid-shift. Boundary management covers appropriate physical, emotional, and digital boundaries with patients and coworkers. Accountability covers admitting errors, accepting feedback without deflection, and following through on corrective actions. The domain that surprises people is accountability. Most healthcare workers think professionalism is about never making mistakes. That's wrong. It's about how you handle mistakes when they happen—which they will. I once had a physician who was brilliant clinically but had a chronic pattern of blaming nursing staff when his orders caused adverse events. We couldn't fire him for being rude. We could however document the pattern, require peer review of his near-miss reports, and eventually remove his privileges when the data showed a statistically significant correlation between his order entries and medication errors. That's professionalism enforcement that actually works because it's data-driven, not personality-driven.
Get the Full Details

For the people reading this who are trying to build or improve professionalism standards in their own departments, here's what I'd actually recommend based on what I've seen succeed and what I've seen waste money. Don't do the annual sensitivity training module and call it a program. That generates zero behavioral change and everyone knows it. Instead, implement brief daily huddles where team members flag one professionalism concern from the previous shift in concrete terms. Ten minutes, structured format, no debate. Within sixty days, the department usually has a clear picture of where the real friction points are. The alternative—waiting for a formal grievance or patient complaint—is how you end up in legal proceedings. There's a limitation to all of this that deserves to be stated plainly: professionalism frameworks don't fix bad systems. If your staffing ratios are impossible, your documentation requirements are contradictory, and your leadership is absent, no amount of professionalism training will make your workplace function. I've seen hospitals spend sixty thousand dollars a year on professionalism seminars while their nurses were working 14-hour shifts without a bathroom break. The seminars are fine as supplementary support. They are not a substitute for basic operational competence. The bottleneck is usually structural, and pretending otherwise just makes professionals feel guilty for problems they didn't create. If you're looking for a concrete tool to start with, the behaviorally anchored rating scale I mentioned earlier is publicly available in the nursing literature and can be adapted for any clinical role. The American Association of Critical-Care Nurses has a published version that's been peer-reviewed and used in over two hundred hospitals. It's free to access through their website if you have a professional membership. For non-nursing roles, the framework is the same—define the behavior, anchor it to specific examples at each performance level, and train evaluators together until their inter-rater reliability is above 0.80. Anything below that threshold means the instrument is measuring evaluator mood, not employee performance.
The bottom line is that professionalism in healthcare is operational, not aspirational. Treat it like one and the metrics improve. Treat it like a vibe and you'll spend years wondering why your retention numbers look the way they do.