So You Keep Running Into PTCs
If you're working with sequencing data or reading about nonsense-mediated decay, you've definitely seen PTC mentioned. It stands for premature termination codon. That's the formal name for a stop signal that shows up way too early in a coding sequence. Instead of producing a full-length protein, the ribosome stalls and quits at the wrong place. The resulting transcript gets chewed up by the cell's quality control machinery. Sometimes it doesn't, and you end up with a truncated protein that causes more trouble than it prevents. The term shows up in two different contexts, which is where most confusion starts. In molecular genetics, a PTC is a premature stop codon introduced by mutation or splicing error. In population genetics, PTC can also refer to phenylthiocarbamide, the bitter-tasting compound used in the classic TAS2R38 taste receptor studies. They share a name. They don't share much else. Most people asking about PTC in a biology research context are talking about the stop codon issue, so I'll go there first and circle back to the taste thing at the end. The three stop codons are UAA, UAG, and UGA. When any of them appear outside the proper 3' untranslated region because of a frameshift, nonsense mutation, or exon skipping event, you have a PTC. The cell detects these through the exon junction complex, which loads onto mRNAs during splicing. When ribosomes stall upstream of an exon junction complex that hasn't been removed yet, the NMD pathway triggers and degrades that transcript. That's the whole mechanism in a sentence.
In practice, this means that not every nonsense mutation creates the same problem. A mutation in the last exon, far from the terminal junction complex, might escape NMD. The protein gets made. It's shorter than it should be, but at least it exists. I spent two weeks once troubleshooting why a CRISPR knock-in with what I thought was a clean nonsense mutation still produced detectable protein at roughly thirty percent of wild-type levels. The culprit was an alternative splice site being activated downstream, effectively bypassing the PTC through partial exon retention. The mRNA wasn't degraded by NMD because the remaining transcript structure looked just normal enough to slip past. I had to redesign the guide RNA and add a second silent mutation nearby to lock down the splice site. Took three weeks total instead of three days. For anyone doing therapeutic work with read-through compounds like ataluren, this is the exact problem you run into. The drug allows ribosomes to occasionally ignore stop codons, so it can suppress PTCs. But it's not selective. It also ignores normal stop codons sometimes, which means full-length proteins get made past their intended end. You get C-terminal extensions on half your protein population. It works, but the side effects pile up quickly if you're treating a systemic condition rather than a localized tissue. I've seen doses scaled down to a quarter of the published effective range just to keep the read-through noise tolerable in vivo. Here's the counter-intuitive part that most papers don't emphasize: PTC position relative to the stop codon matters less than most people assume when it comes to NMD efficiency. The standard rule is that any PTC more than fifty to fifty-five nucleotides upstream of the final exon-exon junction triggers degradation. But in reality, the distance threshold varies wildly depending on cell type, on the sequence context around the PTC, and on how many introns remain downstream. A PTC five hundred nucleotides upstream of the final junction might be fine in one cell line and completely destroyed in another. I learned this the hard way when comparing NMD sensitivity across HEK293, HeLa, and primary fibroblasts. The same PTC in the same construct showed three different levels of residual transcript between those three cell types.
Another thing beginners miss is the difference between a true PTC and a regular stop codon that happens to look premature. If you're scanning sequences computationally, you'll flag any in-frame stop that appears before the annotated CDS end. But the annotated CDS end is often wrong, especially in older genome builds. I spent a day once catching what looked like a pathogenic PTC in a published variant database. The variant was actually in an alternative isoform that terminated earlier. The gene model was incomplete. The stop codon was normal for that isoform. Always check the isoform, not just the gene.
Get the Full Details

Practical identification and handling
When you're hunting for PTCs in your own data, the first step is usually a variant call from DNA sequencing followed by transcript-level analysis. Don't skip the RNA part. DNA tells you what mutation exists. RNA tells you whether it's being transcribed, spliced correctly, or destroyed by NMD. I run RT-qPCR with primers flanking the suspected PTC alongside a primer pair in the terminal exon region. If the transcript is gone or significantly reduced compared to the control, NMD is likely active. If it's still there at normal levels, the PTC is either in the last exon or downstream of it, or the NMD pathway isn't engaging for some reason. There's a cheap workaround for confirming NMD involvement without buying expensive assays. Treat your cells with cycloheximide or emetine before harvesting RNA. These are translational inhibitors, and they effectively shut down NMD because NMD is coupled to translation. If your truncated transcript suddenly increases in abundance after treatment, that's your answer. NMD was degrading it. This test runs overnight and costs basically nothing beyond the drug. The trade-off is that cycloheximide has cellular toxicity, so you can only treat for a few hours before the cells start falling apart. I usually do four-hour treatments and compare to an untreated control run in parallel. For functional studies, you want to know what the truncated protein actually does. The mRNA level is only half the story. A PTC might trigger NMD and reduce transcript abundance, but if NMD is leaky, the protein that does get made could be dominant-negative. It might still bind its interaction partners but lack the C-terminal domain needed for function. Or it might be unstable and aggregate. I ran a western blot once on a cell line I thought had clean NMD-mediated degradation of a PTC-containing transcript. The antibody I was using targeted an N-terminal epitope, so it detected the truncated protein fine. The band was there at roughly sixty kilodaltons instead of the expected one hundred and ten. The protein wasn't being made. It was being made and then rapidly degraded by the proteasome. Adding MG132 stabilized it. NMD wasn't the only quality control mechanism at play.
Therapeutic contexts and limitations
PTC suppression therapy is real but narrow. Ataluren is approved in some countries for Duchenne muscular dystrophy caused by nonsense mutations in the DMD gene. That's probably the most well-known application. The response rate is nowhere near one hundred percent. Patients whose PTCs are in certain sequence contexts respond better. UGA stop codons tend to respond worse than UAA or UAG, and the surrounding nucleotide sequence heavily influences read-through efficiency. You can't predict which patients will respond without testing, and even then, the response is dose-dependent and temporary. You keep taking the drug, the effect persists. You stop, the disease phenotype returns because the underlying mutation is still there. The bigger limitation nobody talks about is tissue distribution. Ataluren has poor bioavailability. The oral formulations require high milligram doses to achieve therapeutic levels in muscle. That increases the off-target read-through effect I mentioned earlier. You're getting read-through in other genes too, not just the target one. The clinical trials showed modest functional improvement but also elevated liver enzymes in a meaningful subset of patients. It works, but it's not a clean solution by any measure.
The taste genetics angle
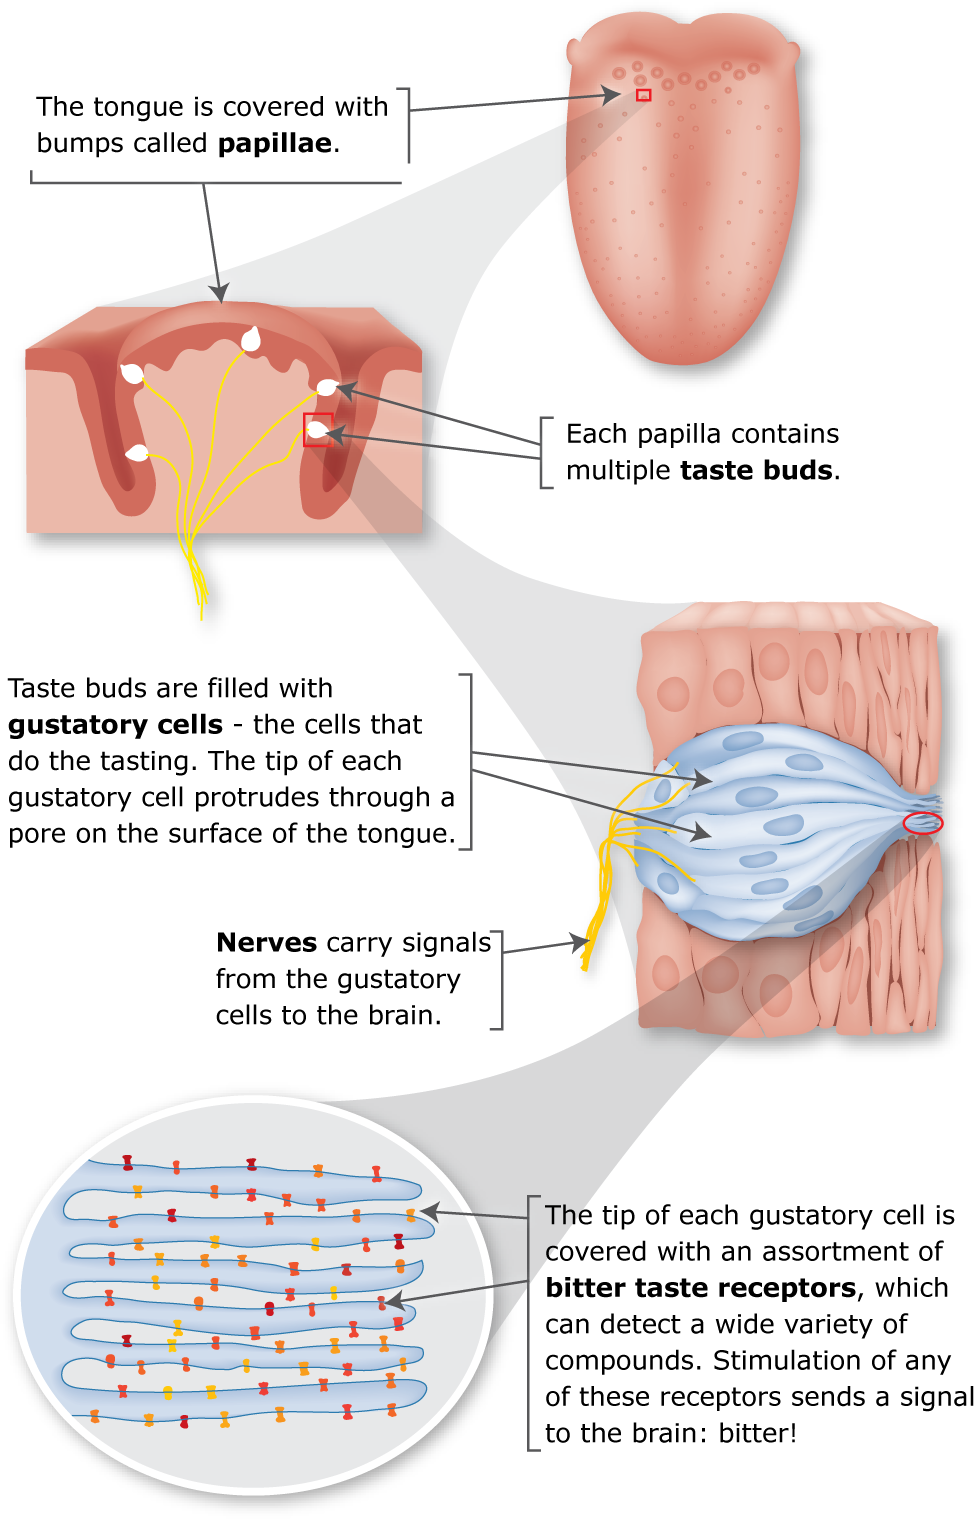
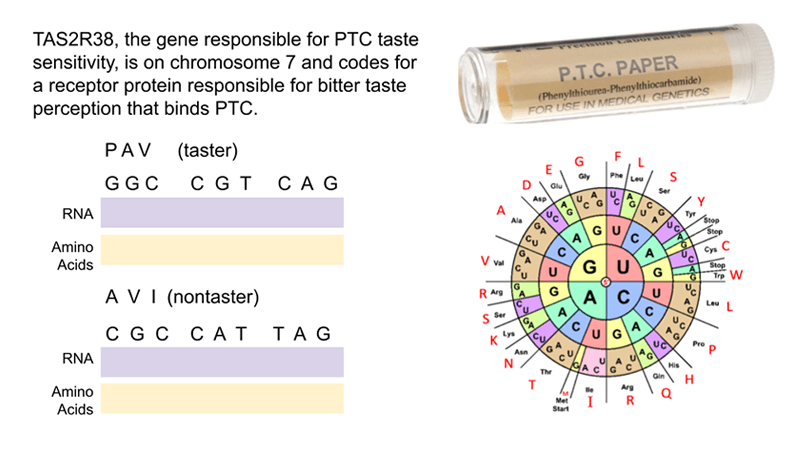
If you came here looking for the phenylthiocarbamide version of PTC, it's a completely different topic. TAS2R38 has three common missense variants that create three haplotypes: PAV, which is the bitter-taster allele, and AVI, which is the non-taster. People homozygous for AVI can't taste PTC at all. Heterozygotes usually detect some bitterness. The population frequency varies geographically, which makes it useful for basic population genetics teaching but not terribly useful for anything requiring high precision. The heritability is high, roughly seventy to eighty percent in most studies, but environment and age can modulate perception. My grandmother stopped tasting it entirely in her seventies despite being a strong taster her whole life. Genetics isn't destiny even for something this straightforward. The original PTC test strips are still sold by a handful of suppliers. You put one on your tongue, wait thirty seconds, and rate the bitterness from one to ten. That's literally the entire protocol. It's been done with far more ceremony than it deserves, but it started that way. The real scientific value came from linking the phenotype to the genotype, which happened in the late nineties when the TAS2R38 gene was cloned.

Bottom line
PTC in biology most often refers to premature termination codons in mRNA. They matter because they determine whether a mutant allele produces protein, produces no protein, or produces a potentially harmful truncated product. The biological outcome depends on position, splice context, cell type, and NMD efficiency. If you're working with them experimentally, sequence the cDNA, not just the genomic DNA, and test for NMD involvement before drawing conclusions about protein expression. The taste chemistry meaning is real but occupies a different corner of the field entirely. Both are valid. Just make sure you know which one you're actually dealing with before you start designing experiments or reading papers.