
Radiology Isn't Just Taking Pictures
Most people think radiologic science means standing behind a leaded glass window and pushing a button. It's closer to applied physics, anatomy, and patient management happening simultaneously, often under time pressure. The field covers how electromagnetic radiation and sound waves interact with tissue, how we capture that interaction into a diagnostic image, and how we keep everyone in the room from absorbing more dose than necessary. I've spent years watching technologists get stuck on protocol selection while the exam clock ticks down. The difference between a decent study and a non-diagnostic one usually comes down to whether you understood the physics behind the sequence rather than just memorizing button positions.
What Is Radiologic Science
At its core, radiologic science is the systematic study of how ionizing and non-ionizing radiation interacts with biological tissue to produce diagnostic information, along with the principles needed to generate that information safely and reproducibly. It spans several disciplines—general radiography, computed tomography, magnetic resonance imaging, fluoroscopy, nuclear medicine, and ultrasound—each built on different physical principles but sharing the same goal: make pathology visible while minimizing risk. The science portion matters more than the operating portion. A technologist who only knows button presses will struggle when the automatic exposure control behaves unexpectedly or when a patient's body habitus falls outside standard protocol ranges. Understanding why the AEC fires when it fires, and what happens if you block the ionization chambers with a lead drape, separates someone who can troubleshoot from someone who calls a repair tech and goes home.
How It Actually Works Behind the Scenes
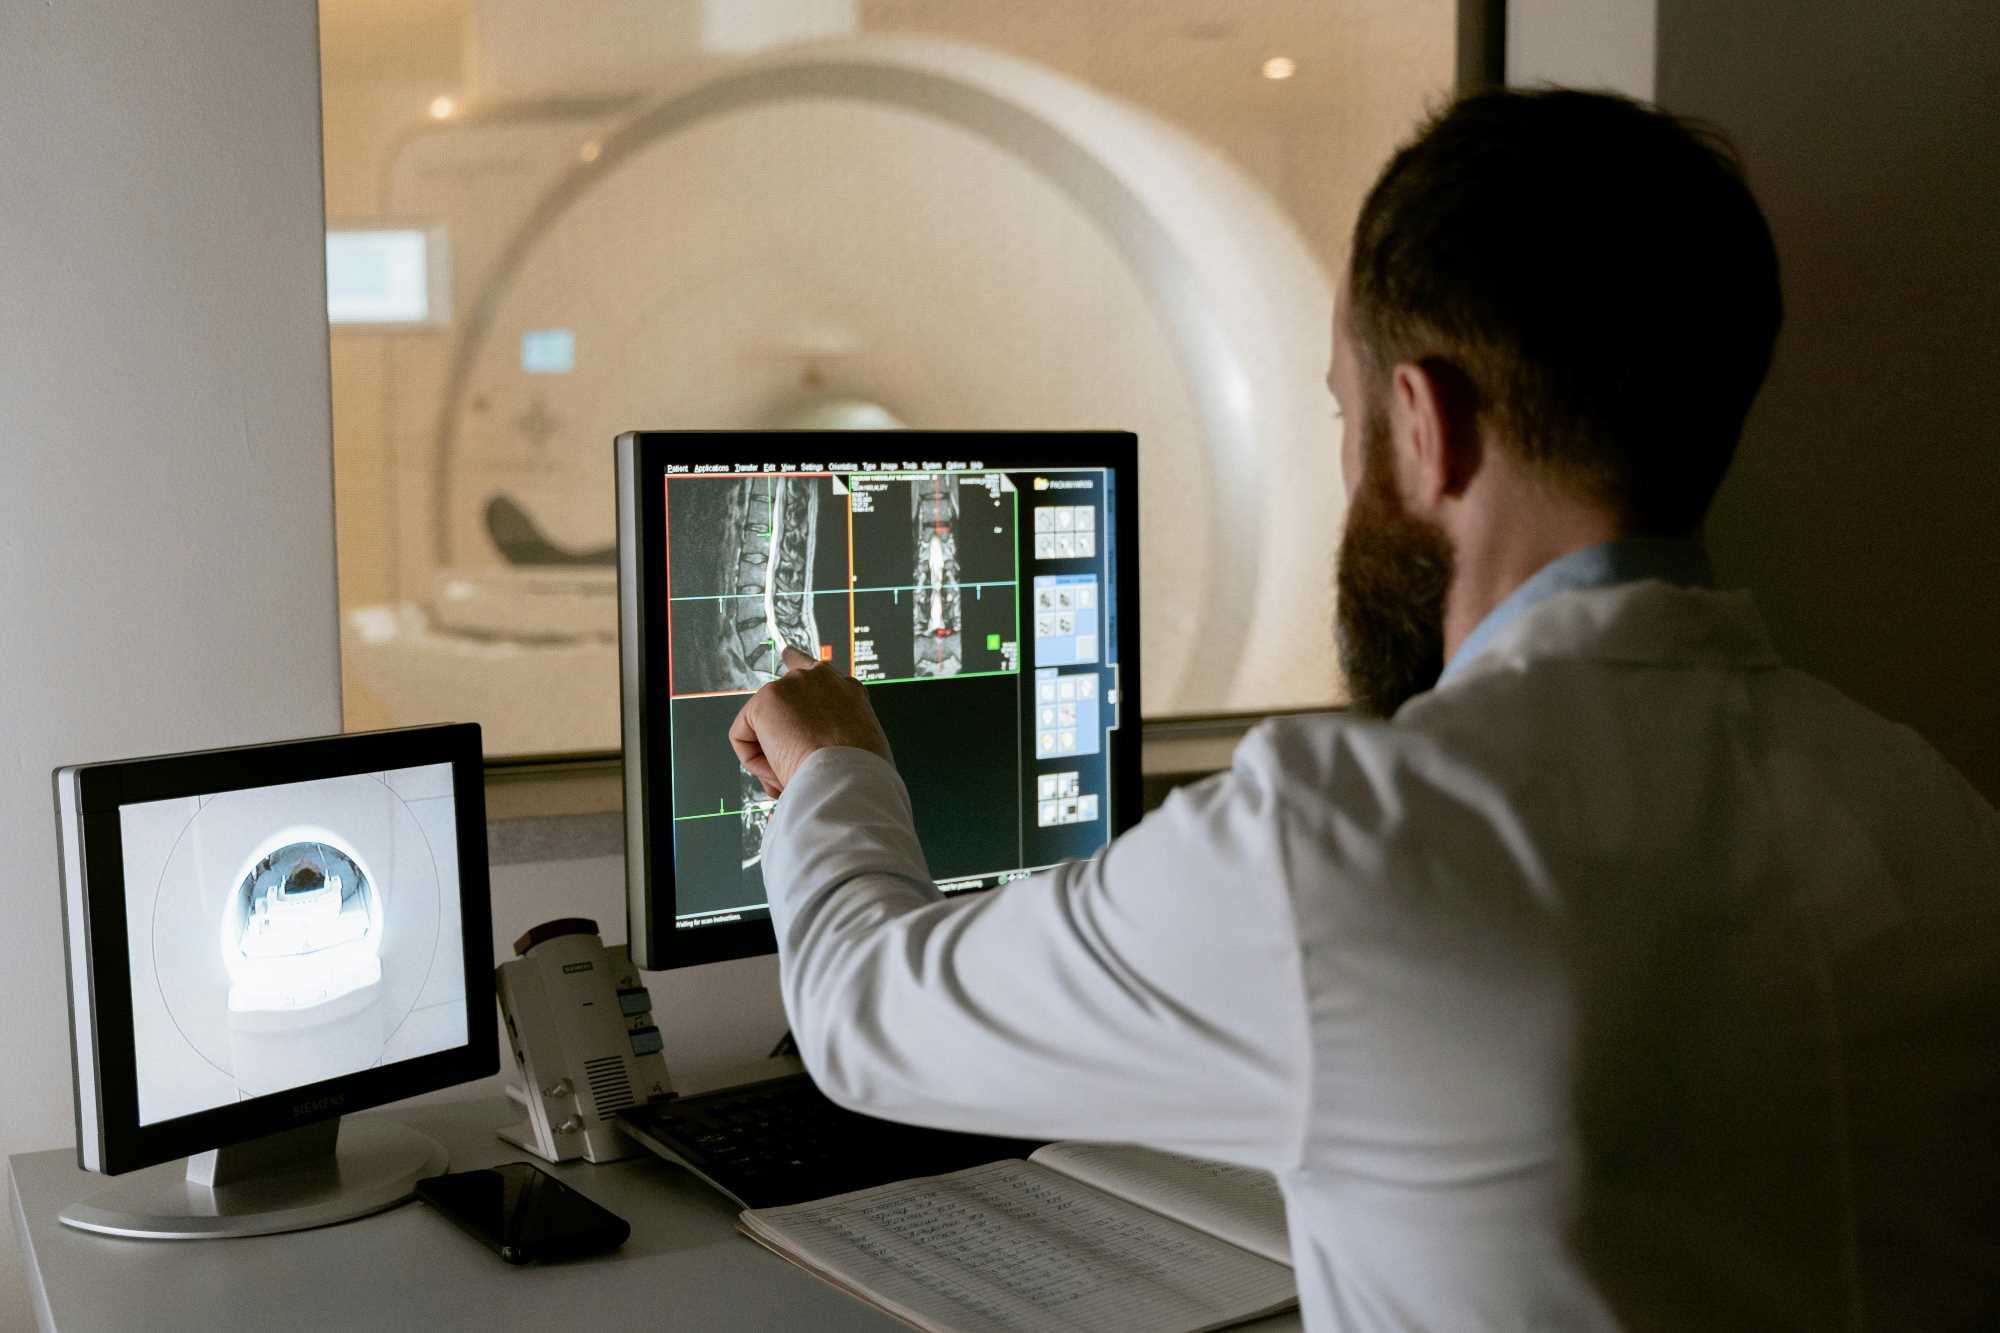
Digital radiography relies on flat-panel detectors that convert x-ray photons into electrical signals through either indirect conversion (scintillator layer turns x-rays into light, photodiodes capture the light) or direct conversion (photoconductors like amorphous selenium convert x-rays directly to charge). The difference shows up in detective quantum efficiency, which is basically how much of the incoming signal actually makes it into the final image versus getting lost as noise. CT adds rotation and reconstruction algorithms to the mix. The raw data is a series of projection measurements taken at hundreds of angles, and the computer solves an inverse problem to map those projections back into cross-sectional voxels. Hounsfield units standardize the resulting grayscale so that water is always zero and air is always negative one thousand, regardless of which manufacturer built the scanner or what tube current was used. MRI operates on an entirely different physics branch involving nuclear magnetic resonance. Hydrogen protons align with a strong static magnetic field, get perturbed by radiofrequency pulses, and emit signals as they relax back into equilibrium. The T1 and T2 relaxation times of different tissues create contrast, and pulse sequence design determines which contrast mechanism dominates the final image.
Get the Full Details
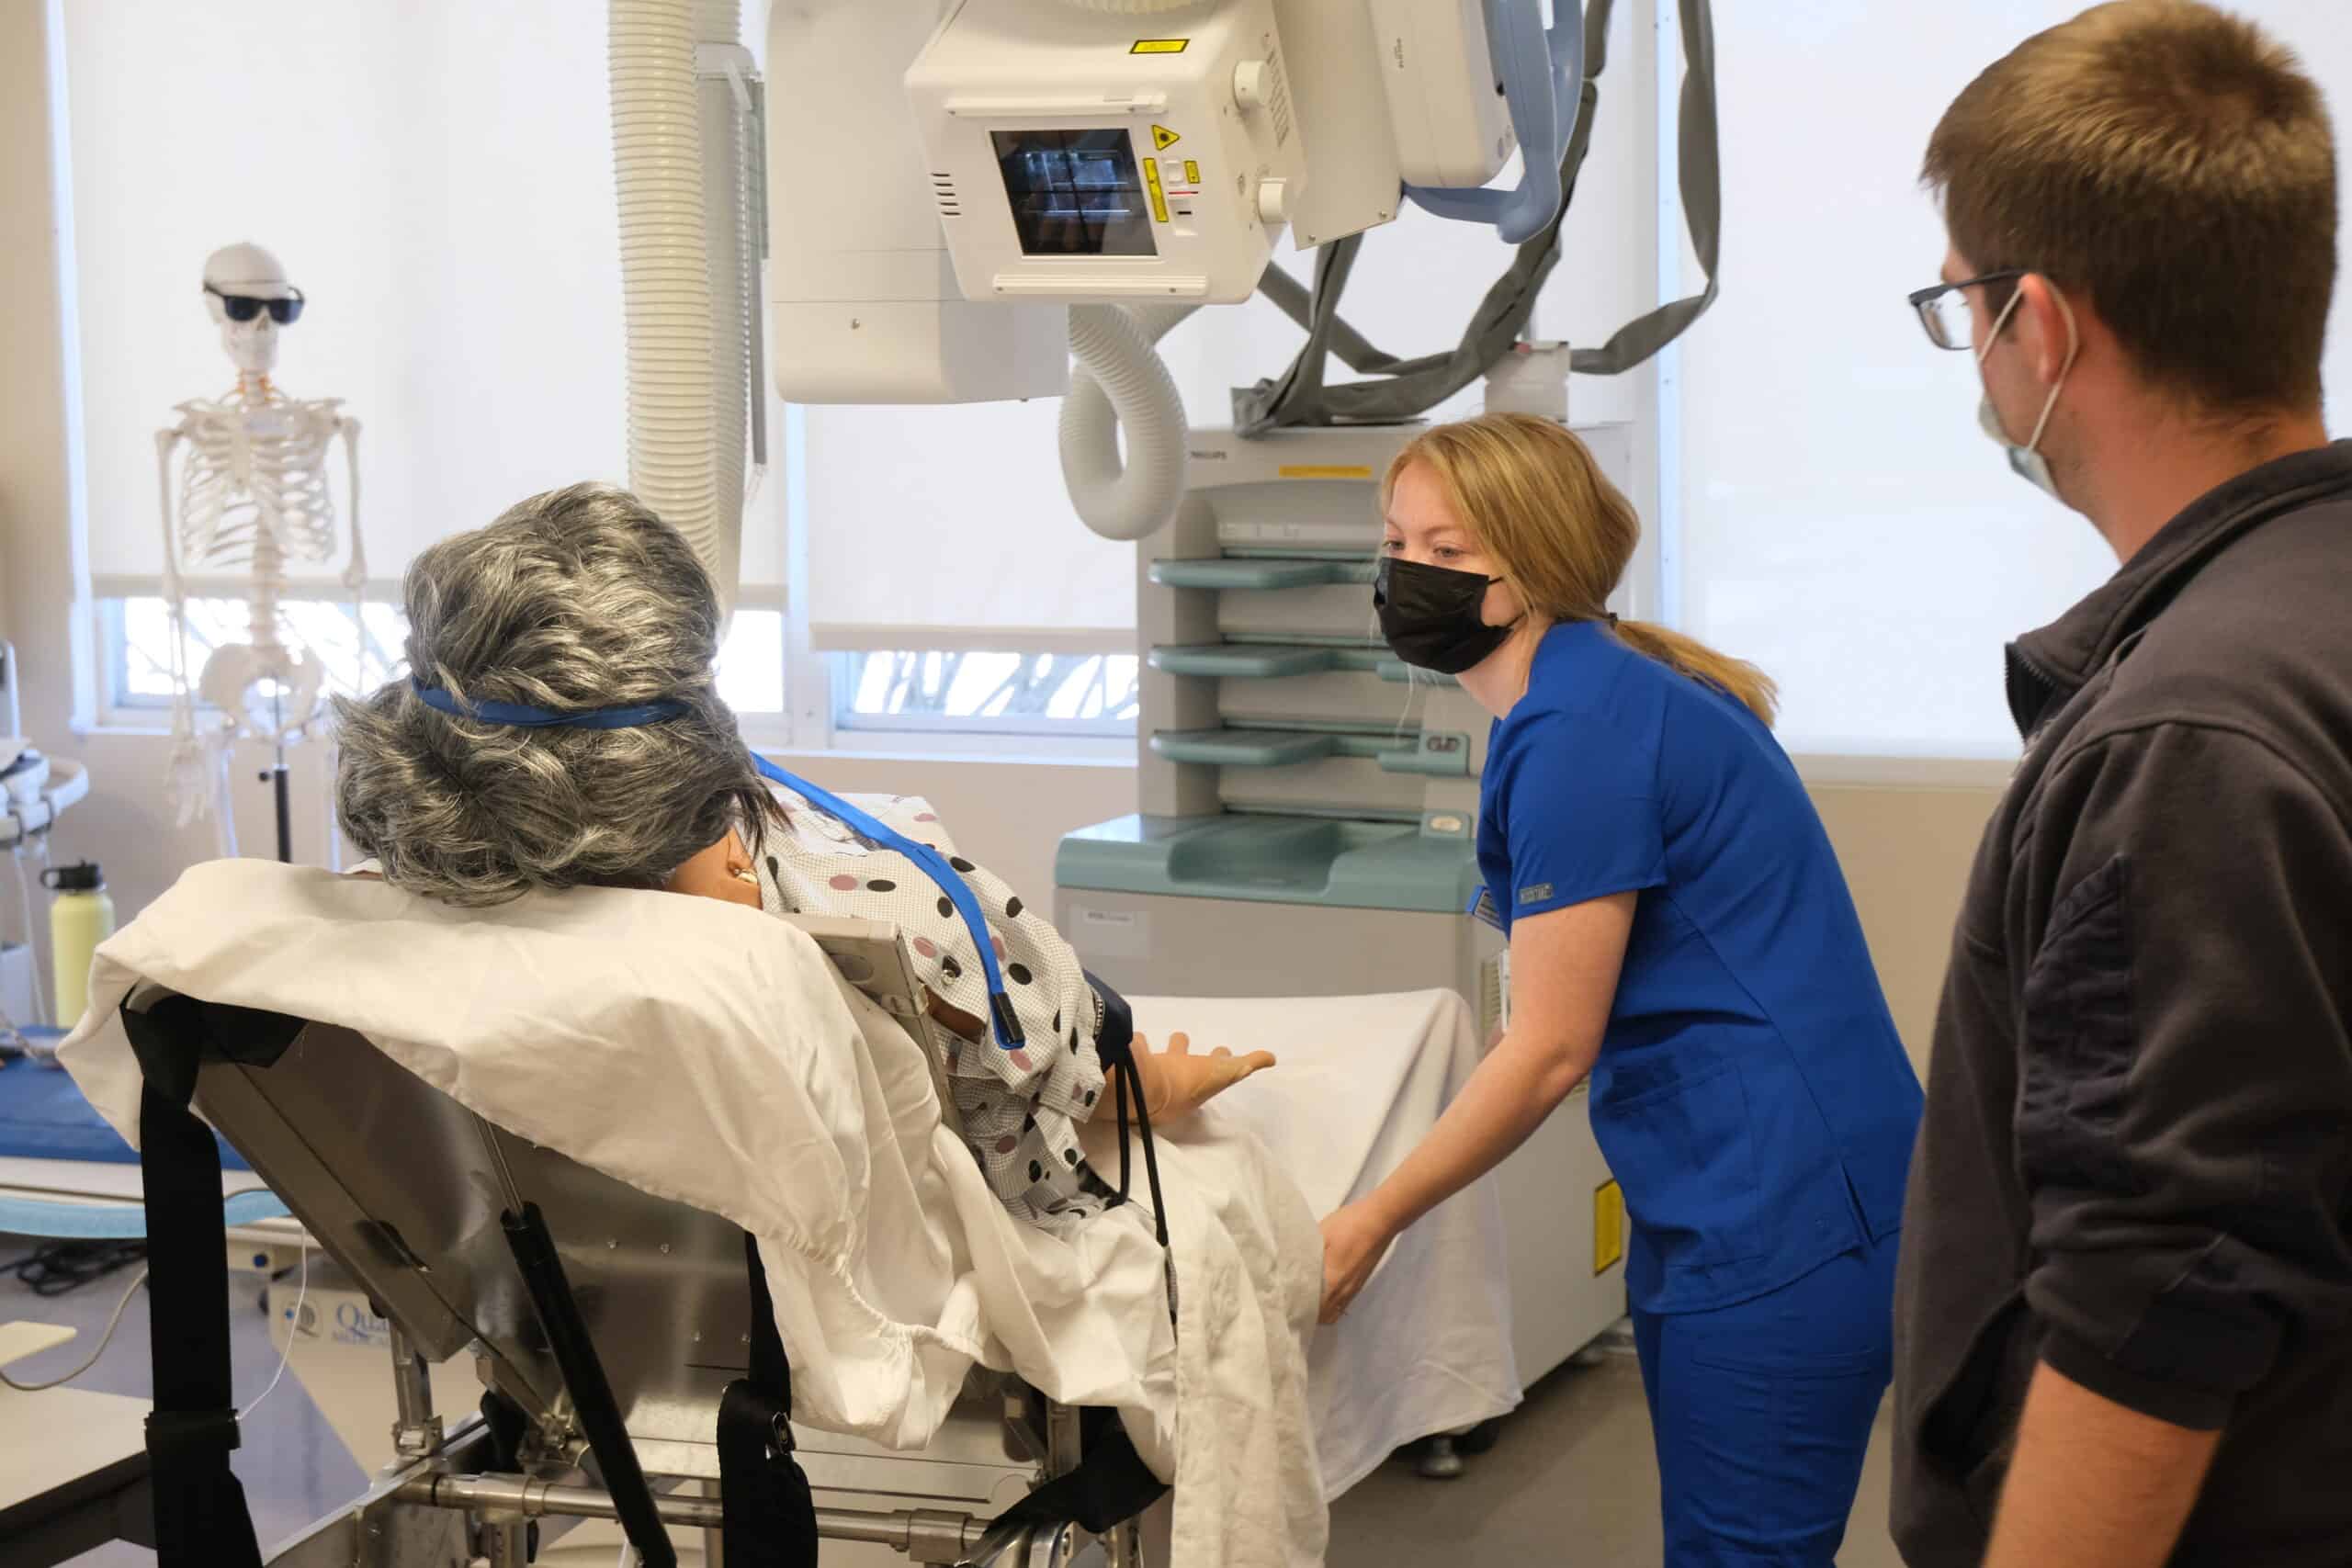
Ultrasound uses piezoelectric transducers that generate short acoustic pulses and measure echo return times. Unlike x-ray based modalities, ultrasound doesn't use ionizing radiation at all, which is why it's the default for obstetric imaging and pediatric abdominal exams. The tradeoff is that acoustic impedance mismatches at bone and air interfaces create shadowing artifacts that can obscure anatomy entirely.
Real-World Problems You Won't Find in a Textbook
Last year I was reviewing a chest series from a portable unit in a satellite clinic, and every image showed a consistent vertical band of increased density running through the mid-lung zones. The obvious assumption was pulmonary pathology, so I called the referring physician to discuss possible consolidations. Then I noticed the band tracked perfectly across every exposure regardless of patient positioning or technique settings. It wasn't the patient. It was a degraded fiber optic taper in the image intensifier of the old fluoroscopy unit the portable was borrowing from. Replaced the taper assembly and the artifact disappeared. The lesson here is that before you ever suspect patient pathology on a repeatedly abnormal study, you check whether the equipment is the common variable. Another thing people get wrong about CT is thinking higher kVp always means better image quality. At 140 kVp with dual-energy capability you do get better penetration through large patients and less beam hardening artifact around the shoulder girdle, but you also lose soft-tissue contrast significantly compared to 100 kVp. The counter-intuitive part is that for obese patients with suspected liver metastases, dropping the kVp to 80 on a modern photon-counting detector actually improves lesion conspicuity because the photoelectric effect scales inversely with energy cubed and those detectors have enough sensitivity to handle the noise. Traditional tube-based systems would just give you a noisy mess at that setting. Equipment generation matters more than protocol convention.
The Parts Nobody Talks About Enough
Quality assurance isn't a quarterly checkbox exercise. Daily QA on a radiography unit involves checking kVp accuracy within five percent, timer accuracy within ten percent, and automatic exposure control consistency across phantom exposures. Weekly checks include spatial resolution with a line pair gauge and low-contrast detectability. If you skip these, you won't notice the drift until a radiologist complains about a study six months later and you're trying to explain why your system's modulation transfer function has degraded by twelve percent. Radiation protection follows the same logic but applied to humans rather than machines. ALARA—As Low As Reasonably Achievable—sounds like a slogan until you're the one deciding whether to repeat an exposure because the collimation was off by two centimeters. Every unnecessary repeat adds cumulative dose to both patient and staff. Lead aprons don't protect against scatter from every angle; they leave the thyroid and gonads exposed unless you're wearing matching thyroid shields and using appropriate positioning. I've seen technologists stand behind aprons that weren't properly stored and develop microfractures in the lead composite, reducing attenuation from 0.5 mm Pb equivalent down to effectively nothing at diagnostic energies. The dosimetry records don't lie, but they require actual measurement rather than estimation. Put your personal dose badge at the correct position under any protective apron if you're wearing one, not clipped to the outside where it overestimates your true occupational exposure. OSHA and state radiation control programs audit these records during inspections, and discrepancies between estimated and measured doses can trigger unnecessary corrective actions or worse, missed overexposures that never get investigated.
Where This Field Falls Short
Radiologic science has genuine limitations that get glossed over in promotional material. CT dose remains a real concern for serial imaging studies. A single abdomen-pelvis CT with contrast delivers roughly eight to ten millisieverts, which is equivalent to about three years of natural background radiation. Repeat scans for conditions like Crohn's disease or recurrent kidney stones accumulate quickly, and there's no threshold below which radiation risk disappears entirely according to the linear no-threshold model that most regulatory bodies still use. MRI is expensive and contraindicated for anyone with certain metallic implants, pacemakers, or cochlear implants. The field also has resolution limits for small structure visualization that x-ray based modalities simply exceed. A dedicated bone density scan with quantitative CT provides volumetric BMD measurements that DXA cannot match, and it's faster than MRI for musculoskeletal detail in many weight-bearing joints. Automated dose monitoring software exists but often flags normal examinations as outliers because the reference doses haven't been updated for newer scanner models or pediatric protocols. Blindly following the software alerts wastes technologist time investigating false positives while genuine problems slip through. The references are dated versions of DLP and CTDIvol benchmarks that don't account for iterative reconstruction reducing dose requirements by forty to sixty percent compared to filtered back projection.
The profession also faces a staffing shortage that's worse in rural and community hospitals. The AAPM and ACR report that over thirty percent of community hospitals struggle to maintain 24/7 radiologic technologist coverage. When you're the only credentialed person on shift, there's no one to consult about an unusual finding or validate a non-standard protocol before you commit to it. That isolation affects both image quality and safety culture.
Getting Into It
The standard pathway in the United States involves completing an accredited radiologic science program, passing the ARRT credentialing examination, and maintaining continuing education credits for relicensure. Several states require additional licensing beyond the national exam. The curriculum covers radiation physics, patient care, image evaluation, radiation biology, and clinical practicum hours that typically total around two thousand across multiple modalities. After the initial credential most technologists pursue additional certifications in CT, MRI, mammography, or vascular intervention. Each requires documented clinical experience hours and a separate examination. The time investment is real but the scope of practice expands considerably with each credential, which matters in facilities where cross-training allowances determine scheduling flexibility. If you're evaluating programs, check accreditation status with JRCERT rather than assuming regional accreditation covers radiologic science specifically. A regionally accredited college doesn't guarantee the program meets the technical standards radiation safety committees expect from graduate hiring managers. I've seen resumes from graduates of unaccredited programs get filtered out at major medical centers regardless of GPA or clinical performance.



