REBT in Practice
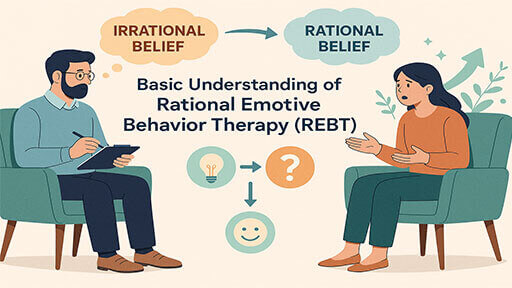
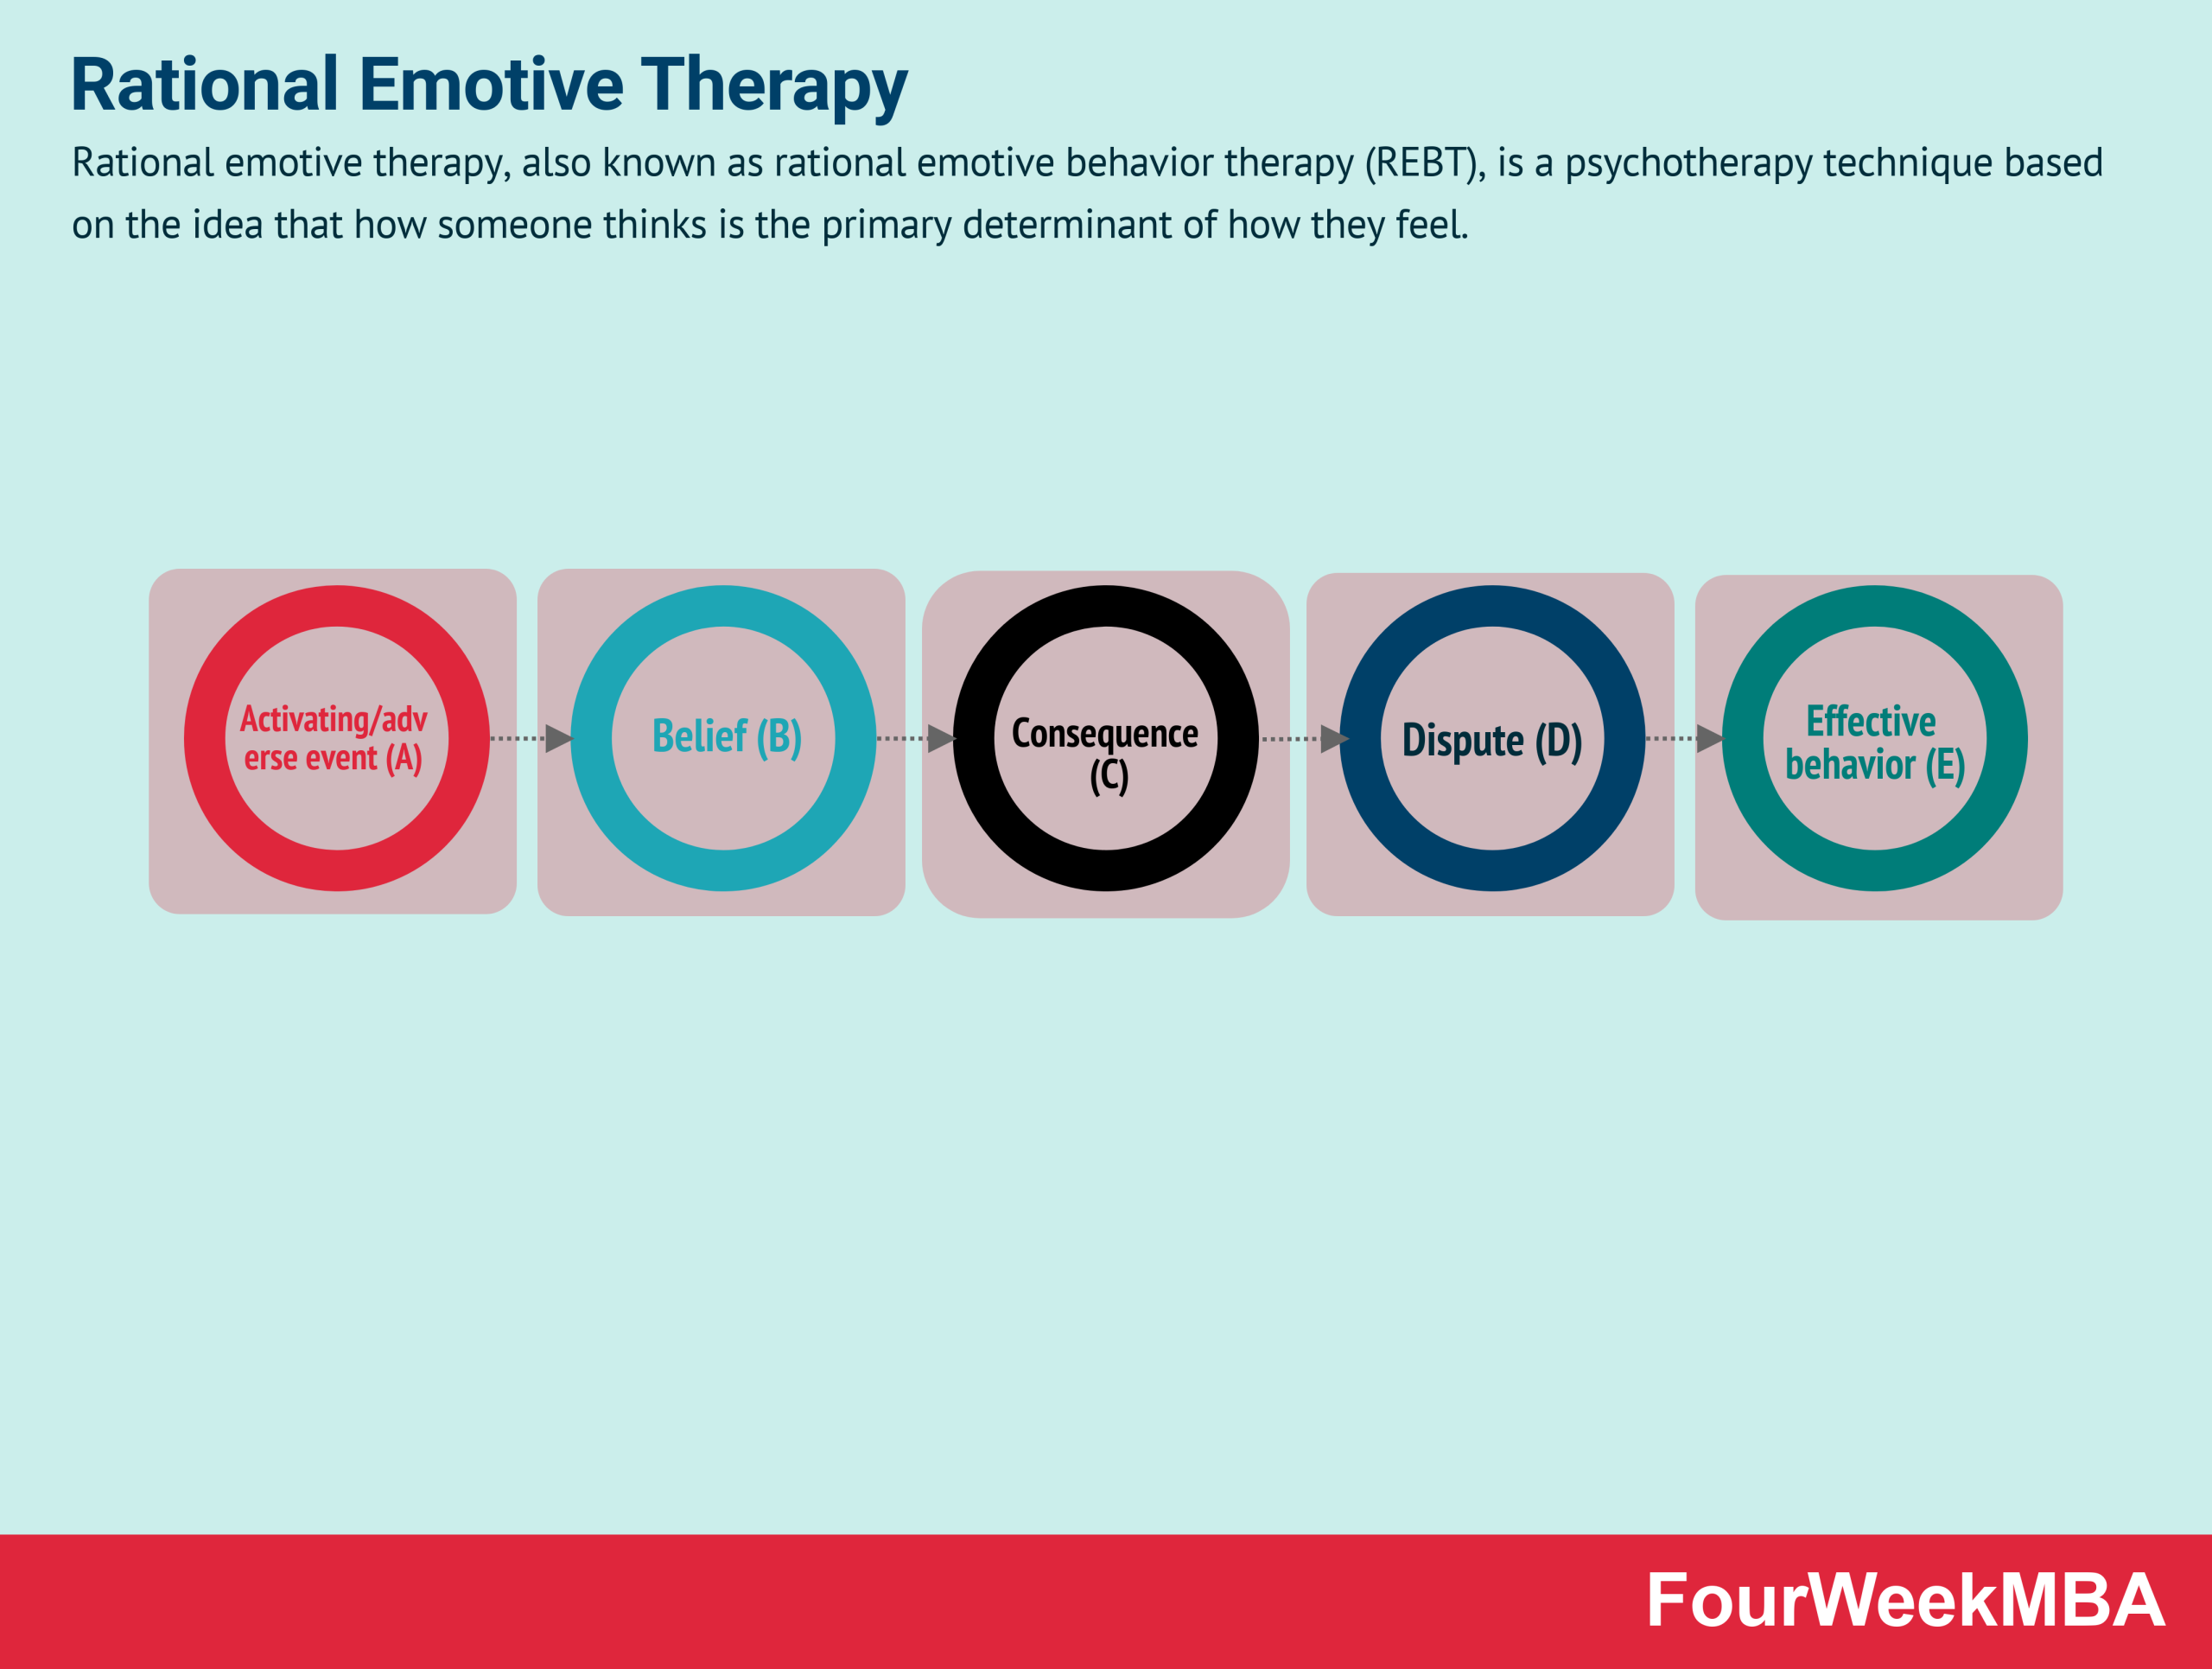
Rational Emotive Behavior Therapy is a form of cognitive-behavioral treatment developed by Albert Ellis in the 1950s. It operates on the premise that emotional distress comes not from events themselves but from the irrational beliefs people hold about those events. The therapy uses the ABC model—Activating event, Belief, Consequence—to trace how someone's interpretation of a situation leads to their emotional and behavioral response. The therapist then works to dispute (D) those irrational beliefs and develop new, more rational (E) ways of thinking. I've worked enough clients who came in convinced their anxiety was caused directly by a person or circumstance, only to find the real lever was a self-reinforcing belief loop they hadn't even noticed. That's the core of it. The therapist doesn't try to change the external world for the client. They challenge the belief system attached to the world.
What Is Rational Emotive Behavior Therapy Used To Treat
REBT is most commonly applied to anxiety disorders, depression, anger management issues, and obsessive-compulsive tendencies. It also shows up in addiction recovery work, though usually alongside other modalities rather than as a standalone protocol. The technique can be adapted for performance-related anxiety in professional and athletic contexts too. I encountered a case where a client came in with what looked like classic panic disorder—sudden episodes of intense dread, heart palpitations, avoidance behavior. After several sessions, I realized the panic wasn't tied to a specific phobia or trigger pattern. It was driven by a core belief: "If I'm not in control of every outcome, something catastrophic will happen." That's not a typical panic presentation. Standard exposure therapy wasn't working because we weren't addressing the underlying absolutist belief. We shifted to disputation techniques focused on that specific cognition, and the panic frequency dropped significantly over six weeks. I wouldn't have made that pivot without recognizing the REBT framework at play.
How It Actually Works in Sessions
The therapist identifies irrational beliefs and then actively challenges them through Socratic questioning, behavioral experiments, and sometimes homework assignments. Clients are asked to catch themselves using absolute language—"I must," "I should," "It's terrible"—and replace it with preferential language. The shift from "I have to succeed at this presentation" to "I would prefer to succeed, but I don't have to, and I can handle it if I don't" sounds simple but it disrupts the emotional cascade. One thing beginners miss is that the disputation phase has to be fairly confrontational. Ellis himself was known for being direct, almost aggressive in challenging client beliefs. That approach isn't for every therapist or every client, but it's worth noting because gentler cognitive restructuring alone often doesn't break through deeply held irrational beliefs. The intensity of the disputation matters. Another common pitfall is confusing REBT with standard CBT. The distinction is subtle but important. REBT specifically targets absolutist and demanding beliefs. Standard CBT is broader and may not zero in on the "musturbation" pattern that Ellis described. If a therapist is using CBT techniques without specifically challenging irrational demands, they're not doing full REBT.
Get the Full Details

Limitations and Where It Falls Short
REBT requires a certain level of cognitive functioning. Clients with significant intellectual disabilities, active psychosis, or severe personality disorders may not engage effectively with the disputation model. The therapy also depends on the client's willingness to do homework and practice the cognitive restructuring between sessions. Without that follow-through, the session content rarely transfers into real-world behavior change. Sometimes it can come across as dismissive to clients who genuinely feel their distress is being minimized by the "just change your thoughts" framing. That's a real risk, especially early in treatment before the therapeutic alliance is solid. In those cases, pairing REBT with more supportive, validation-based approaches from other modalities tends to work better than sticking rigidly to one framework. For trauma-related presentations, REBT alone is generally insufficient. Eye Movement Desensitization and Reprocessing or other trauma-specific interventions tend to produce better outcomes when PTSD or complex trauma is the primary concern. REBT can support that work by addressing secondary cognitive distortions, but it shouldn't be the first tool pulled out for trauma cases.