Where The Numbers Actually Come From
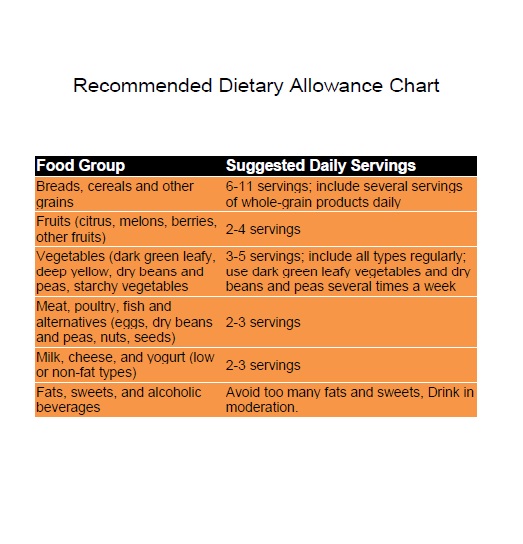
The Recommended Dietary Allowance isn't pulled from thin air. It's calculated by setting the Estimated Average Requirement (EAR) at the point where half the population gets enough of a nutrient, then adding two standard deviations to that value. The result covers roughly 97 to 98 percent of healthy people. That's it. Two sigma above the median. Most people reading a supplement label have no idea what that arithmetic represents, and it shows in how they interpret the numbers. I spent years sitting across from dietitians who treated the RDA like a daily target rather than a safety floor. The difference matters more than you'd think. If you're working with clinical populations, pregnant athletes, or people recovering from surgery, the standard RDA can leave real gaps. You need to adjust upward, and nobody who printed the USDA chart will tell you that.
What Is Recommended Dietary Allowance Rda
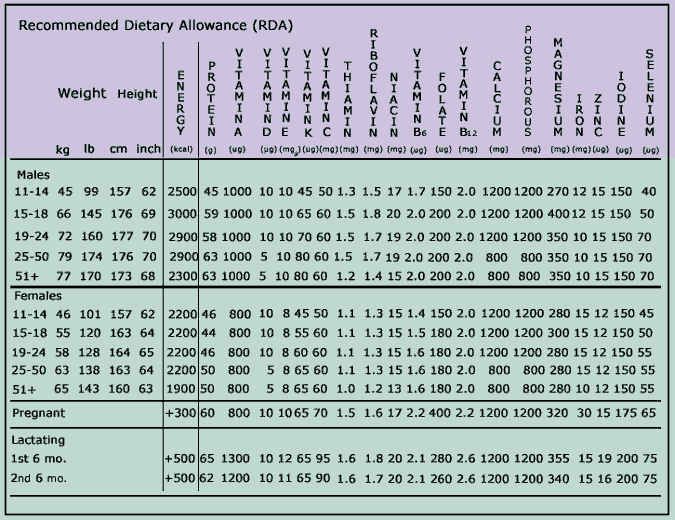
It's a specific term in the Dietary Reference Intake framework maintained jointly by the National Academies of Sciences, Engineering, and Medicine and Health Canada. The DRI umbrella contains four distinct values: the Estimated Average Requirement, the Recommended Dietary Allowance, the Adequate Intake, and the Tolerable Upper Intake Level. Confusing them is the most common mistake I see in practice. The RDA sits above the EAR. The AI replaces the RDA when evidence isn't strong enough to set a proper EAR. The UL is the ceiling above which risk increases. They're not interchangeable. Take vitamin D as an example. The EAR for adults aged 19 through 70 is set at 15 micrograms per day, which equals 600 International Units. Add two standard deviations to that and you get the RDA of 20 micrograms or 800 IU. For adults over 70 the numbers shift to 20 micrograms EAR and 20 micrograms RDA because absorption changes with age and skin synthesis drops. These aren't arbitrary. They come from controlled balance studies, depletion-repletion trials, and fracture outcome data where available. Nutrients without solid dose-response data get an Adequate Intake instead. Chromium is a textbook case. We don't have enough evidence to pin down an EAR, so the RDA isn't defined. You'll find an AI of 25 to 35 micrograms depending on sex and age bracket. Some databases still list it alongside actual RDAs without flagging the weaker evidence base, and that creates false precision on labels.
A Practical Problem I Ran Into
About three years ago I was working with a community health client who tracked her folate intake against the RDA of 400 micrograms for adult women. She was eating fortified bread, fortified cereals, and a handful of legumes each week, yet her red blood cell folate levels suggested a functional deficiency. The standard RDA calculation was misleading her entirely. The issue was that older USDA food composition tables predated widespread folic acid fortification mandates. The database listed raw spinach at about 65 micrograms of folate per cooked cup, but the biologically active form and the fortification coverage in that person's actual food supply told a different story. I switched to the FDA's newer nutrient database that accounts for post-1998 fortification adjustments, recalculated her intake, and the numbers aligned with her lab work within a week. The workaround is simple: stop using legacy USDA Standard Reference data for anything beyond rough estimates. Use the current Food and Nutrient Database for Dietary Studies or the CDC's NHANES-linked tables instead.
Get the Full Details

Counter-Intuitive Things Beginners Miss
First, the RDA is not an optimization number. It's a deficiency-prevention threshold. Hitting it daily doesn't mean you're performing at your best, it means you're unlikely to develop clinical deficiency. Athletes, shift workers, and people managing chronic inflammation often need more than the RDA without crossing into toxicity. I've seen triathletes require three times the RDA for magnesium during heavy training blocks before deficiency markers flip negative. The standard chart won't help them. Second, bioavailability completely rewires what the RDA predicts. The RDA for non-heme iron assumes a typical Western diet with moderate enhancers and inhibitors present. If someone eats primarily plant-based iron sources alongside high-phytate grains and calcium supplements taken simultaneously, they may absorb less than a third of what the label implies. The RDA itself folds in an average absorption rate, but it doesn't adjust for individual meal composition. That gap is where most self-tracking breaks down.
When The RDA Framework Actually Fails
The biggest structural limitation is that RDAs assume a generally healthy population with normal absorption. People with malabsorption disorders, chronic kidney disease, or those on proton pump inhibitors routinely fall outside the group the RDA was designed for. The numbers don't adjust for genetics either. MTHFR variants, for instance, change how people process synthetic folic acid, and the RDA makes no distinction. You end up with populations that technically meet the RDA on paper while remaining functionally deficient. Another failure mode is nutrient interactions. The RDA for zinc is 11 milligrams for men and 8 for women, but high iron supplementation alone can inhibit zinc absorption by up to 50 percent when taken together. The reference values list them in isolation. Combining supplements without adjusting for antagonism is a routine mistake I see in clinical settings, and it explains why some people consistently underperform against their stated intake targets. If the RDA isn't the right tool for your situation, the Adequate Intake provides a softer but still useful baseline when evidence is insufficient. For upper-limit concerns, the Tolerable Upper Intake Level is where you look. They serve different purposes and shouldn't be conflated.
What To Do With This Information
Use the EAR rather than the RDA if you're tracking day-to-day intake and want a realistic middle ground. The RDA works fine as a minimum benchmark, but chasing it precisely adds little value for most people. Calculate your intake using current food composition databases that include fortification data. Adjust for known absorption modifiers if your diet deviates from the standard Western pattern assumed in the original research. And when you're working with someone who has a diagnosed condition, stop treating the RDA as definitive and work from condition-specific guidelines instead. The takeaway is straightforward: the RDA is a population-level safety margin, not an individual performance target. It's useful as a floor. Anything beyond that requires looking at absorption, interactions, and the actual evidence quality behind the number you're reading on a label.