
Understanding What RNs Can and Cannot Do in California
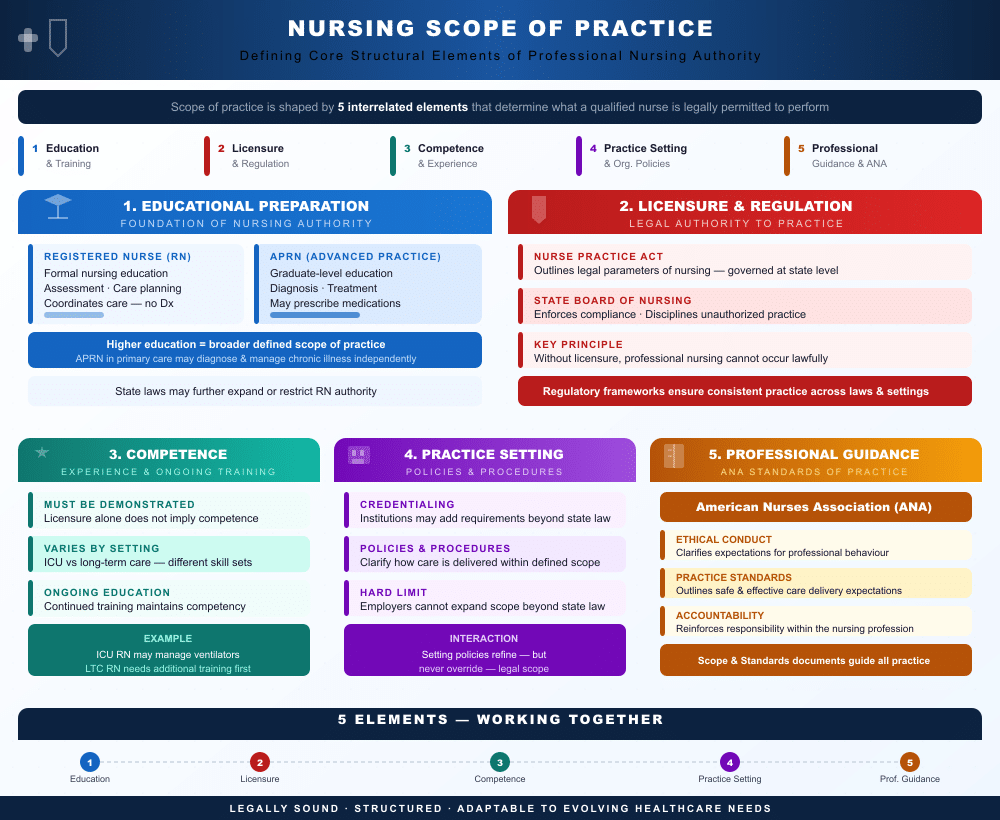
The California Board of Nursing governs what a registered nurse is legally allowed to do, and the rules are written in the Nurse Practice Act and Title 16 of the California Code of Regulations. Knowing the boundary between what you can do independently versus what requires a physician order or additional certification matters when you are covering a shift or working in a setting where someone is watching your chart. The scope definition is not a single list of tasks but a framework that changes depending on your employer policy, the patient's condition, and the current standard of care at that facility. California defines RN scope under Business and Professions Code sections 2725 through 2730, which establish that a registered nurse performs acts of nursing that require substantial knowledge and judgment derived from biological, physical, and behavioral sciences. The law recognizes two categories: independent nursing judgment, which nurses exercise autonomously, and dependent acts that require a physician's order or standing protocol. This distinction drives everything from medication administration to wound care and patient education. Here is the thing most new grad programs gloss over. California is a "dynamic scope" state, meaning your scope can change based on your training, experience, and employer's privileging. A float nurse in a surgical ICU has different allowable procedures than an RN working in an outpatient clinic, even though both hold the same CA RN license. The board expects you to know the difference, and supervisors will hold you to it. I learned this the hard way in 2019 when I was floated to a cardiac step-down unit that required a separate competency checklist for pulmonary artery catheter dressing changes. My home unit never performed those. I completed the facility competency within two days and was cleared for that specific task. Without it, doing the dressing change would have been outside my accepted scope, regardless of my years of experience elsewhere.
Let me walk through the core components so you understand what is actually in front of you day to day.
Independent Nursing Acts Under California Law
These are the tasks you can perform without a direct physician order, as long as they fall within accepted nursing standards and your facility's policies allow them. Assessment and care planning form the backbone of independent practice. You take nursing histories, perform physical assessments, interpret lab trends, and develop or revise nursing diagnoses and care plans. This is where the judgment piece matters most. California explicitly requires nurses to use clinical judgment in assessment, not just data collection. Documenting a blood pressure number is not the same as recognizing a pattern of declining perfusion and escalating your intervention accordingly. Patient education is another independent function. Whether you are teaching a diabetic patient about insulin administration or explaining post-discharge wound care instructions, this falls squarely within RN scope. The board has cited nurses in the past for failing to provide adequate discharge teaching, which is a legal risk if the patient returns with a preventable complication.
Get the Full Details

Medication administration through most routes is within scope, but there are important caveats. You can administer oral, subcutaneous, intramuscular, and intravenous medications under standing protocols or nurse-initiated standing orders, which many California hospitals use extensively. However, you cannot initiate intravenous therapy in an emergency situation without either a physician order or an approved emergency standing protocol that specifically authorizes it. I ran into a situation during a Code Blue where a resident asked me to start a peripheral IV for vasopressin. The hospital had a standing protocol for emergency drug administration during resuscitation, so I proceeded under that authority. Without the protocol, I would have needed a verbal order on the record, and the timing could have been problematic.
Dependent Acts Requiring Orders or Protocols
Dependent acts require a licensed physician, dentist, podiatrist, or chiropractor's order, except when emergency or standing protocols apply. These include most prescription medication administration, invasive procedures, and treatments that go beyond standard nursing interventions. Catheterization is a common example. Inserting a urinary catheter requires a physician order or an approved standing protocol. Many California facilities have order sets that cover this, but the protocol must be documented and available. I worked at a skilled nursing facility where the pharmacy had a blanket protocol for straight catheterization in patients with urinary retention. It was reviewed annually and signed by the medical director. That protocol covered the nurses' ability to perform the procedure without calling the attending each time. Wound debridement is another area where scope gets complicated. Sharp or surgical debridement requires a physician order. Nurse-performed enzymatic or autolytic debridement under established protocols is generally within scope. The key is what type of debridement and whether the facility has a policy that addresses it.
Delegation and Supervision Rules
California allows RNs to delegate certain tasks to licensed vocational nurses and unlicensed assistive personnel, but the delegation must follow specific guidelines. You cannot delegate clinical judgment, assessment, evaluation, or nursing diagnosis. You also cannot delegate tasks that require specialized nursing knowledge or that are inherently dangerous unless the person receiving the delegation is properly credentialed. Licensed vocational nurses in California have a more limited scope than registered nurses. An RN can delegate medication administration to an LVN in most settings, but IV push medications, blood products, and certain high-alert drugs typically cannot be delegated to LVNs without specific authorization. I had a charge nurse in 2021 assign a new LVN to hang a bag of packed red blood cells. The LVN had never crossed-matched before and the facility policy required the assigned RN to remain with the patient for the first 15 minutes. I flagged it to the supervisor because the LVN was not yet competent for that specific task, and the assignment was pulled before the shift ended. That is the kind of oversight that keeps you from being on the hook when something goes wrong.
Advanced Practice and Special Considerations
Advanced Practice Nurses (APNs) in California, including Clinical Nurse Specialists, Certified Nurse Midwives, Nurse Practitioners, and Certified Registered Nurse Anesthetists, operate under a separate but related scope. CNMs and NPs in California have prescribed practice authority that includes diagnosing, ordering diagnostics, and prescribing medications, though the exact prescribing boundaries depend on their credential and any collaborative agreements required at their practice site. The RN scope does not automatically expand just because you complete an additional certification. A wound care certification does not give you independent authority to prescribe topical treatments outside your facility's protocols. It does, however, establish a higher standard of care that your employer and the board will hold you to. If you hold a WOCN certification, expect to be expected to manage complex wounds without escalating every decision to a provider.
Common Pitfalls and Where RNs Get Into Trouble
The most frequent boundary violations I see involve medication errors at the intersection of dependent acts and independent judgment. When an order looks wrong, the nurse is expected to clarify before administering. I have seen nurses give medications they suspected were incorrect doses simply because the prescriber was unavailable. That is a scope violation. The act of clarifying with the prescriber or holding the medication and documenting the issue is your legal protection, not a courtesy. Another common issue is performing procedures outside your competency. California does not require a separate procedure license for most skills, but it does require that you only perform procedures you are trained and competent to perform. If your orientation did not cover central line care and you are asked to manage one, you need to request additional training or decline the assignment. The board has cited nurses for central line infections that resulted from improper sterile technique because the nurse had never been credentialed for that procedure. Emergency situations create their own gray areas. In a true emergency where no provider is immediately available, California law provides some leeway for life-saving interventions. But this is narrow. The intervention must be necessary to prevent imminent harm, and you must document the situation thoroughly. The board evaluates emergency actions retroactively, and documentation is your evidence that you operated within acceptable standards under the circumstances.
How to Verify Your Scope Before Each Shift
The most practical approach is to check three things before accepting any assignment that involves procedures or tasks outside your usual routine. First, review your facility's policy on the specific procedure. Policies are binding and they define the operational scope within the legal framework. Second, confirm your competency status. Some hospitals maintain a real-time privileging list you can access through the nurse scheduling system. Third, know where the standing protocols are located. Emergency and nurse-initiated protocols are typically posted in supply rooms or accessible through the electronic health record. When in doubt, ask for clarification from your charge nurse or the nursing supervisor. This is not a weakness. It is the standard that the board expects. Documenting that you sought clarification and followed the guidance given protects both the patient and your license.



