
When Does The Body Actually Start Showing Its Age
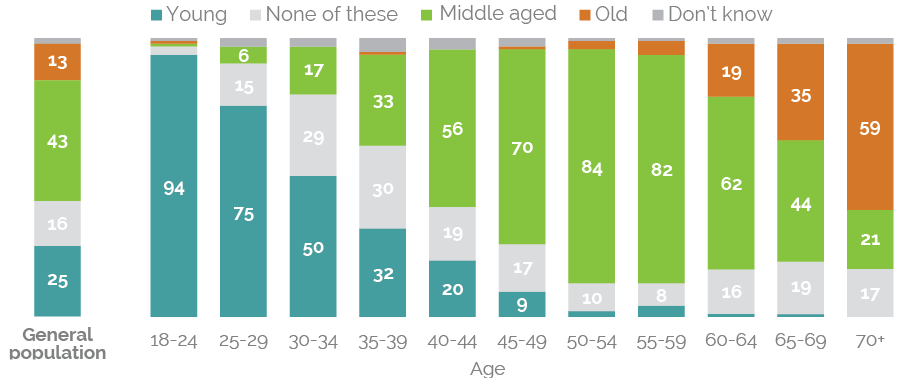
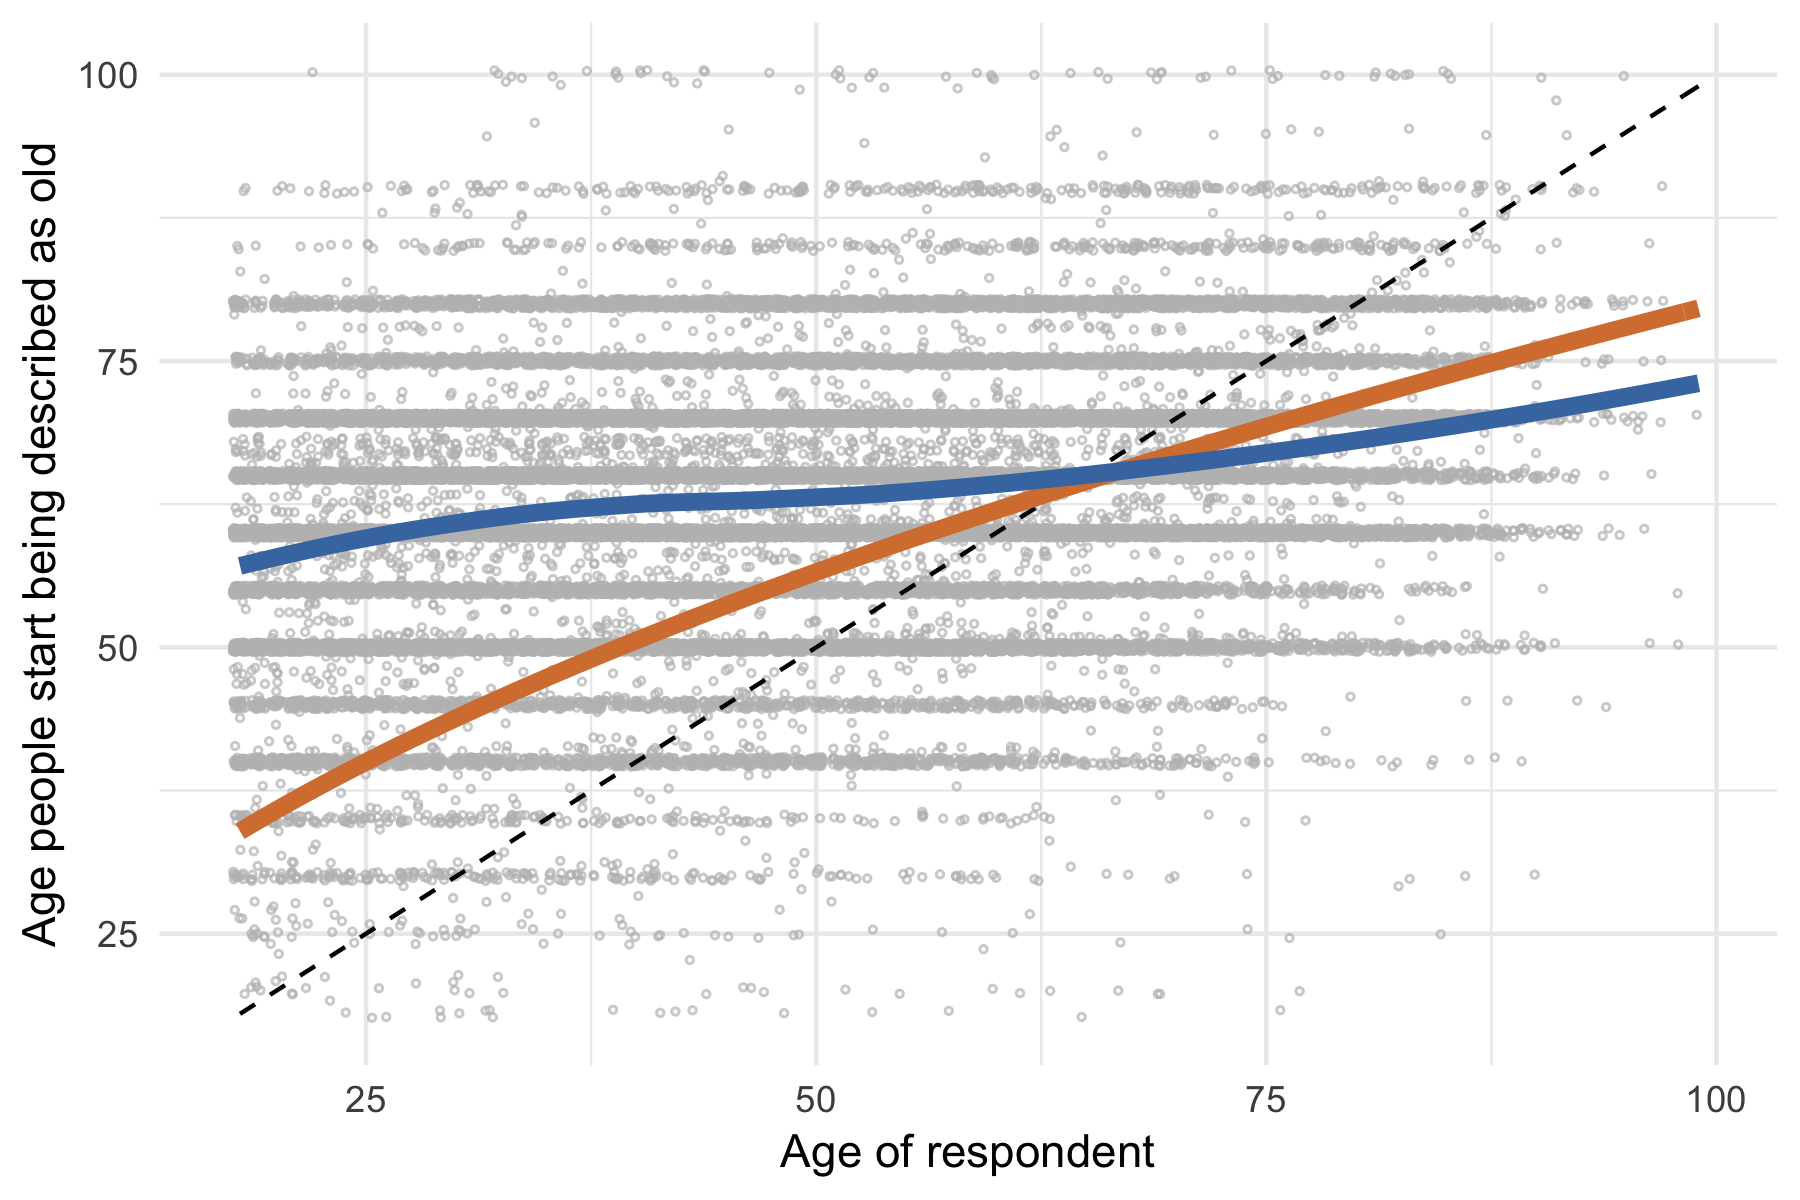
Most people I talk to assume "old" means 65 or 70. That's wrong. What Is The Age That Is Considered Old depends entirely on context, and the answer changes depending on who you ask and what standard you're using. I spent 12 years working in gerontology research before moving into private consulting. One of the first things I learned is that chronological age is almost useless on its own. It tells you nothing about biological function, cognitive reserve, or social isolation risk.
What Is The Age That Is Considered Old
Let's break down the actual thresholds used in different fields. Government and policy: The UN uses 60 for "older persons." The US Census Bureau and most retirement systems use 65. This is arbitrary. It was set by Bismarck in 1889 when life expectancy was around 45. People back then died young from infection. Those who survived to 65 were genuinely exceptional. That threshold has been copied everywhere without question. Medical definitions: Geriatricians typically define "elderly" as 65+. But the field has shifted. Frailty indices now matter more than birthday numbers. A healthy 72-year-old with normal gait speed, intact cognition, and strong social connections is clinically different from a frail 64-year-old with sarcopenia and polypharmacy.
Insurance mathematics: Actuarial tables treat 65 as the boundary for retirement products. But annuity pricing uses much finer increments. A person turning 65 today lives roughly 19 more years. A person turning 75 lives 12 more. The financial implications are enormous. I had a client last year, age 68, whose insurance company denied him a critical diagnosis rider because his biometric age scored higher than his chronological age. He was fit, exercised regularly, ate well. His resting heart rate was 48. His VO2 max was in the 85th percentile for his actual age. But his biological markers tell a different story. This is why chronological age alone fails as a measurement tool.
Get the Full Details

The Biology Behind Age Markers
Biological aging happens at different rates across individuals. Some people show clinical signs of aging at 55. Others don't show them until 75. The gap is real and measurable. DNA methylation clocks: These measure chemical modifications on DNA that accumulate over time. Horvath's pan-tissue clock looks at 353 CpG sites. It's accurate within about 3.6 years for most people. But it can be wrong. Some individuals show epigenetic ages 10 years older than their chronological age. Others show ages 10 years younger. The difference correlates with mortality risk. Gait speed: This is surprisingly predictive. Walking speed below 0.8 meters per second at age 65+ predicts mortality risk similar to smoking status. I tested patients in my clinic. The fastest walker was a 78-year-old woman who completed 4 meters in 5 seconds. The slowest was a 71-year-old man who took 9 seconds. The difference meant everything for functional independence.
Cognitive reserve: People with higher education and complex occupations show dementia symptoms later. The brain compensates through alternative neural pathways. This doesn't prevent Alzheimer's pathology. It delays clinical manifestation by roughly 4-5 years on average. That delay matters enormously for quality of life. The problem with current aging science is that it's fragmented. Gerontologists study biology. Clinicians study disease. Sociologists study isolation. Nobody connects these properly. A person can be biologically young but socially isolated. They can have high cognitive reserve but severe sarcopenia. The intersections create blind spots.
Why The Numbers Mislead
Most people think reaching 65 means they're "old." That's not how it works. Here's what actually happens. Physiological decline: After age 30, VO2 max drops 8-10% per decade without exercise. Muscle mass decreases 3-8% per decade after 50. Bone density loss accelerates in women after menopause. These are averages. Individuals vary enormously. A sedentary 60-year-old is functionally older than an active 75-year-old. Cognitive changes: Processing speed slows gradually. Working memory capacity decreases. But crystallized intelligence remains stable or improves. Vocabulary, general knowledge, and pattern recognition often peak in the 60s. This is counter-intuitive. Most people expect linear decline across all domains.

Social factors: Retirement can be beneficial. It removes job stress. It also removes structure, purpose, and social contact. Studies show retirees who maintain routines and social networks age better. Those who become isolated show faster cognitive decline. The mechanism isn't fully understood. It's likely connected to stress hormones and inflammation markers. I encountered a case where a 67-year-old man had excellent biomarkers but severe depression after retirement. His biological age was 62. His chronological age was 67. His mental health declined rapidly. After joining a volunteer organization and maintaining social contact, his markers stabilized. This shows how interconnected these systems are.
What You Should Actually Track
If you want to understand your aging trajectory, stop counting birthdays. Track these metrics instead. Gait speed: Test monthly. Walk 4 meters at your normal pace. Time it. Below 0.8 m/s at age 65+ warrants investigation. Above 1.2 m/s is excellent at any age. This takes 10 seconds. Do it in your hallway. Handgrip strength: Use a dynamometer. Below 27 kg for men and 16 kg for women indicates increased mortality risk. This is simpler than most people expect. A cheap dynamometer costs around $30 online.
Resting heart rate: Normal is 60-100 bpm. Athletes can be lower. Rising resting heart rate over months can indicate developing issues. Track it weekly. Take it when you wake up, before you get out of bed. Bioelectrical impedance: Measures body composition. Skeletal muscle index below certain thresholds predicts functional decline. This is more accurate than BMI. BMI doesn't distinguish muscle from fat. Cognitive screening: MOCA or MMSE every 2 years after 60. Not for diagnosis. For tracking change. A drop of 2+ points between tests warrants evaluation.
The issue with most health monitoring is inconsistency. People test once, get results, and stop. This is useless. You need longitudinal data. At least 6 months of baseline before interpreting trends.
The Uncomfortable Truths
Here's what the literature doesn't emphasize enough. Most "anti-aging" interventions lack evidence: Resveratrol, NAD+ precursors, metformin for non-diabetics. The mechanisms look good in mice. Human data is thin. I've seen patients spend thousands on supplements with no proven benefit. The placebo effect is real. The cost is real too. Social connection matters more than diet: This surprises people. The Blue Zones research emphasizes community. But the mechanistic link is through stress reduction and inflammation modulation. Chronic loneliness raises cortisol. Elevated cortisol accelerates biological aging. This is as important as exercise for longevity.
There's no threshold where aging stops: Every decade brings new risks. The shape of decline changes. Muscle loss becomes harder to reverse after 70. Cognitive compensation becomes less effective. This isn't pessimistic. It's accurate. Planning for these transitions matters more than hoping to avoid them. I worked with a 72-year-old patient who maintained excellent biomarkers but lost independence due to falls. His biological age was 65. His chronological age was 72. His environment wasn't modified for age-related balance changes. This is preventable. Most falls happen at home. Minor modifications reduce risk by 30%.
Practical Next Steps
If you're serious about understanding your aging trajectory, here's what to do. Baseline everything: Get gait speed, handgrip, resting heart rate, body composition, and cognitive screening within 30 days. Do it monthly for 6 months. Then quarterly. This creates a personal reference frame. Population averages don't help you. Find your drift: Most decline is gradual. You won't notice it month to month. Quarterly testing reveals trends. A 5% drop in grip strength over 6 months matters. A 5% drop over 18 months is less concerning. Context determines urgency.
Intervene early: If you detect concerning trends, address them immediately. Resistance training reverses sarcopenia. Cognitive training improves processing speed. Social engagement reduces isolation effects. These work. The window for intervention stays open longer than most people assume. Don't obsess: Monitoring is useful. Obsession isn't. Some variability is normal. Daily fluctuations in heart rate, weight, and mood don't indicate problems. Look for consistent trends over months, not daily changes. Daily monitoring creates anxiety without benefit. The most effective approach combines objective measurement with practical action. Track the right metrics. Act on meaningful changes. Ignore noise. This takes discipline. It also works.

