How the Nervous System Runs Everything Without You Noticing
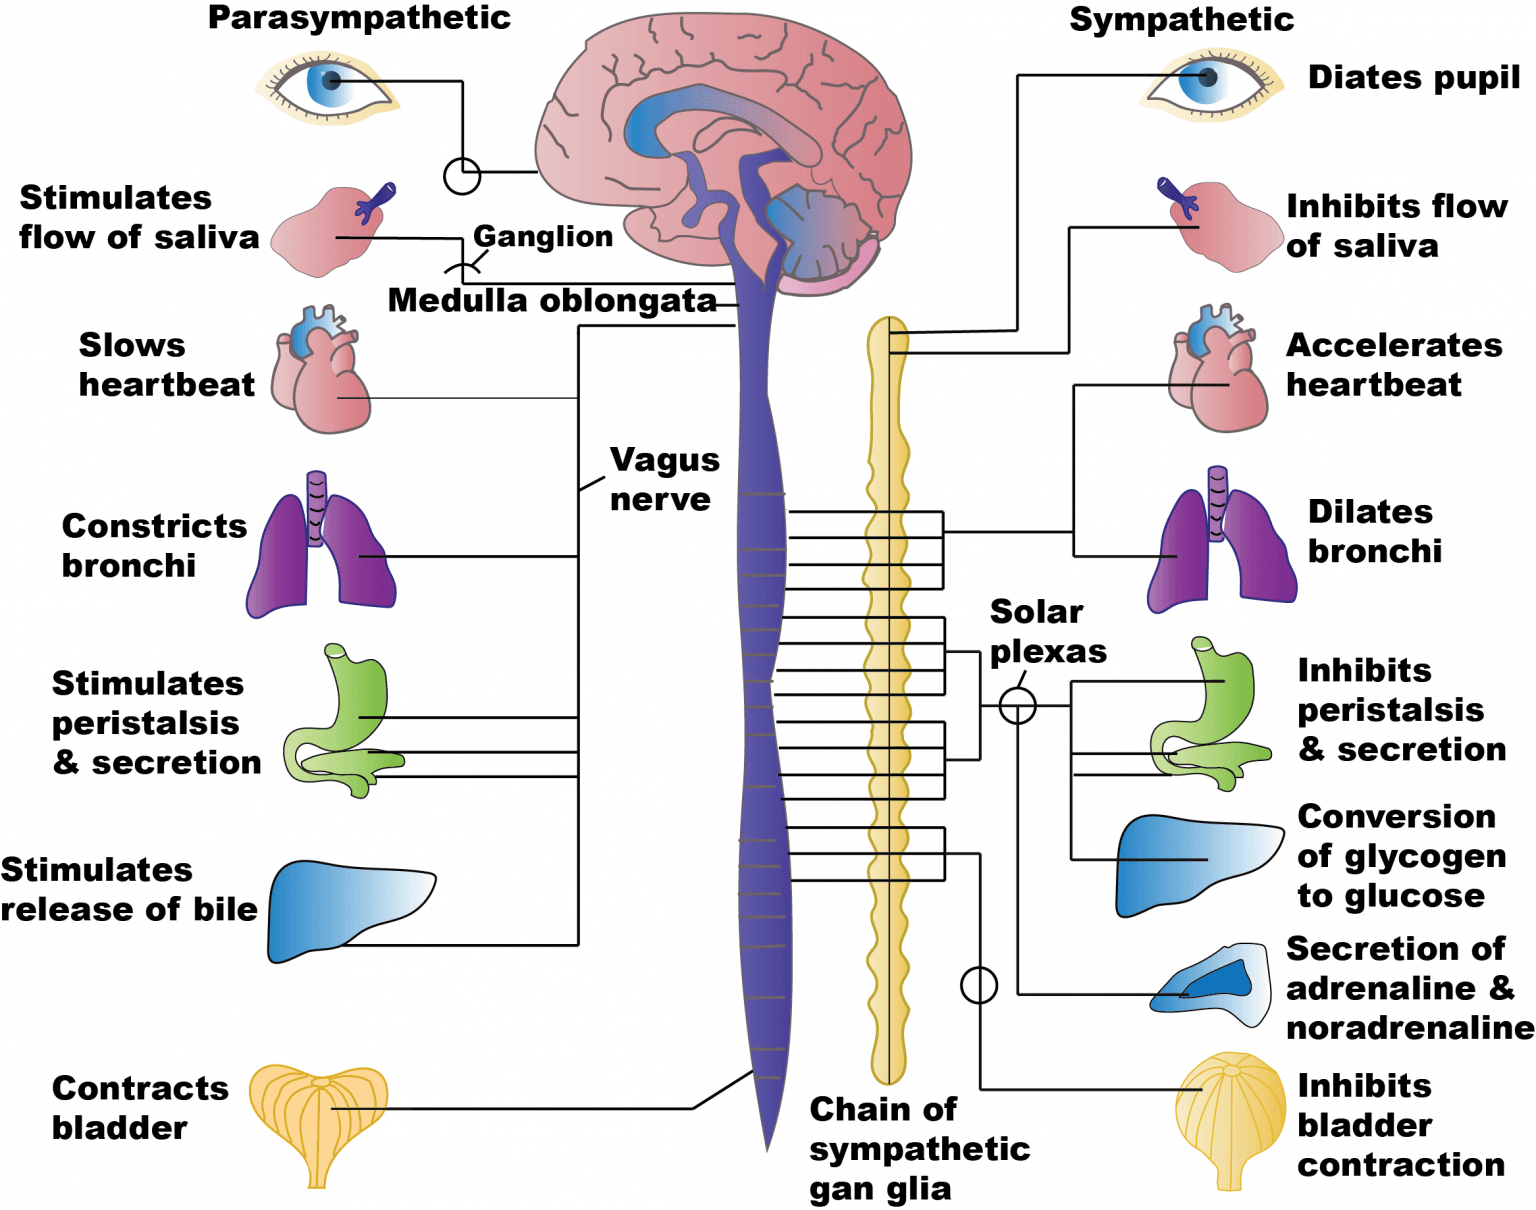
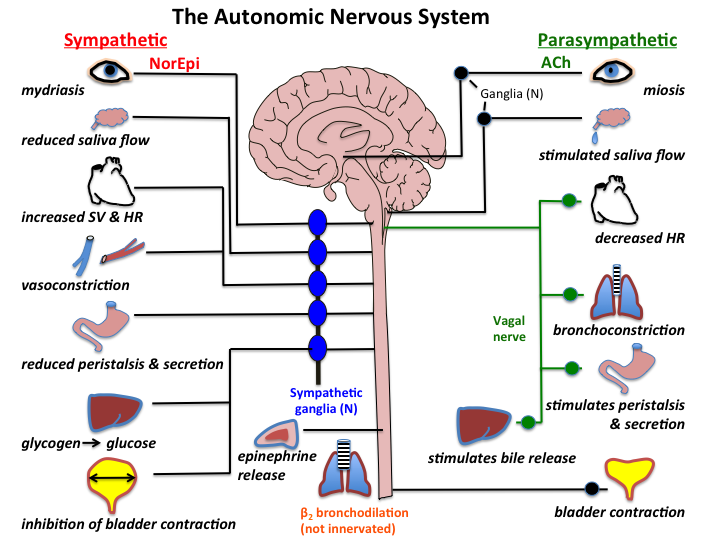
The autonomic nervous system is the part of your peripheral nervous system that controls involuntary functions. Heart rate, digestion, respiratory rate, pupil dilation, sweat production, and blood pressure regulation all fall under its domain. It operates largely outside conscious control, which is usually a good thing because if you had to think about every heartbeat, you would not have time for anything else. It splits into three main branches: the sympathetic nervous system, the parasympathetic nervous system, and the enteric nervous system. The sympathetic branch handles fight-or-flight responses, accelerating heart rate and redirecting blood to major muscles. The parasympathetic branch manages rest-and-digest functions, slowing the heart and promoting digestion. The enteric nervous system runs independently inside your gastrointestinal tract and can operate even when disconnected from the central nervous system, though it normally communicates bidirectionally with both other branches.
What Is The Autonomic Nervous System and Why It Matters in Practice
Most textbooks stop at the basic definitions, but the real complexity shows up when you actually deal with dysregulation. I spent years working with patients who presented with seemingly unrelated symptoms: chronic fatigue, unexplained GI issues, dizziness on standing, and temperature dysregulation. In a significant number of cases, the root was autonomic dysfunction rather than any single organ problem. That is where understanding the system as an integrated network becomes essential instead of treating each symptom in isolation. One counter-intuitive thing that beginners often miss is that the sympathetic and parasympathetic systems are not simply on-off switches. They co-contract all the time. Your heart rate variability, for example, depends on the balance between both branches firing simultaneously, not one being active while the other is completely off. When people try to "activate" their parasympathetic system through breathing exercises or vagal stimulation, they are not turning off the sympathetic system. They are shifting the ratio, and the degree of shift varies enormously between individuals based on baseline health, stress history, medications, and even circadian timing. Another thing most people overlook is the role of the vagus nerve as the primary parasympathetic highway. It extends from the brainstem to the colon, innervating the heart, lungs, digestive tract, and parts of the ear and throat. Stimulation of different branches produces very different effects. Anterior vagal fibers affect the heart and lungs, while posterior fibers dominate GI function. This anatomical detail matters because generic "vagus nerve exercises" do not produce uniform results, and some approaches may even worsen symptoms in people with specific dysfunctions like gastroparesis or inappropriate sinus tachycardia.
I ran into a specific edge case a few years back with a patient who had severe orthostatic intolerance and had been prescribed fludrocortisone and midodrine for presumed POTS. Standard protocol, right? The problem was that her symptoms did not improve, and her resting heart rate paradoxically increased on the midodrine. We tested further and found she actually had neurogenic orthostatic hypotension with a superimposed form of vagal hyperreactivity. The midodrine was constricting her peripheral vessels, which triggered a compensatory vagal response that slowed her heart at the wrong times and raised it at others. We switched her to droxidopa instead, which has a shorter half-life and a different mechanism, and adjusted the dosing schedule around her symptom patterns. Her symptoms improved within three weeks. That case illustrates why autonomic testing requires more than just applying standard treatment algorithms. Proper assessment involves several specific tools. Tilt table testing measures blood pressure and heart rate responses to positional changes over 30 to 60 minutes. Quantitative sudomotor axon reflex testing evaluates sweat gland function and identifies small fiber neuropathy. Heart rate variability analysis provides data on autonomic balance, though the metrics require careful interpretation because factors like age, fitness level, medication, and even meal timing significantly affect readings. Deep breathing tests and the Valsalva maneuver are simpler bedside assessments that reveal important information about parasympathetic and sympathetic integrity. Management depends entirely on the specific dysfunction. For conditions like POTS, the first line is usually non-pharmacological: increased fluid intake, sodium supplementation, compression garments, and graded exercise programs that start recumbent and gradually progress. Pharmacological options include beta-blockers, ivabradine, midodrine, fludrocortisone, and sometimes alpha-agonists. Each has trade-offs. Beta-blockers can worsen exercise tolerance in some patients. Midodrine causes supine hypertension if dosed too late in the day. Fludrocortisone can lead to hypokalemia and requires regular monitoring.
Get the Full Details
For neurogenic orthostatic hypotension, the approach differs significantly. Volume expansion helps but must be balanced against heart failure risk in vulnerable patients. Compression garments are effective but often poorly tolerated in warm climates. Medications like droxidopa, midodrine, and pyridostigmine each target different aspects of the dysfunction. Pyridostigmine is particularly interesting because it enhances ganglionic transmission selectively during postural stress rather than causing constant vasoconstriction, which means fewer side effects like supine hypertension. That selectivity is why I prefer it as a first-line pharmacological option in many cases. Enteric nervous system disorders represent another major category. Conditions like gastroparesis, intestinal pseudo-obstruction, and severe constipation often reflect enteric autonomic dysfunction that is separate from but connected to systemic autonomic issues. Prokinetic agents like metoclopramide and domperidone help some patients, but long-term metoclopramide use carries a risk of tardive dyskinesia. Erythromycin works short-term through motilin receptor agonism but loses efficacy quickly due to receptor downregulation. Newer agents like prucalopride offer better options for chronic constipation with a more favorable side effect profile. The biggest limitation in this field is diagnostic uncertainty. Many autonomic disorders are underdiagnosed because routine clinical evaluations rarely include comprehensive autonomic testing. A standard physical exam and basic blood work will miss most dysautonomias. Patients often visit multiple specialists over years before receiving a correct diagnosis. Even after diagnosis, treatment remains largely symptomatic rather than curative for most conditions. There is no disease-modifying therapy for most autonomic disorders yet, though research into sympathetic denervation procedures, vagal nerve stimulation, and targeted pharmacological approaches is ongoing.
Self-management strategies have limited but real value. paced breathing at six breaths per minute has been shown to improve heart rate variability in some studies, though the effect size is modest and individual variation is large. Cold exposure through face immersion or cold packs on the chest can stimulate the diving reflex and increase vagal tone temporarily, but this is not a treatment for underlying dysfunction. Hydration and sodium management are genuinely helpful for many people with orthostatic intolerance, but the required amounts vary wildly from person to person. The bottom line is that the autonomic nervous system is a complex, interconnected network that is easy to oversimplify and hard to treat comprehensively. Understanding the three-branch model is a starting point, not a complete framework. Real clinical practice requires recognizing that autonomic dysfunction exists on a spectrum, that standard protocols do not fit everyone, and that careful testing and individualized management are essential for meaningful improvement.