Understanding Weight Ranges for Early Adolescence
The average weight for a 13 year old varies significantly between genders and individual development timelines. I get asked this question constantly by parents who pulled a number from a chart and immediately spiraled. It happens so often I stopped trying to be encouraging. Let me just lay out what the data actually shows and why the question itself is usually pointing at something more complicated. According to CDC growth charts, the median weight for a 13-year-old boy is approximately 101 pounds, while for a girl it is around 100 pounds. But median is not a target. It is a statistical midline that divides a population into two equal halves. About half of all 13-year-old boys weigh more than 101 pounds. Half of all 13-year-old girls weigh more than 100 pounds. Those numbers do not mean anything individually. The healthy range, defined by the 5th to 85th percentile on standard growth charts, stretches roughly from 75 to 140 pounds for boys and 78 to 135 pounds for girls at that age. Children falling within that bracket are considered to be on track from a purely statistical standpoint. That does not guarantee they are healthy. It means their weight tracks consistently with a reference population over time.
Here is where people get it wrong. They look at a single data point and treat it like a verdict. Weight at one moment tells you almost nothing about a child's health trajectory. The percentile change over six months matters more than any absolute number on the scale. I ran into a situation last year with a patient whose 13-year-old daughter sat right at the 70th percentile for weight. By all surface-level metrics she looked fine. But her percentile had dropped from the 55th to the 70th over an 18-month period while her height percentile held steady. That divergence flagged something. The family dismissed it until basic labs came back showing early insulin resistance. Catching the trend early changed the intervention from reactive to proactive. A single weight check would have missed it entirely.
Why Percentile Tracking Matters More Than Any Single Number
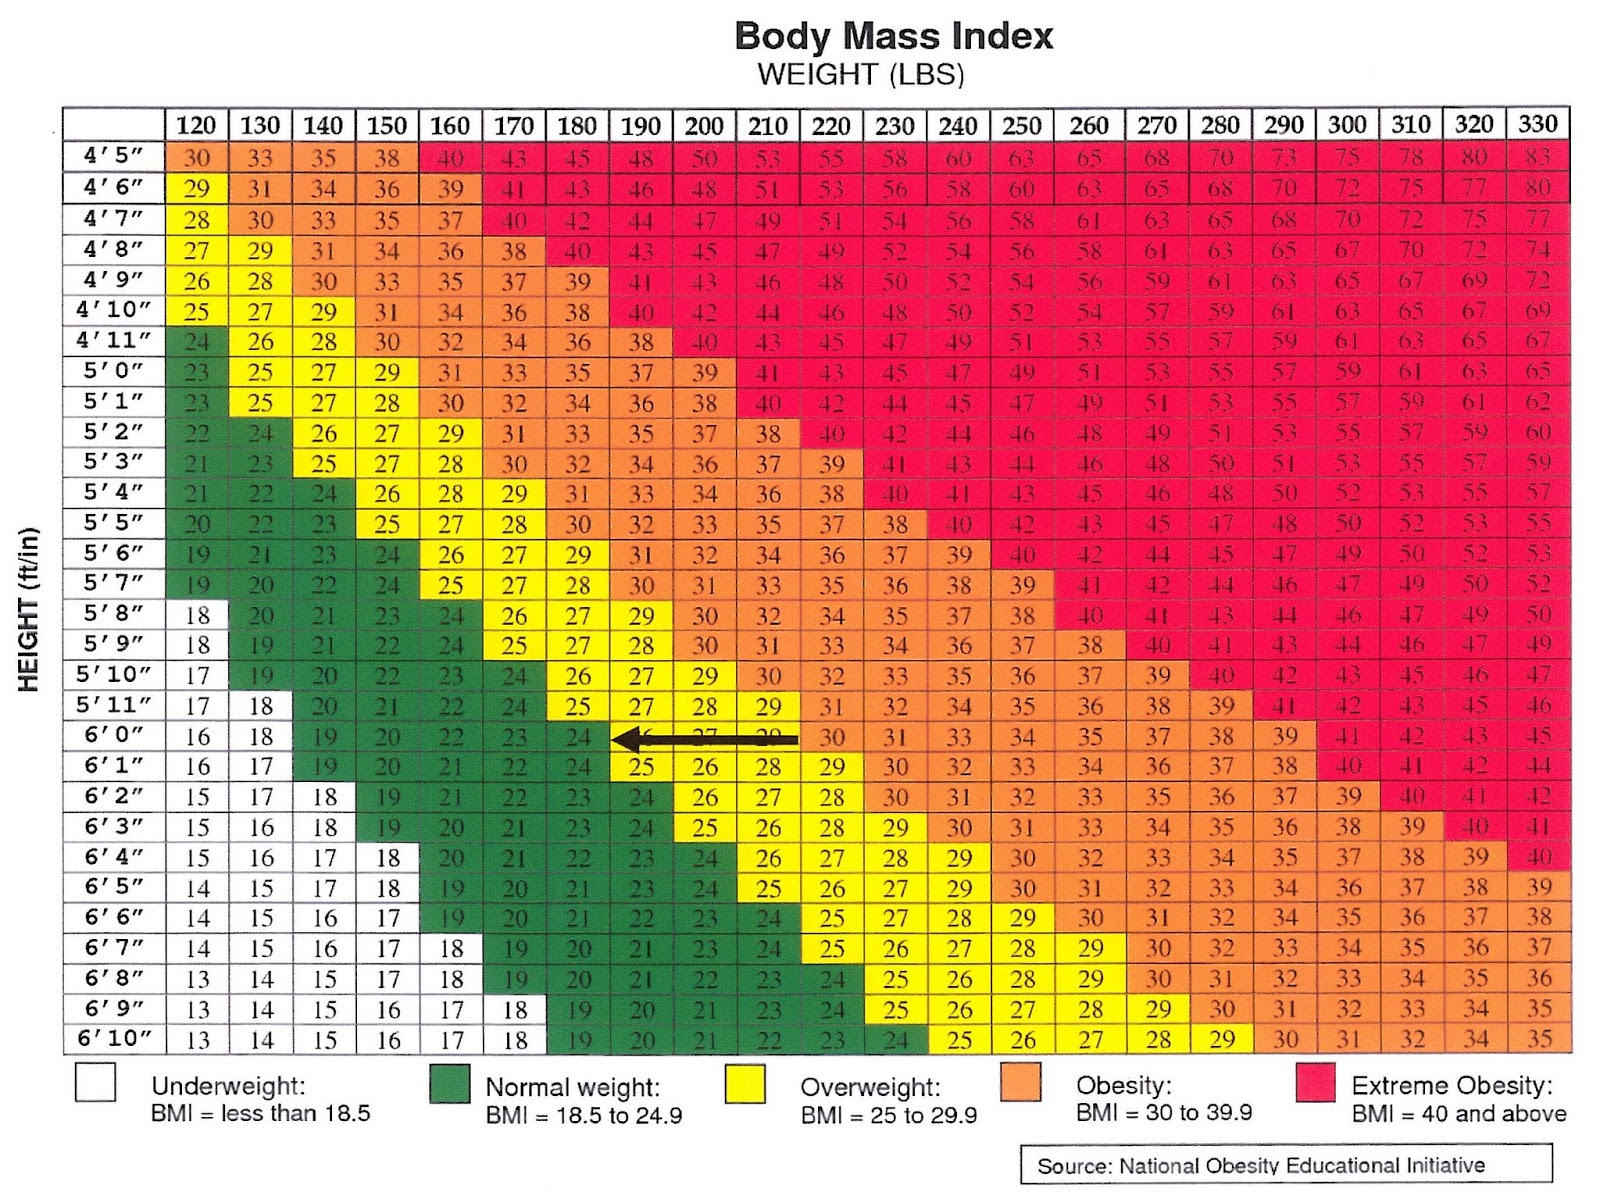
Growth charts were built to track trajectories, not to serve as pass-fail certificates. A child who consistently sits at the 25th percentile for both height and weight is usually perfectly healthy. They have simply grown along that curve their whole life. What raises a red flag is a child who jumps between percentiles without a clear reason. Crossing two or more major percentile lines on a growth chart over a short period warrants investigation regardless of whether the child is trending up or down. Puberty complicates everything. A 13-year-old boy who has not yet entered puberty may sit at the 40th percentile for weight while his peer who started puberty at 10 sits at the 85th percentile. Both can be completely normal. The timing of pubertal onset varies by years and directly impacts weight distribution. Boys who start later often gain weight faster during their growth spurt. Girls who start earlier carry more body fat naturally as hormones shift. These patterns are biological, not behavioral, and they confuse parents who are comparing notes at soccer practice. BMI-for-age is another tool that gets weaponized incorrectly. It is a screening measure, not a diagnostic one. Pediatricians use it because it accounts for the fact that children grow taller at different rates, but it does not distinguish between muscle mass and fat mass. A 13-year-old swimmer with developed shoulder and core muscles will register higher on the BMI scale than a sedentary peer of identical height and body composition. The number alone cannot tell you which kid is metabolically healthier.
Get the Full Details
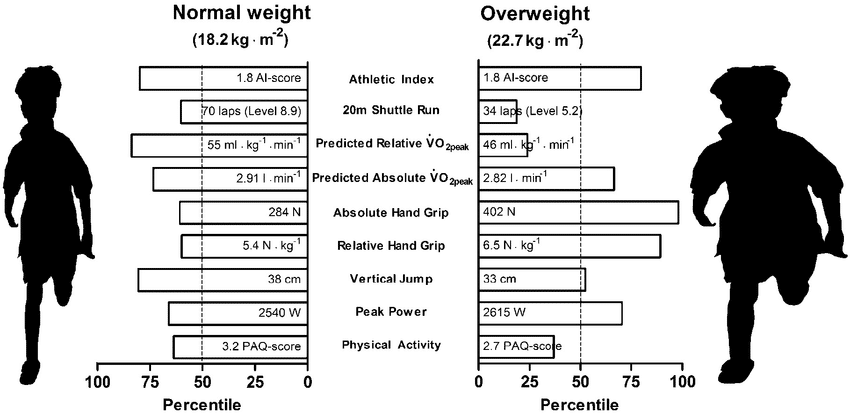
I once dealt with a case involving a 13-year-old who was labeled overweight based on BMI alone. He played competitive wrestling and had what I would call a very high lean mass index. His blood pressure, lipid panel, and blood sugar were all within optimal ranges. The BMI category was technically accurate but clinically misleading. We had to explain to the family that the label they feared was an artifact of the screening tool, not a reflection of his actual health status. Fixating on the percentile number cost them three months of unnecessary anxiety before we redirected the conversation toward actual metabolic markers.
Practical Approaches That Actually Work
If you are a parent trying to understand where your child stands, start by looking at the growth chart history rather than the current number. Grab the well-child visit records and plot where your child has been over the last two years. A steady curve following a consistent percentile is normal. Erratic jumps are not. Do not weigh your child daily. Daily fluctuations of three to five pounds are normal due to hydration, glycogen stores, and digestive content. Weekly averages over a month give you a much cleaner signal. If you must track at home, weigh once a week under consistent conditions and note the trend rather than the individual reading. Focus on behaviors that support healthy growth regardless of where the number lands. Adequate sleep is non-negotiable. Thirteen-year-olds need eight to ten hours. Sleep deprivation disrupts leptin and ghrelin, the hormones that regulate hunger and fullness. I have seen kids who were eating reasonably well suddenly gain weight after their sleep schedule shifted during a seasonal change. The food did not change. The hormones did.
Physical activity should be framed around enjoyment, not calorie burning. Kids who are forced into exercise they despise tend to abandon it entirely during adolescence. The ones who find something they actually like, whether it is dancing, climbing, swimming, or basketball, tend to stay active through their teens. That consistency matters more than any single workout session. Nutrition should be treated as addition rather than restriction. Add vegetables to existing meals. Add protein at breakfast. Add water instead of sugary drinks. Removing foods creates scarcity psychology that backfires during the teenage years when autonomy becomes the primary developmental task. Restriction-based approaches to childhood nutrition have a very poor long-term success rate.
When to Actually Worry
Rapid unexplained weight gain or loss alongside other symptoms is the main concern. Fatigue, changes in bowel habits, excessive thirst, frequent urination, or sudden mood shifts paired with weight changes warrant a pediatric visit. These are not weight problems. They are indicators that something else is going on. The weight is just the visible symptom. Cases where a child is above the 95th percentile or below the 5th percentile deserve professional evaluation even if they feel fine. Being at either extreme increases the probability of underlying issues, though it does not guarantee them. Screening is cheap and non-invasive compared to finding out later when something has progressed further. The one scenario where weight is genuinely irrelevant is when a 13-year-old is obsessively tracking it. That is a psychological health concern, not a nutritional one. I have seen kids with perfect metabolic markers become seriously ill from exercise compulsions and restrictive eating patterns driven by social media comparison. The number on the scale became the problem long before it reflected any actual health issue.
The average weight for a 13 year old exists on paper. Real children grow on timelines that have nothing to do with averages. The question that actually matters is whether the child is growing consistently, sleeping adequately, moving regularly, and eating without shame. Those factors predict outcomes far better than any percentile line on a CDC chart.