Axial Skeleton Breakdown
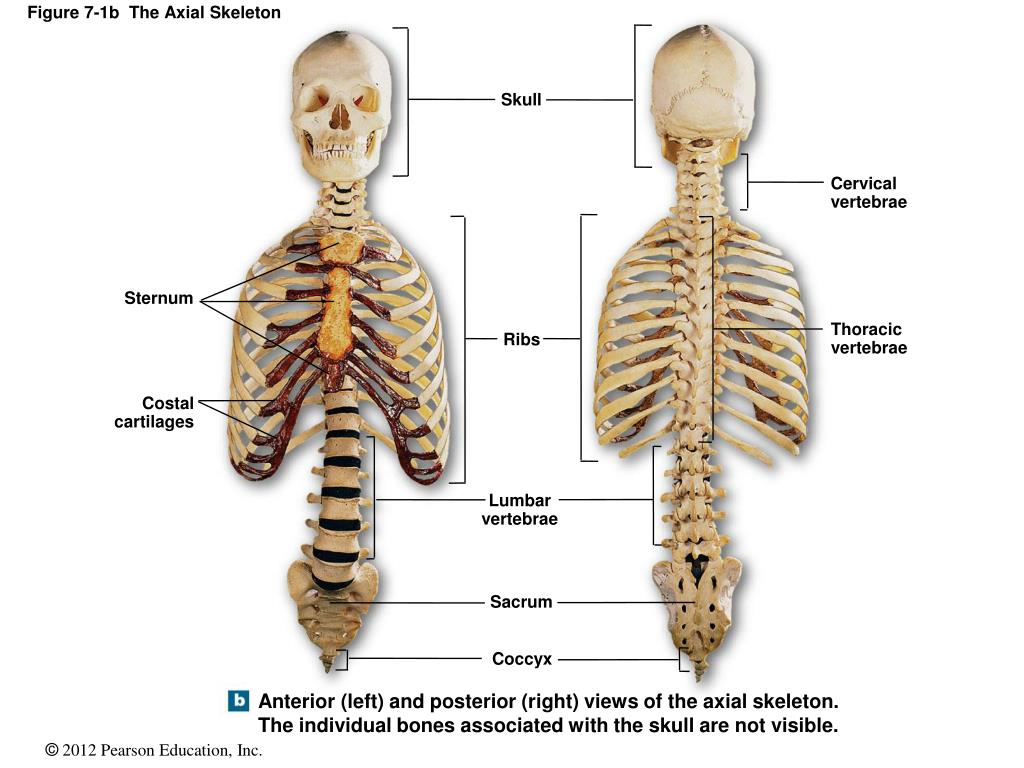
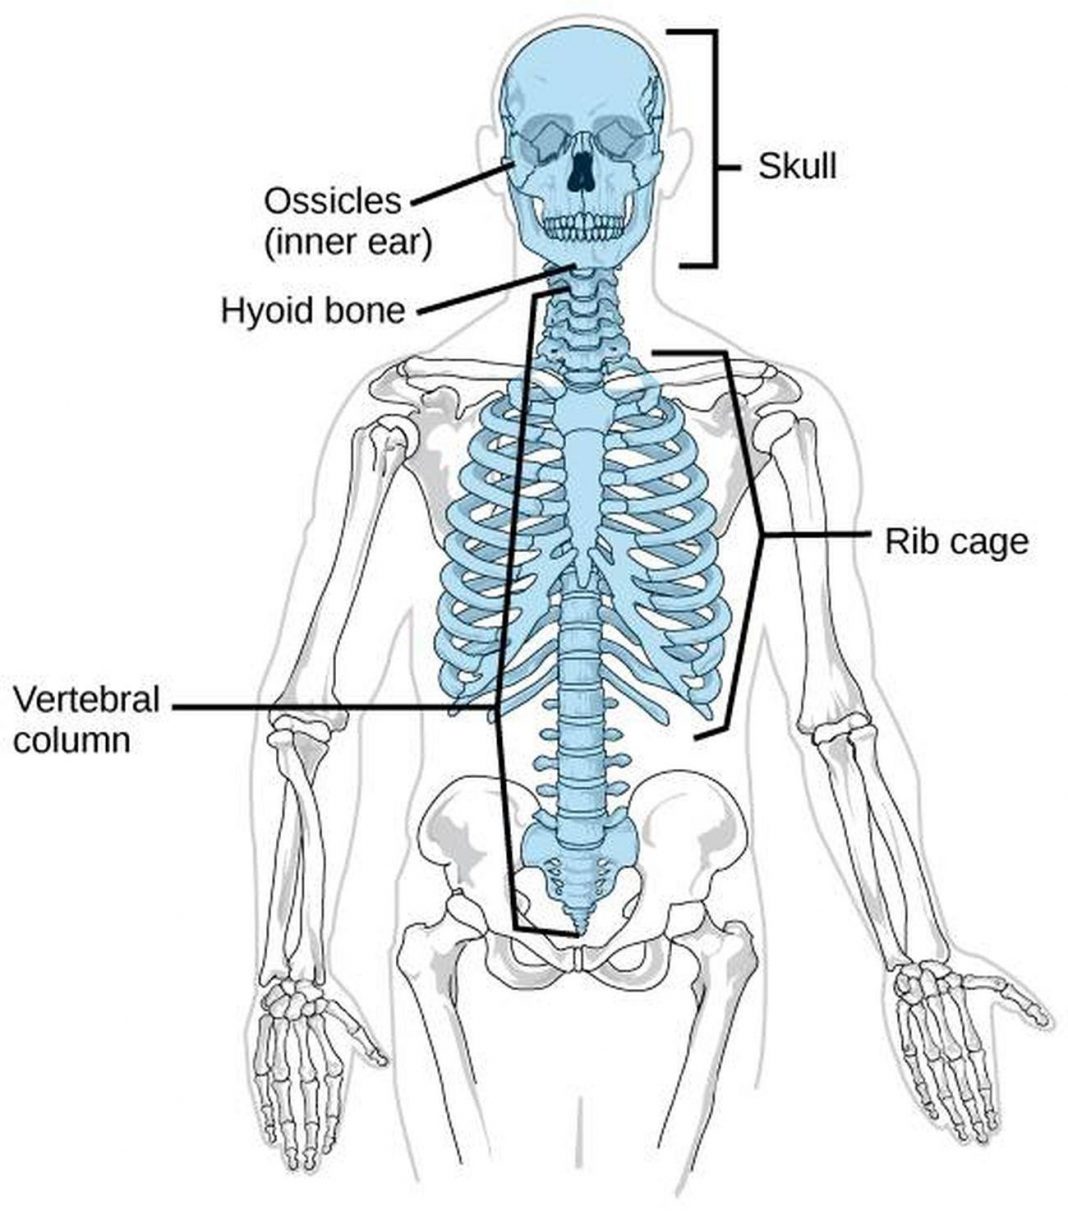
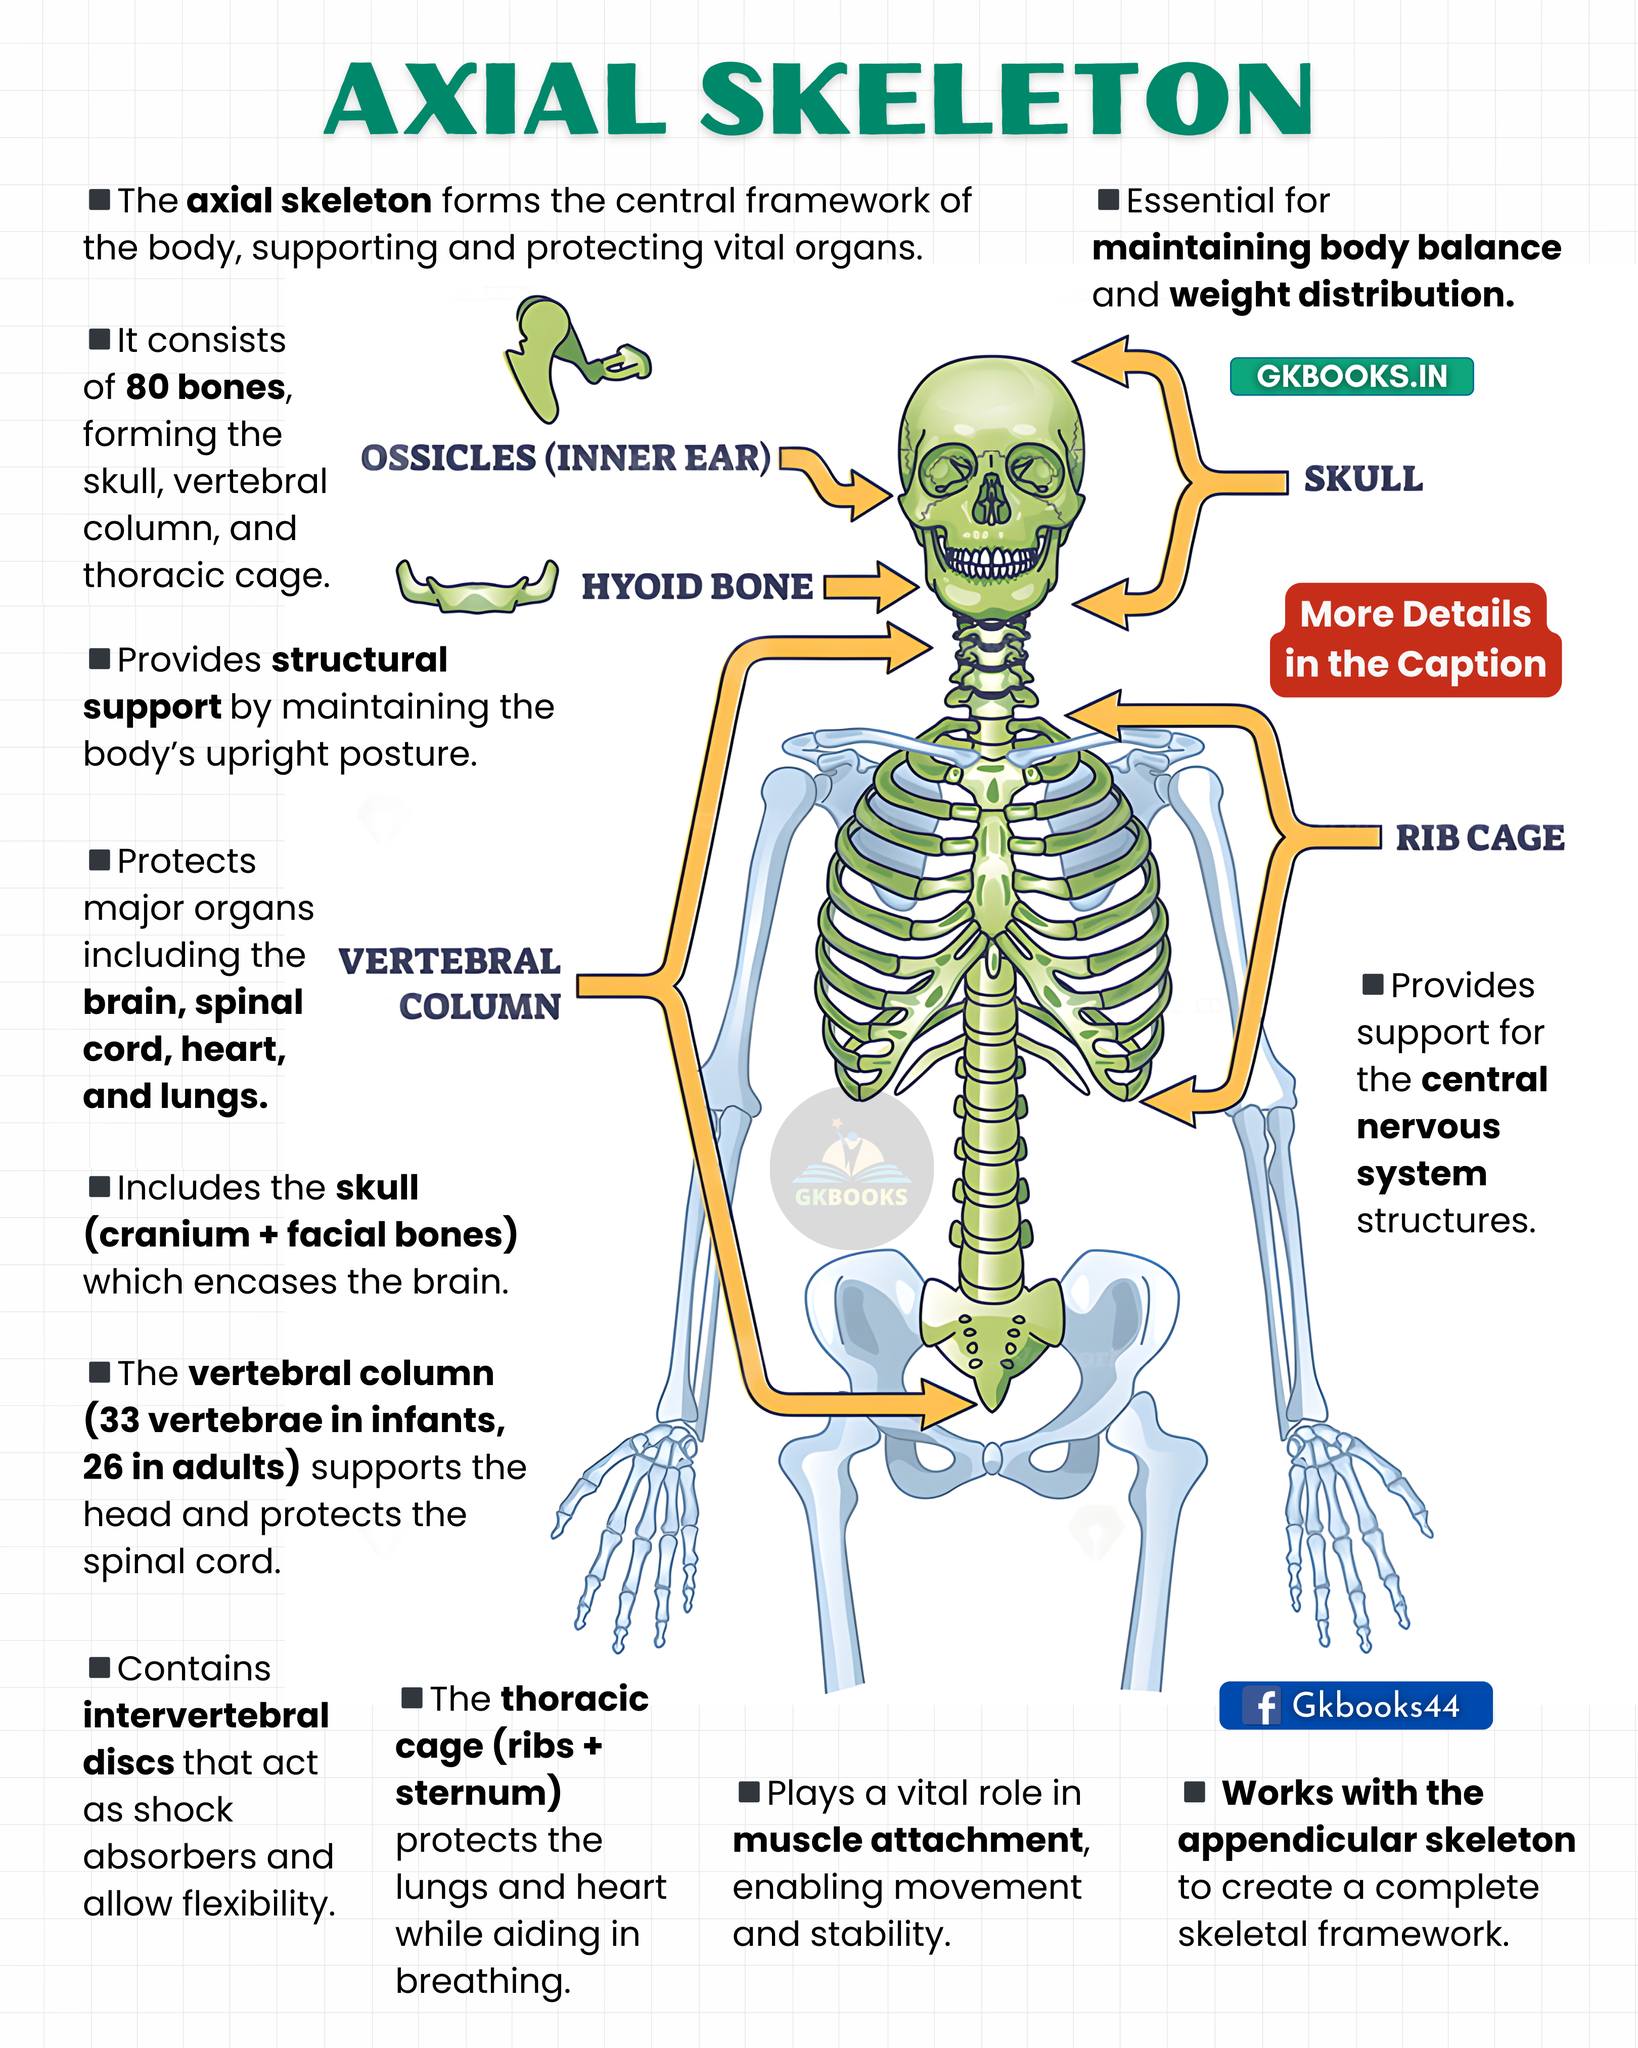
When someone asks what is the axial skeleton, they are looking at the central structural core of the human body. It includes the skull, vertebral column, thoracic cage, and the hyoid bone. That is roughly eighty bones total, give or take depending on how you count the auditory ossicles and the variable numbers of ribs and sacral vertebrae. It runs along the body's midline and serves as the attachment point for all the appendicular components. I spent several years working in anatomical illustration and forensic reconstruction, and the axial skeleton is where most people cut corners. They treat it like a static rack of bones rather than a functional mechanical system. Here is what actually matters when you are dealing with it in practice.
What Is The Axial Skeleton and How It Actually Works
The skull protects the brain and anchors the face. The vertebral column provides the central axis and houses the spinal cord. The thoracic cage protects the heart and lungs while enabling respiration. The hyoid bone is easily overlooked but essential — it anchors the tongue and allows for swallowing and speech. Every part connects to the others through ligaments, cartilage, and muscle attachments, not just direct bone-to-bone contact. The vertebral column alone contains twenty-four articulated vertebrae plus the sacrum and coccyx. The cervical region has seven, thoracic twelve, and lumbar five. Counting them wrong on an exam is one of those embarrassingly common mistakes beginners make. I have seen people lose points for miscounting the lumbar vertebrae because they confuse L5 with S1, which happens frequently since the lumbosacral junction can look ambiguous on certain imaging. The ribs come in three types: true ribs (one through seven), false ribs (eight through ten), and floating ribs (eleven and twelve). The costal cartilages connecting the true and false ribs to the sternum are clinically relevant. They calcify with age, and the pattern of calcification is used in forensic age estimation, but it is also one of the least reliable indicators available. I worked on a case where age estimates based on rib cartilage calcification ranged from twenty years off. It is not precise enough to rely on without supporting evidence.
Common Pitfalls and Counter-Intuitive Details
One thing most textbooks gloss over is the mobility of the axial skeleton. It is not rigid. The sutures between cranial bones allow for slight movement during birth and persist as flexible joints throughout life. The intervertebral discs compress and expand with loading. The costovertebral joints move during every breath. When you model or reconstruct an axial skeleton as a fixed structure, you are missing a significant portion of its functional reality. Another counter-intuitive point is that the auditory ossicles — the malleus, incus, and stapes — are technically part of the axial skeleton despite being tiny bones housed within the temporal bone. They are modified neural crest-derived structures, not typical skeletal elements. Beginners frequently omit them from their counts or classifications, which throws off the total bone count and suggests a gap in understanding developmental embryology. The sacrum is another area where people get tripped up. It is classified as a single bone in adults because the five sacral vertebrae fuse together, but in younger individuals it is five distinct vertebrae. If you are studying skeletal remains or imaging and see unfused sacral segments, that does not mean you are looking at five separate bones. It means you are looking at a younger individual. I once had a student who spent twenty minutes trying to identify five separate vertebrae in a pelvis specimen before realizing the fusion was incomplete due to the specimen's age.
Get the Full Details
Practical Applications and Real Problems
If you are working in 3D modeling, biomechanical simulation, or anatomical education, treating the axial skeleton as a collection of disconnected parts will create problems down the line. I ran into this specifically when building a cervical spine rig for animation. The common approach is to treat each cervical vertebra as an independent rigid body with simple rotation joints between them. This produces unnaturally smooth movement that does not match real biomechanics. The workaround I ended up using was modeling the cervical spine with coupled translation and rotation based on the actual facet joint orientations. The atlanto-occipital joint allows primarily flexion and extension with minimal rotation. The atlantoaxial joint handles most of the rotational movement. Below that, each segment contributes a small amount of multi-axis movement that compounds into the overall range of motion. Implementing this increased my development time by roughly three days on a project that was already behind schedule, but the result was dramatically more accurate and saved me from having to redo the entire rig later. For forensic or anthropological work, the axial skeleton provides some of the most reliable data for determining sex, ancestry, and age. The pelvis is actually the most sexually dimorphic region, but the axial skeleton contributes significantly. The thoracic cage shape differs between sexes — female cages tend to be more rounded and narrower, male cages broader and more barrel-shaped. Rib fragility patterns also differ, with females showing higher rates of anterior rib fractures in certain populations. These are not definitive on their own but become meaningful when combined with other indicators.
Limitations and When the Axial Skeleton Approach Fails
The axial skeleton as a classification system is useful but has real limitations. It breaks down when dealing with congenital anomalies. Variations such as cervical ribs, lumbarization of S1, or sacralization of L5 are relatively common — affecting roughly one to four percent of the population — and they blur the line between axial and appendicular classifications. A cervical rib is anatomically part of the axial skeleton but functionally more relevant to upper limb conditions like thoracic outlet syndrome. Pathology also complicates things. Degenerative disc disease, kyphosis, scoliosis, and osteoporosis change the axial skeleton's structure and function dramatically. If you are building any kind of predictive model based on normal axial skeleton anatomy, these conditions represent a significant failure mode. The models simply will not generalize well without accounting for pathological variation, and in many cases the predictive accuracy drops below what is clinically useful. When I need to assess axial skeleton function or pathology, I supplement anatomical study with imaging data — CT scans and MRI — because the soft tissue relationships matter almost as much as the bony structures. Ligaments, discs, and muscle attachments provide functional context that bone alone cannot convey. Relying solely on skeletal specimens or textbook diagrams gives you an incomplete picture, especially for clinical or biomechanical applications.