Understanding The Braden Scale In Real Practice
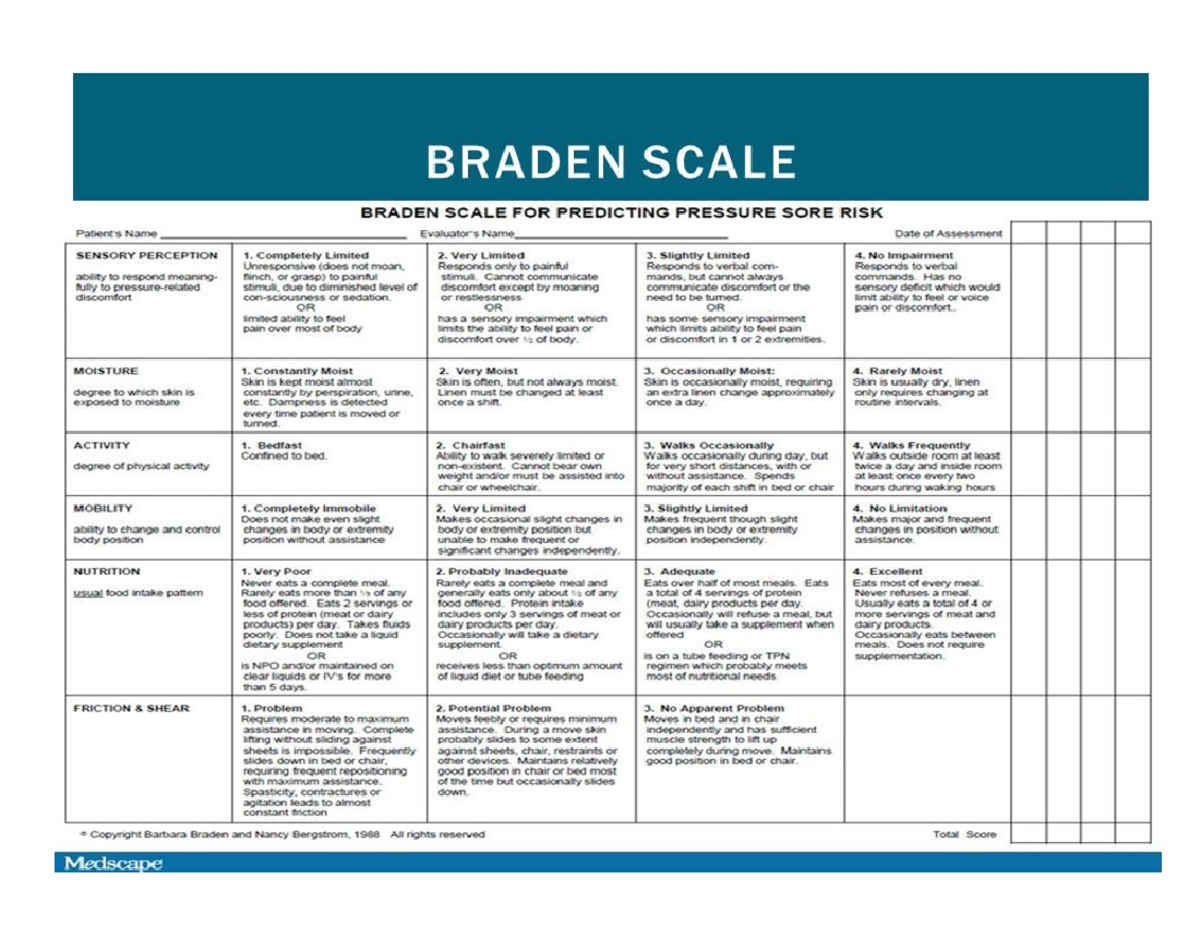
The Braden Scale is a clinical risk assessment tool for pressure ulcer development. It evaluates six domains: sensory perception, moisture, activity, mobility, nutrition, and friction and shear. Each domain receives a sub-score, and these combine into a total that categorizes a patient's risk level. It was developed by Barbara Braden and Nancy Bergstrom in 1987 and has been the standard in hospitals ever since. I've been using this on rounds for years, and the thing nobody tells you is that the total score almost never helps you do anything. It's the individual sub-scores that matter. A patient can come in at 14 overall and look "moderate risk," but if their friction and shear score is a 1 and their mobility is a 1, you have two specific problems to address immediately. Most people just write down the total and move on.
What Is The Braden Scale And How It Actually Works
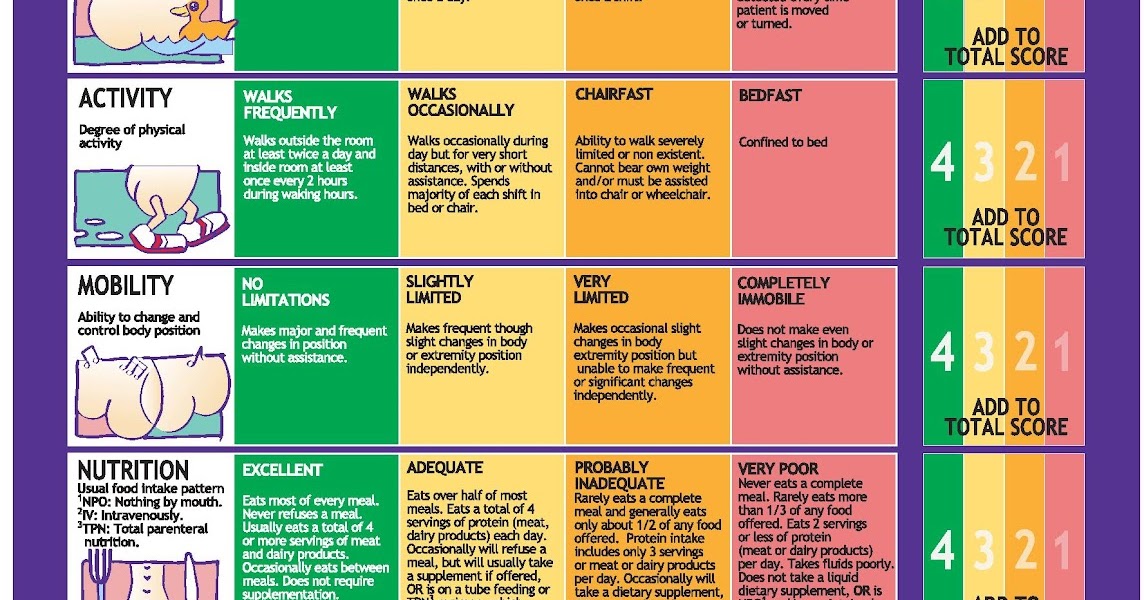
Here's the breakdown of each domain and what you're really assessing: Sensory Perception — Can the patient feel and respond to pressure discomfort? A score of 1 means completely unresponsive. A 4 means no impaired sensation. Most people get this wrong because they confuse "can feel touch" with "can feel pressure discomfort." A diabetic with neuropathy might feel light touch but not the deep ache of a bony prominence pressing into a mattress for four hours. Moisture — How often is the skin exposed to moisture? This ranges from 1 (constantly moist) to 4 (not rarely moist). The catch here is incontinence-associated dermatitis versus simple sweating. If a patient is incontinent but promptly cleaned and repositioned, they score differently than someone whose skin stays damp for hours. Document the timing, not just the presence of moisture.
Activity — What level of physical activity does the patient sustain? This is about ambulation and functional movement, not bedbound status alone. A 1 means bedfast. A 4 means walking frequently. I've seen this one misapplied on patients with limited mobility who still manage short walks — they should score a 2 or 3, not a 1. Mobility — Can the patient change and control body position independently? This is distinct from activity. A patient might be bedfast (activity score of 1) but able to shift themselves in bed (mobility score of 3). That distinction changes your turning protocol significantly. Nutrition — What's the typical food intake pattern? This is surprisingly hard to score accurately. A 1 means poor intake consistently. A 4 means almost always eats well. The problem is that albumin and prealbumin don't reliably reflect intake on a given day, and most nurses don't have concrete data. I've started requiring two days of actual intake logs before finalizing this score rather than guessing from memory.
Get the Full Details

Friction and Shear — How well can the patient move independently without sliding? This is scored 1 to 3. It's the most subjective domain and the one most prone to inflation. A patient who needs minimal assistance scores a 2. Someone who requires moderate to maximal assistance scores a 1. The problem is that on busy shifts, this score consistently goes up by a point. I've seen experienced nurses rate the same patient as a 2 in the morning and a 1 in the evening after watching them struggle to reposition. Total scores range from 4 to 19. Generally, scores of 9-12 indicate high risk, 13-14 moderate risk, 15-18 mild risk, and 19 is no risk. But these cutoffs aren't carved in stone — different facilities use slightly different thresholds, and the evidence actually supports risk starting to climb noticeably around 16. The biggest blind spot in this scale is perfusion. It completely ignores vascular status. I had a patient last year with severe peripheral arterial disease who scored 15 on the Braden — technically mild risk. Their skin was already showing discoloration over the malleoli from poor blood flow. The scale said they were fine. They weren't. Now I pair the Braden with a simple perfusion check — capillary refill, pedal pulses, skin temperature — before finalizing any assessment. The Braden alone will miss vascular-related pressure injury risk almost every time in that population.
Another issue is the learning curve. When your unit first implements the Braden Scale, inter-rater reliability is usually terrible. Two nurses can assess the same patient and end up with scores two or three points apart, usually on friction and shear and nutrition. I've found that the only fix is doing paired assessments for the first month — both nurses score independently, then compare and discuss differences until they converge. This usually brings the variance down to within one point, which typically takes about two weeks of consistent practice. The scale also doesn't account for medical devices. An oxygen cannula, a Foley catheter tube, a cervical collar — these can all cause pressure injuries in areas the Braden doesn't evaluate. I make it a habit to visually scan for any device contacting the skin, especially on patients scoring in the high-risk range, because the Braden won't flag those sites for you. If you need the official tool, the original Braden Scale questionnaire is available free from the publisher through standard clinical resource channels. Most hospital EHR systems also have it built into the admission assessment workflow, which saves you about ten minutes per patient compared to filling out a paper form.