Understanding The Cognitive Behavioral Model From A Practical Standpoint
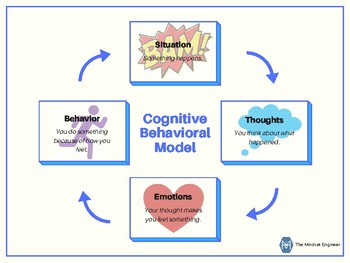
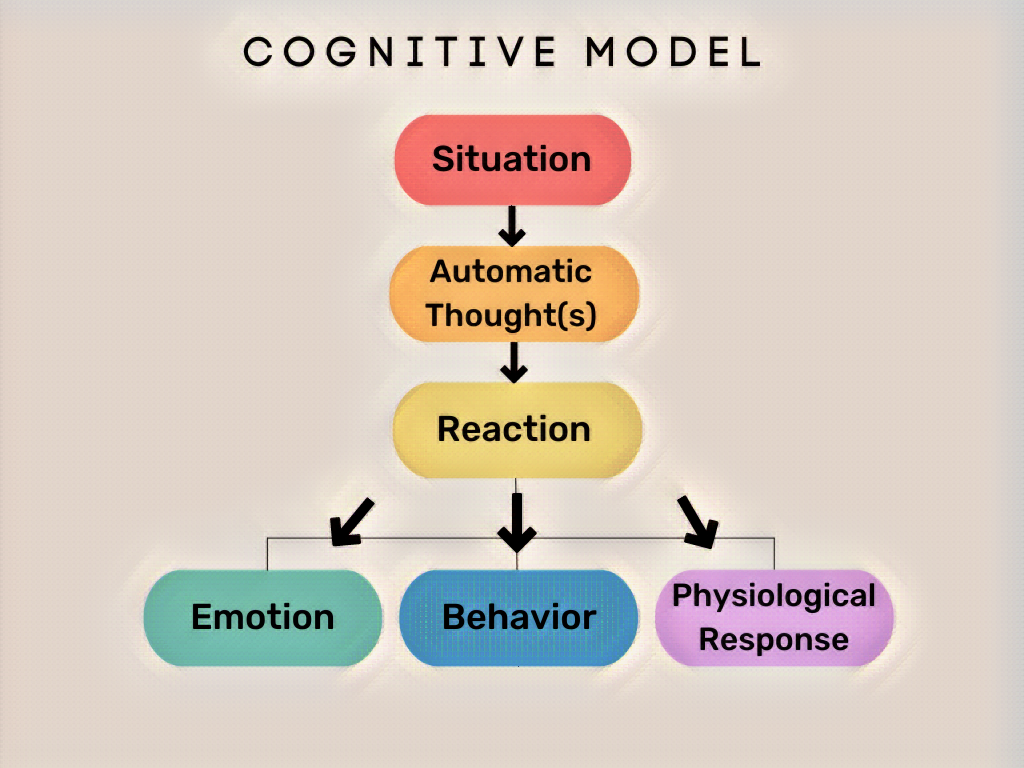
The cognitive behavioral model is a psychological framework that maps how thoughts, emotions, and behaviors feed into each other in real time. It was formalized by Aaron Beck in the 1960s and later refined into the more widely known cognitive triad and cognitive distortion taxonomy. At its core, the model proposes that it is not events themselves that cause distress, but the interpretations people assign to those events. That interpretation sits between the trigger and the response. Therapists call this the cognitive mediation principle. I spent years working with clients who came in saying their anxiety was unprovoked. In practice, very few cases were truly unprovoked. What usually happened was that the triggering thought occurred so fast the client could not identify it. The thought was implicit, automatic, and layered beneath a wave of physiological arousal. I learned to map backward from the emotion. If someone reported panic at 3 PM, I would ask what happened five minutes before, then ten, then fifteen. The cognitive model forces you to trace a chain: situation, automatic thought, emotional response, behavioral response. Breaking any link in that chain alters the outcome.
What Is The Cognitive Behavioral Model
The cognitive behavioral model describes a structured approach to understanding and changing maladaptive patterns. It rests on a few key assumptions. First, cognitions are accessible to awareness, even when they are automatic and fleeting. Second, cognitions mediate emotional and behavioral reactions. Third, changing distorted cognitions can produce measurable shifts in mood and behavior. These assumptions are not theoretical fluff. They translate directly into techniques like Socratic questioning, behavioral experiments, and thought records. A standard session often begins with psychoeducation. The therapist explains the model on a whiteboard or napkin. They draw a simple diagram: Situation -> Automatic Thought -> Emotion -> Behavior. Then they fill it in with a recent example from the client's life. This step alone changes how many clients view their problems. They stop seeing themselves as victims of external circumstances and start seeing themselves as participants in a feedback loop. That shift is often the most important part of the work. Here is where beginners get tripped up. They assume identifying a cognitive distortion is the same as resolving it. It is not. Naming a thought as catastrophizing or mind reading does nothing clinically until the client tests the thought against evidence. I had a client whose depression was maintained by a thought pattern I could see clearly from the first session. She believed she was a burden to everyone in her life. We spent six weeks reviewing her thought records before she ever challenged the core belief. The record keeping was not busywork. It revealed the frequency and context of the distortion across situations. Without that data, any attempt at cognitive restructuring would have been abstract and ineffective.
Another common pitfall is over-relying on thought records alone. Thought records capture surface-level cognition. They often miss the deeper schema-level beliefs that generate those surface thoughts. Schema beliefs are stable, broad, and resistant to challenge because they are held with high conviction. A client might record a thought like "I will fail this presentation" and then examine evidence for and against it. That works for the surface layer. But if the underlying schema is "I am inadequate," the surface thought will simply regenerate in a new context. Schema-focused CBT or techniques like chair work address this gap. I switched to a hybrid approach when I noticed my standard CBT protocol was plateauing around session eight with certain personality disorders. The model also has limits. It is not well suited for acute psychotic episodes where reality testing is impaired. It is less effective for conditions with strong neurobiological components when used in isolation, such as severe bipolar disorder or OCD without exposure and response prevention. It assumes a certain level of cognitive functioning and verbal ability. Clients with significant intellectual disabilities or severe dissociative symptoms often need adapted protocols. The model is also vulnerable to misuse by therapists who turn it into a rigid checklist rather than a flexible framework. When done mechanically, CBT becomes just another form of suggestion that clients comply with temporarily and reject at home. One practical detail that matters more than most people realize is the quality of the therapeutic relationship. The cognitive model works best when delivered with warmth and collaboration. Becks original term for it was "collaborative empiricism." The therapist and client work together as investigators. The therapist is not an authority who tells the client what to think. The therapist guides the client to test hypotheses about their own thinking. This distinction is critical. A therapist who comes in swinging with "that thought is irrational" will trigger resistance. A therapist who says "let us look at what evidence supports and contradicts that thought together" will get far more engagement.
Get the Full Details
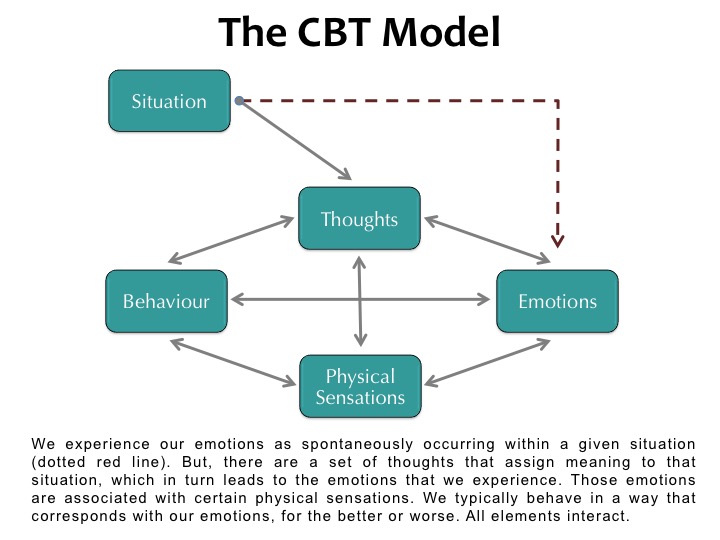
Behavioral activation is another piece of the model that gets underappreciated. Many clinicians focus almost exclusively on cognitive restructuring and neglect the behavioral side. But behavior change can precede cognitive change. Sometimes acting differently is how you get a client to doubt their distorted beliefs. I had a client with social anxiety who believed everyone was judging her negatively. We did not spend months analyzing her thoughts. Instead, we scheduled brief social exposures with a clear behavioral hypothesis. Each exposure tested the prediction. After three or four sessions, her cognitive distortions lost their grip because the data contradicted them directly. The behavior led the cognition. If you are studying this model or planning to apply it, start with the basic case formulation template. Map a single episode from your client or your own experience through the five components: triggering situation, automatic thought, emotion, physical sensation, and behavioral response. Do this for five different episodes. Look for patterns. The patterns reveal the cognitive distortions and the underlying schemas. From there, you build an intervention plan that targets the most disruptive links in the chain. The plan is never one size fits all. Different clients need more cognitive work, more behavioral work, or more schema work depending on where the maintaining factors sit. The model has stood up to decades of randomized controlled trials. It is one of the most empirically supported frameworks in clinical psychology. That does not make it perfect. No single model is. But it remains the default starting point for most evidence-based therapy training programs because it works, it is testable, and it gives clinicians a concrete way to organize complex human suffering into something manageable.