The Actual Difference Between CBT and Behavioral Therapy
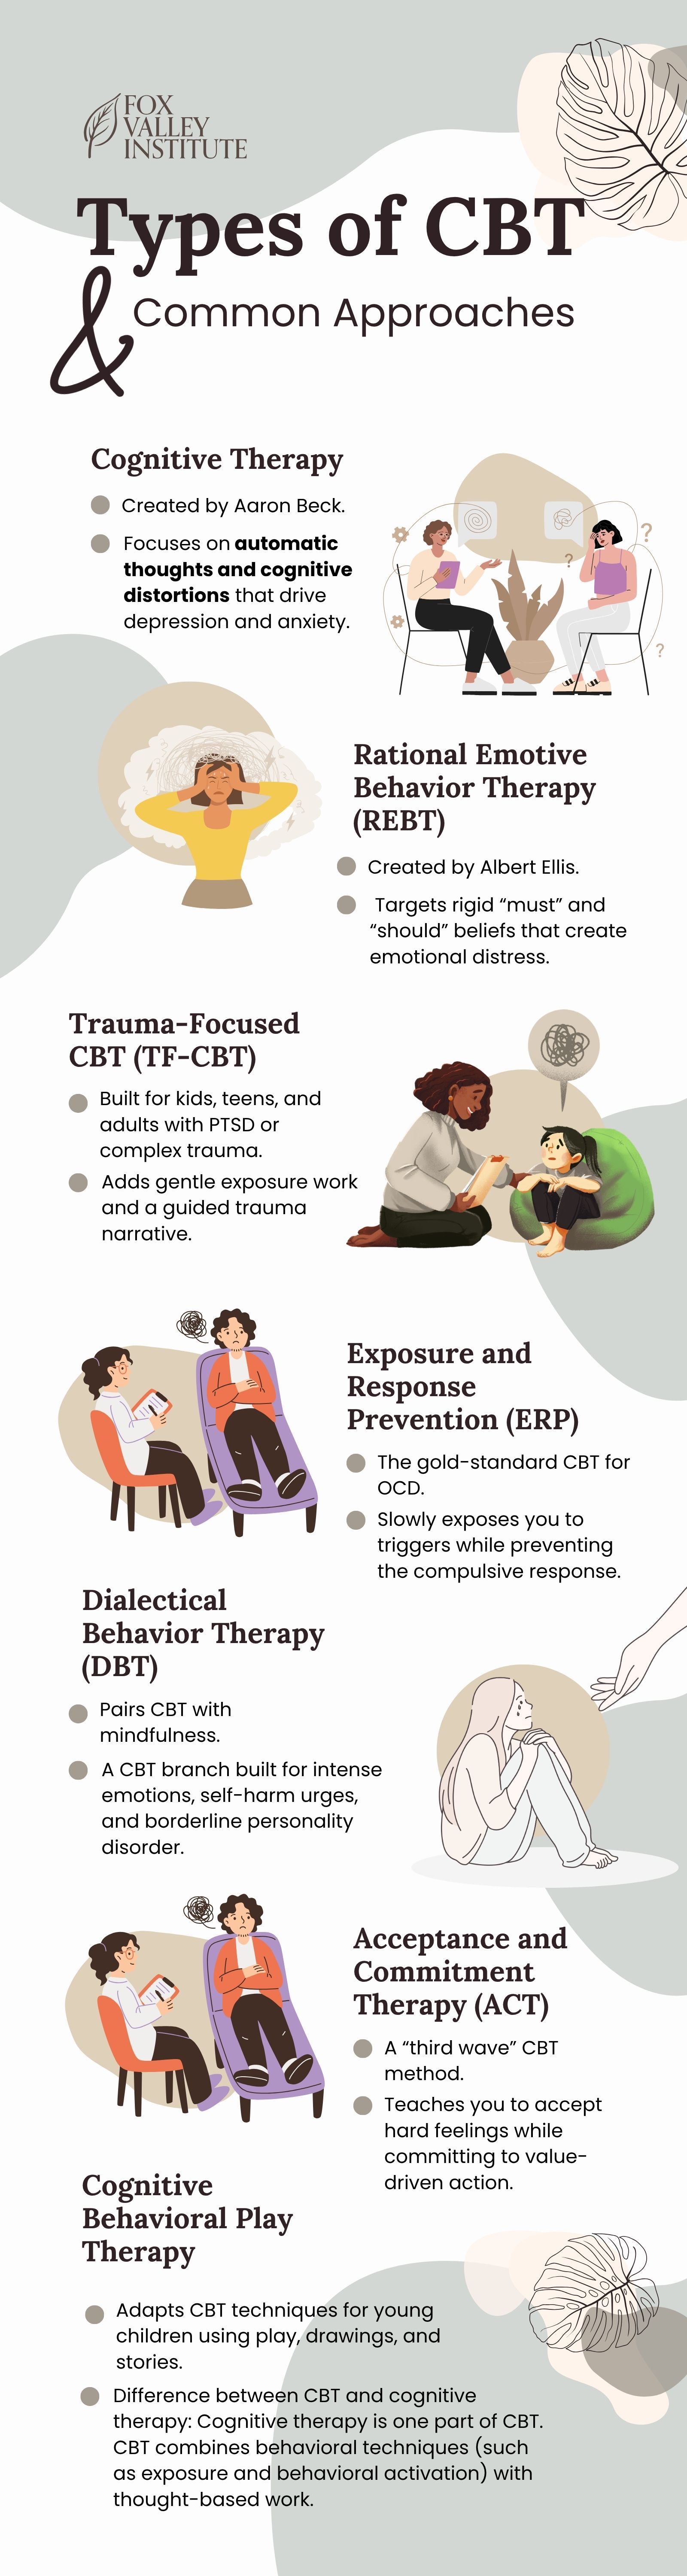
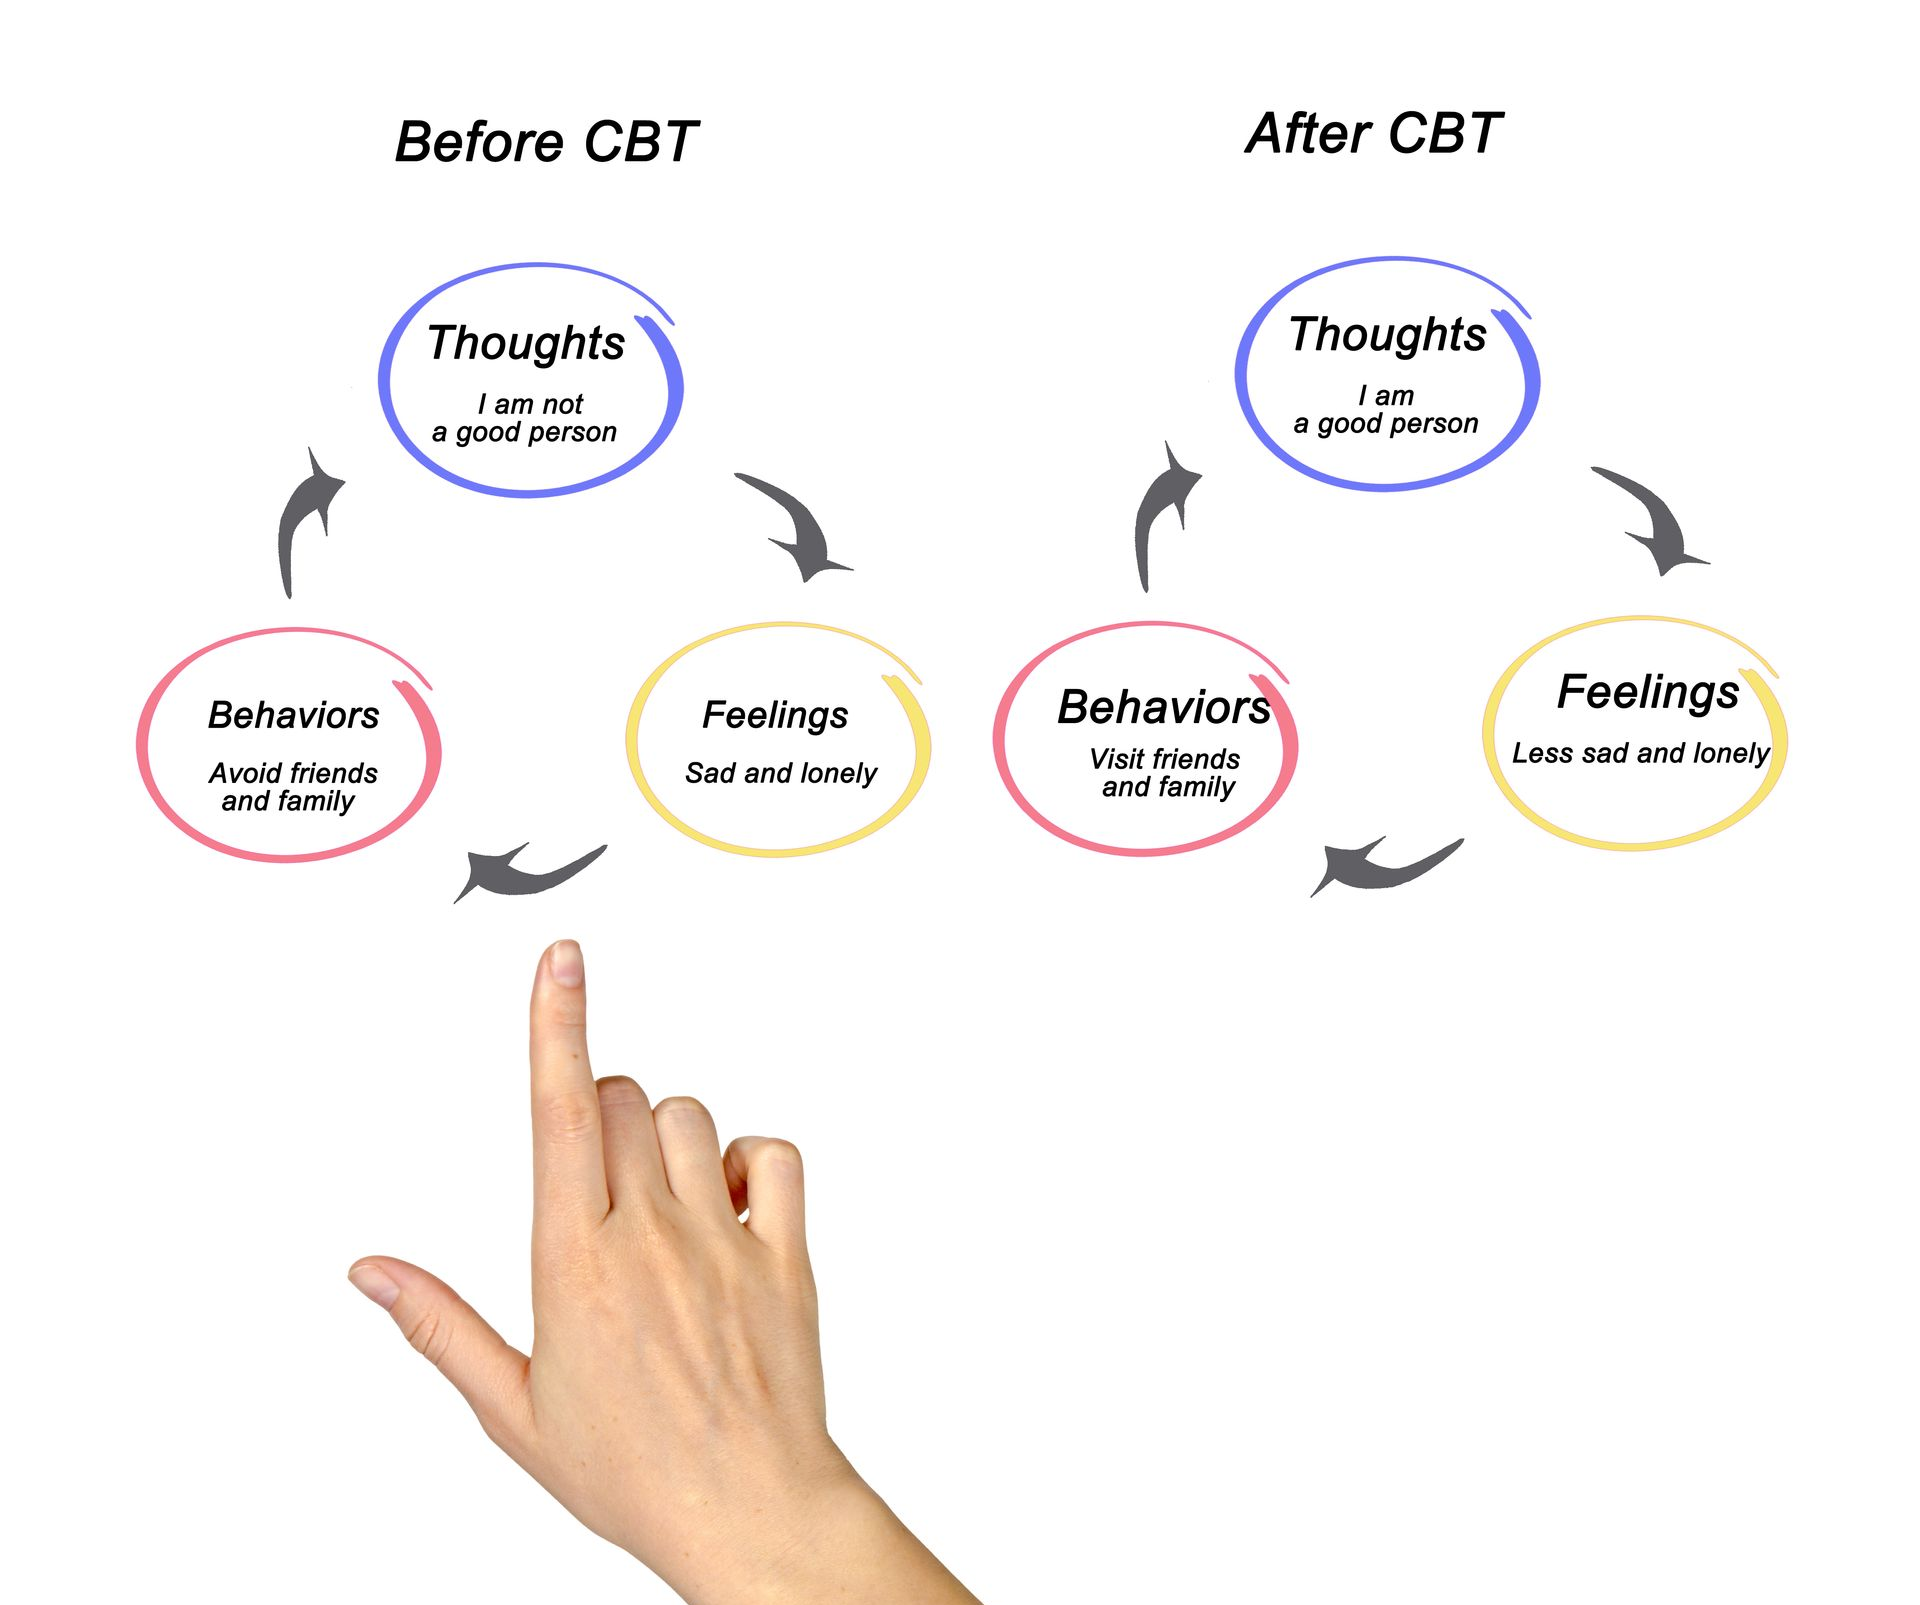
I spent years working in clinical practice before I even thought about writing this. People toss these terms around like they mean the same thing, which is annoying because they aren't interchangeable. Let me just lay it out straight. Behavioral therapy is the older, narrower umbrella. It comes from behaviorism—Watson, Skinner, Pavlov territory. The core idea is that maladaptive behaviors are learned and can be unlearned through conditioning. You don't spend much time digging into thoughts or feelings. You identify the behavior, you introduce a new stimulus or consequence, and you measure whether the behavior changes. Exposure therapy, systematic desensitization, aversion therapy—those fall under behavioral therapy. They're all about changing what people do, not what they think. CBT, or Cognitive Behavioral Therapy, split off later. It took the behavioral framework and grafted cognitive processes onto it. The assumption is that your thoughts mediate your emotions and behaviors. So you don't just change the behavior; you also challenge the thoughts driving it. You identify cognitive distortions, test them against evidence, and restructure them. The behavioral piece is still there, but now it's paired with cognitive work.
What Is The Difference Between Cbt And Behavioral Therapy
Here's the thing most guides miss: the difference isn't just academic. It changes how you actually run a session. In pure behavioral therapy, I might have a client with a phobia and set up a graded exposure hierarchy without asking them to journal about their fear beliefs. We'd track heart rate, self-reported anxiety, and behavioral avoidance scores. That's it. In CBT, I'd ask them to write down the automatic thought "the elevator will crash," examine the evidence for and against it, generate alternative thoughts, and then do the exposure while testing those new cognitions. One practical edge case I ran into: a client with OCD who had contamination fears. Pure behavioral therapy would mean exposure and response prevention—touching doorknobs and not washing. That works, but I found the cognitive piece was the sticking point. He'd do the exposure, but afterward he'd ruminate for forty-five minutes rewriting the event in his head to make it feel "safe." The behavioral work was being undone by the cognitive compulsion. So we added a metacognitive layer—challenging his belief that thinking about contamination was functionally equivalent to encountering it. That's not standard behavioral therapy. That's CBT territory. Another nuance people overlook: behavioral therapy doesn't require the client to be verbal or insight-oriented. I've run successful behavioral interventions with clients who have limited cognitive capacity, severe intellectual disabilities, or acute psychosis where cognitive restructuring would be counterproductive. You can do stimulus control, habit reversal, and reinforcement scheduling without needing someone to articulate their thought patterns. CBT struggles in those contexts because the "cognitive" part demands a level of abstract reasoning that isn't always available.
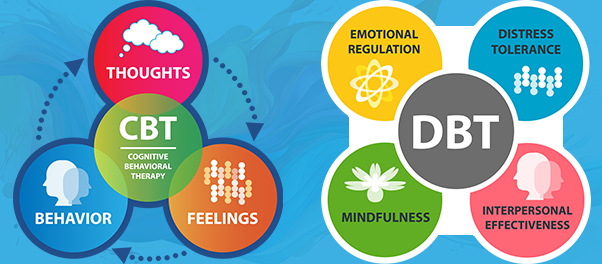
On the flip side, CBT has its own bottleneck. It's time-limited by design—typically twelve to twenty sessions. That's a feature for insurance companies and public health systems, but it's a bug if you're dealing with complex trauma or personality disorders where the cognitive distortions are deeply woven into identity. Behavioral approaches like Dialectical Behavior Therapy, which came from Linehan and has roots in both behavioral and acceptance strategies, handle some of that ground better. Not because they're superior, but because they acknowledge that pure cognitive restructuring can feel invalidating to someone whose entire worldview is shaped by chronic relational trauma. If you're looking to actually use this distinction instead of just knowing it, start by mapping your client's presenting problem. Is it primarily a behavior that needs changing? Maybe a tic, a habit, a phobic avoidance? Behavioral therapy might get you there faster. Is it a pattern of anxious thoughts maintaining avoidance or depression? CBT gives you more tools there. When both are present—and they usually are—you blend them, but you lead with whichever lever produces measurable change first.
Get the Full Details