How Psychodynamic Therapy Actually Works When You Strip Away the Textbooks
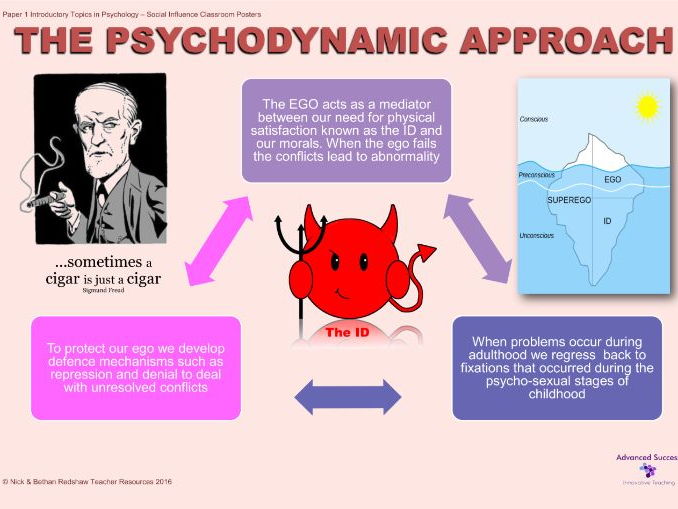
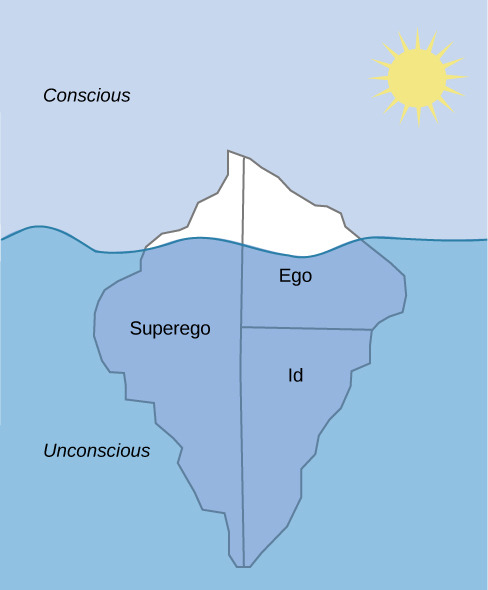
I first encountered the psychodynamic perspective in graduate school, where we spent three semesters trying to map every behavior back to childhood attachments and defense mechanisms. It seemed elegant on paper. Reality is messier. A patient comes in with depression, and your job isn't to diagnose their repressed anger at a mother who died when they were six. Your job is to keep the room steady while they find words for something that's been operating below awareness since before they had language. At its core, the psychodynamic perspective is a framework for understanding human behavior through the lens of unconscious processes and early relational patterns. It assumes that much of what drives us isn't accessible to conscious reflection, that earlier relationships—especially with caregivers—create templates we replay without realizing it, and that bringing these patterns into awareness can change them. This isn't one theory. It's a cluster of theories, starting with Freud and extending through Klein, Winnicott, Kohut, Bion, and dozens of others who refined or split away from each other over a century. The key mechanisms people actually use in clinical work are transference, resistance, defense, and the repetition compulsion. Transference is when a patient redirects feelings from an important past figure onto the therapist. Resistance is everything that keeps material unconscious. Defense mechanisms—repression, projection, splitting, intellectualization—are the psychic operations that maintain the status quo. The repetition compulsion is the stubborn habit of reenacting old relational dynamics even when they're painful or self-defeating.
The Practical Mechanics You Won't Find in Intro Courses
Here's what the textbooks leave out. Psychodynamic work is slow by design. It's not a brief intervention. The average course runs 45 to 90 minutes per session, two or three times a week, over months or years. The length matters because unconscious material surfaces gradually through the therapeutic relationship, not through direct questioning. You can't ask someone directly about their Oedipus complex and get honest data. But you can notice how they respond when you're five minutes late, or when you smile at them in a way that reminds them of a parent, or when they suddenly fall silent mid-sentence. The technique that does most of the work is interpretation. Not every utterance counts as an interpretation. An interpretation connects a current pattern to its historical origin or unconscious meaning. A good interpretation lands when the patient has some emotional experience of it. If you offer an interpretation and they simply agree intellectually, you've missed something. They need to feel the connection, not just understand it cognitively. Countertransference—the therapist's emotional response to the patient—isn't a problem to eliminate. It's a tool. When I worked with a young woman who consistently arrived ten minutes late and then apologized profusely, I noticed I felt impatient and then guilty about feeling impatient. That guilt was useful data. She was recreating her dynamic with a father who demanded perfection and punished any sign of frustration. My countertransference let me feel what she made others feel, which gave me a window into her relational world.
Where Psychodynamic Theory Actually Fails
Let me be blunt about the limitations. Psychodynamic therapy has weak evidence for certain conditions. For simple phobias, acute grief reactions, or mild situational anxiety, it's overkill. Cognitive-behavioral therapy reaches similar outcomes in fewer sessions for those problems. The data from the APA Division 12 task force and multiple meta-analyses shows psychodynamic therapy excels for personality disorders, chronic depression, and complex trauma—conditions where the underlying structure of relating needs changing, not just symptoms suppressing. The biggest methodological problem is falsifiability. Many psychodynamic constructs resist empirical testing. Drive theory, the Oedipus complex as universal, the precise age stages Freud proposed—most of this didn't hold up. Good psychodynamic clinicians don't treat these as dogma. They treat them as useful metaphors. The real contribution of the perspective isn't the specific theory of psychosexual development. It's the recognition that unconscious motivation exists, that early relationships shape later functioning, and that the therapeutic relationship itself is a vehicle for change. Another honest limitation: psychodynamic training is expensive and time-consuming. In the United States, most psychodynamic programs require two to four additional years of supervised clinical work beyond a master's or doctoral degree. This creates access inequality. The populations that need depth-oriented therapy most often can't access it because of cost and availability. I've watched patients with genuine personality-level pathology sit on waiting lists for fourteen months while better-matched brief therapies sat empty.
Get the Full Details

A Specific Problem I Encountered and How I Worked Around It
Early in my training, I had a patient whose transference was so intense I couldn't distinguish between his feelings about me and his feelings about his therapist before me. He was idealizing one and devaluing the other in ways that shifted weekly. The standard psychodynamic move would've been to interpret the split immediately. But doing so would've felt like I was taking his side in an internal family war, which is exactly the dynamic he was enacting with his caregivers. Instead, I slowed down. I stopped offering interpretations for six weeks. I stayed present with the intensity without collapsing into either the idealized or hated role. This is called holding, a concept from Winnicott that's easier to name than to do. The breakthrough came when he said, almost offhand, that he'd had the same experience with every therapist he'd ever seen. That observation, coming from him rather than extracted from me, was the interpretive moment. It carried far more weight because it was his discovery, not my diagnosis.
The Modern Landscape
Contemporary psychodynamic therapy has moved significantly from classical Freudian analysis. Short-term psychodynamic psychotherapy (STPP) typically runs 16 to 30 sessions and focuses on a specific relational pattern rather than global personality restructuring. Mentalization-based treatment, derived from psychodynamic theory but adapted for borderline personality disorder, has solid RCT support. Attachment-based couples therapy similarly borrows the core insight—that early bonding shapes adult intimacy—while working within a structured format. If you're studying this perspective, don't treat it as a single doctrine. Read Freud for historical context. Read object relations theorists like Fairbairn and Ogden for the relational turn. Read contemporary integrations like Shedler for the empirical evidence base. Read criticism from cognitive and behavioral traditions to understand where the framework genuinely struggles. The best psychodynamic clinicians I know are honest about both the power and the limits of their approach. The bottom line is practical, not philosophical. The psychodynamic perspective teaches that behavior has causes that aren't immediately visible, that relationships repeat patterns formed long ago, and that awareness within a reliable relational context can alter those patterns. Whether you're a clinician, a student, or someone trying to understand their own recurring difficulties, that's a framework worth knowing—even if you ultimately use something else alongside it.