Understanding Why Alcohol Becomes Hard to Stop
Alcohol addiction isn't a moral failing or a character flaw. It's a measurable shift in how the brain processes reward, stress, and decision-making. The psychology behind alcohol addiction centers on three systems that progressively hijack each other: the reward pathway, the stress response, and the prefrontal cortex. Once these systems interact long enough, drinking stops being a choice and starts being a physiological necessity. I spent several years working with clients who were "high-functioning" alcoholics. The standard definitions didn't fit them because they held jobs and maintained relationships while consuming enough ethanol to fill a bathtub. The real indicator I learned to look for wasn't how much they drank, but what happened the day after. One client, a 42-year-old project manager, could go a full week without a drop but would still experience a spike in anxiety every afternoon at 4:30 PM. That was his brain signaling that it expected alcohol to offset the accumulating cortisol from work stress. The timing was precise. The expectation was conditioned. That pattern alone is more predictive of clinical alcoholism than total volume ever is.
What Is The Psychology Behind Alcohol Addiction
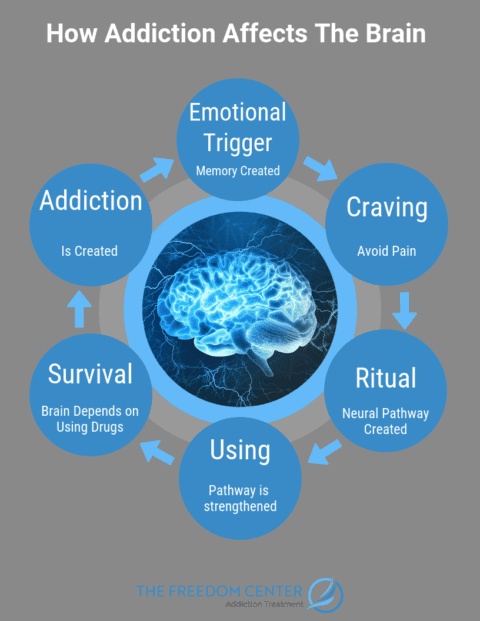
The core mechanism involves dopamine regulation in the nucleus accumbens. Alcohol causes a surge of dopamine that exceeds anything natural rewards produce. Over repeated exposure, the brain downregulates its own dopamine receptors to compensate. This means two things happen simultaneously. Natural rewards like food, social interaction, and achievement no longer register as satisfying. And the baseline mood drops below normal, creating a chemical deficit that only alcohol can temporarily correct. The stress system plays an equally critical role. Chronic alcohol use dysregulates the hypothalamic-pituitary-adrenal axis. GABA receptors, which normally calm neural activity, become desensitized. Glutamate receptors, which excite neurons, become overactive. The result is a brain that is permanently stuck in a state of hyperarousal when not drinking. Anxiety, insomnia, and irritability aren't side effects of withdrawal. They are the new normal for an alcohol-dependent nervous system. Prefrontal cortex impairment is where the behavioral control breaks down. This region handles impulse regulation, long-term planning, and consequence evaluation. Alcohol suppresses prefrontal activity. With continued use, the structural connectivity in this area degrades. Studies using MRI scans show reduced gray matter volume in the dorsolateral prefrontal cortex of chronic drinkers. The person isn't making bad decisions because they're weak. Their capacity to make good decisions is chemically compromised.
A common misconception is that addiction is purely about the positive reinforcement of getting drunk. The negative reinforcement component is actually what maintains long-term dependence. Drinking stops the withdrawal symptoms. This distinction matters enormously for treatment. Programs that only address the pleasure-seeking behavior miss the larger picture. The person drinks primarily to feel normal, not to feel good. I worked with a woman in recovery who explained that her cravings hit hardest not when she was stressed, but when she was completely relaxed. She called it the "Sunday afternoon trap." Her brain had associated the absence of stress with the opportunity to drink because those were the moments she used to allow herself to let loose. The workaround was straightforward but counterintuitive. She scheduled high-engagement activities for exactly those times. Not passive activities like watching TV, but activities that required cognitive focus. Coding puzzles, learning guitar chords, anything that occupied the prefrontal cortex directly. It wasn't about distraction. It was about keeping the impaired decision-making region actively engaged so it couldn't default to autopilot. The conditioning aspect is often underweighted in public understanding. Environmental cues trigger craving pathways almost instantaneously. A specific brand of beer on television, the sound of a fridge door closing, the particular texture of a barstool. These stimuli activate the same neural circuits as the alcohol itself. Classical conditioning, the same mechanism behind Pavlov's dogs, operates here with devastating efficiency. For someone in early recovery, simply walking past a liquor store can trigger a measurable cortisol spike and dopamine craving within seconds.
Get the Full Details
Personality factors do play a role, but not in the way self-help books typically frame them. It's not that certain personality types are more prone to addiction. Rather, pre-existing conditions like depression, anxiety disorders, and ADHD significantly increase risk because self-medication becomes a plausible explanation for why drinking feels useful. People with untreated ADHD particularly struggle because alcohol temporarily improves focus by modulating dopamine and norepinephrine pathways. The short-term benefit creates a powerful reinforcement loop that overrides long-term consequences. Treatment approaches vary in effectiveness depending on which psychological mechanism is dominant in the individual. Cognitive behavioral therapy works well for people whose addiction is primarily driven by conditioned environmental cues and maladaptive thought patterns. It retrains the brain's response to triggers through structured identification and replacement. Medication-assisted treatment like naltrexone or acamprosate addresses the neurochemical imbalance directly. Naltrexone blocks opioid receptors, reducing the euphoric effect of alcohol. Acamprosate helps stabilize the glutamate-GABA imbalance that persists after cessation. The combination of both approaches produces significantly better outcomes than either alone. A 2021 study in the journal Addiction found that patients receiving both medication and CBT had a 68% abstinence rate at six months compared to 43% for medication-only and 38% for therapy-only. The numbers are clear. Addressing only the behavior without the biology leaves most people vulnerable to relapse. Addressing only the biology without teaching coping skills creates a different kind of vulnerability.
Relapse patterns follow predictable trajectories that most people don't recognize until they're in the middle of one. It typically begins with a cognitive relapse where the person starts fantasizing about drinking, rationalizing it, or reminiscing about past experiences. This is followed by an emotional relapse where mood instability and unresolved emotions create internal pressure. The final stage is a mental relapse where the person is actively deciding whether to drink and weighing the pros and cons. By the time physical relapse occurs, the window for intervention has largely closed. The most overlooked factor in long-term recovery is social environment. Recovery isn't sustainable in the same social circles that enabled the addiction. This isn't about judging friends. It's about recognizing that every interaction with someone who drinks recreationally reinforces neural pathways associated with drinking behavior. People in recovery need to rebuild their social infrastructure with individuals who don't drink. This is practically difficult but neurologically necessary. There's also the issue of polydrug use that complicates the psychology considerably. Many people with alcohol use disorder also use cannabis, benzodiazepines, or opioids. Each substance affects the reward pathway differently but they interact in ways that make the underlying addiction more entrenched. A person might stop drinking but continue using cannabis, which maintains the avoidance coping pattern that originally drove the alcohol use. Untangling these patterns requires professional assessment rather than DIY recovery approaches.
The timeline for neural recovery varies significantly between individuals. Some cognitive function improvements appear within weeks of abstinence. Structural brain changes can take six to twelve months to show measurable improvement on imaging studies. But the timeline is unreliable for clinical purposes because many people use the concept of "my brain needs time to heal" as implicit permission to continue drinking. The accurate framing is that abstinence allows the brain to begin healing, but the healing is incomplete without sustained behavioral change and often ongoing support. One important limitation to acknowledge is that current psychological models don't fully explain why some people with identical consumption patterns never develop addiction. Genetics account for roughly 50-60% of vulnerability, but the remaining variance involves epigenetic factors, early life trauma, gut microbiome composition, and numerous variables we're still researching. No single psychological framework captures the complete picture yet. The practical takeaway is straightforward. Alcohol addiction is a chronic neurological condition with identifiable mechanisms. Understanding those mechanisms reduces shame and increases the likelihood of effective intervention. The most effective approach combines pharmacological support, behavioral therapy, environmental restructuring, and long-term monitoring. Short-term solutions rarely produce lasting results because the underlying neurochemistry doesn't resolve on its own.