How Reabsorption Actually Works in Dialysis
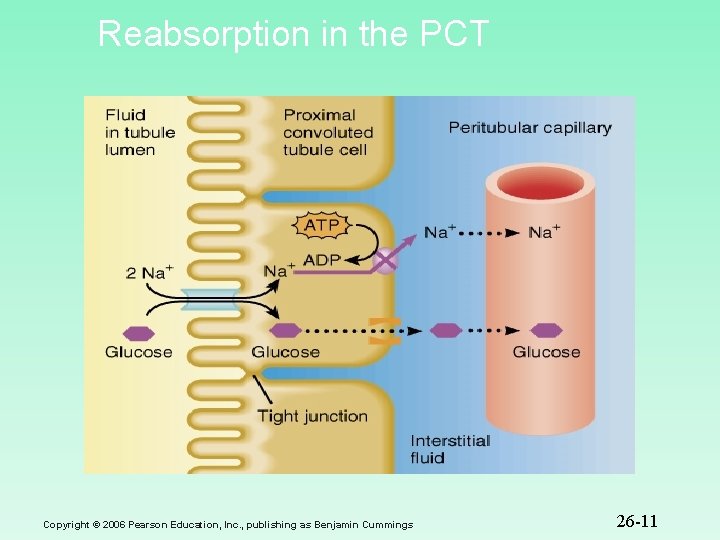
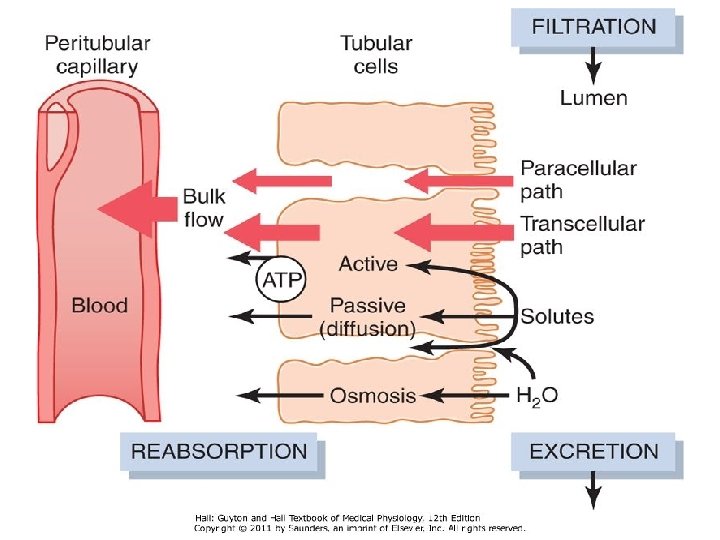
The term is a bit of a misnomer when we talk about blood purification, because nobody is actually reabsorbing anything the way a kidney does. What happens in hemodialysis is the reverse of what your tubules do. Your kidneys actively reclaim glucose, amino acids, and bicarbonate from the filtrate. Dialysis machines don't reclaim anything at all. They remove waste by running blood alongside a dialysate fluid, and the only thing moving across the membrane is whatever passes by diffusion, convection, or ultrafiltration. I've seen this confusion come up constantly when engineers design new membrane coatings or when clinicians explain treatment protocols to patients who've never had the procedure before. The wording matters because it shapes expectations about what the machine can and cannot do.
What Is The Reabsorption Process In Blood Purification
In the context of blood purification, reabsorption refers to the back-diffusion of certain solutes from the dialysate side into the blood compartment. This is not an active process. It happens because the concentration gradient can shift during treatment, and some molecules move in both directions depending on what the dialysate contains. Bicarbonate is the clearest example. The dialysate is set to a specific pH and bicarbonate level, usually around 30 to 35 millimoles per liter. If the patient's blood bicarbonate rises above that during treatment, bicarbonate will move out of the blood and into the dialysate. But if the bath concentration is higher than the patient's serum level, bicarbonate moves the other way. That backward movement is what people sometimes call reabsorption, though it's just simple Fickian diffusion across a semipermeable membrane. Glucose appears in dialysate used for peritoneal dialysis because dextrose is added as an osmotic agent. Small amounts of glucose can cross the peritoneal membrane and enter the bloodstream during a dwell. That is a real reabsorption event in the clinical sense, and it matters for diabetic patients who are already managing blood sugar. I've had cases where a patient's insulin requirement shifted overnight after a long peritoneal session simply because of glucose load they weren't accounting for.
The Membrane Dynamics You Need to Understand
The choice of membrane material determines what crosses and what stays. High-flux polysulfone membranes have larger pores than low-flux cuprophane membranes, so they allow middle molecules like beta-2 microglobulin to pass more readily. But high-flux membranes also allow more albumin loss, sometimes 5 to 15 grams per treatment session depending on the transmembrane pressure and the specific product. That's a significant amount if you're treating a malnourished patient. Convection-based therapies like hemodiafiltration use replacement fluid pushed into the blood stream during ultrafiltration. This brings solutes back into circulation that would otherwise be removed. Some of that is deliberate—keeping electrolytes balanced—but it also means you're partially offsetting the clearance you're trying to achieve. The trade-off is real and it's something you calculate before starting the treatment, not something you discover mid-session. I once worked with a machine setup where the online hemodiafiltration system was delivering replacement fluid at a rate that exceeded the ultrafiltration target. The result was net fluid gain instead of fluid removal. The alarm didn't trigger because the individual parameters looked fine on their own. It took about twenty minutes of watching the weight curve before someone noticed the imbalance. We switched to pre-dilution mode and reduced the replacement volume until the net ultrafiltration matched the prescription. That kind of error doesn't show up in any textbook. It shows up when the pump curves drift and nobody is checking the mass balance every few minutes.
Get the Full Details
What Actually Gets Removed Versus What Stays
Small solutes like urea and creatinine clear efficiently with standard treatments. Urea Kt/V targets are well established, and you can predict clearance within a reasonable range based on blood flow rate, dialysate flow rate, and membrane surface area. Middle molecules are harder. Beta-2 microglobulin clearance varies wildly depending on membrane type and treatment mode. Larger proteins are effectively impossible to remove without also losing albumin, and that's why plasma adsorption columns and hemoperfusion exist as niche alternatives for specific toxins. Sodium management is another area where reabsorption dynamics matter clinically. If the dialysate sodium is set too high, patients retain more fluid between sessions and become hypertensive. If it's set too low, cramping and hypotension become frequent problems. The dialysate sodium profile can be adjusted during treatment—starting higher and tapering down—but that requires a machine capable of sodium modeling and a trained operator who understands what's happening. I've seen protocols where the sodium profile was programmed incorrectly and the patient ended up with a post-dialysis sodium of 152, which caused severe thirst and aggressive fluid intake afterward. The machine display looked normal the entire time.
The Problems Nobody Talks About
Membrane biocompatibility affects complement activation and cytokine release. Old-generation dialyzer materials activated the complement system more aggressively than modern synthetic membranes, leading to chest pain and hypoxia during the first fifteen minutes of treatment. That reaction isn't reabsorption, but it's part of the same conversation about what happens when blood meets an artificial surface. Modern membranes are better, but they're not inert. Protein fouling still occurs on the blood side of the membrane during treatment, and that fouling layer changes clearance characteristics over time. Urea clearance drops slightly as the membrane ages in use, and convective transport becomes less efficient. Potassium management depends entirely on the dialysate potassium concentration. Standard baths use 2.0 milliequivalents per liter, but some patients need 1.0 or even zero potassium in the bath if their pre-treatment levels are extremely high. The risk with low-potassium baths is arrhythmia during treatment, especially in patients with underlying cardiac disease. I've pulled two patients out of atrial fibrillation during a session where the potassium bath was set to zero. Their pre-treatment potassium was 7.2, so the clinical reasoning was sound, but the rapid shift triggered dysrhythmia anyway. We switched to a 1.0 bath and stabilized the rhythm. The lesson was obvious in retrospect, but it wasn't something I'd read anywhere. It was something I learned because it happened. Anticoagulation strategy also interacts with the reabsorption conversation. Heparin is standard, but citrate regional anticoagulation is used for patients with bleeding risks. Citrate binds calcium in the blood before it enters the filter, preventing clotting. Calcium is then replaced in the venous line after the blood returns to the patient. The citrate itself doesn't cross the membrane significantly, but calcium management is critical. If the replacement fluid calcium concentration is wrong, the patient can develop hypocalcemia or hypercalcemia rapidly. I worked a shift once where the citrate pump was running correctly but the replacement fluid bag had been mislabeled. The patient's ionized calcium dropped to 0.7 millimoles per liter within forty minutes. We caught it on routine monitoring and stopped the citrate, but it was close. Labeled fluids matter more than you'd think when the machine is doing the calculations for you.
When This Approach Doesn't Work
Conventional hemodialysis with its reliance on diffusion and convection simply cannot replace continuous renal replacement therapy (CRRT) for hemodynamically unstable patients in the ICU. CRRT removes solutes slowly over twenty-four hours using continuous venovenous hemofiltration or hemodialysis. The slower rate means less fluid shift, less hypotension, and better tolerance. If you try to run a standard three-hour hemodialysis session on a patient who can't maintain blood pressure, you'll crash them. That's not a matter of adjusting the dialysate. It's a matter of choosing the right modality from the start. Plasma exchange and immunoadsorption handle toxins that dialysis membranes can't touch. Autoantibodies, immune complexes, and large protein-bound toxins require entirely different technology. Saying that reabsorption in blood purification handles these cases would be inaccurate. These procedures use centrifugation, affinity columns, or specific adsorbent materials. They're expensive, they require specialized equipment, and they're not universally available. But they're the only option for conditions like thrombotic thrombocytopenic purpura or severe sepsis with toxin loads that conventional dialysis can't address. The fundamental limitation of any diffusion-based blood purification method is protein binding. Drugs and toxins that are highly bound to albumin or other plasma proteins don't clear well because only the free fraction is available to cross the membrane. Valproic acid overdose is a decent example. It's highly protein-bound, so standard hemodialysis removes very little of it. You need high-flux membranes, prolonged treatment, and sometimes multiple sessions before you see meaningful clearance. Even then, the numbers are modest compared to what you'd get with an unbound toxin.
What to Watch For in Practice
Monitor bicarbonate trends during treatment, not just the pre- and post-values. A flat or rising bicarbonate level when you expect it to drop suggests inadequate dialysate flow or a membrane that's fouling faster than usual. Check the conductance readings on the dialysate side. If they drift from the expected value, the mixture of concentrate and water may be off, and that affects every solute transport occurring in real time. Track albumin loss if you're using high-flux membranes for prolonged treatments or hemodiafiltration. A drop of more than 0.5 grams per deciliter between sessions is worth investigating. It could be membrane-related, or it could signal inflammation increasing capillary permeability. Either way, ignoring it leads to cumulative protein depletion over weeks. Document the actual ultrafiltration volume against the prescribed volume. Machines report theoretical values based on pump settings, but line priming, filter compaction, and venous pressure changes all affect real-world performance. I've seen discrepancies of 400 milliliters or more between what the machine said was removed and what the patient actually lost, and those discrepancies matter when you're managing a patient on the edge of volume tolerance.