TF-CBT for Adults: What It Actually Looks Like
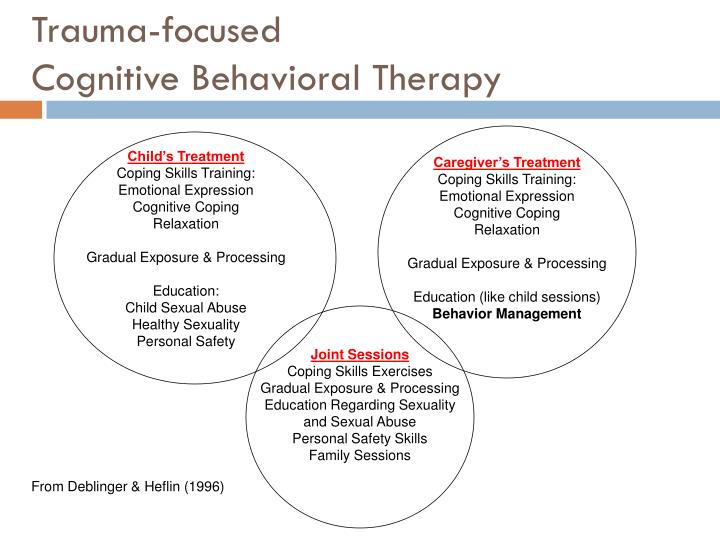
Trauma-Focused Cognitive Behavioral Therapy is a structured, time-limited approach that helps people process and work through the effects of traumatic experiences. It combines cognitive behavioral techniques with elements specifically designed to address trauma memories and their lingering impact. For adults, it tends to run between 8 and 25 sessions depending on complexity, and it pulls from both cognitive restructuring and exposure-based methods. TF-CBT was originally developed for children and adolescents, which is why a lot of people get confused about whether it even applies to grown-ups. The model got adapted for adult populations because researchers found the core components held up well. It's not the same as standard CBT where you might just work on general anxiety or depression. The trauma focus changes everything about the pacing and the way you approach the work. The typical session structure involves psychoeducation early on, followed by skill-building around emotional regulation and coping, then gradual processing of the traumatic memory through narrative work or controlled exposure. The cognitive pieces address distorted beliefs that often come from trauma, like self-blame or a shattered sense of safety. All of this happens within a predictable framework so the client knows what's coming next.
I spent years working with complex trauma cases before I really understood where TF-CBT fell short. There's a specific problem that comes up pretty regularly with adults who've experienced prolonged interpersonal trauma, and it's this: the standard trauma narrative component can actually feel retraumatizing if you move too fast. I had a client a few years back, someone with a history of chronic childhood abuse, who was doing fine in the skills phase. Everything seemed on track. Then we started the narrative portion and she had severe dissociative episodes during the exposure work. Standard protocol says you slow down and spend more time in psychoeducation and coping skills. But the real fix was adding in some grounding techniques and doing a modified version of the narrative where she wrote the account first rather than telling it out loud. Hearing her own voice describe the trauma was too much. Writing let her control the pace. That adjustment saved the whole thing from falling apart. Here's something most people don't realize about TF-CBT with adults: the cognitive restructuring piece is often the part that gets short-changed, but it's usually the most important for long-term outcomes. You can process a memory until it doesn't hurt as much, but if the person still walks away believing they deserved what happened or that the world is entirely dangerous, they're going to relapse into old patterns. I've seen this repeatedly. The treatment looks like it's working because the flashbacks decrease and the anxiety drops, but six months later the person is back in the same place because the core beliefs never shifted. Another nuance that beginners miss is the difference between processing avoidance and everyday avoidance. In TF-CBT, you're specifically targeting trauma-related avoidance, which means things like avoiding certain places, people, or conversations that remind them of the event. But some clients conflate that with general life avoidance, and if you push the exposure too aggressively on the wrong targets, you waste sessions and damage the therapeutic alliance. I once worked with a veteran who was avoiding all crowded places. We were spending three sessions on this before I realized the crowded places weren't really trauma-related triggers. They were more about social anxiety that came from a separate issue. We redirected the exposure to actual trauma cues instead, and the progress became measurable within a couple weeks.
The evidence base is solid for PTSD and acute trauma. Meta-analyses show moderate to large effect sizes, particularly when compared to waitlist controls. But the research also shows that TF-CBT doesn't work well for everyone. People with significant dissociative disorders, active substance dependence, or untreated personality disorders tend to have much higher dropout rates. I'd say roughly 15 to 20 percent of my adult cases dropped out before finishing the narrative phase, and in most of those cases, it wasn't because the therapy didn't help. It was because the preparation phase wasn't long enough for their specific situation. One thing to keep in mind is that TF-CBT is not the same thing as EMDR, which people often confuse. EMDR uses bilateral stimulation and has its own set of protocols. TF-CBT is more talk-based with deliberate cognitive and behavioral components. They overlap in some areas but the mechanisms are different. If someone asks you which is better, the honest answer is that it depends on the person and the type of trauma. Complex developmental trauma sometimes responds better to a phased approach where stabilization takes months before any trauma processing begins. TF-CBT can be adapted for that, but you have to be willing to stretch the model beyond its standard timeline. The main downsides are straightforward. It requires a trained therapist. Not every CBT provider is trained in the trauma-specific protocols. The model is fairly structured, which means it can feel rigid if the therapist isn't flexible enough to adjust pacing. And it's not appropriate for people who aren't in a stable enough place to tolerate exposure work. If someone is currently in an unsafe living situation or actively using substances, starting TF-CBT is usually a mistake. Stabilize first, process later.
Get the Full Details

If you're looking for resources on TF-CBT for adults, the TFCBT.org website has the training and certification information. The original manual by Judith Cohen, Anthony Mannarino, and Esther Deblinger covers the child and adolescent model in detail, but there are adapted versions and supplementary materials for adult populations published in clinical journals. The National Center for PTSD also has consumer-facing materials that explain the treatment in plain language if you're trying to decide whether it's the right fit.