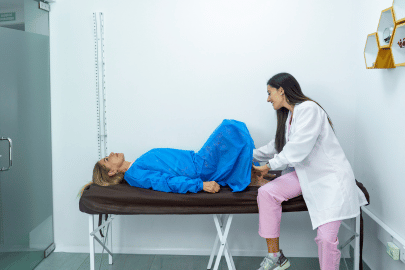
Understanding the Lithotomy Position in Clinical Practice
The standard position for a pelvic exam is the dorsal lithotomy position, and I have spent over a decade watching it get done right and wrong. The patient lies on their back with legs elevated and supported by stirrups, thighs flexed and abducted. It is what most people picture when they think of a gynecological exam. But there is a lot more nuance to it than simply laying someone down and going to town. The lithotomy position has been the default for centuries, but it is not the only option, and in some cases it is actively the wrong choice. I remember a patient in my third year of practice who had severe pelvic floor hypertonicity. Every time we attempted the standard lithotomy position, she went into such significant guarding that we couldn't visualize anything. We tried adjusting the stirrups, lowering the footboards, giving her more time — nothing worked until we switched to the left lateral decubitus position. She lay on her side with the top knee drawn up, and suddenly the exam became possible. That was a hard lesson in flexibility. The anatomy in lithotomy is straightforward. The bladder is dependent, which helps with ultrasound visualization during transvaginal work. The perineum is accessible. The cervix sits at a predictable angle. But here is what beginners miss: the angle of the cervix changes dramatically based on how far apart the stirrups are positioned. Wide leg abduction tilts the pelvis and can actually make the cervix point more posteriorly, which catches people off guard. I have seen residents struggle with this repeatedly until they figured out that a more moderate leg position often gives a clearer view of the os.
There are also modifications to the standard setup that are worth knowing. The Sim's position, where the patient lies on their left side with the right leg extended, is useful for patients who cannot tolerate the supine position due to pregnancy, obesity, or cardiovascular issues. The prone jackknife position has a niche application for evaluating certain types of pelvic organ prolapse that only become apparent under different gravitational forces. I once diagnosed a stage III rectocele that was completely missed during three years of standard lithotomy exams because the prolapse only reduced when the patient was supine with legs elevated. Switching to the knee-chest position revealed it immediately. The equipment matters more than people admit. Stirrup design affects hip rotation, which affects pelvic floor tension. Heel loops can cause more discomfort and less stability than proper stirrup supports. I have found that the height of the examination table should be adjusted so that the patient's hips are at or slightly above the level of the examiner's elbows. If the table is too low, you end up hunching, and your manual palpation becomes less precise. If it is too high, the patient's legs can slip and they tense up from fear of falling. Pain management during the exam is another area where the position plays a role. The lithotomy position itself can be uncomfortable for patients with hip osteoarthritis or recent knee surgery. In those cases, placing a small pillow under the sacrum can reduce lumbar hyperextension and make the exam tolerable. I routinely ask about joint issues before positioning any patient, and I keep a selection of padded wedges and pillows at the exam table for exactly this reason.
The documentation aspect is also worth noting. When writing up the exam findings, you should always note the position used. If you performed a portion of the exam in a modified position, that should be recorded because it affects the interpretation of your findings. A cervical length measured in lithotomy may differ from one taken in a lateral position, and knowing which was used matters for clinical decision-making. I would not claim that lithotomy is the only correct approach. It is the most common, it is well studied, and for the majority of patients it is perfectly adequate. But the edge cases exist, and recognizing them early prevents unnecessary trauma and missed diagnoses. The best examiners are the ones who know when to stick with the standard and when to adapt.
Get the Full Details